



1. INTRODUCTION
Medicine has used pharmacological compounds isolated from plants to treat human disease before completely understanding their mechanism of action or the target in the body. A prime example is the use of ‘loop diuretics’ that inhibited renal reabsorption of salts and obligatory body water and as a result alleviated excessive edema (Oh and Han 2015; Shankar and Brater 2003). Physiologists have utilized a variety of these pharmacological compounds to isolate and characterize sodium (Na+), potassium (K+), and chloride (Cl−) transport across cell membranes (Ellory et al. 1990; Geck et al. 1980; Haas and Forbush 1986; Kregenow 1971). Although these compounds altered renal physiology and improved patient health, what they were targeting and how they were affecting their targets was largely unknown. Nearly a quarter century after their initial use as medicinal therapeutics, the molecular targets of these compounds was determined to be members of the cation-chloride cotransporter family (Delpire et al. 1994; Gamba et al. 1994; Gamba et al. 1993; Gillen et al. 1996; Mount et al. 1999; Payne et al. 1996; Xu et al. 1994). These membrane protein targets are referred to as the cation-chloride cotransporters because they transport Na+ and/or K+ with an obligatory Cl−. In addition, the term electroneutral is often included as an equal number of cations and anions are carried across the cell membrane per transport cycle (e.g., 1K+ and 1 Cl− for KCCs; 1 Na+ and 1 Cl− for NCC; and 1 Na+, 1K+, and 2Cl− ions for NKCCs).
The first member of the cation-chloride cotransporter family or solute carrier 12 (SLC12) family genetically identified in 1993 was the Na-Cl cotransporter (NCC) from the winter flounder (Pseudopleuronectes americanus) (Gamba et al. 1993). Soon after, molecular cloning studies identified NCC and Na-K-2Cl cotransporter isoform 2 (NKCC2) from the brown rat (Rattus norvegicus) (Gamba et al. 1994), Na-K-2Cl cotransporter isoform 1 (NKCC1) from the dogfish shark (Squalus acanthias) (Xu et al. 1994), and NKCC1 from the house mouse (Mus musculus) (Delpire et al. 1994). The identification of four sodium-independent K-Cl cotransporters (KCCs) a few years later expanded the family to seven functionally well-characterized members (Gillen et al. 1996; Mount et al. 1999; Payne et al. 1996). The addition of two orphan members (proteins of unknown function) increased the number of genes to nine (Figure 1).
Figure 1.

Phylogeny of electroneutral cation-chloride SLC12 transporters. Two functionally uncharacterized orphan members (CCC8-SLC12A9 and CCC9-SLC12A8) separate the Na+-dependent branch (left) from the Na+-independent branch (right). On the Na+-dependent side, there are one Na-Cl cotransporter: NCC (SLC12A3), and two Na-K-2Cl cotransporters: NKCC1 (SLC12A2) and NKCC2 (SLC12A1). Due to high Na+, Cl− concentrations in the extracellular versus intracellular spaces, these transporters are typically inward transport mechanisms. Na+-independent transporters are the four K-Cl cotransporters: KCC1 (SLC12A4), KCC2 (SLC12A5), KCC3 (SLC12A6) and KCC4 (SLC12A7). Due to high K+ concentration in the cytosol compared to the extracellular space, the K-Cl cotransporters typically transport ions out of the cell.
In this chapter, we will first discuss the history, physical properties, molecular effects, clinical uses, and side effects of several pharmacological compounds that target key members of the cation-chloride cotransporter family. We will add information about additional cation-chloride cotransporter modulators that are used as research tools but are not used in the clinic. We will then discuss the major structural features of these membrane transport proteins highlighting cytosolic, intramembrane, and extracellular domains. We will describe the ion binding sites and the site of inhibitor interaction.
2. DIURETIC COUMPOUNDS
2.1. Mercurial diuretics
Pharmacological treatment of fluid balance disorders during the Middle Ages was performed using mercury-containing compounds promoted diuresis. The Swiss physician and alchemist, Paracelsus, recognized in 1553 that abnormal accumulation of fluids in tissue spaces or edema was treatable by injections of mercuric chloride (Barber 1938). In 1807, Dr. James Stringham reported that during commencement of a mercurial course of treatment for a case of syphilis, his patient developed an “unusual flow of urine” with no adverse effects on the stomach or bowels (Stringham 1807). The direct action of mercurial diuretics upon the kidneys suggested a diminished reabsorptive power of the renal tubular epithelium. Physicians continued using modified forms of mercury to negate toxic side effects while improving their diuretic action (Barber 1938). Addition of acid producing salts like ammonium chloride, calcium chloride, or ammonium nitrate considerably enhanced the diuretic effects of mercury due to increased excretion of sodium and potassium (and obligatory water) from tissue spaces (Barber 1938). Expansion of the physician’s diuretic armamentarium beyond mercurials did not occur until the middle of the 20th century and mercury-containing compounds have no role in the medical management of fluid balance today. High efficacy combined with low cost has resulted in the World Health Organization identifying multiple modern diuretics as “essential medicines” (https://list.essentialmeds.org/). An overview of the members of the modern diuretic class that target cation chloride cotransporters is the subject of this section.
2.2. Thiazide-type diuretics
The thiazide-type diuretics are a class of non-mercurial, sulfa-containing organic molecules based on the structure of benzothiadiazine discovered in the 1950s (Keyes and Berlacher 1958). Chlorothiazide was the first orally bioavailable member of this family shown to be clinically useful. Its administration increased excretion of sodium and chloride with minimal bicarbonate wasting. This diuretic class has since become one of the most widely prescribed medications in the world as it is used to treat some of the most prevalent medical conditions including hypertension and edema.
2.2.1. Mechanism of action of thiazide-type diuretics
Thiazide diuretics inhibit the Na-Cl cotransporter (NCC) along the distal convoluted tubule (DCT) of the kidney, which is responsible for reabsorbing 5–10% of the filtered Na load. Thiazides are highly protein bound (some compounds >98% bound), which limits their glomerular filtration. Therefore, their efficacy depends on secretion by the proximal tubule via organic anion cotransporters (OATs). Once secreted into the lumen of the nephron, thiazides are delivered downstream to the DCT where they bind to and inhibit NCC along the apical membrane of epithelial cells. Normally, Na reabsorbed by the DCT via NCC is then pumped into the renal interstitium by the basolateral Na+/K+ ATPase. The trans-epithelial sodium concentration gradient created by this process promotes the reabsorption of luminal water (Subramanya and Ellison 2014). A recently reported structure of NCC bound to polythiazide based on cryo-electron microscopy data revealed the specific binding pocket and the residues that interact with the compound (see below).
2.2.2. Clinical uses of thiazide-type diuretics
Thiazides are used primarily as an anti-hypertension agent for the control of elevated blood pressure and are considered a first-line medication (Chobanian et al. 2003). Thiazides are often combined with angiotensin-converting enzyme (ACE) inhibitors, angiotensin II receptor blockers (ARBs), or calcium channel blockers (CCBs) to treat hypertension (Nichols et al. 2022). Their diuretic activity also makes thiazides useful in the treatment fluid retention, known clinically as edema. Additionally, thiazides cause urinary calcium retention making them clinically useful for the treatment of calcium-containing kidney stones. These common uses are summarized below:
- Essential hypertension
- Refractory edema
- Calcium-containing kidney stones (nephrolithiasis)
2.2.3. Side effects of thiazide-type diuretics
Dysregulated electrolyte balance is the most common side effect of thiazide diuretics with the most common finding being low blood sodium levels (hyponatremia). Low potassium in the blood (hypokalemia), low chloride (hypochloremia), high bicarbonate (alkalemia), high uric acid (hyperuricemia), low magnesium (hypomagnesemia), and high calcium (hypercalcemia) are also observed side effects. Because these are blood pressure-lowering diuretics, low blood pressure and dehydration can occur. Other common side effects include metabolic derangements such as increased glucose, cholesterol, and triglyceride levels in the blood. Because of this, thiazide-type diuretics can increase the occurrence of the metabolic syndrome and diabetes. Muscle weakness and cramping can be observed.
2.2.4. Commonly used thiazide-type diuretics
2.2.4.1. HYDROCHLOROTHIAZIDE
A hydrogenated derivative of chlorothiazide (Figure 2), hydrochlorothiazide (HCTZ), exhibited a greater potency on a weight-for-weight basis with prolonged activity which reduced dosage and administration frequency (Platts 1959). The United States Food and Drug Administration approved HCTZ for clinical use in 1959.
Figure 2.

Properties and structure of hydrochlorothiazide (Compound CID: 3639).
HCTZ is a benzothiadiazine with a chloride group substituted at carbon position 6 and a sulfonamide group substituted at position 7. HCTZ is a nearly white, odorless, crystalline powder that is slightly soluble in water, soluble in ethanol, acetone, dilute ammonia, and freely soluble in sodium hydroxide (see Pubchem CID: 3639). HCTZ can be synthesized either by combining paraformaldehyde with 5-chloro-2,4-disulfamoylaniline in non-aqueous media or combining formaldehyde with 6-chloro-7-sulfamoyl-2H-1,2,4-benzothiadizine-1,1-dioxide in aqueous alkaline solution (Deppeler 1981).
2.2.4.2. METOLAZONE
Metolazone (Figure 3) was first synthesized in the 1960s and early tests in patients occurred in the early 1970s. It has become the most widely used thiazide-type diuretic to be used in conjunction with loop diuretics in the treatment of refractory edema, although clinical evidence that suggests it is more effective in this setting compared with other thiazide-type diuretics is lacking. It was approved for the treatment of edema by the FDA in 1973.
Figure 3.

Properties and structure of metolazone (Compound CID: 4170).
Metolazone is technically not a thiazide because it is not a substituted bezothiadiazine. Because it also acts on NCC with similar effects as thiazides it is considered a thiazide-type diuretic. It is a quinazoline-based sulfonamide with additional methyl, 2-tolyl, sulfamyl, and chloro substituents at carbon positions 2, 3, 6, and 7 respectively. Metolazone is a long acting, quinazoline-based sulfonamide thiazide-like diuretic. Metolazone is 10 times more potent than quinethazone (Belair et al. 1972).
2.2.4.3. INDAPAMIDE
Indapamide (Figure 4) was first patented in the 1960s and approved by the FDA in the 1970s. It is not as widely used as other thiazide-like diuretics, but its mechanism of action and pharmacological effects are similar.
Figure 4.

Properties and structure of indapamide (Compound CID: 3702).
Indapamide is also a thiazide-like diuretic. It is a sulfonamide formed by condensation of the carboxylic group of 4-chloro-3-sulfamoylbenzoic acid with the amino group of 2-methyl-2,3-dihydro-1H-indol-1-amine. Indapamide is characterized by both a methylindoline and a sulfamoyl chlorobenzamide functional group, with the former being largely responsible for the molecule’s lipid solubility.
2.3. Loop diuretics
Loop diuretics have many similarities with thiazide-type diuretics. They are also a class of non-mercurial, sulfa-containing organic molecules, and one of the most widely prescribed medications in the world. They are a cornerstone of the treatment of edema in patients with dysregulated fluid balance, including those with heart failure, kidney disease, and liver disease among others. Furosemide was the first to be approved by the FDA in 1966 and their administration results in a potent diuresis, natriuresis, and kaliuresis.
2.3.1. Mechanism of action of loop diuretics
Loop diuretics are named for the primary site at which they act clinically. They bind to and inhibit the sodium potassium 2 chloride cotransporter (NKCC2), which is expressed along the thick ascending limb (TAL) of Henle’s loop in the kidney. Because the TAL is responsible for reabsorption of 25% of the filtered sodium load, compared with just 5–10% reabsorbed along the DCT, loop diuretics inhibit a greater proportion of reabsorbed sodium than thiazides. Because of this they are said to have a “higher diuretic ceiling”. NKCC2 blockade results in a diuresis, natriuresis, kaliuresis, and chloruresis. Like thiazide-type diuretics, they are highly protein bound and require secretion along the proximal tubule via organic anion transporters. Once in the lumen, they are delivered downstream where they bind to and inhibit NKCC2. Primary inhibition of NKCC2 gives rise to the increased Na, K, and Cl excretion, but also secondarily promotes calcium and magnesium excretion give the important role of the TAL in divalent cation reabsorption. Furthermore, the importance of NKCC2 and the TAL in the generation of a concentrated urine via establishing an osmotic gradient in the renal medulla underlies the potent diuresis that occurs with NKCC2 blockade. Loop diuretics also inhibit the structurally similar NKCC1, which is more widely expressed throughout the body.
2.3.2. Clinical uses of loop diuretics
Unlike thiazides, loops are not a first line agent in the treatment of hypertension. They are less potent antihypertensive agents than thiazides despite the TAL reabsorbing a greater portion of the filtered sodium load than the DCT. While the reason for this is not entirely clear, it is thought the longer duration of action of several thiazides and the ability of the DCT to compensate for TAL inhibition contribute. The primary use of loop diuretics is in the treatment of edema most commonly in patients with heart failure, kidney disease, and liver failure. Because nephron segments more distal to the TAL can increase their electrolyte reabsorptive functions to compensate for NKCC2 inhibition, loops are often combined clinically with diuretics of other classes, including thiazides, for a sustained effect. Loop diuretics are also used for the treatment of hyperkalemia and hypercalcemia because of their kaliuretic and calciuretic effects. While they are not first-line antihypertensive agents, loop diuretics are used as adjunctive agents for difficult-to-treat hypertension, particularly in the setting of chronic kidney disease. They are also used to aid in diuresis when excess fluid is present in the brain and lungs. These common uses are summarized below:
- Edema
- Hyperkalemia
- Hypercalcemia
- Hypertension (in patients with chronic kidney disease. Not a first line agent)
- Pulmonary and cerebral edema
2.3.3. Side effects of loop diuretics
The most common side effects of loop diuretics include signs and symptoms associated with high dose loop diuretic treatment. These include dehydration, low blood pressure, and electrolyte imbalance including low blood sodium (hyponatremia), blood potassium (hypokalemia), low chloride (hypochloremia), high bicarbonate (alkalemia), low calcium (hypocalcemia), and high uric acid (hyperuricemia). Elevated uric acid levels may precipitate gout flares. Reports of ototoxicity have been reported at very high levels, likely because of NKCC1 inhibition in the inner ear.
2.3.4. Commonly used loop diuretics
2.3.4.1. FUROSEMIDE
Furosemide (Figure 5) was discovered in 1964. It is a potent sulfamoylanthranilic acid derivative. It has highly variable orally bioavailability (often cited at 10–90%) but remains a commonly prescribed loop diuretic via both oral and intravenous delivery methods.
Figure 5.

Properties and structure of furosemide (Compound CID: 3440).
Furosemide is a 4-chlorobenzoic acid with a (furan-2-ylmethyl) amino and a halogenated sulfamoyl benzene group substituted at carbon positions 2 and 5 respectively.
2.3.4.2. BUMETANIDE
Bumentanide (Figure 6) is also a potent sulfamoylanthranilic acid derivative. It was originally patented in 1968 and initially used medically in 1972. It is 40 times more potent than furosemide.
Figure 6.

Properties and structure of bumetanide (Compound CID: 2471).
Bumetanide is a 4-phenoxybenzoic acid with 2 six-carbon rings connected by an oxygen and a carbon with a single and double bonded oxygen or phenoxy group at carbon position 1. Hydrogens orthogonal to the phenoxy group are substituted with a NHC4 and an SO2NH2 at carbon positions 3 and 5, respectively.
Note that bumetanide has received attention from clinicians treating pediatric patients with neurodevelopmental disorders, such as autism spectrum disorders, and patients with Alzheimer’s disease (Delpire and Ben-Ari 2022). Considering that NKCC1 plays a significant role in GABA depolarization in the immature brain (Dzhala et al. 2005), it is not surprising that the transporter is involved in neurodevelopmental disorders. More unexpected is the fact that bumetanide, which is not readily reaching peripheral tissues as it binds tightly to serum proteins (Kim and Lee 2001; Walker et al. 1989) often improves neurological symptoms. This is the case for Down syndrome (Gharaylou et al. 2023; Raveendran et al. 2020), autism (Fernell et al. 2021; Hadjikhani et al. 2018; Hadjikhani et al. 2015; Lemonnier et al. 2017; Li et al. 2022; van Andel et al. 2020), schizophrenia (Lemonnier et al. 2016; Rahmanzadeh et al. 2017). The fact that an inhibitor of NKCC1 improves symptoms seems to indicate that an excessive NKCC1 activity is promoting these symptoms. This has been confirmed independently using an anti-NKCC1 therapy in a mouse model of Down-syndrome (Parrini et al. 2021). In addition to neurodevelopmental disorders, bumetanide also attenuates neuropathic pain (Zarepour et al. 2020) and might also improves symptoms in Parkinson disease (Damier et al. 2016). Thus, without having a full understanding of bumetanide bioavailability in the brain and periphery, evidence is accumulating implicating bumetanide in a variety of neurological disorders (Delpire and Ben-Ari 2022).
2.3.4.3. TORSEMIDE
Torsemide (Figure 7) is twice as potent as furosemide and is only administered orally. It is a long-acting diuretic and is dosed once per day. It was approved by the FDA in 1993.
Figure 7.
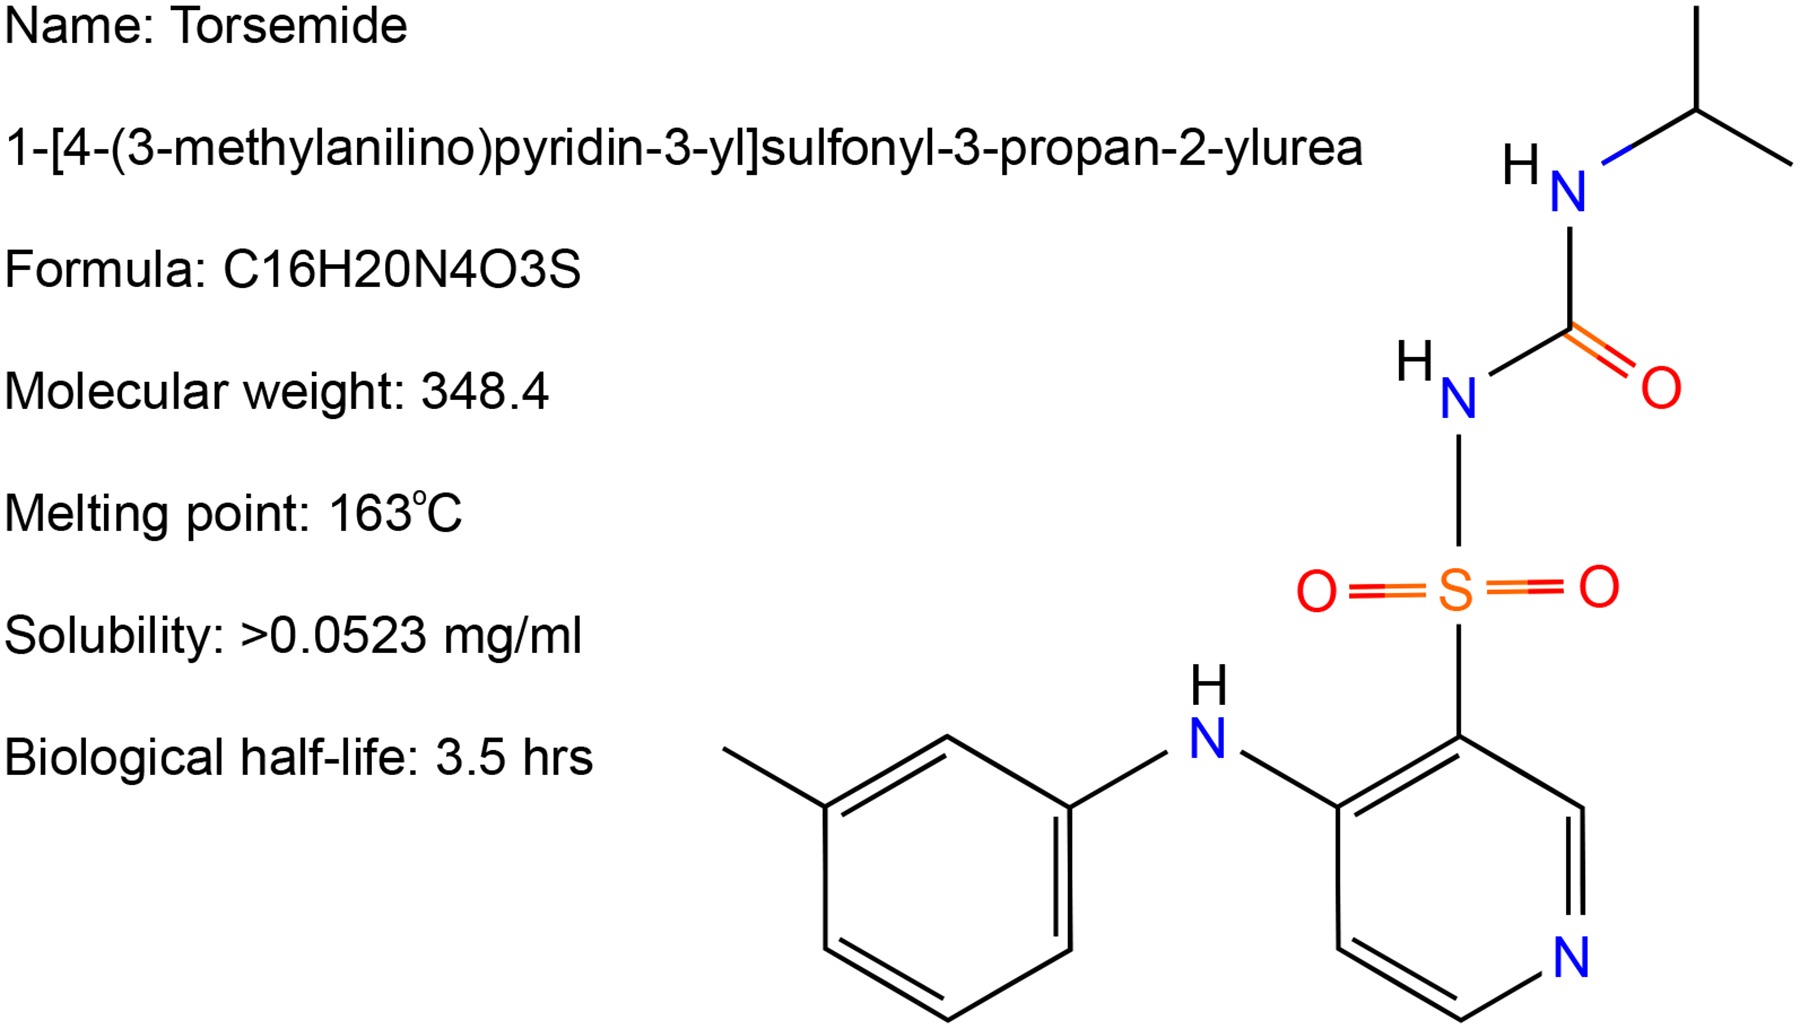
Properties and structure of torsemide (Compound CID: 41781).
Torsemide is an N-sulfonylurea obtained by formal condensation of [(3-methylphenyl)amino]pyridine-3-sulfonic acid with the free amino group of N-isopropylurea. It has a role as a loop diuretic and an antihypertensive agent. It is a N-sulfonylurea, an aminopyridine and a secondary amino compound. It is functionally related to a 4-aminopyridine.
2.3.4.4. ETHACRYNIC ACID
Ethacrynic (Figure 8) acid is a less commonly used loop diuretic. It is an aromatic ether that is phenoxyacetic acid in which the phenyl ring is substituted by chlorines at positions 2 and 3, and by a 2-methylidenebutanoyl group at position 4. While its effects are like other diuretics in this class, ethacrynic acid does not contain a sulfa group. Therefore, it is most prescribed for patients that have an allergy (or hypersensitivity) to sulfa-containing drugs.
Figure 8.

Properties and structure of ethacrynic acid (Compound CID: 3278).
3. OTHER MODULATORS OF SCL12 TRANSPORTERS
3.1. Inhibitors of K-Cl cotransporters
The loop diuretic furosemide (Figure 5) was key in the characterization of the K-Cl cotransporter as a distinct transport unit in the plasma membrane of red blood cells. Indeed, Clive Ellory (Cambridge, England) reported a swelling-activated, Cl-sensitive K+ leak in human red cells that was inhibited by the addition of furosemide (Dunham et al. 1980). Concomitantly, Peter Lauf at Duke University (Durham, North Carolina) described a N-ethylmaleimide-stimulated Cl-dependent, furosemide-inhibitable, K+ efflux in sheep red blood cells (Lauf and Theg 1980). Ellory used 1 mM furosemide in his study, a concentration that is far greater than required to inhibit the Na-K-2Cl cotransporter. In his study dedicated to furosemide inhibition of thiol-dependent passive K-Cl transport in sheep red blood cells, Lauf estimated the EC50 to be in the order of 10–50 μM (Lauf 1984). This affinity was far greater than the 600 μM EC50 we measured for KCC2 heterologously expressed in HEK293 cells (Delpire et al. 2009) or the 1 mM, or higher, reported in human red blood cells (Garay et al. 1988). Irrespective of the actual value, furosemide is 2–3 order of magnitude less potent in inhibiting the K-Cl cotransporters than the Na-K-2Cl cotransporters.
The binding of furosemide to red blood cell KCC seems to require both the presence of external Cl− and external K+ (Lauf 1984). Does it mean that the binding of the ions on the outside greatly increases the affinity of the diuretic? This will be discussed below in the section covering the structure of the cotransporter. Note that even more puzzling was the observation that the furosemide binding was also somewhat dependent upon external Na+. Furosemide inhibition of K+ efflux was greater in the presence of external NaCl versus C5H14NOCl. (Lauf 1984). Because furosemide and bumetanide taken orally end up primarily bound to albumin in the blood (Kim and Lee 2001; Walker et al. 1989) and the affinity of the loop diuretics for the cotransporters is in the sub millimolar range, it is unlikely that loop diuretics have secondary effects on K-Cl cotransporters in tissues.
In 1988, compound 2-[(2-butyl-6,7-dichloro-2-cyclopentyl-1-oxo-3H-inden-5-yl)oxy]acetic acid, a [(dihydroindenyl)oxy]alkanoic acid, simply named DIOA (Figure 9), was identified as the first potent inhibitor of NEM-stimulated or swelling-stimulated K+ efflux in human red blood cells (Garay et al. 1988). The IC50 affinity was measured around 10 μM (10−5M). The effect of the drug was modified by manipulating the concentration of external Cl−. It was shown that at low external Cl− concentrations, DIOA stimulated the K+ efflux, whereas at increasing Cl− concentrations the efflux was inhibited by the drug. As with furosemide, this suggest that DIOA binding is affected by the presence of Cl− at its binding site. Twenty years later, we conducted a large screen of ~230,000 compounds on KCC2-mediated Tl+ uptake in HEK293 cells (Delpire et al. 2009). Thallium is an element with oxidation states of +1 and +3, but the most oxidation state being +1. As Tl+ is carried across the plasma membrane through many transporters: K+ channels, the Na+/K+ pump, and cation-chloride cotransporters, the cation is likely transported at the K+ binding site. Membrane-penetrant thallium-sensitive fluorescent dyes (BTC, fluozin-2, Thallos) can then be used to assay specific transport mechanisms in cells. Using this approach, we identified VU0240511 (Figure 10) as a potent inhibitor of KCC2, as its IC50 was measured at 560 nM (Delpire et al. 2009). Limited structure activity relationship study was conducted revealing compound VU0250511 (N-Me amide congener at position 4 of the thiazole ring) with identical potency, whereas a N-cyclopropyl amide at the same position (VU ) increased the compound potency by another 10-fold (61 nM, (Delpire et al. 2012)). Importantly, moving a methyl group from position 2 to position 1 on the thiazol group eliminated inhibition. Thus, chemical manipulation of the original hit could improve, worsen, or even eliminate the inhibitory properties of VU0240511 towards KCC2. Although no data with KCC3 were shown in the original paper, we reported as a note added in proof that VU0240511 was able to inhibit the K-Cl cotransporter-3.
Figure 9.

Properties and structure of DIOA (Compound CID: 5017).
Figure 10.

Properties and structure of VU0255011 (Compound CID: 25067404) and analogues. Groups were modified on the thiazole ring. As shown by a red arrow, the original hit from the screen had a secondary amide instead of a tertiary N-Me amide. As shown by the second red arrow, the structure of an inactive compound with the 4-methyl group moved to a different position. Finally substituting the secondary amide into a N-cyclopropyl amide resulted in compound VU046271 with higher potency.
3.2. Activators of K-Cl cotransporters
As mentioned earlier, the original functional characterization of the K-Cl cotransporter was founded on a volume-stimulated or N-ethylmaleimide-stimulated, Cl− sensitive passive K+ flux. The original paper showing the NEM effect report an 8-fold stimulation of transport (Lauf and Theg 1980). Whether NEM (Figure 11) affected the transporter protein directly or indirectly was debated for quite some time, but today’s consensus is that the target is a kinase and not the transporter itself. Evidence is based on the following observations: (1) as KCCs and NKCCs have opposite responses to cell swelling and cell shrinkage (KCC is activated by cell swelling and inhibited by cell shrinkage, whereas NKCC is activated by cell shrinkage), the two transporters demonstrate opposite responses to phosphatase inhibitors: inhibition for KCC (Jennings and Schultz 1991; Kaji and Tsukitani 1991; Orringer et al. 1991; Parker et al. 1991; Sachs and Martin 1993), whereas activation for NKCC (Kurihara et al. 2002; Liedtke et al. 2005; Palfrey and Pewitt 1993); (2) Similarly, NEM exerts opposite effect on KCC (stimulation) and NKCC1 (inhibition, (Palfrey and Leung 1993; Zhang et al. 2020)); (3) NEM inhibits autophosphorylation of the kinases that regulate KCC and NKCC1 (Gagnon et al. 2006). It might be useful to add that exposure of red blood cells to the divalent ionophore A23187 also stimulates Cl-dependent K+ efflux in sheep red blood cells and this effect is reversed by the addition of manganese >> calcium > magnesium still in the presence of A23187. This activation is also related to the kinase phosphorylating the transporter as we also demonstrated with recombinant protein that SPAK autophosphorylation was stimulated to a far greater extend by manganese compared to magnesium (Gagnon et al. 2006).
Figure 11.

Properties and structure of N-ethylmaleimide (Compound CID: 4362).
Using high throughput screening with the Cl− sensitive fluorescent dye SuperChlomeleon and a targeted library of ~23,000 compounds, we recently identified compounds stimulating KCC2-mediated Cl− efflux (Prael Iii et al. 2022). The Cl− sensor was genetically engineered in HEK293 cells. Intracellular Cl− quenches the fluorescent signal generated by the yellow fluorescent protein and when KCC2 is activated, the intracellular concentration drops leading to an increase in fluorescence. We isolated VU0500469 (Figure 12) as an activator of KCC2 function. The activation observed with the Cl− sensitive dye was reproduced with the Tl+ assay and the radiolabeled Rb+ assay, and was prevented with the KCC-specific inhibitor, ML077. To assess the biological usefulness of the compound, VU0500469 was applied to high-density neuronal-glial rat cortical cultures undergoing synchronous Ca2+ oscillations and a dose-dependent decrease in oscillations was observed. This effect was specific as the use of a closely related analog with negligible activity on KCC2 failed to affect the Ca2+ oscillation rate (Prael Iii et al. 2022).
Figure 12.
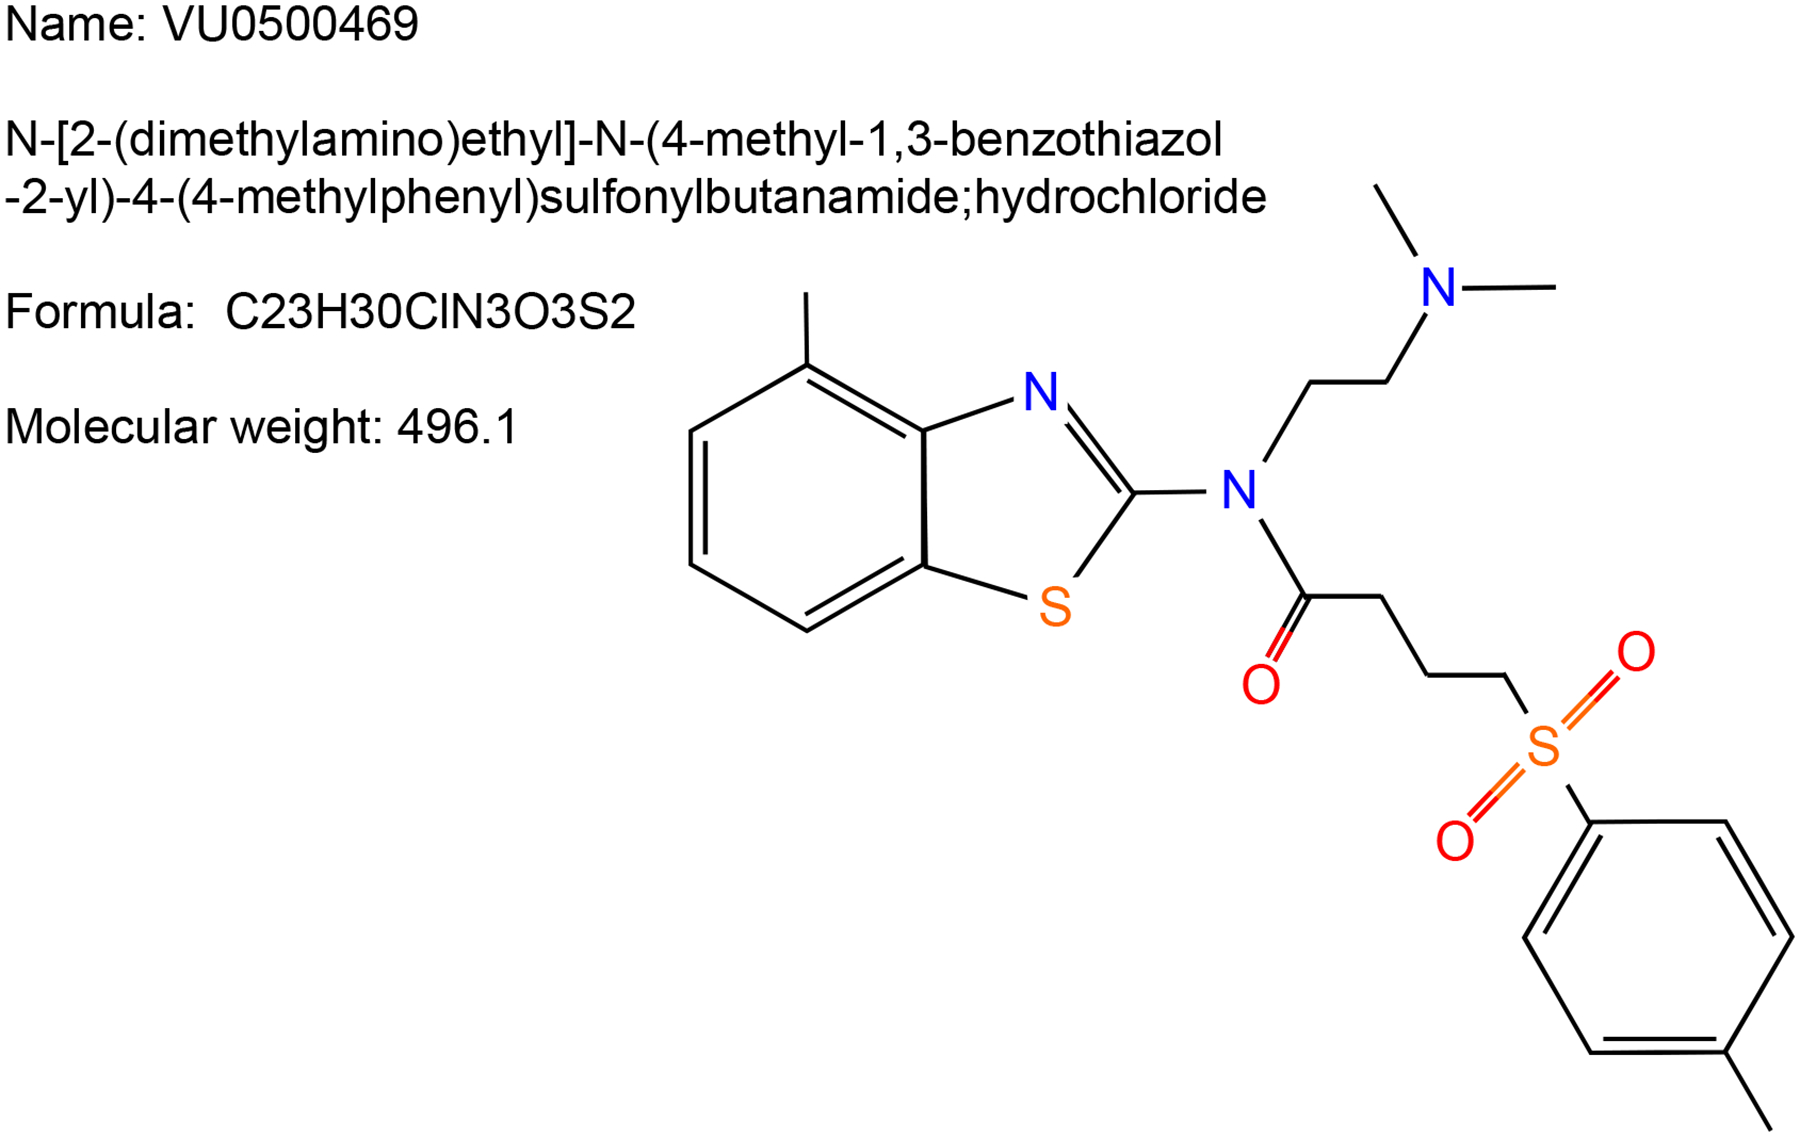
Properties and structure of VU-500469 (Compound CID: 18585704).
4. STRUCTURES OF SLC12 TRANSPORTERS
Kyte-Doolittle hydropathy analysis of the primary amino acid sequence of NKCC1 predicted twelve transmembrane domains with cytosolic amino- and carboxyl-termini (Delpire et al. 1994; Xu et al. 1994). The twelve transmembrane domains of the electroneutral cation-chloride cotransporters are organized into three structural groups represented by TMD1–5, TMD6–10, and TMD11 plus TMD12. Transmembrane domains 6–10 are an inverted ‘repeat’ of TMD1–5 (Figure 13A). This structure is highly conserved, and this arrangement follows a pattern shared with members of a much larger family of proteins: the amino acid-polyamine-organocation (APC) transporter superfamily (Wong et al. 2012). The repeat and inversion of the first two structural groups presumably occurred early in prokaryotes and first observed in the crystal structure of the prokaryotic Aquifex aeolicus LeuT structure (Yamashita et al. 2005). Indeed, this 5 + 5 configuration is conserved by most solute carriers of the APC superfamily and still exists in the human cation-chloride cotransporters among the corresponding transmembrane domains within the two pentamers (e.g., TMD2 vs. TMD7 and TMD3 vs. TMD8, as shown in Figure 13B).
Figure 13.

The secondary structure of cation-chloride cotransporters follows the general pattern of the amino acid-polyamine-organocation (APC) superfamily. A. The transmembrane core is composed of an inverted repeat of five transmembrane domains (I – V and VI – X) followed by TMD11 and TMD12. TMD1 and TMD6 helices are disrupted in the middle by a linker, and TMD3 and TMD8 are tilted and longer helices, as they traverse a longer distance in the lipid bilayer. B. Alignment of TMD2-TMD7 and TMB3-TMD8 showing some degree of conservation.
Before we describe the features constituting the ion binding sites, we will review key structural features of the cotransporters starting with the dimer, followed by the flexible amino terminus, the extracellular domain, and the highly structured carboxyl-terminus. When useful, we will contrast the structure of NKCC1 with the structure of the K-Cl cotransporters.
4.1. The dimer
Generation of the first antibodies against the cation-chloride cotransporters produced bands at the expected sizes for glycosylated proteins by Western blot analysis. Interestingly, when the samples were not fully denatured or fully reduced, additional bands consistent with protein dimers were also observed (Kaplan et al. 1996). In 2000, James Turner from the National Institute of Dental and Craniofacial Research demonstrated that the functional unit of NKCC1 is in fact a dimer (Moore-Hoon and Turner 2000). This feature is consistent with other members of the APC transporter superfamily and confirmed with the cryo-EM structures of the cotransporter (Chew et al. 2019; Moseng et al. 2022; Zhao et al. 2022a). The organization of the dimer is anti-parallel such that TMD12 is located at the back of the structure in the first monomer, while TMD12 is reversed and at the front of the structure in the second monomer (Figure 14). The smallest distance between TMD12-monomer 1 and TMD12-monomer 2 is ~ 8.5 Å and ~ 13.7 Å at the longest. We will discuss later how the binding of bumetanide to the transporter affects the configuration of the dimer. An important feature of the dimers is the ‘exchange’ of carboxyl-terminal domains (CTD) between the two monomers with the CTD of monomer 1 ‘sitting’ under the amino terminal domain (NTD) of monomer 2, whereas the CTD of monomer 2 sits under the NTD of monomer 1 (Figure 14). There are some key differences between the dimer formation in the Na+-dependent cotransporters versus Na+-independent cotransporters. In human KCC1 structure, TMD9 of one monomer is near TMD12 of the partner monomer. The distance is relatively short (10Å-13Å), and hydrophobic residues of TMD12 of one molecule interdigitate with nonpolar residues of TMD9 of the other molecule. This seals the dimer interface at the edges but leaves an interior hydrophobic cavity between the monomers (Liu et al. 2019). In contrast, in cryo-EM structures of both zebrafish and human NKCC1, TMD9 is located far away from TMD12 (30–38A for PDB#: 6npl and PDB#: 7mxo) and there is no transmembrane domain interaction between the two monomers.
Figure 14.

Structure of NKCC1 as a cation-chloride cotransporter representative. A. Cartoon (left) and surface(right) representation of human NKCC1 (PDB: 7mxo) showing the dimer. Note the ‘exchange’ of carboxyl-termini with the C-terminus of monomer 1 (cyan) sitting under the core of monomer 2 (yellow), whereas the C-terminus of monomer 2 (orange) sits under the core of monomer 1 (green). The dimer is roughly 90–100 Å x 140 Å in size.
Structures of NCC in inward facing and in outward-facing (in complex with polythiazide) were released in early 2023 (Fan et al. 2023). Overall, the two structures are similar to those of NKCC1 and of the four K-Cl cotransporters. The functional unit is a dimer and as for the transporters already described, the inward-facing configuration is stabilized by a salt bridge between TMD1 Arg158 and TMD3 GluE240. Mutations of these residues into alanine severely affected cell surface expression. The data are similar to those previously published with the KCC3 E289G mutant that had deficit in cell trafficking, cell surface expression, and therefore function (Ding et al. 2013). Interestingly Arg158Leu and Arg158Gln are Gitleman syndrome mutations (Portioli et al. 2021). In the outward-facing conformation, the salt bridge is inexistent.
4.2. The amino terminus
As indicated above, hydropathy analysis predicted the amino acid termini of the Na-K-2Cl cotransporter and the K-Cl cotransporter to be within the cytosol. Antibody accessibility studies have confirmed the cytosolic localization of both the N- and C-termini of NKCC1 (Moore-Hoon and Turner 1998). Amino acid alignment of twelve NKCC1 proteins from fish to human revealed that a large portion of the amino terminus has extremely low amino acid identity, apart from two short motifs that constitute Ste20-like proline-alanine rich kinase (SPAK) binding sites (Gagnon et al. 2007a). Interestingly, and still unresolved, the second SPAK binding site overlaps with a protein phosphatase-1 (PP1) binding domain (Darman et al. 2001). The segment proximal to the first transmembrane domain is more conserved and includes several threonine and serine residues which are targets of phosphorylation (Darman and Forbush 2002). Experiments performed with a separate protein able to scaffold SPAK and PP1 revealed that the scaffolding property of the NKCC1 amino terminus is critical for kinase activation and deactivation of the cotransporter (Gagnon et al. 2007b). As none of the current crystal structures of the cation-chloride cotransporter contain the N-terminus, it is assumed that the NTD is flexible and/or disorganized such that it cannot be averaged/visualized by cryo-EM.
Recently, the Guo Laboratory (Zhejiang University School of Medicine, Hangzhou, China) were able to capture and resolve a small portion of the amino terminus of KCC2 by cryo-EM (Xie et al. 2020). The fragment consists of 27 amino acid residues that are located towards the distal end of the NTD of the cotransporter. The most likely reason for the successful capture and resolution of this fragment is that it enters the internal cavity of the protein and forms chemical bonds with residues of the carboxyl terminus. Secondary structure of the 27 amino acid fragment can be divided into three segments (Figure 15A): α-helices N1 (Val81 to Asn90; yellow) and N2 (Ser98 to Asn107; cyan), separated by a linker L12 (Tyr91 to Gly97; red). The N1 helix interacts with TMD1a and TMD5 mainly via hydrophobic interactions, whereas L12 establishes an extensive interaction network with TMD1a, TMD6b, and TMD8 via hydrogen bonds. Arg443 (TMD6b) and Arg531 (TMD8) tightly hold the peptide fragment as a lock, by forming two strong hydrogen bonds with the carbonyls of Leu94 and Pro95. In addition, the side chain of Gln96 also forms two strong hydrogen bonds with the amide groups of Ser444 and Gly445 of TMD6b. The N2 helix also contains multiple charged or polar residues that interact with the TMD. In addition, the C-terminus of KCC2 is located right under the N2 helix and displays a positive electrostatic surface that attracts the negatively charged residues Glu102 and Glu105 in N2 helix and a negative electrostatic potential via the helix dipole. Under this configuration, the domain is likely inhibitory, as it plugs the ion permeation pathway. Transport activation must then involve detachment of the peptide from the mouth of the permeation pathway and movement away from the carboxyl-terminus.
Figure 15.

A. Surface filled model of a monomer of human KCC2 transporter (PDB: 7d8z). An inhibitory amino-terminal peptide enters the cytosolic cavity of the human KCC2 transporter (PDB: 7d8z). The peptide is composed of alpha helix N1 (yellow), a L12 linker (red), and alpha helix N2 (cyan). Note the presence of cavities (black) at the base of the transmembrane domain. Sitting below the core transporter is the carboxyl-terminus of the adjacent monomer. Note the globular structure with, possibly, a hollow core (black). B. Structure of the carboxyl-terminal domain of a bacterial (Methanosarcina acetivorans) cation-chloride transporter (PDB: 3g40) showing the presence of two domains (domain I in orange and domain II in green). Each domain is composed of 5 b-sheets surrounded by 4 a-helices in so doing forming globular structures. C. Similar structure of the carboxyl-terminus of KCC2 showing that domain II is itself composed of two subdomains separated by a large unresolved (missing) peptide.
4.3. The carboxyl-terminus
In 2009, Warmuth and colleagues reported the highly organized crystal structure of the Methanosarcina acetivorans transporter carboxyl-terminal domain (CTD). This bacterial transporter is likely a prokaryotic ortholog of the Na-K-2Cl cotransporter (Warmuth et al. 2009). They observed the presence of two subdomains with similar architectures (here named I and II). These domains are formed by a series of parallel β-sheets surrounded by α-helices. In the Methanosarcina acetivorans structure, domains I and II are separated by 10 residues (Figure 15B). In the fish and human NKCC1 structures, the two domains are separated by a much longer peptide (80 residues) which is unresolved in all structures (Chew et al. 2019; Moseng et al. 2022; Zhao et al. 2022a). In the human KCC1–4 structures, the distance between domains I and II is also quite short (only 14 residues), however, domain II is further split into two subdomains separated by 150 residues in KCC2 and 100 residues in KCC3 (Figure 15C). The relevance of these differences is still unknown but likely significant as these highly organized C-terminal domains are undoubtedly involved in the function of the transporters. For instance, the large carboxyl-termini movements that were predicted by FRET studies (Monette and Forbush 2012) have been observed in cryo-EM structures, particularly while comparing the apo structure of NKCC1 with the occluded structure of the transporter in complex with pharmacological inhibitors (Moseng et al. 2022). Examination of the subdomains revealed that they form globular structures (Figure 15A). The precise function and nature of these subdomain structures are still unknown.
4.4. The extracellular domain
Per mass, the extracellular domain of K-Cl cotransporters is greater (13.6%) than the extracellular domain of NKCCs (8%). This can be visualized in Figure 16, which displays the structures of the human KCC2 transporter (panel A) in comparison to human NKCC1 (panel B). In the human KCC1 cryo-EM structure, the extracellular domains of the 2 monomers interact and form a cap on top of the transmembrane domains (Liu et al. 2019). While this configuration seems unique to KCC1, as it has not been seen in other transporters, it might constitute a possible closed conformation of the transporters.
Figure 16.

Cryo-EM structure representation of human KCC2 (A) and NKCC1 (B) transporters. Note the large extracellular domains created by extracellular loops: ECL2 (yellow) and ECL3 (pink) for hKCC2, and ECL2 (blue), ECL3 (yellow), and ECL4 (pink) for NKCC1. C. N-glycosylation sites of ECL3 (for K-Cl cotransporters) and ECL4 (for Na-[K]-Cl cotransporters). The number of residues separating the consensus sites is indicated in red. The last and first residues of TMD5, TMD6 and TMD7, TMD8 are boxed and given in red color over a yellow background.
Apart from key asparagine residues that constitute sites of N-glycosylation, the function of the extracellular domains of NCC/NKCCs and KCCs is mostly unknown. Glycosylation is critical for the proper processing of the transporters in the endoplasmic reticulum and Golgi and trafficking to the plasma membrane. The consensus site for N-glycolyslation sites is Asn-Xaa-Ser/Thr/Cys (Medzihradszky 2008). The N-glycosylation sites are located within the largest extracellular loops: ECL3 between TMD5 and TMD6 for KCCs and ECL4 between TMD7 and TMD8 for NCC/NKCCs. As seen in Figure 16C, there are 3 conserved glycosylation sites in KCC1-KCC4 (ECL3), and an additional putative site in KCC3 and KCC4. There is one highly conserved site and 1–2 additional less conserved sites NKCC1/2 and NCC (ECL4). Mutagenesis of each of the two sites into glutamine residues in NCC resulted in 50% decrease in NCC transport. Substitution of both sites resulted in 90% decrease. This decrease is due to reduced expression at the plasma membrane (Hoover et al. 2003). Similar data were obtained with the two N-glycosylation site of rat NKCC2 (Paredes et al. 2006). Interestingly, there are other features in the transporter that affect glycosylation. One example is a di-leucine like motif in the carboxyl-terminus of NKCC2. Its mutation results in impaired glycosylation and exit from the endoplasmic reticulum (Zaarour et al. 2012). In this case, since the defect occurs upstream of the Golgi, it makes sense that glycosylation and trafficking will be affected. Note that in NKCC1, when this conserved di-leucine motif is absent, the transporter traffics improperly to the apical membrane, instead of basolateral membrane (Delpire et al. 2016; Koumangoye et al. 2018). Another example is given by the salt bridge that exists between Arg307 and Glu289 in KCC3. When disrupted in a Glu289Gly mutant transporter, the core mannose residues seemed to be properly added transporter’s asparagine residues in the ER, but addition of acethylglucosamyl groups, followed by galactose and sialic acid groups in the Golgi is impaired (Ding et al. 2013). This indicate that while the N-glycosylation sites are an important component of trafficking, proper folding is also a critical step in the processing of the transporter through the ER and Golgi to the plasma membrane.
The large extracellular loops contain cysteine residues, and in some cases, their role has been addressed experimentally. In the K-Cl cotransporter, there are 4 highly conserved cysteines towards the beginning of the loop. The first one is located 7 residues from TMD5 and the others are separated by 9–20 residues. Interestingly mutation of these four cysteines eliminated KCC2 function, but maintained KCC4 function, indicating some isoform-specific differences (Hartmann et al. 2010). In the human KCC1 cryo-EM structure, Cys308 forms a disulfide bond with C323 and Cys343 forms a bond with Cys353. These two disulfide bridges stabilize the extracellular domain (Liu et al. 2019). As with KCC4, substitution of the 4 cysteine residues in ECL4 into serine residues in NKCC1 reduced transport activity by only 20% (Somasekharan et al. 2013).
4.5. The transmembrane domain and ion binding sites
Disruption by short glycine-containing loops in the middle of anti-parallel TMD1 and TMD6 (Figures 13A, 17B) is a conserved feature among the cotransporters and the amino acid transporters such as LeuT (Yamashita et al. 2005), GAT1 (Motiwala et al. 2022), and SERT (Coleman et al. 2020). The breaks in helical structures approximately halfway across the membrane bilayer expose main-chain carbonyl oxygen and nitrogen atoms for hydrogen bonding and coordination of K+, Na+ and Cl− ions (Figure 17A). Helices forming TMD3 and TMD8 are tilted and therefore longer as they need to cross a longer lipidic environment. Residues in TMD3 and TMD8 come close to the helical breaks in TMD1 and TMD6 and provide additional coordination sites for ion binding. K+ seems to be the most central ion, coordinated by five hydrogen bonds: two bonds with residues located in TMD1; two bonds with residues located in the TMD6; and an additional critical bond with a highly conserved tyrosine residue located in TMD3. The binding site is conserved between the Na-K-2Cl cotransporter (zebrafish (Chew et al. 2019) and human (Moseng et al. 2022; Zhao et al. 2022a) structures) and the K-Cl cotransporters 1 (Liu et al. 2019), 2, 3, and 4 (Chi et al. 2020; Xie et al. 2020). The binding site for Na+ is located closer to the second half of the pentamer, it forms 3 hydrogen bonds with residues in TMD8. The five residues that coordinate the binding of Na+ are not conserved in the Na+-independent K-Cl cotransporters (Liu et al. 2019). Note that the position of the Na+ cation in the NKCC1 structure is identical to the position of the Na+ at site II in the LeuT structure (Yamashita et al. 2005). In the structures of the Na-K-2Cl cotransporter and the K-Cl cotransporter densities compatible with Cl− ions were observed. The first Cl− site (SCl1) is located right above the K+ site. In fact, the presence of the K+ ion helps position Cl− at SCl1. A second Cl− site is observed lower down, coordinated by residues in TMD6 and TMD10 (Figure 17A).
Figure 17.

Location of 3 of the 4 ions in NKCC1. A. Residues in NKCC1 that form the K+ and Cl− (Cl1) binding sites. Note that the ions are located close to the discontinuity in the helices of TMD1 and TMD6. Multiple residues in TM1a, TM6a, and a highly conserved tyrosine residue in TMD3 coordinate the K+ ion. Three residues in TM1 also coordinate Cl− binding. In addition, an ionic interaction between K+ and Cl− (at Cl1) further stabilize the ions. Residues in TMD1a, TMD3, and TMD8 coordinate the Na+ binding. B. Alignment of the second transmembrane domain of the 3 NKCC2 variants: NKCC2A, NKCC2B, and NKCC2F. Position of the second transmembrane domain of NKCC1 (yellow) in relationship with the position of Na+ (indicated by an “x”). The distance between residues in TMD2 and Na+ ranges between 13Å and 17Å.
NKCC2 is the Na-K-2Cl cotransporter expressed in the thick ascending limb of Henle and macula densa in the kidney. Exon 5 is a non-unique but a mutually exclusive, small cassette exon that encodes 32 amino acids representing the entire alpha helix of transmembrane domain 2. It is triplicated leading to the formation of three variants known as NKCC2F, B, and A (Igarashi et al. 1994). Each of the three variants contain a few unique amino acid residues (Figure 17B) that confer differential Na+ binding affinities that maximize their respective cotransporter capacity relative to tubular Na+ concentrations (Gimenez and Forbush 2007). Deep in the kidney medulla where the pre-urine tubular Na+ and Cl− concentrations are high, NKCC2F has lower Na+ and Cl− affinities (e.g., 60–70 mM for Na+ and 120 mM for Cl−). In contrast, the tubular Na+ concentration in the upper portion of the thick ascending limb of Henle and the macula densa is much lower. Accordingly, NKCC2B has much higher affinities for both ions (20–25 mM for Na+ and 10–15 mM for Cl−). Curiously, TMD2 is located far away from the Cl− and Na+ binding site. The distance measured between residues of TMD2 and the residues of TMD1b, TMD3 and TMD8, are too far away for direct interactions (Figure 17B). Thus, in order for residues of TMD2 to be affecting the Na+ and Cl− binding affinities, there must be long-range conformational coupling.
While two Cl− ions are transported with the Na+ and K+ cations through NKCC1, only one Cl− is transported with K+ through KCC (Figure 18). It is therefore surprising to observe two Cl− densities in the structure of the K-Cl cotransporter (Liu et al. 2019). As only one Cl− is transported, the structural information suggests that one Cl− is bound but not released during transport. The structure of the Na-Cl cotransporter might provide insights into which Cl− is released. Again, the ion binding sites in the NCC structure are also highly conserved. All residues coordinating the K+ ions in NKCC1 and the K-Cl cotransporters are conserved in NCC, except a key tyrosine residue located within TMD3. Instead, the Tyr is substituted by His234. As there is ionic stabilization between the K+ ion and the Cl− ion at Cl− site 1 (SCl1) in the NKCC1 and KCC structures, one can speculate that in the absence of K+, there will be no binding of Cl− at SCl1. Accordingly, a density compatible with a Cl− ion was detected at SCl2 but not SCl1. (Fan et al. 2023). Thus, for K+ and Cl− influx, if the Cl− transported is the one binding at the SCl2 site, Cl− would need to access this site before K+ occupies its own site (Figure 18). This is compatible with the ordered binding determined by kinetic studies: Cl− binding first, followed by K+ (Delpire et al. 2009; Delpire and Lauf 1991a; Delpire and Lauf 1991b). For K+ and Cl− efflux, if Cl− binding at SCl1 is not released, the K+ ion can be coordinated by the Cl− ion at SCl1, but because the internal cavity is relatively large, either Cl− at SCl2 or K+ at its site can bind first (Figure 18). This is also compatible with the random nature of Cl− and K+ binding determined by the aforementioned kinetic studies (Delpire and Lauf 1991a; Delpire and Lauf 1991b).
Figure 18.

Ion binding to the three main cation-chloride cotransporters: NKCC, NCC, and KCC. While two Cl− densities are observed in NKCC (green), only one Cl− density is observed for NCC. In the absence of K+, Cl− cannot be coordinated at SCl1 (white empty circle). Two Cl− densities were however observed in the KCC structure and based on the cryo-EM structure of NCC, we hypothesize that Cl− at SCl1 (red) is not released, whereas Cl− at SCl2 (green) is transported. Based on the position of the ions and the narrow channel on the outside, for influx (left model), Cl− must bind first, followed by K+. On the other hand, since the cavity on the inside is larger, either ion can access its binding site, not restricted by the other. This model is consistent with previous kinetic studies showing strictly ordered binding of ions on the outside, while random binding on the inside.
4.6. Inward versus outward structures
Apart from the structure of NKCC1 in complex with bumetanide or furosemide (see below), all available structures of K-Cl cotransporter and of NKCC1 are inward facing or inward open structures. In this configuration, there is a salt bridge formed by a key arginine residue located in the middle of the TMD1b helix and an aspartic acid located towards the end of the TMD3 helix (Figure 19). The two residues are separated by 2.5 Å (NKCC1, PDB: 7mxo) to 3.1 Å (KCC2, PDB: 7d8z). In the outward facing structure of NKCC1 in complex with bumetanide, these residues are located farther apart (10 Å, (Zhao et al. 2022a)) 6–8 Å (Moseng et al. 2022) and no longer facing each other to form a salt bridge.
Figure 19.

Salt bridge between the NH2+ group of Arg307 in TMD1b and the O− group of the glutamic acid of Glu389 in TMD3. The distance between the groups is short: 2.5 Å in human NKCC1 (PDB: 7mxo).
4.7. Do ions move through the carboxyl-terminus?
Because the carboxyl-terminus of the cation-chloride cotransporters is composed of two globular domains containing cavities, is it possible that the permeation channel is not confined to the membrane but extends within the carboxyl-terminus. To answer the question, we utilized MOLE 2.5, a universal toolkit for rapid and fully automated identification and characterization of channels, tunnels and pores within protein structures. The PDB file of NKCC1 (7xmo) was uploaded and the software predicted a 251-Angstrom-long channel starting at the top of the extracellular loop, traversing the membrane, and extending through the carboxyl-terminus of the cotransporter (Figure 20). The narrowest points were located at the interface between the lipid bilayer and the outside environment. Whether the tunnel within the carboxyl-terminal domain fulfill any function remains to be determined.
Figure 20.

Evidence of a pore (tunnel) going through the extracellular domain, the transmembrane domain, and the carboxyl-terminus of NKCC1. The 7mxo structure stripped of its ions was uploaded to MOLEonline to run MOLE 2.5, a tool that allows rapid and fully automated identification of channels, tunnels, and pores in protein structures. This model provides evidence for possible movement of ions or water molecules through the globular carboxyl-terminus of the cotransporter.
4.8. The inhibitor binding site(s).
In vitro experiments performed in the 1980s demonstrated that bumetanide inhibition was affected by the concentration of external ions (Haas and McManus 1983; Palfrey et al. 1980). Because inhibition was maximal at saturating concentrations of Na+ and K+, Palfrey, Feit, and Greengard concluded that cations did not enter in straightforward competitive interaction with the inhibitor (Palfrey et al. 1980). At the time, they proposed the idea of a separate drug-binding site that could somehow “immobilize” the cotransporter in the membrane. In contrast, in duck red blood cells, negatively charged Cl− seemed to have more of a competitive action on bumetanide inhibition. The EC50 for bumetanide had a 3.2-fold increase in affinity (1.8 × 10⁻⁷ versus 5.6 × 10⁻⁸) when the external Cl− concentration was reduced from 100 mM to 20 mM, respectively (Haas and McManus 1983). Furthermore, cotransporters from different species exhibited differences in bumetanide affinities. For example, the bumetanide affinity of shark NKCC1 is much lower than the bumetanide affinity of human NKCC1 (Isenring and Forbush 1997; Isenring et al. 1998). As such, a series of cotransporter chimeras were constructed between shark and human NKCC1 proteins to identify ‘hot spots’ for bumetanide inhibition (Isenring and Forbush 1997; Isenring et al. 1998). In addition to residues in TMD11 and 12, specific residues in TMD2, 4, and 7 (which were shown to affect ion binding), were also involved in bumetanide affinity. Prior to cryo-EM data, with the caveat that mutagenesis might lead to long-distance effects, it was hypothesized that bumetanide sat within the permeation channel likely close to the surface, above the ion binding sites. The first structure of NKCC1 in complex with bumetanide confirmed the location of the inhibitor: within the permeation pathway, above the ion binding sites (Zhao et al. 2022a). As seen in Figure 21A, in the absence of K+, the inhibitor is coordinated by 5 hydrophobic interactions (residues Val302, Ala379, Tyr383, Pro496, Phe682) and 4 hydrogen bonds (residues Val302, Tyr383, Pro496, and Ala497). Note that residues Pro496, located in TM6, and Tyr383, located in TM3 are both part of the K+ binding site. It is unclear how the structure contained both K+ and bumetanide at the same time. When the analysis was done in the presence of K+, the ligand loses its interactions with Pro496. Recently, a second cryo-EM study provided multiple structures of NKCC1 in complex with bumetanide or furosemide with some very different observations (Moseng et al. 2022). First, the structures seemed to capture the cotransporter in distinct conformations highlighting major movements of the carboxyl-terminus and distance between monomers. Second, bumetanide was observed in the permeation pathway forming interactions with Val302, Ala378, and Pro496. The position of the inhibitor was, however, different with bonds now forming with Gly301, Met303, Val 385, and Ala675. Third, furosemide and bumetanide were also captured within a carboxyl-terminal domain pocket. Mutagenesis of residues lining this pocket led to the absence of bumetanide inhibition. Finally, when inhibitors were present, in the C-terminal pocket, the permeation pathway was collapsed, consistent with absence of NKCC1-mediated transport (Moseng et al. 2022).
Figure 21.

Two cryo-EM structures of NKCC1 in with bumetanide indicate that the inhibitor can take slightly different positions within the NKCC1 structure: as in PDB: 7smp (A) and in PDB: 7s1x (B). Note that some coordinating residues (underlined) are common in the two structures: Val302, Met303, Ala379, Val385, Pro496.
Using molecular docking, we modeled the binding of ML077 and other inhibitors to different regions of human KCC2. To this end, we wrote a python script that systematically moved the center of ML077 coordinates in the three dimensions around the cotransporter structure. At each position we attempted ligand docking to the transporter and extracted a docking score (Delpire and Guo 2020). Thus, through this process, we covered the entire volume or space within and around the transporter. Note that this approach is biased by the configuration of transporter. If the actual binding pocket is occluded in the cryo-EM structure, the site is not accessible, and the ‘in silico’ docking is unlikely to find it. Irrespective, we observed that the top model predicted ligand binding within the permeation channel (Figure 22). Interestingly, the ligand was positioned in such a way that a methyl group attached to position 4 in the thiazol ring reached towards the center of the K+ binding site. Indeed, the methyl group was located just 3.6 Å from the side chain of Tyr216 which coordinates K+ binding. This observation is consistent with known competitive inhibition existing between K+ and ML077 (Delpire et al. 2009). Also worth noting was that when the methyl group was moved from position 4 to position 5 on the thiazol ring, the docking score dropped significantly, consistent with the observation that this change eliminated the inhibitory effect of ML077. After we modeled the binding of ML077 onto the existing structure of KCC2, the cryo-EM structure of KCC1 in complex with VU0463271, a ML077 analogue, was published (Zhao et al. 2022b). As discussed above, the structure was in an outward open conformation and the inhibitor was bound closer to the surface, in the same overall location than bumetanide binding to NKCC1 (Figure 23A). This observation suggests that VU0463271 (potent inhibitor) and furosemide (weak inhibitor) of K-Cl cotransporters bind at the same location. This could be confirmed by displacing a radiolabeled furosemide with increasing concentrations of cold VU0463271. Interestingly, the pose of VU0463271 in the structure is also different than what we would have anticipated. The thiazol group does not plunge deep into the structure (towards the K+ site) as the carboxyl group of bumetanide does in NKCC1. Instead, the compound is flipped 180° and the thiazol group is located closer to the surface. This position in fact agrees with modeling of VU0463271 to the human KCC1 transporter, which indicates that modeling was possibly done to arrange the inhibitor within the structure. Seven hydrophobic interactions and a hydrogen bond coordinate the binding of the inhibitor. The residues involved are Val135 (TM1), Ala212, Tyr216, and Glu222 (TM3), Pro429 (TM6b), Leu581 and Phe585 (TM10). Note that three of the residues coordinating the VU0463271 binding are located within TM3 with Glu222 stabilizing the thiazol ring. Interestingly, Glu222 is the acidic residue that forms a salt bridge with Arg1440 in TM1b, thereby locking the outside of the ‘pore’ and stabilizing the monomer in its inward open conformation.
Figure 22.

Molecular docking of ML077 (VU0255011) with human KCC1. Note that residue Tyr216 which coordinates the binding of K+ in hKCC1 is the equivalent of Tyr383 in NKCC1, residue that also coordinates K+ binding (and possibly bumetanide binding) in the Na+-dependent transporter. Note that the binding might be biased by a structure that is an inward facing configuration and a different binding pocket could be formed when the transporter is in an outward facing configuration, i.e., similar to what is seen in the cryo-EM structure of NKCC1 in complex with bumetanide.
Figure 23.
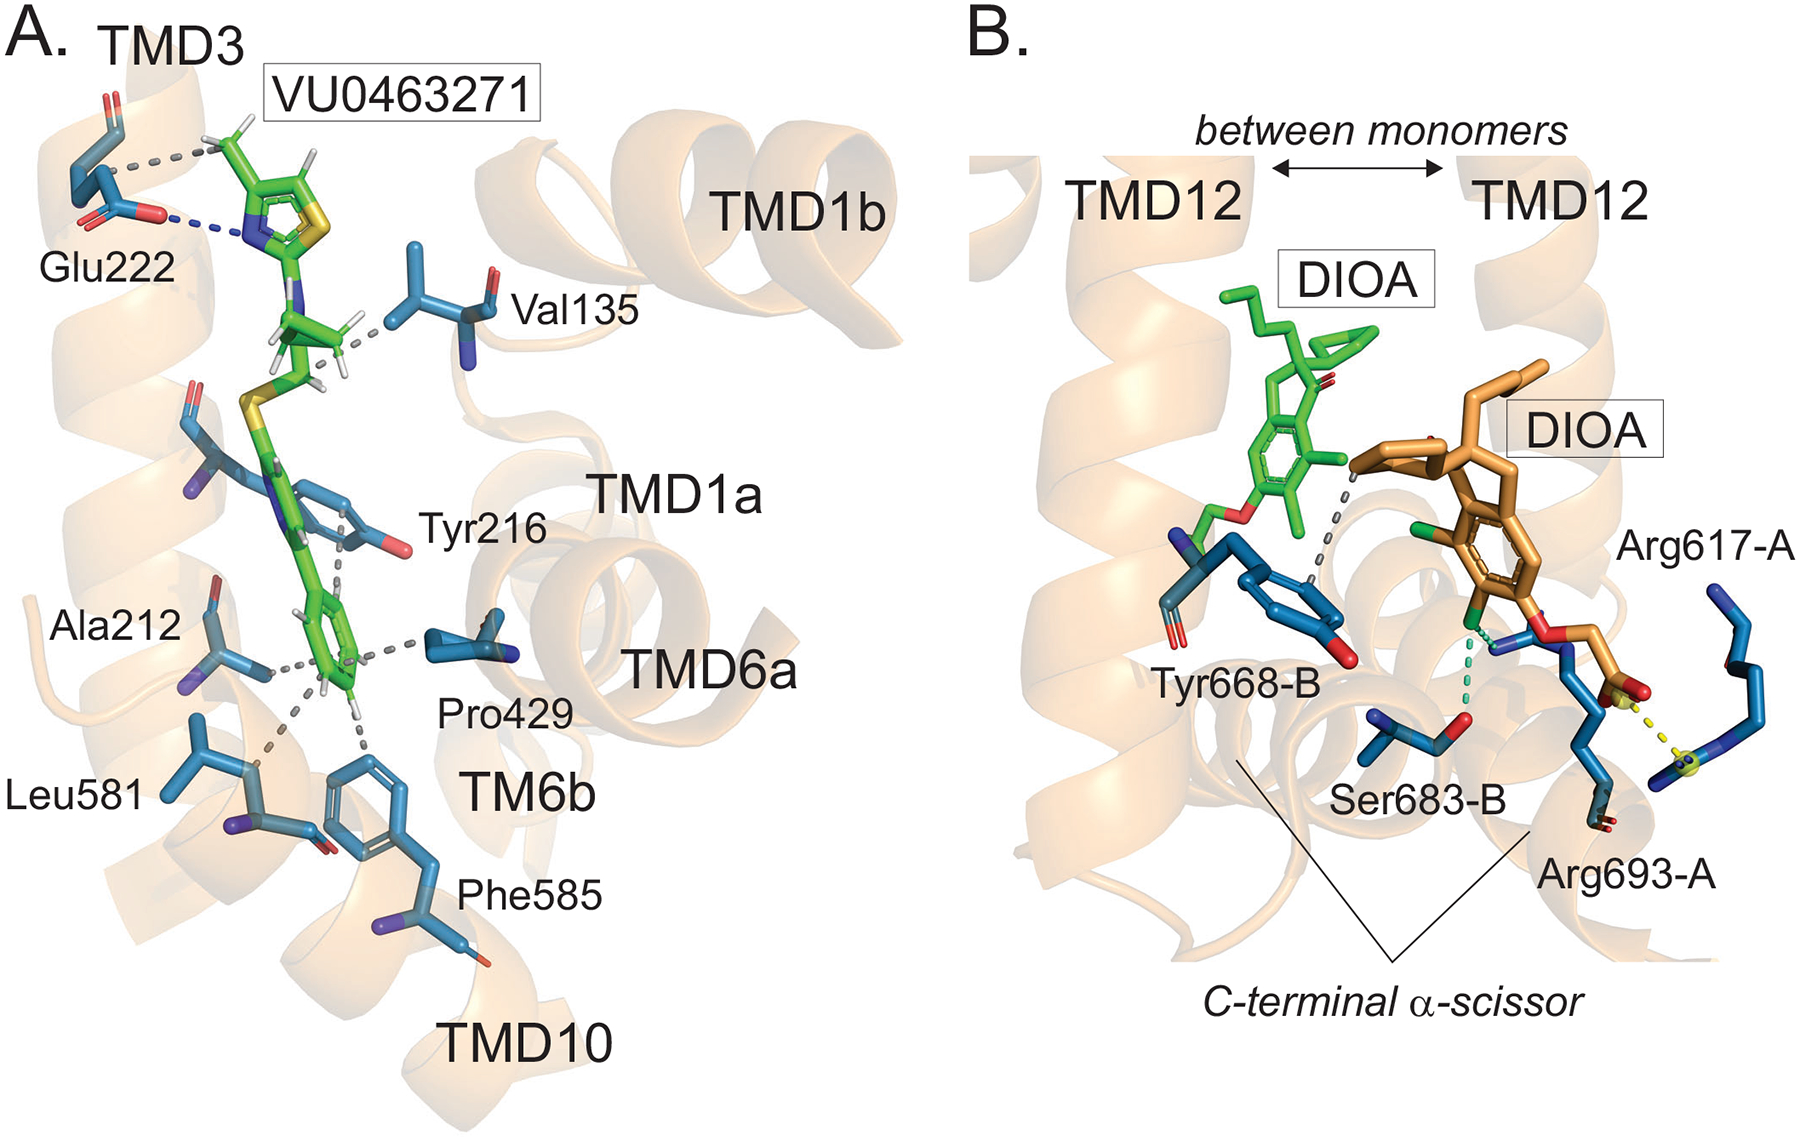
Positions of VU0463271 (A) and DIOA (B) in the cryo-EM structures of KCC1 and KCC3 demonstrate different modes of inhibition. VU0463271 is located in the external pore of the permeation channel, similar to bumetanide. While the thiazole group interacts with the glutamic acid residue responsible for locking the transporter in the inward conformation, the two aromatic rings at the opposite end enter deeper in the channel, interacting with residues in TM1, TM6, and TM10. DIOA, on the other hand, binds between the two monomers interacting with residues of both monomers. The binding of DIOA at that position likely prevents the proper movement of carboxyl-termini and transmembrane domains associated with transport.
The structures of KCC2 and KCC3 in complex with DIOA (compound shown in Figure 9) were reported in 2021 (Chi et al. 2020). Interestingly the binding occurs intracellularly between the transmembrane domains (Figure 23B). The strongest interaction involves a salt bridge between Arg617 (residue following TM10) and the carboxylate of the small molecule. One of the two Cl− in the small molecules forms bonds with Arg 693, a residue located in the intracellular α-scissor helix positioned proximal to TM12 as well as with Ser683 located on the intracellular α-scissor helix of the adjacent monomer. Finally, a hydrophobic interaction exists with Tyr668 also of the adjacent monomer. Thus, the alkanoic acid derivative seems to lock the position of the two monomers, possibly preventing a movement that is associated with transition from one configuration (e.g., inward) to another (i.e., outward).
In conclusions, compounds that for many decades were the most used medicines in the clinic target the cation-chloride cotransporters. They are the two main families of diuretics: the thiazide diuretics that target the Na-Cl cotransporter, and the loop diuretics that target the Na-K-2Cl cotransporter-2. The recent cryo-EM structures of the transporters in complex with these drugs provides novel information about mechanism of inhibition. In addition, new compounds have been discovered inhibiting or stimulating the K-Cl cotransporters. Whether any of these compounds or their analogues/derivatives will make it to the clinic is unknown. Today, they are utilized in research to probe the function of these transporters. Being a small family of just 7 functionally well-characterized members, the cation-chloride cotransporter (SLC12) family) has been a fertile ground for both drugs used in the clinic as well drugs used in research.
Transporters of the solute carrier family 12 (SLC12) carry inorganic cations such as Na+ and/or K+ alongside Cl− across the plasma membrane of cells. These tightly coupled, electroneutral, transporters are expressed in almost all tissues/organs in the body where they fulfil many critical functions. The family includes two key transporters participating in salt reabsorption in the kidney: the Na-K-2Cl cotransporter-2 (NKCC2), expressed in the loop of Henle, and the Na-Cl cotransporter (NCC), expressed in the distal convoluted tubule. NCC and NKCC2 are the targets of thiazides and “loop” diuretics, respectively, drugs that are widely used in clinical medicine to treat hypertension and edema. Bumetanide, in addition to its effect as a loop diuretic, has recently received increasing attention as a possible therapeutic agent for neurodevelopmental disorders. This chapter also describes how over the past two decades, the pharmacology of Na+-independent transporters has expanded significantly to provide novel tools for research. This work has indeed led to the identification of compounds that are 100-fold to 1000-fold more potent than furosemide, the first described inhibitor of K-Cl cotransport, and identified compounds that possibly directly stimulate the function of the K-Cl cotransporter. Finally, the recent cryo-electron microscopy revolution has begun providing answers as to where and how pharmacological agents bind to and affect the function of the transporters.
List of abbreviations
- ACE
Angiotensin-converting enzyme
- ARB
angiotensin II receptor blocker
- BTC
coumarin benzothiazole-based Ca2+ indicator
- CCB
calcium channel blocker
- CTD
carboxyl-terminal domain
- Cryo-EM
Cryo-electron microscopy
- DCT
Distal convoluted tubule
- DIDS
4,4’-Diisothiocyano-2,2’-stilbenedisulfonic acid
- DIOA
[(dihydroindenyl)oxy] alkanoic acid
- EC50
Half-maximal effective concentration
- ECL
Extracellular loop
- FDA
Food and Drug Administration (USA)
- HCTZ
hydrochlorothiazide
- HEK293
Human embryonic kidney cell line
- NKCC1
Na-K-2Cl cotransporter isoform 1
- NKCC2
Na-K-2Cl cotransporter isoform 2
- NCC
Na-Cl cotransporter
- NTD
amino terminal domain
- KCC1
K-Cl cotransporter isoform 1
- KCC2
K-Cl cotransporter isoform 2
- KCC3
K-Cl cotransporter isoform 3
- KCC4
K-Cl cotransporter isoform 4
- NEM
N-ethylmaleimide
- OAT
Organic anion transporter
- PDB
Protein data bank number
- PP1
Protein phosphatase 1
- SPAK
Ste20-like proline-alanine rich kinase
- SLC12
Solute carrier family 12
- TAL
Thick ascending limb
- TMD
Transmembrane domain
REFERENCES
- Barber HS(1938) The Mercurial Diuretics. Postgrad Med J 14: 288–294 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Belair EJ, Cohen AI, and Yelnosky J(1972) Renal excretion of metolazone, a new diuretic. Br J Pharmacol 45: 476–479 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Chew TA, Orlando BJ, Zhang J, Latorraca NR, Wang A, Hollingsworth SA, Chen DH, Dror RO, Liao M, and Feng L(2019) Structure and mechanism of the cation-chloride cotransporter NKCC1. Nature 572: 488–492 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Chi X, Li X, Chen Y, Zhang Y, Su Q, and Zhou Q(2020) Cryo-EM structures of the full-length human KCC2 and KCC3 cation-chloride cotransporters. Cell Res 31: 482–484 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Chobanian AV, Bakris GL, Black HR, Cushman WC, Green LA, Izzo JL Jr., Jones DW, Materson BJ, Oparil S, Wright JT Jr., and Roccella EJ(2003) Seventh report of the Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure. Hypertension 42: 1206–1252 [DOI] [PubMed] [Google Scholar]
- Coleman JA, Navratna V, Antermite D, Yang D, Bull JA, and Gouaux E(2020) Chemical and structural investigation of the paroxetine-human serotonin transporter complex. Elife 9: e56427. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Damier P, Hammond C, and Ben-Ari Y(2016) Bumetanide to Treat Parkinson Disease: A Report of 4 Cases. Clin Neuropharmacol 39: 57–59 [DOI] [PubMed] [Google Scholar]
- Darman RB, Flemmer A, and Forbush BI(2001) Modulation of ion transport by direct targeting of PP1 to the Na-K-Cl cotransporter. J Biol Chem 276: 34359–34362 [DOI] [PubMed] [Google Scholar]
- Darman RB and Forbush B(2002) A regulatory locus of phosphorylation in the N terminus of the Na-K-Cl cotransporter, NKCC1. J Biol Chem 277: 37542–37550 [DOI] [PubMed] [Google Scholar]
- Delpire E, Baranczak A, Waterson AG, Kim K, Kett N, Morrison RD, Daniels JS, Weaver CD, and Lindsley CW(2012) Further optimization of the neuronal K-Cl cotransporter KCC2 antagonist ML077: Development of a highly selective and more potent in vitro probe. Bioorg Med Chem Lett 22: 4532–4535 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Delpire E and Ben-Ari Y(2022) A Wholistic View of How Bumetanide Attenuates Autism Spectrum Disorders. Cells 11: 2419. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Delpire E, Days E, Mi D, Lewis M, Kim K, Lindsley C, and Weaver CD(2009) Small molecule screen identifies inhibitors of the neuronal K-Cl cotransporter KCC2. Proc Natl Acad Sci U S A 106: 5383–5388 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Delpire E and Guo J(2020) The cryo-EM structures of DrNKCC1 and hKCC1: a new milestone in the physiology of cation-chloride cotransporters. Am J Physiol Cell Physiol 318: C225–C237 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Delpire E and Lauf PK(1991a) Kinetics of Cl-dependent K fluxes in hyposmotically low K sheep erythrocytes. J Gen Physiol 97: 173–193 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Delpire E and Lauf PK(1991b) Trans-effects of cellular K and Cl on ouabain-resistant Rb(K) influx in low K sheep red blood cells: Further evidence for asymmetry of K-Cl cotransport. Pflügers Arch 419: 540–542 [DOI] [PubMed] [Google Scholar]
- Delpire E, Rauchman MI, Beier DR, Hebert SC, and Gullans SR(1994) Molecular cloning and chromosome localization of a putative basolateral Na-K-2Cl cotransporter from mouse inner medullary collecting duct (mIMCD-3) cells. J Biol Chem 269: 25677–25683 [PubMed] [Google Scholar]
- Delpire E, Wolfe L, Flores B, Koumangoye R, Schornak CC, Omer S, Pusey B, Lau C, Markello T, and Adams DR(2016) A patient with multisystem dysfunction carries a truncation mutation in human SLC12A2, the gene encoding the Na-K-2Cl cotransporter, NKCC1. Cold Spring Harb Mol Case Studies 2: a001289. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Deppeler HP. Hydrochlorothiazide, 1981. [Google Scholar]
- Ding J, Ponce-Coria J, and Delpire E(2013) A trafficking-deficient mutant of KCC3 reveals dominant-negative effects on K-Cl cotransport function. PLoS One 8: e61112. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Dunham PB, Steward GW, and Ellory JC(1980) Chloride-activated passive potassium transport in human erythrocytes. Proc Natl Acad Sci USA 77: 1711–1715 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Dzhala VI, Talos DM, Sdrulla DA, Brumback AC, Mathews GC, Benke TA, Delpire E, Jensen FE, and Staley KJ(2005) NKCC1 transporter facilitates seizures in the developing brain. Nat Med 11: 1205–1213 [DOI] [PubMed] [Google Scholar]
- Ellory JC, Hall AC, Ody SO, Englert HC, Mania D, and Lang H-J(1990) Selective inhibitors of KCl cotranport in human red cells. FEBS Lett 262: 215–218 [DOI] [PubMed] [Google Scholar]
- Fan M, Zhang J, Lee CL, Zhang J, and Feng L(2023) Structure and thiazide inhibition mechanism of the human Na-Cl cotransporter. Nature 614: 788–793 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Fernell E, Gustafsson P, and Gillberg C(2021) Bumetanide for autism: Open-label trial in six children. Acta Paediatr 110: 1548–1553 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Gagnon KB, England R, and Delpire E(2006) Characterization of SPAK and OSR1, regulatory kinases of the Na-K-2Cl cotransporter. Mol Cell Biol 26: 689–698 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Gagnon KB, England R, and Delpire E(2007a) A single binding motif is required for SPAK activation of the Na-K-2Cl cotransporter. Cell Physiol Biochem 20: 131–142 [DOI] [PubMed] [Google Scholar]
- Gagnon KB, England R, Diehl L, and Delpire E(2007b) Apoptosis associated tyrosine kinase scaffolding of protein phosphatase 1 and SPAK reveals a novel pathway for Na-K-2Cl cotransporter regulation. Am J Physiol (Cell Physiol) 292: C1809–C1815 [DOI] [PubMed] [Google Scholar]
- Gamba G, Miyanoshita A, Lombardi M, Lytton J, Lee W-S, Hediger M, and Hebert SC(1994) Molecular cloning, primary structure, and characterization of two members of the mammalian electroneutral sodium-(potassium)-chloride cotransporter family expressed in kidney. J Biol Chem 269: 17713–17722 [PubMed] [Google Scholar]
- Gamba G, Saltzberg SN, Lombardi M, Miyanoshita A, Lytton J, Hediger MA, Brenner BM, and Hebert SC(1993) Primary structure and functional expression of a cDNA encoding the thiazide-sensitive, electroneutral sodium-chloride cotransporter. Proc Natl Acad Sci USA 90: 2749–2753 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Garay RP, Nazaret C, Hannaert PA, and Cragoe EJ Jr.(1988) Demonstration of a [K+Cl-]-cotransport system in human red cells by its sensitivity to [(dihydroindenyl)oxy]alkanoic acids: regulation of cell swelling and distinction from the bumetanide-sensitive [Na+, K+, Cl-]-cotransport system. Mol Pharmacol 33: 696–701 [PubMed] [Google Scholar]
- Geck P, Pietrzyk C, Burckhardt B-C, Pfeiffer B, and Heinz E(1980) Electrically silent cotransport of Na+ , K+ and Cl− in Ehrlich cells. Biochim Biophys Acta 600: 432–447 [DOI] [PubMed] [Google Scholar]
- Gharaylou Z, Shafaghi L, Pestehei SK, and Hadjighassem M(2023) Long-term bumetanide administration altered behavioral pattern in mosaic Down’s Syndrome: A case report. Appl Neuropsychol Child 12: 88–95 [DOI] [PubMed] [Google Scholar]
- Gillen CM, Brill S, Payne JA, and Forbush BI(1996) Molecular cloning and functional expression of the K-Cl cotransporter from rabbit, rat, and human. A new member of the cation-chloride cotransporter family. J Biol Chem 271: 16237–16244 [DOI] [PubMed] [Google Scholar]
- Gimenez I and Forbush B(2007) The residues determining differences in ion affinities among the alternative splice variants F, A, and B of the mammalian renal Na-K-Cl cotransporter (NKCC2). J Biol Chem 282: 6540–6547 [DOI] [PubMed] [Google Scholar]
- Haas M and Forbush BI(1986) [3H]bumetanide binding to duck red cells. Correlation with inhibition of (Na + K + 2Cl) co-transport. J Biol Chem 261: 8434–8441 [PubMed] [Google Scholar]
- Haas M and McManus TJ(1983) Bumetanide inhibits (Na + K + 2Cl) co-transport at a chloride site. Am J Physiol 245: C235–C240 [DOI] [PubMed] [Google Scholar]
- Hadjikhani N, Åsberg Johnels J, Lassalle A, Zürcher NR, Hippolyte L, Gillberg C, Lemonnier E, and Ben-Ari Y(2018) Bumetanide for autism: more eye contact, less amygdala activation. Sci Rep 8: 3602. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Hadjikhani N, Zürcher NR, Rogier O, Ruest T, Hippolyte L, Ben-Ari Y, and Lemonnier E(2015) Improving emotional face perception in autism with diuretic bumetanide: a proof-of-concept behavioral and functional brain imaging pilot study. Autism 19: 149–157 [DOI] [PubMed] [Google Scholar]
- Hartmann AM, Wenz M, Mercado A, Störger C, Mount DB, Friauf E, and Nothwang HG(2010) Differences in the large extracellular loop between the K(+)-Cl(−) cotransporters KCC2 and KCC4. J Biol Chem 285: 23994–24002 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Hoover RS, Poch E, Monroy A, Vazquez N, Nishio T, Gamba G, and Hebert SC(2003) N-Glycosylation at two sites critically alters thiazide binding and activity of the rat thiazide-sensitive Na(+):Cl(−) cotransporter. J Am Soc Nephrol 14: 271–282 [DOI] [PubMed] [Google Scholar]
- Igarashi P, Vanden Heuvel GB, Quaggin SE, Payne JA, and Forbush BI(1994) Cloning, embryonic expression, and chromosomal localization of murine renal Na-K-Cl cotransporter (NKCC2). J Am Soc Nephrol 5: 288 [Google Scholar]
- Isenring P and Forbush BI(1997) Ion and bumetanide binding by the Na-K-2Cl cotransporter: Importance of transmembrane domains. J Biol Chem 272: 24556–24562 [DOI] [PubMed] [Google Scholar]
- Isenring P, Jacoby SC, Chang J, and Forbush BI(1998) Mutagenic mapping of the Na-K-Cl cotransporter for domains involved in ion transport and bumetanide binding. J Gen Physiol 112: 549–558 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Jennings ML and Schultz RK(1991) Okadaic acid inhibition of KCl cotransport. Evidence that protein dephosphorylation is necessary for activation of transport by either swelling or N-ethylmaleimide. J Gen Physiol 97: 799–817 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Kaji D and Tsukitani Y(1991) Role of protein phosphatase in activation of KCl cotransport in human erythrocytes. Am J Physiol 260: C176–C182 [DOI] [PubMed] [Google Scholar]
- Kaplan MR, Plotkin MD, Brown D, Hebert SC, and Delpire E(1996) Expression of the mouse Na-K-2Cl cotransporter, mBSC2, in the terminal IMCD, the glomerular and extraglomerular mesangium and the glomerular afferent arteriole. J Clin Invest 98: 723–730 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Keyes JW and Berlacher FJ(1958) Chlorothiazide (diuril); a new non-mercurial oral diuretic. Henry Ford Hosp Med Bull 6: 32–37 [PubMed] [Google Scholar]
- Kim EJ and Lee MG(2001) Pharmacokinetics and pharmacodynamics of intravenous bumetanide in mutant Nagase analbuminemic rats: importance of globulin binding for the pharmacodynamic effects. Biopharm Drug Dispos 22: 147–156 [DOI] [PubMed] [Google Scholar]
- Koumangoye R, Omer S, and Delpire E(2018) Mistargeting of a truncated Na-K-2Cl cotransporter in epithelial cells. Am J Physiol Cell Physiol 315: C258–C276 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Kregenow FM(1971) The response of duck erythrocytes to hypertonic media. Further evidence for a volume-controlling mechanism. J Gen Physiol 58: 396–411 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Kurihara K, Nakanishi N, Moore-Hoon ML, and Turner RJ(2002) Phosphorylation of the salivary Na(+)-K(+)-2Cl(−) cotransporter. Am J Physiol Cell Physiol 282: C817–C823 [DOI] [PubMed] [Google Scholar]
- Lauf PK(1984) Thiol-dependent passive K/Cl transport in sheep red cells. IV. Furosemide inhibition as a function of external Rb+, Na+, and Cl−. J Membrane Biol 77: 57–62 [DOI] [PubMed] [Google Scholar]
- Lauf PK and Theg BE(1980) A chloride dependent K+ flux induced by N-ethylmaleimide in genetically low K+ sheep and goat erythrocytes. Biochem Biophys Res Commun 70: 221–242 [DOI] [PubMed] [Google Scholar]
- Lemonnier E, Lazartigues A, and Ben-Ari Y(2016) Treating Schizophrenia With the Diuretic Bumetanide: A Case Report. Clin Neuropharmacol 39: 115–117 [DOI] [PubMed] [Google Scholar]
- Lemonnier E, Villeneuve N, Sonie S, Serret S, Rosier A, Roue M, Brosset P, Viellard M, Bernoux D, Rondeau S, Thummler S, Ravel D, and Ben-Ari Y(2017) Effects of bumetanide on neurobehavioral function in children and adolescents with autism spectrum disorders. Transl Psychiatry 7: e1056. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Li Q, Zhang L, Shan H, Yu J, Dai Y, He H, Li WG, Langley C, Sahakian BJ, Yao Y, Luo Q, and Li F(2022) The immuno-behavioural covariation associated with the treatment response to bumetanide in young children with autism spectrum disorder. Transl Psychiatry 12: 228. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Liedtke CM, Wang X, and Smallwood ND(2005) Role for protein phosphatase 2A in the regulation of Calu-3 epithelial Na+-K+−2Cl-, type 1 co-transport function. J Biol Chem 280: 25491–25498 [DOI] [PubMed] [Google Scholar]
- Liu S, Chang S, Han B, Lingyi Xu L, Zhang M, Zhao C, Yang W, Wang F, Li J, Delpire E, Ye S, Bai X-C, and Guo J(2019) Cryo-EM Structures of the Human Cation-Chloride Cotransporter KCC1. Science 366: 505–508 [DOI] [PubMed] [Google Scholar]
- Medzihradszky KF(2008) Characterization of site-specific N-glycosylation. Methods Mol Biol 446: 293–316 [DOI] [PubMed] [Google Scholar]
- Monette MY and Forbush B(2012) Regulatory activation is accompanied by movement in the C terminus of the Na-K-Cl cotransporter (NKCC1). J Biol Chem 287: 2210–2220 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Moore-Hoon ML and Turner RJ(1998) Molecular and topological characterization of the rat parotid Na+-K+−2Cl- cotransporter1. Biochim Biophys Acta 1373: 261–269 [DOI] [PubMed] [Google Scholar]
- Moore-Hoon ML and Turner RJ(2000) The structural unit of the secretory Na+-K+−2Cl- cotransporter (NKCC1) is a homodimer. Biochemistry 39: 3718–3724 [DOI] [PubMed] [Google Scholar]
- Moseng MA, Su CC, Rios K, Cui M, Lyu M, Glaza P, Klenotic PA, Delpire E, and Yu EW(2022) Inhibition mechanism of NKCC1 involves the carboxyl terminus and long-range conformational coupling. Sci Adv 8: eabq0952. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Motiwala Z, Aduri NG, Shaye H, Han GW, Lam JH, Katritch V, Cherezov V, and Gati C(2022) Structural basis of GABA reuptake inhibition. Nature 606: 820–826 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Mount DB, Mercado A, Song L, Xu J, George JAL, Delpire E, and Gamba G(1999) Cloning and Characterization of KCC3 and KCC4, new members of the cation-chloride cotransporter gene family. J Biol Chem 274: 16355–16362 [DOI] [PubMed] [Google Scholar]
- Nichols H, Cannon CP, Scirica BM, and Fisher NDL(2022) A remote hypertension management program clinical algorithm. Clin Cardiol 45: 1147–1162 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Oh SW and Han SY(2015) Loop Diuretics in Clinical Practice. Electrolyte Blood Press 13: 17–21 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Orringer EP, Brockenbrough JS, Whitney JA, Glosson PS, and Parker JC(1991) Okadaic acid inhibits activation of K-Cl cotransport in red cells containing hemoglobin S and C. Am J Physiol 261: C591–C593 [DOI] [PubMed] [Google Scholar]
- Palfrey HC, Feit PW, and Greengard P(1980) cAMP-stimulated cation cotransport in avian erythrocytes: inhibition by “loop” diuretics. Am J Physiol 238: C139–148 [DOI] [PubMed] [Google Scholar]
- Palfrey HC and Leung S(1993) Inhibition of Na-K-2Cl cotransport and bumetainde binding by ethacrinic acid, its analogues, and adducts. Am J Physiol (Cell Physiol) 264: C1270–1277 [DOI] [PubMed] [Google Scholar]
- Palfrey HC and Pewitt EB(1993) The ATP and Mg2+ dependence of Na(+)-K(+)-2Cl- cotransport reflects a requirement for protein phosphorylation: studies using calyculin A. Pflugers Archiv 425: 321–328 [DOI] [PubMed] [Google Scholar]
- Paredes A, Plata C, Rivera M, Moreno E, Vázquez N, Muñoz-Clares R, Hebert SC, and G. G(2006) Activity of the renal Na+-K+−2Cl- cotransporter is reduced by mutagenesis of N-glycosylation sites: role for protein surface charge in Cl- transport. Am J Physiol Renal Physiol 290: F1094–F1102 [DOI] [PubMed] [Google Scholar]
- Parker JC, Colclasure GG, and McManus TJ(1991) Coordinated regulation of shrinkage-induced Na/H exchange and swelling-induced [K-Cl] cotransport in dog red cells. Further evidence from activation kinetics and phosphatase inhibition. J Gen Physiol 98: 869–880 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Parrini M, Naskar S, Alberti M, Colombi I, Morelli G, Rocchi A, Nanni M, Piccardi F, Charles S, Ronzitti G, Mingozzi F, Contestabile A, and Cancedda L(2021) Restoring neuronal chloride homeostasis with anti-NKCC1 gene therapy rescues cognitive deficits in a mouse model of Down syndrome. Mol Ther 29: 3072–3092 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Payne JA, Stevenson TJ, and Donaldson LF(1996) Molecular characterization of a putative K-Cl cotransporter in rat brain. A neuronal-specific isoform. J Biol Chem 271: 16245–16252 [DOI] [PubMed] [Google Scholar]
- Platts MM(1959) Hydrochlorothiazide, a new oral diuretic. Br Med J 1: 1565–1568 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Portioli C, Ruiz Munevar MJ, De Vivo M, and Cancedda L(2021) Cation-coupled chloride cotransporters: chemical insights and disease implications. Trends Chem 3: 832–849 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Prael Iii FJ, Kim K, Du Y, Spitznagel BD, Sulikowski GA, Delpire E, and Weaver CD(2022) Discovery of Small Molecule KCC2 Potentiators Which Attenuate In Vitro Seizure-Like Activity in Cultured Neurons. Front Cell Dev Biol 10: 912812. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Rahmanzadeh R, Eftekhari S, Shahbazi A, Khodaei Ardakani MR, Rahmanzade R, Mehrabi S, Barati M, and Joghataei MT(2017) Effect of bumetanide, a selective NKCC1 inhibitor, on hallucinations of schizophrenic patients; a double-blind randomized clinical trial. Schizophr Res 184: 145–146 [DOI] [PubMed] [Google Scholar]
- Raveendran VA, Pressey JC, and Woodin MA(2020) A Novel Small Molecule Targets NKCC1 To Restore Synaptic Inhibition. Trends Pharmacol Sci 41: 897–899 [DOI] [PubMed] [Google Scholar]
- Sachs JR and Martin DW(1993) The role of ATP in swelling-stimulated K-Cl cotransport in human red cell ghosts. J Gen Physiol 102: 551–573 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Shankar SS and Brater DC(2003) Loop diuretics: from the Na-K-2Cl transporter to clinical use. Am J Physiol Renal Physiol 284: F11–F21 [DOI] [PubMed] [Google Scholar]
- Somasekharan S, Monette MY, and Forbush B(2013) Functional expression of human NKCC1 from a synthetic cassette-based cDNA: introduction of extracellular epitope tags and removal of cysteines. PLoS One 8: e82060. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Stringham JS(1807) On the Diuretic Effects of Mercury in a Case of Syphilis. Med Phys J 18: 331–333 [PMC free article] [PubMed] [Google Scholar]
- Subramanya AR and Ellison DH(2014) Distal convoluted tubule. Clin J Am Soc Nephrol 9: 2147–2163 [DOI] [PMC free article] [PubMed] [Google Scholar]
- van Andel DM, Sprengers JJ, Oranje B, Scheepers FE, Jansen FE, and Bruining H(2020) Effects of bumetanide on neurodevelopmental impairments in patients with tuberous sclerosis complex: an open-label pilot study. Mol Autism 11: 30. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Walker PC, Berry NS, and Edwards DJ(1989) Protein binding characteristics of bumetanide. Dev Pharmacol Ther 12: 13–18 [PubMed] [Google Scholar]
- Warmuth S, Zimmermann I, and Dutzler R(2009) X-ray structure of the C-terminal domain of a prokaryotic cation-chloride cotransporter. Structure 17: 538–546 [DOI] [PubMed] [Google Scholar]
- Wong FH, Chen JS, Reddy V, Day JL, Shlykov MA, Wakabayashi ST, and Saier MHJ(2012) The amino acid-polyamine-organocation superfamily. J Mol Microbiol Biotechnol 22: 105–113 [DOI] [PubMed] [Google Scholar]
- Xie Y, Chang S, Zhao C, Wang F, Liu S, J. W, Delpire E, Ye S, and Guo J(2020) Structures and an activation mechanism of human potassium-chloride cotransporters. Science Adv 6: eabc5883. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Xu J-C, Lytle C, Zhu TT, Payne JA, Benz EJ, and Forbush BI(1994) Molecular cloning and functional expression of the bumetanide-sensitive Na-K-2Cl cotransporter. Proc Natl Acad Sci USA 91: 2201–2205 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Yamashita A, Singh SK, Kawate T, Jin Y, and Gouaux E(2005) Crystal structure of a bacterial homologue of Na+/Cl−-dependent neurotransmitter transporters. Nature 437: 215–223 [DOI] [PubMed] [Google Scholar]
- Zaarour N, Demaretz S, Defontaine N, Zhu Y, and Laghmani K(2012) Multiple evolutionarily conserved Di-leucine like motifs in the carboxyl terminus control the anterograde trafficking of NKCC2. J Biol Chem 287: 42642–42653 [DOI] [PMC free article] [PubMed] [Google Scholar]
- Zarepour L, Gharaylou Z, Hadjighassem M, Shafaghi L, Majedi H, Behzad E, Hosseindoost S, Ramezani F, and Nasirinezhad F(2020) Preliminary study of analgesic effect of bumetanide on neuropathic pain in patients with spinal cord injury. J Clin Neurosci 81: 477–484 [DOI] [PubMed] [Google Scholar]
- Zhang J, Cordshagen A, Medina I, Nothwang HG, Wisniewski JR, Winklhofer M, and Hartmann AM(2020) Staurosporine and NEM mainly impair WNK-SPAK/OSR1 mediated phosphorylation of KCC2 and NKCC1. PLoS One 15: e0232967. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Zhao Y, Roy K, Vidossich P, Cancedda L, De Vivo M, Forbush B, and Cao E(2022a) Structural basis for inhibition of the Cation-chloride cotransporter NKCC1 by the diuretic drug bumetanide. Nat Commun 13: 2747. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Zhao Y, Shen J, Wang Q, Ruiz Munevar MJ, Vidossich P, De Vivo M, Zhou M, and Cao E(2022b) Structure of the human cation-chloride cotransport KCC1 in an outward-open state. Proc Natl Acad Sci U S A 119: e2109083119. [DOI] [PMC free article] [PubMed] [Google Scholar]