


Key Points
Question
Is group-based emotional awareness and expression therapy (EAET)—a psychological intervention targeting trauma and emotional processing—superior to cognitive-behavioral therapy (CBT) for treatment of chronic pain in a racially and ethnically diverse cohort of older veterans?
Findings
In this randomized clinical trial with 126 participants, those randomized to EAET had significantly greater improvements in the primary outcome of reduction in pain severity from baseline to the primary end point of posttreatment (week 10). Moreover, 63% of EAET participants had clinically significant (at least 30%) posttreatment pain reduction vs only 17% in CBT.
Meaning
These findings support the superiority of EAET compared with CBT in reducing chronic pain among older veterans.
Abstract
Importance
Chronic pain is common and disabling in older adults, and psychological interventions are indicated. However, the gold standard approach, cognitive-behavioral therapy (CBT), produces only modest benefits, and more powerful options are needed.
Objectives
To evaluate whether emotional awareness and expression therapy (EAET) is superior to CBT for treatment of chronic pain among predominantly male older veterans and whether higher baseline depression, anxiety, or posttraumatic stress disorder (PTSD) symptoms—key targets of EAET—moderate treatment response.
Design, Setting, and Participants
This 2-arm randomized clinical trial was conducted from May 16, 2019, to September 14, 2023, in the US Department of Veterans Affairs Greater Los Angeles Healthcare System. The trial included a racially and ethnically diverse group of veterans aged 60 to 95 years with at least 3 months of musculoskeletal pain.
Interventions
Emotional awareness and expression therapy or CBT, conducted concurrently, each presented as one 90-minute individual session followed by eight 90-minute group sessions.
Main Outcomes and Measures
The primary outcome was Brief Pain Inventory pain severity (range, 0 to 10) from baseline to posttreatment (week 10, primary end point) and 6-month follow-up. Secondary outcomes included Patient Reported Outcomes Institute Measurement System Anxiety, Depression, Fatigue, General Life Satisfaction (NIH Toolbox), Pain Interference, and Sleep Disturbance Short Forms, Patient Global Impression of Change (PGIC), and Satisfaction with Therapy and Therapist Scale-Revised. A subset of participants completed the PTSD Checklist for Diagnostic and Statistical Manual of Mental Disorders (Fifth Edition). All analyses were for the intention-to-treat population and included all randomized participants.
Results
Among 126 randomized participants (66 in the EAET group and 60 in the CBT group; mean [SD] age, 71.9 [5.9] years; 116 [92%] male), 111 (88%) completed posttreatment, and 104 (82%) completed the 6-month follow-up. The EAET was superior to CBT for the primary outcome of reduction in pain severity at posttreatment (estimate, −1.59 [95% CI, −2.35 to −0.83]; P < .001) and follow-up (estimate, −1.01 [95% CI, −1.78 to −0.24]; P = .01). A greater percentage of participants in EAET vs CBT had clinically significant (at least 30%) pain reduction (63% vs 17%; odds ratio, 21.54 [95% CI, 4.66-99.56]; P < .001) at posttreatment. In addition, EAET was superior to CBT on 50% pain reduction (35% vs 7%; odds ratio, 11.77 [95% CI, 2.38-58.25]; P = .002), anxiety (estimate, −2.49 [95% CI, −4.30 to −0.68]; P = .006), depression (estimate, −3.06 [95% CI, −5.88 to −0.25]; P = .03), general life satisfaction (estimate, 1.23 [95% CI, 0.36-2.10]; P = .005), PTSD symptoms (estimate, −4.39 [95% CI, −8.44 to −0.34]; P = .03), PGIC score (estimate, 1.46 [95% CI, 0.77-2.15]; P < .001), and global treatment satisfaction (estimate, 0.28 [95% CI, 0.12-0.45]; P < .001) at posttreatment. Higher baseline depression (estimate, −1.55 [95% CI, −0.37 to 2.73]; P < .001), anxiety (estimate, −1.53 [95% CI, −2.19 to −0.88]; P < .001), and PTSD symptoms (estimate, −1.69 [95% CI, −2.96 to −0.42]; P = .009) moderated greater reduction in pain severity after EAET but not CBT.
Conclusions and Relevance
The results of this randomized clinical trial suggest that EAET may be a preferred intervention for medically and psychiatrically complex patients with pain. The societal burden of chronic pain could be improved by further incorporating the principles of EAET into mainstream clinical pain medicine.
Trial Registration
ClinicalTrials.gov Identifier: NCT03918642
This randomized clinical trial assesses whether emotional awareness and expression therapy is superior to cognitive-behavioral therapy (CBT) for treatment of chronic musculoskeletal pain among a racially and ethnically diverse cohort of older veterans.
Introduction
Chronic pain affects many older adults1,2 and is a risk factor for cognitive decline3 and premature death.4 Medical and surgical interventions, particularly opioids, often produce only partial efficacy5 and pose substantial risks,6 including polypharmacy,7 drug-drug interactions,8 and falls.9,10 Psychological interventions may be safer, but standard options, such as cognitive-behavioral therapy (CBT), provide only small effect size benefits.11,12 In addition, veterans have high rates of severe pain13 and overlap between pain and psychiatric conditions, such as depression, anxiety, and posttraumatic stress disorder (PTSD),14,15,16,17 which may further limit the effectiveness of CBT.18
Adverse childhood experiences,19,20,21 military combat,22 racism or discrimination,23,24 and psychiatric conditions16,25 are associated with the presence and severity of chronic pain, but are not directly addressed by CBT. Emotional awareness and expression therapy (EAET)26 was developed to target these critical drivers of chronic pain.20,27,28,29,30 Emotional awareness and expression therapy demonstrated efficacy in several controlled and uncontrolled trials,31,32,33,34,35,36,37,38,39 including 2 showing some superiority to CBT.40,41 Yet most trials of EAET have been in largely white, female, often young samples, and testing in an older, diverse population is needed. Given preliminary evidence of efficacy of group-based EAET in small samples of diverse older veterans,39,41 the current full-scale trial evaluated whether group-based EAET is superior to CBT among a racially and ethnically diverse cohort of older veterans on the primary outcome of pain severity, and on secondary or exploratory mood and functional outcomes, from baseline to the primary end point of posttreatment (week 10) and to 6 months posttreatment. The effects of baseline levels of depression, anxiety, and PTSD symptoms on extent of pain reduction were also assessed.
Methods
Study Design
This randomized clinical trial was conducted at the US Department of Veterans Affairs (VA) Greater Los Angeles Healthcare System (GLA) to evaluate comparative efficacy and moderators of EAET and CBT (trial protocol in Supplement 1). Ethics approval was provided by the institutional review board at GLA, and the trial was preregistered. Enrollment occurred from May 16, 2019, to February 1, 2023, with the final follow-up on September 14, 2023. The study was paused because of COVID-19–related administrative holds from March 20, 2020, until February 4, 2021, at which time a small number of patients who had provided informed consent but had not been randomly allocated to a group were transitioned to a separate single-arm trial of EAET presented via video telehealth.39 The study was monitored by the VA Clinical Science Research and Development Data Monitoring Committee. All participants provided written informed consent. This report followed the Consolidated Standards of Reporting Trials (CONSORT) guideline for parallel group randomized trials.
Participants
Recruitment methods included referrals from outpatient clinics at GLA, letter-based recruitment to veterans registered at GLA who met basic selection criteria (eg, age, pain diagnosis) based on a search of data from the VA Corporate Warehouse, and self-referral from posted flyers. Inclusion criteria were veteran status, age 60 to 95 years, and at least 3 months of musculoskeletal pain, including back, leg, or pelvic pain; neck pain or whiplash; temporomandibular joint disorder; fibromyalgia; tension headache; or any combination of these. Exclusion criteria were pain secondary to primary disorders, including cancer, autoimmune disease, sickle cell disease, neuralgia, burn, infection, cauda equina syndrome, gout, migraine or cluster headache, radiography-confirmed hip or knee osteoarthritis, radiculopathy, or electromyography-confirmed carpal or tarsal tunnel syndrome. Also excluded were individuals with psychotic disorder or severe mood disorder not controlled with medications; severe alcohol or substance use disorder; Mini-Mental State Examination (MMSE)42 score of 24 or lower (MMSE score ranges from 0 to 30, with higher numbers indicating better cognition); current pain-related litigation; currently receiving EAET or CBT as part of clinical care; participation in CBT in the past 3 months; not fluent in English; and a plan to move from the area in the next 6 months.
Race and ethnicity data were collected by multiple choice self-report using categories in accordance with the National Institutes of Health guidelines. These categories were American Indian or Alaska Native, Asian, Black or African American, Hispanic or Latino, Native Hawaiian or Other Pacific Islander, and White, as well as multiracial or unknown.
Randomization
An independent team member with no patient contact (M.A.L.) generated the 1:1 computer randomization sequence in blocks of 16 at the start of the trial. The principal investigator (B.C.Y.) and study coordinators (including A.A.) were blinded to the randomization until the next cohort of 16 patients was recruited and ready to be randomized. Participants were randomized to EAET or CBT following the baseline assessment session. Participants learned of their assignment at the first treatment session but remained blinded to study hypotheses for the duration of the trial.
Interventions
Each treatment included one 90-minute individual session followed by eight 90-minute sessions in small groups with a mean (SD) of 6.3 (1.6) veterans per group. The trial included a total of 10 EAET groups and 10 CBT groups; an EAET group was always conducted concurrently with a CBT group throughout the trial. All sessions took place in person at GLA.
To avoid threats to fidelity, several steps were taken. Both EAET and CBT were presented as effective for chronic pain and had written manuals43,44 with similar amounts of discussion, experiential exercises, and homework. Therapists were nested within treatment condition, presenting only the treatment (EAET or CBT) in which they had training and competence. One primary therapist led a complete course of treatment, including individual and group sessions, under the direction of an expert supervisor who monitored treatment adherence and fidelity. Primary therapists for EAET included 1 licensed psychologist, 2 licensed psychiatrists, and 1 psychiatry resident, who became a geriatric psychiatry fellow during the trial. Primary therapists for CBT were 1 licensed psychologist and 3 geriatric psychology postdoctoral residents. Sessions were video recorded, and 25% were rated by an independent fidelity monitor using a standard rating form39,40 of topics and activities from EAET and CBT; treatment fidelity was generally rated as high (eTable 1 in Supplement 2).
The EAET followed a manual for the individual session that was developed and piloted for this population41 and the group manual developed by Lumley and Schubiner,43 which was previously adapted for the population.41 The EAET participants were presented with the EAET conceptual model that failure to adaptively process and resolve emotional symptoms—resulting from adverse childhood experiences, trauma, or victimization—can change brain pathways involved in the processing of both pain and emotion, leading to or exacerbating pain symptoms.19,20,21,22,23,24,25,26,27,28,29,30 The goals of EAET are to learn that the brain’s perception of pain is strongly influenced by evading trauma- or stress-related emotions (eg, emotional pain or grief, fear, rage, and guilt) and to face and resolve such emotions to reduce or eliminate chronic pain.26,45 The individual session presented the therapy model and invited participants to engage in a trial of emotional processing, consisting of experiencing trauma- or stress-related emotions in the body, expressing them in words, and releasing or letting them go in adaptive ways (eg, imaginarily buried or cast out to sea). Group sessions included psychoeducation on pain and emotions, further emotional processing, and social disclosure and validation of emotional experiences. Written homework included identifying stress-symptom connections, expressive writing, and practicing adaptive communication of emotions.
The CBT followed the VA Cognitive Behavioral Therapy for Chronic Pain manual,44 which was presented with minimal adaptations, although the timing of certain sections had been adjusted by the trial’s CBT supervisor during piloting41 to match EAET’s 1 individual and 8 group sessions. The CBT participants were presented with the CBT model that chronic pain often leads to patterns of negative thoughts, feelings, and behaviors that can subsequently worsen pain and functioning. The goal of CBT is to target maladaptive patterns of thinking and behavior by learning alternative, more adaptive pain coping skills. The individual session included a pain and health history and introduction of CBT skills training. Group sessions included psychoeducation on 1 or more pain coping skills (eg, progressive muscle relaxation, guided imagery), experiential practice of a skill, and homework applying skills to daily life and recording progress on worksheets.
Outcomes
Participants completed self-report paper and pencil outcome measures at baseline, posttreatment (week 10), and the 6-month-follow-up. The primary outcome was change in Brief Pain Inventory pain severity,46 which calculates the mean of the worst, least, and average pain in the last week and current pain on scales ranging from 0 to 10. Pain severity response at 3 levels 31,40,41,47 was also recorded for pain reduction from baseline: at least 30% (clinically significant), at least 50%, and greater than 70%. Secondary or exploratory outcome measures included PROMIS Anxiety,48 Depression,48 Fatigue,49 General Life Satisfaction (NIH Toolbox),50 Pain Interference,51 and Sleep Disturbance52 Short Forms; the Patient Global Impression of Change (PGIC) Scale53 score (at posttreatment and 6-month follow-up); and the Satisfaction with Therapy and Therapist Scale-Revised54 (at posttreatment only). In addition, the PTSD Checklist for Diagnostic and Statistical Manual of Mental Disorders (Fifth Edition)55 was added at the beginning of group 3 at the request of the Data Monitoring Committee.
Sample Size Calculation
We used an empirical power simulation to estimate the power to detect between-group differences in pain severity change from baseline to posttreatment. Using multivariate normal distributions, we assumed a mean difference of −0.70 points between EAET and CBT, within-time-period SD of 1.6, and correlation of 0.6 (ρ) between baseline and posttreatment. Estimates were based on preliminary data in the population, which demonstrated a mean difference of −0.80 points. Based on these parameters, we assessed for differences using a mixed-effects linear regression model and a 2-sided α level of .05. A sample size of 120 participants (n = 60 per treatment) was needed to demonstrate 80% power to detect a between-group difference in pain severity change over time of −0.70 points. We planned to obtain informed consent from 160 participants to account for an estimated 25% attrition prior to randomization. The actual number of participants who provided written consent was 175 because an additional 15 participants discontinued prior to baseline during the COVID-19 administrative hold.
Statistical Analysis
All analyses were for the intention-to-treat sample and included all randomized participants. For pain severity and secondary (exploratory) outcomes of anxiety, depression, fatigue, general life satisfaction, pain interference, sleep disturbance, PTSD symptoms, and PGIC score, mixed-effects linear regression models were used with group number (1-10) random intercept, nested patient random intercept with nested time random slope, and clustered robust SEs for group provision of treatment (to account for heteroscedasticity). Fixed effects were treatment (EAET vs CBT), time (modeled as a categorical factor referent to baseline), and time by treatment interaction. For posttreatment satisfaction, mixed-effects linear regressions were used with group number random intercept and clustered robust SEs for group treatment. Fixed effects were treatment (EAET vs CBT).
In prespecified secondary analyses of the primary outcome of pain severity, the percentages of participants achieving 3 pain reduction response levels (at least 30%, at least 50%, and greater than 70% reduction from baseline) were analyzed using mixed-effects logistic regression with group number random intercept and nested patient random intercept. Fixed effects were treatment, time (modeled as a categorical factor referent to baseline), and time by treatment interaction. Although our primary interest was between-condition differences in response within each time point after baseline, data were modeled longitudinally to minimize bias from attrition at the 6-month follow-up. Marginal estimates were used to compute within–time point, between-condition comparisons.
To explore moderation of treatment effect by baseline depression and anxiety, mixed-effects models incorporated additional fixed effects for depression or anxiety into a 3-way interaction of treatment by time by baseline mood. Baseline depression and anxiety were examined as binary variables representing scores above or below the median and as continuous variables. In addition, post hoc analyses explored moderation of treatment effect by PTSD symptoms in the subsample for which the measure was available (groups 3-10).
All statistical analyses were conducted with Stata MP, version 18.0 (StataCorp LLC). A 2-sided value of P < .05 was considered statistically significant.
Results
Participant Characteristics
In total, 1225 individuals were contacted by the study team; 175 completed screening and signed written informed consent (Figure 1). Of these, 31 could not be contacted to be randomized, 12 withdrew for personal or medical reasons, and 6 were transitioned to a virtual EAET pilot study39 after the present trial was placed on a COVID-19–related administrative hold. Thus, 126 individuals were randomized, 111 individuals (88%) completed posttreatment assessments, and 104 individuals (82%) completed 6-month follow-up assessments. There were no significant baseline differences between individuals with or without posttreatment or follow-up data (eTable 2 in Supplement 2). All randomized participants attended an individual session and a mean (SD) of 5.5 (2.7) of 8 group sessions.
Figure 1. Flow of Participants through the Clinical Trial.

CBT indicates cognitive behavioral therapy; EAET, emotional awareness and expression therapy.
The full randomized sample had a mean (SD) age of 71.9 (5.9) years, and 116 (92%) were male, and 10 (8%) were female (Table 1). Most participants, 69 (55%), were Black or African American (not of Hispanic origin), 39 (31%) were White (not of Hispanic origin), and 17 (14%) reported being of more than 1 race or ethnicity or their race unknown. In addition, 8 participants (6%) reported Hispanic or Latino ethnicity. The results in the categories American Indian or Alaska Native and Asian or Native Hawaiian or Other Pacific Islander are not reported owing to small numbers. Nearly all participants (121 [96%]) reported back pain, although multiple pain locations were typical; mean (SD) pain duration was 23.3 (17.7) years; and 14 participants (11%) were prescribed opioids. Over two-thirds of participants (87 [69%]) had psychiatric diagnoses, and 47 participants (37%) had PTSD. Participants in the sample had a mean (SD) of 5.0 (2.4) chronic medical conditions, 9.6 (4.8) prescription medications, and MMSE score of 28.6 (1.4).
Table 1. Baseline Demographic and Clinical Characteristics and Outcome Measures of All Randomized Participants by Treatment Condition.
| Characteristic | Participants, No. (%) | |
|---|---|---|
| EAET (n = 66) | CBT (n = 60) | |
| Demographic characteristics | ||
| Age, mean (SD), y | 72.6 (5.2) | 71.3 (6.6) |
| Sex | ||
| Female | 7 (11) | 3 (5) |
| Male | 59 (89) | 57 (95) |
| Racea | ||
| American Indian or Alaska Native | NR | NR |
| Asian or Native Hawaiian or Other Pacific Islander | NR | NR |
| Black or African American (not of Hispanic origin) | 32 (48) | 37 (62) |
| Multiracial or unknown | 11 (17) | 6 (10) |
| White (not of Hispanic origin) | 22 (33) | 17 (28) |
| Hispanic or Latino ethnicity | 6 (9) | 2 (3) |
| Marital status | ||
| Married or partnered | 23 (35) | 19 (32) |
| Divorced or separated | 25 (38) | 25 (42) |
| Never married or other | 18 (27) | 16 (27) |
| Educational level | ||
| ≤High school graduate | 10 (15) | 14 (23) |
| Some college | 36 (55) | 26 (43) |
| ≥College graduate | 20 (30) | 20 (33) |
| Pain-related characteristics | ||
| Pain location | ||
| Back | 63 (95) | 58 (97) |
| Neck | 45 (68) | 32 (53) |
| Leg | 52 (79) | 50 (83) |
| Pelvic or groin | 28 (42) | 20 (33) |
| Temporomandibular joint disorder | 11 (17) | 10 (17) |
| Fibromyalgia | 3 (5) | 2 (3) |
| Tension headache | 19 (29) | 15 (25) |
| Pain duration, mean (SD), y | 22.5 (18.2) | 24.2 (17.3) |
| Prescribed opioids at baseline | 8 (12) | 6 (10) |
| Other clinical characteristics | ||
| Any psychiatric diagnosis | 44 (67) | 43 (72) |
| VA service–connected for PTSD | 25 (38) | 22 (37) |
| Nonpain chronic medical conditions, mean (SD), No. | 5.0 (2.2) | 4.9 (2.7) |
| Prescription medications, mean (SD), No. | 9.9 (5.2) | 9.4 (4.3) |
| Mini-Mental State Examination, mean (SD), scoreb | 28.9 (1.1) | 28.4 (1.6) |
| Baseline outcome measure scores, mean (SD) | ||
| BPI pain severity, mean (SD), scorec | 5.97 (1.98) | 6.23 (1.63) |
| PROMIS Anxiety Short Form 7a, mean (SD), scored | 19.0 (7.0) | 19.7 (7.3) |
| PROMIS Depression Short Form 8a, mean (SD), scoree | 20.6 (7.7) | 20.3 (8.5) |
| PROMIS Fatigue Short Form 7a, mean (SD), scoref | 20.8 (5.4) | 21.4 (5.4) |
| NIH Toolbox General Life Satisfaction Fixed Form B, mean (SD), scoreg | 15.1 (4.4) | 14.6 (4.1) |
| PROMIS Pain Interference Short Form 8a, mean (SD), scoreh | 27.7 (8.1) | 29.6 (7.0) |
| PROMIS Sleep Disturbance Short Form 8a, mean (SD), scorei | 24.6 (8.2) | 24.0 (8.2) |
| PCL-5, mean (SD), scorej | 28.9 (19.1) | 25.5 (18.6) |
Abbreviations: BPI, Brief Pain Inventory; CBT, cognitive-behavioral therapy; EAET, emotional awareness and expression therapy; NR, not reported; PCL-5, PTSD Checklist for DSM-5; PROMIS, Patient Reported Outcomes Institute Measurement System; PTSD, posttraumatic stress disorder; VA, Veterans Affairs.
Race and ethnicity data from categories with only a few people were not reported to protect the individuals’ identity.
Score ranged from 0 to 30, with higher scores indicating better cognition.
The primary outcome was the average of the 4 pain severity items of the BPI,46 which measures current pain and worst, least, and average pain over the last 7 days, each on a scale of 0 to 10, with higher values indicating worse pain.
The PROMIS Anxiety Short Form 7a48 includes 7 items assessing anxiety symptoms over the last 7 days, each rated from 1 to 5 for total scores ranging from 7 to 35; higher scores indicate greater anxiety.
The PROMIS Depression Short Form48 includes 8 items assessing depressive symptoms over the last 7 days, each rated from 1 to 5 for total scores ranging from 8 to 40; higher scores indicate greater depression.
The PROMIS Fatigue Short Form 7a49 includes 7 items assessing symptoms of fatigue over the last 7 days, each rated from 1 to 5 for total scores ranging from 7 to 35; higher scores indicate greater fatigue.
The NIH Toolbox General Life Satisfaction Fixed Form B50 includes 5 items assessing the degree to which participants agree or disagree with statements about life satisfaction; each item is scored from 1 to 5 for total scores between 5 and 25, and higher scores indicate greater life satisfaction.
The PROMIS Pain Interference Short Form 8a51 includes 8 items assessing the interference of pain with mood and activities over the last 7 days, each rated from 1 to 5 for total scores ranging from 8 to 40; higher scores indicate greater pain interference.
The PROMIS Sleep Disturbance Short Form 8a52 includes 8 items assessing sleep disturbance over the last 7 days, each rated from 1 to 5 for total scores ranging from 8 to 40; higher scores indicate greater sleep disturbance.
The PCL-555 includes 20 items on PTSD symptoms related to the most stressful experience in life, each rated from 0 to 4 for total scores between 0 and 80, with higher scores indicating greater stress. Sample sizes for the PCL-5 are EAET, n = 52; CBT, n = 47.
Outcomes
Descriptive statistics for outcomes appear in eTable 3 in Supplement 2. All results for primary analyses are shown in Table 2. For the primary outcome of pain severity (Figure 2A), both treatment conditions showed significant within-condition reductions at posttreatment, with EAET demonstrating a greater reduction in pain severity than CBT (estimate, −1.59 [95% CI, −2.35 to −0.83]; P < .001). At the 6-month follow-up, only EAET showed a significant within-condition reduction from baseline, with a difference in the change from baseline favoring EAET over CBT (estimate, −1.01 [95% CI, −1.78 to −0.24]; P = .01).
Table 2. Primary Analyses Using Mixed-Effects Linear and Logistic Regression Models With Group by Time Interaction.
| Outcome | Estimate (95% CI) | EAET vs CBT comparison | ||
|---|---|---|---|---|
| EAET | CBT | Difference or OR, estimate (95% CI) | P value | |
| Primary outcome | ||||
| BPI pain severity | ||||
| Change from baseline to posttreatment | −2.18 (−3.00 to −1.37)a | −0.60 (−1.13 to −0.06)b | −1.59 (−2.35 to −0.83) | <.001 |
| Change from baseline at 6-mo follow-up | −1.26 (−1.83 to −0.68)a | −0.25 (−0.72 to 0.23) | −1.01 (−1.78 to −0.24) | .01 |
| At least 30% pain reduction | ||||
| Posttreatment, % | 63.5 (50.6 to 76.4) | 17.1 (6.8 to 27.5) | 21.54 (4.66 to 99.56)c | <.001 |
| 6-mo Follow-up, % | 40.3 (26.8 to 53.8) | 14.2 (4.3 to 24.0) | 7.24 (1.74 to 30.06)c | .006 |
| At least 50% pain reduction | ||||
| Posttreatment, % | 35.7 (21.5 to 49.8) | 7.4 (0.0 to 14.7) | 11.77 (2.38 to 58.25)c | .002 |
| 6-mo Follow-up, % | 16.6 (5.8 to 27.4) | 3.9 (0.0 to 9.4) | 6.58 (0.99 to 43.67)c | .05 |
| At least 70% pain reduction | ||||
| Posttreatment, % | 12.8 (2.7 to 22.8) | 1.9 (0.0 to 5.8) | 13.93 (0.86 to 225.44)c | .06 |
| 6-mo Follow-up, % | 7.5 (0.0 to 15.3) | 2.1 (0.0 to 6.1) | 5.61 (0.35 to 89.30)c | .22 |
| Secondary outcomes | ||||
| PROMIS Anxiety Short Form 7a | ||||
| Change from baseline to posttreatment | −3.13 (−4.56 to −1.70)a | −0.64 (−2.18 to 0.89) | −2.49 (−4.30 to −0.68) | .006 |
| Change from baseline at 6-mo follow-up | −3.17 (−4.58 to −1.76)a | −1.22 (−2.53 to 0.09) | −1.95 (−4.34 to 0.45) | .11 |
| PROMIS Depression Short Form 8a | ||||
| Change from baseline to posttreatment | −5.12 (−6.62 to −3.62)a | −2.06 (−4.31 to 0.20) | −3.06 (−5.88 to −0.25) | .03 |
| Change from baseline at 6-mo follow-up | −3.48 (−4.94 to −2.03)a | −1.09 (−2.97 to 0.78) | −2.39 (−4.33 to −0.45) | .02 |
| PROMIS Fatigue Short Form 7a | ||||
| Change from baseline to posttreatment | −1.97 (−3.00 to −0.93)a | −1.19 (−2.44 to 0.06) | −0.78 (−2.33 to 0.78) | .33 |
| Change from baseline at 6-mo follow-up | −1.47 (−2.53 to −0.40)d | −1.17 (−2.49 to 0.15) | −0.30 (−1.74 to 1.14) | .69 |
| NIH Toolbox General Life Satisfaction Fixed Form B | ||||
| Change from baseline to posttreatment | 1.68 (1.02 to 2.34)a | 0.45 (−0.15 to 1.05) | 1.23 (0.36 to 2.10) | .005 |
| Change from baseline at 6-mo follow-up | 1.15 (0.82 to 1.48)a | 0.21 (−0.94 to 1.35) | 0.95 (−0.40 to 2.29) | .17 |
| PROMIS Pain Interference Short Form 8a | ||||
| Change from baseline to posttreatment | −5.41 (−7.33 to −3.48)a | −3.99 (−6.41 to −1.56)a | −1.42 (−3.30 to 0.46) | .14 |
| Change from baseline at 6-mo follow-up | −2.87 (−4.96 to −0.78)d | −3.08 (−4.59 to −1.57)a | 0.21 (−1.99 to 2.42) | .85 |
| PROMIS Sleep Disturbance Short Form 8a | ||||
| Change from baseline to posttreatment | −2.69 (−4.39 to −0.98)d | −0.84 (−2.61 to 0.94) | −1.85 (−4.14 to 0.44) | .11 |
| Change from baseline at 6-mo follow-up | −2.73 (−4.21 to −1.24)a | −0.16 (−2.21 to 1.89) | −2.57 (−5.73 to 0.60) | .11 |
| Patient Global Impression of Changee | ||||
| Posttreatment score | 4.67 (4.17 to 5.16) | 3.20 (2.79 to 3.61) | 1.46 (0.77 to 2.15) | <.001 |
| 6-mo Follow-up score | 4.01 (3.61 to 4.41) | 2.77 (2.34 to 3.21) | 1.24 (0.62 to 1.86) | <.001 |
| PCL-5f | ||||
| Change from baseline to posttreatment | −4.45 (−7.55 to −1.34)d | −0.06 (−3.55 to 3.44) | −4.39 (−8.44 to −0.34) | .03 |
| Change from baseline at 6-mo follow-up | −4.07 (−6.26 to −1.88)a | −0.31 (−5.28 to 4.66) | −3.76 (−7.83 to 0.32) | .07 |
| Satisfaction with Therapyg | ||||
| Posttreatment score | 24.68 (23.33 to 26.02) | 23.59 (22.48 to 24.70) | 1.09 (−0.08 to 2.26) | .07 |
| Satisfaction with Therapistg | ||||
| Posttreatment score | 25.73 (24.55 to 26.92) | 25.54 (24.60 to 26.48) | 0.20 (−0.80 to 1.19) | .70 |
| Global Satisfaction Scoreh | ||||
| Posttreatment score | 4.30 (4.05 to 4.54) | 4.01 (3.83 to 4.19) | 0.28 (0.12 to 0.45) | <.001 |
Abbreviations: BPI, Brief Pain Inventory; CBT, cognitive-behavioral therapy; EAET, emotional awareness and expression therapy; OR, odds ratio; PCL-5, PTSD Checklist for DSM-5; PROMIS, Patient Reported Outcomes Institute Measurement System; STTS-R, Satisfaction with Therapy and Therapist Scale-Revised.
Within condition P < .001.
Within condition P < .05.
Values are ORs (95% CIs).
Within condition P < .01.
Single item rated from 1 to 7 assessing change in activity limitations, symptoms, emotions, and quality of life since beginning treatment; higher scores indicate greater improvement.
Sample sizes for the PCL-5 are EAET, n = 52; CBT, n = 47.
Subscale of the STTS-R54 includes 6 items rated from 1 to 5 for possible scores ranging from 6 to 30; higher scores indicate better satisfaction.
Single item of the STTS-R54 rated from 1 to 5; higher scores indicate better satisfaction.
Figure 2. Pain Severity Outcomes.
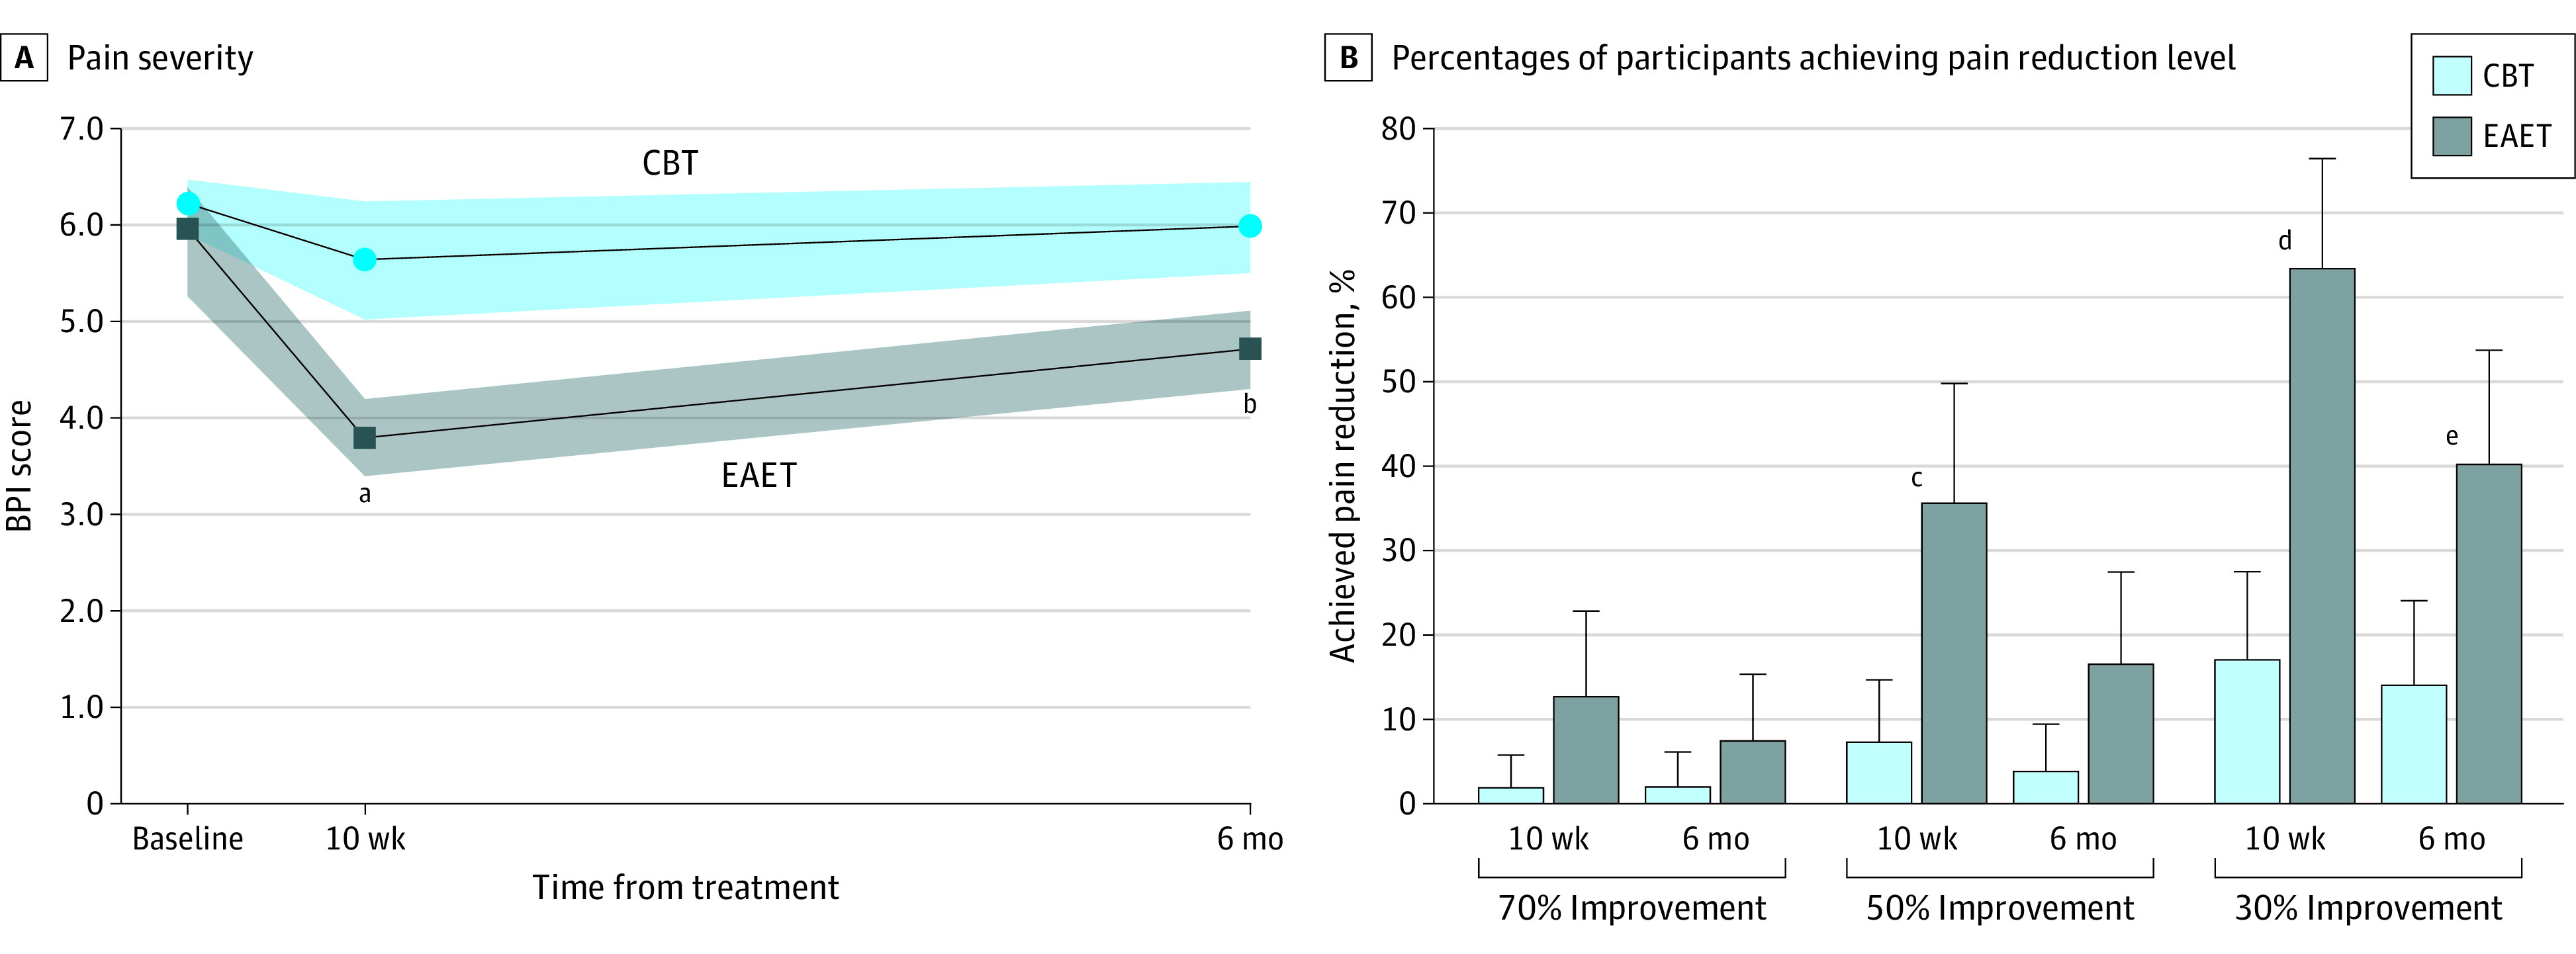
A, Shading represents SEs. B, Vertical lines represent upper bound of the 95% CI. CBT indicates cognitive behavioral therapy; EAET, emotional awareness and expression therapy.
aP < .001.
bP = .01.
cP = .002.
eP < .001.
eP = .006.
At posttreatment, a significantly greater percentage of EAET vs CBT participants had at least 30% pain reduction (63% vs 17%; odds ratio [OR], 21.54 [95% CI, 4.66-99.56]; P < .001) and at least 50% pain reduction (35% vs 7%; OR, 11.77 [95% CI, 2.38-58.25]; P = .002). At the 6-month follow-up, a greater percentage of EAET vs CBT participants maintained at least 30% pain reduction (41% vs 14%; OR, 7.24 [95% CI, 1.74-30.06]; P = .006; Figure 2B).
For secondary or exploratory outcomes, significant between-group differences favoring EAET over CBT in baseline to posttreatment change were observed for anxiety (estimate, −2.49 [95% CI, −4.30 to −0.68]; P = .006), depression (estimate, −3.06 [95% CI, −5.88 to −0.25]; P = .03), general life satisfaction (estimate, 1.23 [95% CI, 0.36-2.10]; P = .005), PTSD symptoms (estimate, −4.39 [95% CI, −8.44 to −0.34]; P = .03), PGIC score (estimate, 1.46 [95% CI, 0.77-2.15]; P < .001), and global satisfaction (estimate, 0.28 [95% CI, 0.12-0.45]; P < .001). Significant differences favoring EAET over CBT were observed in baseline to 6-month follow-up change for depression (estimate, −2.39 [95% CI, −4.33 to −0.45]; P = .02) and PGIC score (estimate, 1.24 [95% CI, 0.62-1.86]; P < .001). No other reliable differences were observed.
Moderation
When examining above-median vs below-median baseline depression, the differential depression effect for EAET (difference-in-differences [DID] estimate, –1.42) was different for CBT (DID, 0.13) (difference in DID estimate for the interaction effect, −1.55 [95% CI, −2.73 to −0.37]; P = .01), suggesting a greater effect of baseline depression on reduction in pain severity for EAET relative to CBT (Figure 3A). When using baseline depression as a continuous moderator, for a 1-SD increase in baseline depression, the between-condition reduction in pain severity at posttreatment was greater for EAET than CBT (estimate, −0.83 [95% CI, −1.32 to −0.35]; P < .001). Similar effects were observed when examining above-median vs below-median anxiety (difference in DID estimate, −1.53 [95% CI, −2.19 to −0.88]; P < .001; Figure 3B) and PTSD (difference in DID estimate, −1.69 [95% CI, −2.96 to −0.42]; P = .009; Figure 3C). See eTable 4 in Supplement 2 for further detail.
Figure 3. Moderation of Pain Severity Reduction between Treatment Conditions by Baseline Depression, Anxiety, and PTSD Symptom Scores.
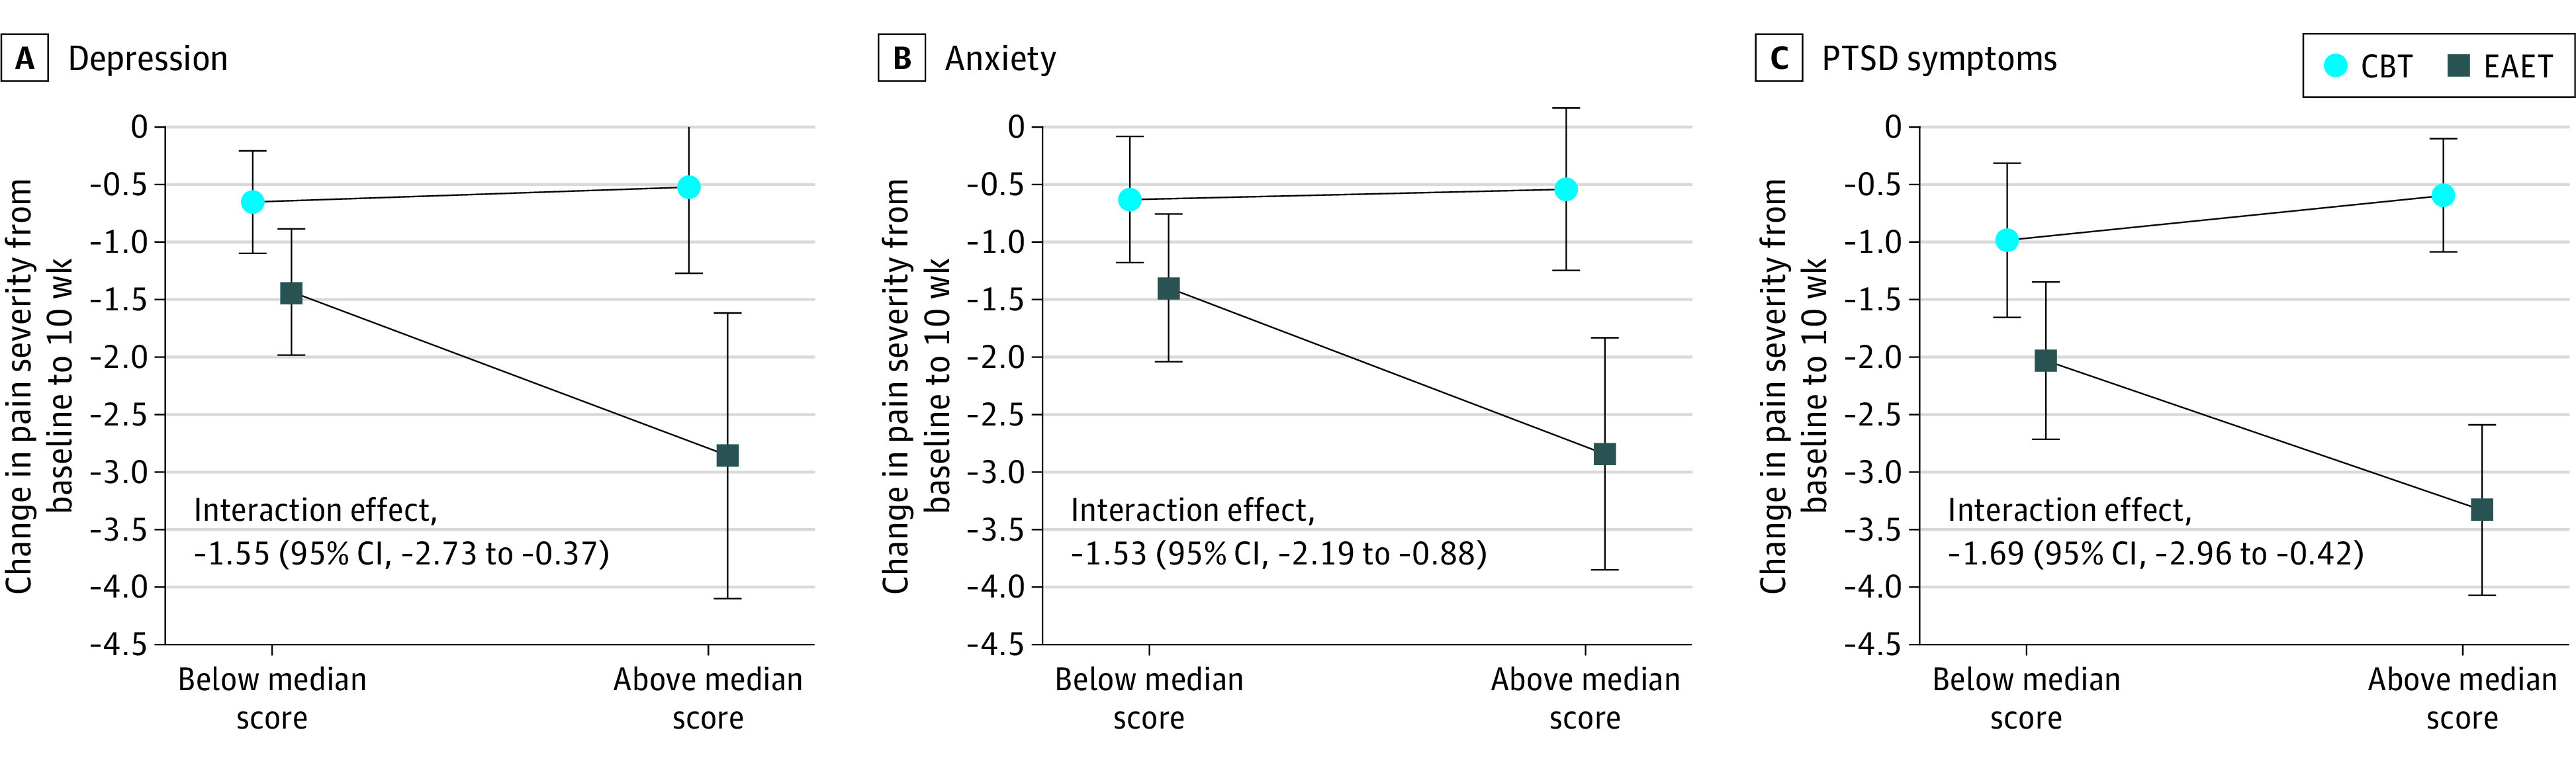
The interaction effect estimate is the difference in the differences-in-difference estimates between the 2 treatment conditions. CBT indicates cognitive-behavioral therapy; EAET, emotional awareness and expression therapy; PTSD, posttraumatic stress disorder.
Discussion
In this randomized clinical trial among a racially and ethnically diverse cohort of veterans 60 to 95 years of age with chronic musculoskeletal pain, EAET was superior to CBT on the primary outcome of reduction in pain severity from baseline to posttreatment and 6-month follow-up. Compared with CBT, EAET led to a significantly greater percentage of participants who reached the benchmarks of at least 30% and 50% pain reduction at posttreatment and at least 30% pain reduction at follow-up. At posttreatment, EAET also demonstrated greater improvements than CBT on most secondary or exploratory outcomes—anxiety, depression, life satisfaction, PTSD symptoms, patient global impression of change, and global satisfaction—and maintained advantages on depression and global impression 6 months posttreatment. Moderation analyses revealed that patients with higher baseline symptoms of depression, anxiety, or PTSD had particularly robust pain reduction following EAET but not CBT.
This trial is the first full-scale evaluation of EAET, to our knowledge, in a medically or psychiatrically complex, racially and ethnically diverse, older sample comprising predominantly men. Findings align with prior smaller controlled or uncontrolled trials of EAET that have shown large effect size reductions in pain severity39,41 and high response rates, with up to two-thirds of patients achieving at least a 30% pain reduction.31,39,47 The present trial is only the third to directly compare EAET with CBT. A small trial in the same population41 showed superiority of EAET to CBT on pain severity and anxiety, and a large trial of patients with fibromyalgia40 showed that EAET was superior to CBT on several secondary outcomes (fibromyalgia symptoms, widespread pain, and 50% pain reduction at 6-month follow-up), but not on mean pain severity. Moreover, while previous research indicated a less favorable response to CBT among patients with the common comorbidities of depression and anxiety,18 the current trial indicated that EAET is especially effective for such patients. Thus, the current trial provides the strongest evidence to date supporting the superiority of EAET over CBT.
The results of this trial lend credence to 2 interrelated conceptual models of chronic pain proposing that the condition may be substantially reduced and, in some cases, eliminated by helping patients (1) change beliefs about the potential amelioration of pain via psychological techniques,56 and (2) process difficult and often trauma-related emotions in specific ways.57 The EAET integrates both models and targets both mechanisms.26 The superiority of EAET vs CBT suggests the potential benefits of further incorporating these concepts into mainstream clinical pain medicine.
Limitations
This study has several limitations. First, the trial focused on older veterans, and findings may not be generalizable to younger patients or to nonveterans; the trial should be replicated in younger adults. Second, the trial included mostly men and a high percentage of patients with PTSD, which may have improved response to EAET. However, the sample size precluded sufficient power for a legitimate test of these issues. Third, study therapists’ backgrounds were not exactly matched between the 2 conditions. Fourth, all sessions were conducted in person; thus, whether EAET is similarly effective via telehealth is unknown. Fifth, the trial excluded patients with cognitive impairment, and these patients should be examined in future research.
Conclusions
This randomized clinical trial found that among a racially and ethnically diverse cohort of older adults with chronic musculoskeletal pain, time-limited, group-based EAET was superior to CBT on posttreatment improvements in pain severity, anxiety, depression, life satisfaction, PTSD symptoms, global satisfaction, and PGIC. Improvements in pain severity, depression, and PGIC were sustained for many participants 6 months following the intervention. In contrast to participants in CBT, participants undergoing EAET who had higher baseline depression, anxiety, and PTSD symptoms had particularly robust posttreatment pain reduction. The results suggest that EAET is a preferred intervention for medically and psychiatrically complex older patients with pain. The societal burden of chronic pain may be eased by further incorporating EAET principles into mainstream clinical pain medicine.
Trial Protocol
eTable 1. Fidelity ratings for each treatment
eTable 2. Differences between those with and without missing posttreatment or follow-up
eTable 3. Descriptive statistics for primary and secondary outcomes
eTable 4. Full results from moderation analyses on change in pain severity
Data Sharing Statement
References
- 1.Rikard SM, Strahan AE, Schmit KM, Guy GP Jr. Chronic pain among adults—United States, 2019-2021. MMWR Morb Mortal Wkly Rep. 2023;72(15):379-385. doi: 10.15585/mmwr.mm7215a1 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 2.Gibson SJ, Lussier D. Prevalence and relevance of pain in older persons. Pain Med. 2012;13(suppl 2):S23-S26. doi: 10.1111/j.1526-4637.2012.01349.x [DOI] [PubMed] [Google Scholar]
- 3.Whitlock EL, Diaz-Ramirez LG, Glymour MM, Boscardin WJ, Covinsky KE, Smith AK. Association between persistent pain and memory decline and dementia in a longitudinal cohort of elders. JAMA Intern Med. 2017;177(8):1146-1153. doi: 10.1001/jamainternmed.2017.1622 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 4.Macfarlane GJ, Barnish MS, Jones GT. Persons with chronic widespread pain experience excess mortality: longitudinal results from UK Biobank and meta-analysis. Ann Rheum Dis. 2017;76(11):1815-1822. doi: 10.1136/annrheumdis-2017-211476 [DOI] [PubMed] [Google Scholar]
- 5.Domenichiello AF, Ramsden CE. The silent epidemic of chronic pain in older adults. Prog Neuropsychopharmacol Biol Psychiatry. 2019;93:284-290. doi: 10.1016/j.pnpbp.2019.04.006 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 6.Shehab N, Lovegrove MC, Geller AI, Rose KO, Weidle NJ, Budnitz DS. US emergency department visits for outpatient adverse drug events, 2013-2014. JAMA. 2016;316(20):2115-2125. doi: 10.1001/jama.2016.16201 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 7.Al-Qurain AA, Gebremichael LG, Khan MS, et al. Prevalence and factors associated with analgesic prescribing in poly-medicated elderly patients. Drugs Aging. 2020;37(4):291-300. doi: 10.1007/s40266-019-00742-0 [DOI] [PubMed] [Google Scholar]
- 8.Kardas P, Urbański F, Lichwierowicz A, et al. The prevalence of selected potential drug-drug interactions of analgesic drugs and possible methods of preventing them: lessons learned from the analysis of the real-world national database of 38 million citizens of Poland. Front Pharmacol. 2021;11:607852. doi: 10.3389/fphar.2020.607852 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 9.Seppala LJ, van de Glind EMM, Daams JG, et al. ; EUGMS Task and Finish Group on Fall-Risk-Increasing Drugs . Fall-risk–increasing drugs: a systematic review and meta-analysis: III: others. J Am Med Dir Assoc. 2018;19(4):372.e1-372.e8. doi: 10.1016/j.jamda.2017.12.099 [DOI] [PubMed] [Google Scholar]
- 10.Saunders KW, Dunn KM, Merrill JO, et al. Relationship of opioid use and dosage levels to fractures in older chronic pain patients. J Gen Intern Med. 2010;25(4):310-315. doi: 10.1007/s11606-009-1218-z [DOI] [PMC free article] [PubMed] [Google Scholar]
- 11.Niknejad B, Bolier R, Henderson CR Jr, et al. Association between psychological interventions and chronic pain outcomes in older adults: a systematic review and meta-analysis. JAMA Intern Med. 2018;178(6):830-839. doi: 10.1001/jamainternmed.2018.0756 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 12.Williams ACC, Fisher E, Hearn L, Eccleston C. Psychological therapies for the management of chronic pain (excluding headache) in adults. doi: 10.1002/14651858.CD007407.pub3 Cochrane Database Syst Rev. 2020;8(8):CD007407. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 13.Nahin RL. Severe pain in veterans: the effect of age and sex, and comparisons with the general population. J Pain. 2017;18(3):247-254. doi: 10.1016/j.jpain.2016.10.021 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 14.Phillips KM, Clark ME, Gironda RJ, et al. Pain and psychiatric comorbidities among two groups of Iraq and Afghanistan era Veterans. J Rehabil Res Dev. 2016;53(4):413-432. doi: 10.1682/JRRD.2014.05.0126 [DOI] [PubMed] [Google Scholar]
- 15.Watrous JR, McCabe CT, Jones G, et al. Low back pain, mental health symptoms, and quality of life among injured service members. Health Psychol. 2020;39(7):549-557. doi: 10.1037/hea0000850 [DOI] [PubMed] [Google Scholar]
- 16.Beckham JC, Crawford AL, Feldman ME, et al. Chronic posttraumatic stress disorder and chronic pain in Vietnam combat veterans. J Psychosom Res. 1997;43(4):379-389. doi: 10.1016/S0022-3999(97)00129-3 [DOI] [PubMed] [Google Scholar]
- 17.Fishbain DA, Pulikal A, Lewis JE, Gao J. Chronic pain types differ in their reported prevalence of post-traumatic stress disorder (PTSD) and there is consistent evidence that chronic pain is associated with PTSD: an evidence-based structured systematic review. Pain Med. 2017;18(4):711-735. doi: 10.1093/pm/pnw065 [DOI] [PubMed] [Google Scholar]
- 18.McCracken LM, Turk DC. Behavioral and cognitive-behavioral treatment for chronic pain: outcome, predictors of outcome, and treatment process. Spine (Phila Pa 1976). 2002;27(22):2564-2573. doi: 10.1097/00007632-200211150-00033 [DOI] [PubMed] [Google Scholar]
- 19.Felitti VJ, Anda RF, Nordenberg D, et al. Relationship of childhood abuse and household dysfunction to many of the leading causes of death in adults. the Adverse Childhood Experiences (ACE) Study. Am J Prev Med. 1998;14(4):245-258. doi: 10.1016/S0749-3797(98)00017-8 [DOI] [PubMed] [Google Scholar]
- 20.Lumley MA, Yamin JB, Pester BD, Krohner S, Urbanik CP. Trauma matters: psychological interventions for comorbid psychosocial trauma and chronic pain. Pain. 2022;163(4):599-603. doi: 10.1097/j.pain.0000000000002425 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 21.Jones GT, Power C, Macfarlane GJ. Adverse events in childhood and chronic widespread pain in adult life: results from the 1958 British Birth Cohort Study. Pain. 2009;143(1-2):92-96. doi: 10.1016/j.pain.2009.02.003 [DOI] [PubMed] [Google Scholar]
- 22.Toblin RL, Quartana PJ, Riviere LA, Walper KC, Hoge CW. Chronic pain and opioid use in US soldiers after combat deployment. JAMA Intern Med. 2014;174(8):1400-1401. doi: 10.1001/jamainternmed.2014.2726 [DOI] [PubMed] [Google Scholar]
- 23.Schubiner H, Jackson B, Molina KM, et al. Racism as a source of pain. J Gen Intern Med. 2023;38(7):1729-1734. doi: 10.1007/s11606-022-08015-0 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 24.McClendon J, Essien UR, Youk A, et al. Cumulative disadvantage and disparities in depression and pain among veterans with osteoarthritis: the role of perceived discrimination. Arthritis Care Res (Hoboken). 2021;73(1):11-17. doi: 10.1002/acr.24481 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 25.McWilliams LA, Cox BJ, Enns MWJP. Mood and anxiety disorders associated with chronic pain: an examination in a nationally representative sample. Pain. 2003;106(1-2):127-133. doi: 10.1016/S0304-3959(03)00301-4 [DOI] [PubMed] [Google Scholar]
- 26.Lumley MA, Schubiner H. Emotional awareness and expression therapy for chronic pain: rationale, principles and techniques, evidence, and critical review. Curr Rheumatol Rep. 2019;21(7):30. doi: 10.1007/s11926-019-0829-6 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27.Yarns BC, Cassidy JT, Jimenez AM. At the intersection of anger, chronic pain, and the brain: a mini-review. Neurosci Biobehav Rev. 2022;135:104558. doi: 10.1016/j.neubiorev.2022.104558 [DOI] [PubMed] [Google Scholar]
- 28.Lumley MA, Cohen JL, Borszcz GS, et al. Pain and emotion: a biopsychosocial review of recent research. J Clin Psychol. 2011;67(9):942-968. doi: 10.1002/jclp.20816 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 29.Hashmi JA, Baliki MN, Huang L, et al. Shape shifting pain: chronification of back pain shifts brain representation from nociceptive to emotional circuits. Brain. 2013;136(pt 9):2751-2768. doi: 10.1093/brain/awt211 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 30.Aaron RV, Finan PH, Wegener ST, Keefe FJ, Lumley MA. Emotion regulation as a transdiagnostic factor underlying co-occurring chronic pain and problematic opioid use. Am Psychol. 2020;75(6):796-810. doi: 10.1037/amp0000678 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 31.Burger AJ, Lumley MA, Carty JN, et al. The effects of a novel psychological attribution and emotional awareness and expression therapy for chronic musculoskeletal pain: a preliminary, uncontrolled trial. J Psychosom Res. 2016;81:1-8. doi: 10.1016/j.jpsychores.2015.12.003 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 32.Thakur ER, Holmes HJ, Lockhart NA, et al. Emotional awareness and expression training improves irritable bowel syndrome: a randomized controlled trial. Neurogastroenterol Motil. 2017;29(12). doi: 10.1111/nmo.13143 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 33.Ziadni MS, Carty JN, Doherty HK, et al. A life-stress, emotional awareness, and expression interview for primary care patients with medically unexplained symptoms: a randomized controlled trial. Health Psychol. 2018;37(3):282-290. doi: 10.1037/hea0000566 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 34.Carty JN, Ziadni MS, Holmes HJ, et al. The effects of a life stress emotional awareness and expression interview for women with chronic urogenital pain: a randomized controlled trial. Pain Med. 2019;20(7):1321-1329. doi: 10.1093/pm/pny182 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 35.Ziadni MS, Sturgeon JA, Lumley MA. “Pain, stress, and emotions”: uncontrolled trial of a single-session, telehealth, emotional awareness and expression therapy class for patients with chronic pain. Front Pain Res (Lausanne). 2022;3:1028561. doi: 10.3389/fpain.2022.1028561 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 36.Maroti D, Lumley MA, Schubiner H, et al. Internet-based emotional awareness and expression therapy for somatic symptom disorder: a randomized controlled trial. J Psychosom Res. 2022;163:111068. doi: 10.1016/j.jpsychores.2022.111068 [DOI] [PubMed] [Google Scholar]
- 37.Maroti D, Ek J, Widlund RM, et al. Internet-administered emotional awareness and expression therapy for somatic symptom disorder with centralized symptoms: a preliminary efficacy trial. Front Psychiatry. 2021;12:620359. doi: 10.3389/fpsyt.2021.620359 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 38.Krohner S, Yamin JB, Ziadni MS, Carty McIntosh JN, Schubiner H, Lumley MA. Emotional awareness and expression interview: examining interview content and patient experiences in two medical samples. J Clin Psychol Med Settings. 2023;30(3):520-530. doi: 10.1007/s10880-022-09913-5 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 39.Yarns BC, Molaie AM, Lumley MA, et al. Video telehealth emotional awareness and expression therapy for older U.S. military veterans with chronic pain: a pilot study. Clin Gerontol. 2024;47(1):136-148. doi: 10.1080/07317115.2022.2159909 [DOI] [PubMed] [Google Scholar]
- 40.Lumley MA, Schubiner H, Lockhart NA, et al. Emotional awareness and expression therapy, cognitive behavioral therapy, and education for fibromyalgia: a cluster-randomized controlled trial. Pain. 2017;158(12):2354-2363. doi: 10.1097/j.pain.0000000000001036 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 41.Yarns BC, Lumley MA, Cassidy JT, et al. Emotional awareness and expression therapy achieves greater pain reduction than cognitive behavioral therapy in older adults with chronic musculoskeletal pain: a preliminary randomized comparison trial. Pain Med. 2020;21(11):2811-2822. doi: 10.1093/pm/pnaa145 [DOI] [PubMed] [Google Scholar]
- 42.Folstein MF, Folstein SE, McHugh PR. “Mini-Mental State”: a practical method for grading the cognitive state of patients for the clinician. J Psychiatr Res. 1975;12(3):189-198. doi: 10.1016/0022-3956(75)90026-6 [DOI] [PubMed] [Google Scholar]
- 43.Lumley MA, Schubiner H. Emotional Awareness and Expression Therapy (EAET): A Group-Based Treatment Manual For Patients With Fibromyalgia And Related Centralized Pain Disorders (Version 2). Wayne State University; 2012/2017. [Google Scholar]
- 44.Murphy JL, McKellar JD, Raffa SD, Clark ME, Kerns RD, Karlin BE. Cognitive Behavioral Therapy for Chronic Pain Among Veterans: Therapist Manual. US Department of Veterans Affairs; 2014. [Google Scholar]
- 45.Yarns BC, Zhu TA, Najafian Jazi A. Chronic pain in older adults: a neuroscience-based psychological assessment and treatment approach. Am J Geriatr Psychiatry. 2022;30(12):1342-1350. doi: 10.1016/j.jagp.2022.07.009 [DOI] [PubMed] [Google Scholar]
- 46.Tan G, Jensen MP, Thornby JI, Shanti BF. Validation of the Brief Pain Inventory for chronic nonmalignant pain. J Pain. 2004;5(2):133-137. doi: 10.1016/j.jpain.2003.12.005 [DOI] [PubMed] [Google Scholar]
- 47.Hsu MC, Schubiner H, Lumley MA, Stracks JS, Clauw DJ, Williams DA. Sustained pain reduction through affective self-awareness in fibromyalgia: a randomized controlled trial. J Gen Intern Med. 2010;25(10):1064-1070. doi: 10.1007/s11606-010-1418-6 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 48.Pilkonis PA, Choi SW, Reise SP, Stover AM, Riley WT, Cella D; PROMIS Cooperative Group . Item banks for measuring emotional distress from the Patient-Reported Outcomes Measurement Information System (PROMIS): depression, anxiety, and anger. Assessment. 2011;18(3):263-283. doi: 10.1177/1073191111411667 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 49.Cella D, Riley W, Stone A, et al. ; PROMIS Cooperative Group . The Patient-Reported Outcomes Measurement Information System (PROMIS) developed and tested its first wave of adult self-reported health outcome item banks: 2005-2008. J Clin Epidemiol. 2010;63(11):1179-1194. doi: 10.1016/j.jclinepi.2010.04.011 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 50.Salsman JM, Lai JS, Hendrie HC, et al. Assessing psychological well-being: self-report instruments for the NIH Toolbox. Qual Life Res. 2014;23(1):205-215. doi: 10.1007/s11136-013-0452-3 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 51.Amtmann D, Cook KF, Jensen MP, et al. Development of a PROMIS item bank to measure pain interference. Pain. 2010;150(1):173-182. doi: 10.1016/j.pain.2010.04.025 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 52.Yu L, Buysse DJ, Germain A, et al. Development of short forms from the PROMIS sleep disturbance and sleep-related impairment item banks. Behav Sleep Med. 2011;10(1):6-24. doi: 10.1080/15402002.2012.636266 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 53.Arnold LM, Lu Y, Crofford LJ, et al. A double-blind, multicenter trial comparing duloxetine with placebo in the treatment of fibromyalgia patients with or without major depressive disorder. Arthritis Rheum. 2004;50(9):2974-2984. doi: 10.1002/art.20485 [DOI] [PubMed] [Google Scholar]
- 54.Oei TPS, Green AL. The Satisfaction With Therapy and Therapist Scale–Revised (STTS-R) for group psychotherapy: psychometric properties and confirmatory factor analysis. Prof Psychol Res Pr. 2008;39(4):435-442. doi: 10.1037/0735-7028.39.4.435 [DOI] [Google Scholar]
- 55.Bovin MJ, Marx BP, Weathers FW, et al. Psychometric properties of the PTSD Checklist for Diagnostic and Statistical Manual of Mental Disorders–Fifth Edition (PCL-5) in veterans. Psychol Assess. 2016;28(11):1379-1391. doi: 10.1037/pas0000254 [DOI] [PubMed] [Google Scholar]
- 56.Ashar YK, Gordon A, Schubiner H, et al. Effect of pain reprocessing therapy vs placebo and usual care for patients with chronic back pain: a randomized clinical trial. JAMA Psychiatry. 2022;79(1):13-23. doi: 10.1001/jamapsychiatry.2021.2669 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 57.Abbass A, Town J, Holmes H, et al. Short-term psychodynamic psychotherapy for functional somatic disorders: a meta-analysis of randomized controlled trials. Psychother Psychosom. 2020;89(6):363-370. doi: 10.1159/000507738 [DOI] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Supplementary Materials
Trial Protocol
eTable 1. Fidelity ratings for each treatment
eTable 2. Differences between those with and without missing posttreatment or follow-up
eTable 3. Descriptive statistics for primary and secondary outcomes
eTable 4. Full results from moderation analyses on change in pain severity
Data Sharing Statement
