



ABSTRACT
Objectives:
Pelvic floor disorders (PFDs) such as stress urinary incontinence (SUI) and pelvic organ prolapse (POP) can be managed through conservative treatments, such as conservative management involving biofeedback (BF) and electrostimulation. This study aimed to investigate the therapeutic effects of conservative treatments on PFDs.
Materials and Methods:
A retrospective cohort study was conducted. Women with PFD who underwent 1–3 months of BF and electrostimulation between January 1, 2020, and January 31, 2021, were included in the study. BF treatment was administered using three sensors to monitor pelvic floor muscle activity, providing patients with immediate feedback and guidance on muscle exercises. One session lasted for 5–10 min. Electrostimulation treatment utilized a specially made pelvic belt with electrode sheets to stimulate and contract pelvic floor muscles passively. One session lasted for 15 min. Six therapies in 1 month were prescribed. Pre- and post-treatment Pelvic Floor Distress Inventory (PFDI-20) scores, including POP distress inventory 6 (POPDI-6), colorectal-anal distress inventory (CRAD-8), and urinary distress inventory 6 (UDI-6) scores, were compared. Subgroup analysis by age, menopause, body mass index (BMI), and child delivery mode was performed.
Results:
The study included 51 women with PFDs (SUI, POP, frequency or urgency or nocturia, and pain) treated with BF and electrostimulation, with a mean age of 49.94 ± 13.63 years. Sixteen patients (37.1%) were menopausal, with a mean menopause age of 50 ± 5.20 years. Twenty-six patients (68.4%) had a history of normal vaginal delivery. The mean PFDI-20 scores before and after treatment were 32.67 (standard deviation [SD] 10.05) and 25.99 (SD 9.61), respectively (P < 0.001). This decrease in scores reflected an improvement in subjective perceptions of symptoms and quality of life. The POPDI-6, CRAD-8, and UDI-6 scores significantly decreased after treatment. Subgroup analysis of scores change regarding age, menopause, BMI, and child delivery mode was not statistically significant.
Conclusion:
The study demonstrated the effectiveness of BF and electrostimulation for treating women with PFDs. The findings contributed to the understanding of treatment duration, patient characteristics, and the potential benefits of a multimodal approach. Moreover, the study’s diverse participant population and the use of validated outcome measures enhance the generalizability and scientific rigor of the findings.
KEYWORDS: Biofeedback, Electrostimulation, Pelvic organ prolapse, Pelvic pain, Stress urinary incontinence
INTRODUCTION
Pelvic floor disorders (PFDs) affect many women throughout their lifetime [1]. PFDs considerably impact women’s quality of life, affecting their physical, emotional, and social well-being [2]. While the prevalence of PFDs is reported to be lower in Asian women (6%), it is still a prevalent issue globally [3].
PFDs involve the dysfunction of the pelvic floor muscles and surrounding structures. These disorders include urinary incontinence, pelvic organ prolapse (POP), pelvic pain, and bowel dysfunction [4]. These symptoms can significantly impact a woman’s daily life, making it essential to seek appropriate treatment. The risk factors of PFDs are variable, including older age, weight, parity, and a history of hysterectomy [5]. It is, therefore, essential to identify these risk factors and take appropriate measures to prevent or manage PFDs.
The two main treatment options for PFDs are conservative and surgical management. Conservative management involves noninvasive methods such as pelvic floor muscle training (PFMT), biofeedback (BF), and electrostimulation, which help train and strengthen the pelvic floor muscles [6].
BF is a technique commonly used in conjunction with PFMT. It involves using specialized devices or sensors to provide real-time information about muscle activity and function [7]. By visualizing or receiving auditory cues based on the measurements, patients can learn to identify and engage their pelvic floor muscles correctly [8]. BF helps individuals develop greater awareness and control over their muscles, optimizing the effectiveness of PFMT [9].
Electrostimulation, also known as electrical stimulation or neuromuscular electrical stimulation, is another adjunctive therapy often used alongside PFMT [10]. It involves the application of electrical currents to the pelvic floor muscles, causing muscle contractions. Electrostimulation can benefit individuals with difficulty voluntarily activating their pelvic floor muscles or those needing additional support in strengthening and retraining the muscles [11].
The Pelvic Floor Distress Inventory-20 (PFDI-20) is a validated questionnaire commonly used to assess and evaluate the symptoms and impact of PFDs. It focuses on three specific aspects of PFDs: POP, urinary, and fecal incontinence [12]. The PFDI-20 is a valuable tool in clinical and research settings to assess the symptoms and impact of PFDs, allowing health-care professionals to better understand and evaluate the effectiveness of interventions and treatment strategies for individuals with PFDs [13].
We hypothesized conservative treatment with BF and electrostimulation might have a positive therapeutic effect on PFD. Therefore, this study aimed to explore the therapeutic effects of conservative treatments, including BF and electrostimulation, on PFDs and evaluate them using the PFDI-20. By utilizing this approach, we can better understand the impact of conservative treatments on the physical and emotional well-being of women with PFDs.
MATERIALS AND METHODS
Ethics
This study was approved by the research ethics committee of our hospital (IRB 112–068-B) and conducted in accordance with the Declaration of Helsinki. We retrospectively analyzed the data of patients with PFD who underwent conservative treatment in our hospital between January 1, 2020, and January 31, 2021. The research ethics committee waived the requirement for informed consent because of the low risk to the patient’s safety. All methods were implemented in compliance with the relevant guidelines and regulations.
Study population
A retrospective study design was employed to enroll women with the symptoms of PFDs who received conservative treatment with BF and electrostimulation.
Inclusion criteria
Women with PFD (stress urinary incontinence [SUI], frequency or urgency or nocturia, pelvic pain, and POP) received conservative treatment (BF and electrical stimulation). Women with PFD were diagnosed in the OPD by a gynecologist or urogynecologist. They were not treated before. They did not receive medication simultaneously, except for those with pelvic pain who may have received analgesics. SUI was diagnosed by the patient’s symptoms or an urodynamic study. The patient’s symptoms were diagnosed as frequent urination. A urine examination was performed to exclude urinary tract infections. Pelvic pain was diagnosed by the patient’s symptoms and per vaginal examination (found pelvic muscle pain). POP was diagnosed by per vaginal examination to find a cystocele, uterine prolapse, or rectocele.
Exclusion criteria
Women with PFD could not receive conservative treatment, would not like to receive treatment, quit therapy, or lose follow-up. Patients with a cancer history, surgery, or radiotherapy over the pelvic cavity or relevant neurological history were also excluded from the study.
Patients’ information was collected from their medical records, and patients were categorized into subgroups based on age, weight, menopausal status, body mass index (BMI), and type of delivery (vaginal, cesarean, or both) for further analysis.
Biofeedback and electrostimulation
During BF treatment (WPM M1E2; MMS, Enschede, Netherlands), three sensors were placed to detect the electrical activity of the pelvic floor muscles. Two sensors were placed laterally at the anus and one at the inner thigh to monitor muscle contraction and relaxation. Patients were taught the exercise technique and received immediate feedback on whether they were correctly exercising their muscles. An assistant monitored the patients’ progress and provided feedback on whether they were using the correct muscles by observing the monitor. The treatment duration lasted for 5–10 min. If the patient could not contract the correct muscle, the treatment would be longer, 10–20 min. Patients without pain symptoms received combined electrostimulation treatment.
Pelvic muscle exercise was recommended to perform 15 exercises three times in 1 day [14]. The initial duration of each individual contraction was established by assessing the capabilities demonstrated by each patient during the initial training session. Throughout subsequent sessions, the duration of contractions was progressively extended, reaching a maximum of 10 s, followed by an equal duration of relaxation between contractions. Patients were encouraged to practice the exercises in different positions, such as lying, sitting, and standing, and were advised to incorporate them into their daily activities whenever feasible. In addition, they were instructed to actively engage their pelvic floor muscles during activities that previously caused incontinence and to practice interrupting or slowing the urinary stream during voiding at least once daily. The duration of self-pelvic muscle training was the same as the treatment duration, ranging from 1 to 3 months.
For electrostimulation, patients were instructed to wear a specially made “pelvic belt” containing four electrode sheets (WSB101C, SHINE ALPHA ELECTRONIC CO., LTD, Taoyuan, Taiwan). Two electrode sheets were placed on the lower abdomen and one on each posterior thigh. The electrode sheets directly contacted the skin and could provide six different types of current frequency. The protocol involved a 15-min session, during which electrical stimulation was administered for 10–15 s intermittently, stimulating and contracting the patient’s pelvic floor muscles passively. Each patient received two different protocols for two types of frequency simultaneously. In addition, patients without pain symptoms received BF treatment in combination with electrostimulation.
Treatment protocol
The intervention protocol was six times in 1 month (or 1–2 times in 1 week). The duration of treatment ranged from 1 month to 3 months, depending on the patient’s preference. Patients with pelvic pain received electrostimulation treatment only.
Posttreatment evaluation
We utilized the PFDI-20 as a self-reported questionnaire to assess disease severity before the intervention and the subjective improvement after the intervention. The PFDI-20 consists of three distinct parts: the POP distress inventory-6 (POPDI-6), the Colorectal-Anal Distress Inventory-8 (CRAD-8), and the urinary distress inventory-6 (UDI-6). The questionnaire consisted of 20 items, each scored from 0 to 4, and aimed to measure the degree to which the symptoms had affected the patients. The lower scores mean a better outcome. The questionnaire was collected before and immediately after completing conservative treatment.
Outcomes
The primary outcome of this study was the improvement of pre- and post-treatment PFDI-20 scores collected after patients had received at least five treatment courses. The score difference was used to assess the extent of clinical improvement before and after the intervention. Secondary outcomes included subgroup analysis of score change regarding age, menopause status, BMI, and child delivery modes.
Statistical analysis
The primary outcome was analyzed using the paired t-test to compare the pre- and post-treatment PFDI-20 scores. The differences in the extent of average changes in the PFDI-20, POPDI-6, CRAD-8, and UDI-6 scores between subgroups were compared using the exchangeable generalized estimating equations (GEEs) model. The GEE model was also used to find the variables associated with various scores (outcome: PFDI-20, POPDI-6, CRAD-8, and UDI-6 and covariates: age, menopause, parity, indication, and treatment). All statistical analyses were performed using SPSS 24.0 (IBM Corp., Armonk, NY, USA), and statistical significance was set at P < 0.05.
RESULTS
Demographic characteristics
Fifty-one women with PFDs who underwent conservative treatment between January 1, 2020, and January 31, 2021, were included in this study. The demographic characteristics of the patients are summarized in Table 1. The mean age of the patients was 49.94 ± 13.63 years, with ages ranging from 25 to 81 years. Sixteen patients (37.1%) were menopausal, and the mean menopause age was 50 ± 5.20 years. In addition, 26 patients (68.4%) had a history of normal vaginal delivery. The dominant PFD symptom was SUI, followed by pelvic pain, frequency or urgency or nocturia, and POP [Table 1]. POP stages were cystocele, Stage 2 (n = 2); cystocele, Stage 1 (n = 1); and uterine prolapse, Stage 3 (n = 1). One patient with POP received a pelvic reconstruction surgery 2 years after conservative treatment.
Table 1.
Patient characteristics
| Characteristic | Mean±SD, n (%), or median (Q1, Q3) |
|---|---|
| Age (years) (n=51) | 49.94±13.63 |
| BMI (kg/m2) (n=13)* | 26.28±6.44 |
| Menopause (n=43)* | |
| No | 27 (62.79) |
| Yes | 16 (37.21) |
| Age at menopause* | 50±5.20 |
| Parity | 40 (78.4) |
| NSD | 26 (68.42) |
| C/S | 6 (15.79) |
| NSD+C/S | 6 (15.79) |
| Number of childbirths | 2 (2, 3) |
| Nulliparity | 8 (15.6) |
| Indications | |
| Stress urinary incontinence | 21 (41.2) |
| Frequency or urgency or nocturia | 10 (19.6) |
| Pelvic organ prolapse | 4 (7.8) |
| Pelvic pain | 16 (31.3) |
*Some patients were missing data. NSD: Normal spontaneous delivery, C/S: Cesarean section, BMI: Body mass index, SD: Standard deviation, Q1: First quartile, Q3: Third quartile
Changes in the Pelvic Floor Distress Inventory-20 score before and after treatment
The mean PFDI-20 score before the intervention was 32.67 (standard deviation [SD] 10.05), and the mean score after the intervention was 25.99 (SD 9.61) [Table 1, P < 0.001]. This indicates an improvement in subjective perceptions of symptoms and quality of life. Similar results were observed for the POPDI-6, CRAD-8, and UDI-6 scores [Table 2]. The percentage of decrease in various scores is illustrated in Figure 1.
Table 2.
PFDI-20 scores before and after treatment
| Item | n | Mean±SD | Percentage of pretreatment, n (%) | P | ||
|---|---|---|---|---|---|---|
|
| ||||||
| Before treatment | After treatment | Difference | ||||
| PFDI-20 | 51 | 32.67±10.05 | 25.99±9.61 | −6.68±5.04 | −20.45 | <0.001 |
| POPDI-6 | 51 | 10.08±3.93 | 7.74±3.23 | −2.34±1.95 | −23.21 | <0.001 |
| CRAD-8 | 51 | 11.67±4.89 | 9.86±4.45 | −1.80±2.36 | −15.51 | <0.001 |
| UDI-6 | 51 | 10.92±3.38 | 8.39±3.19 | −2.53±2.22 | −23.17 | <0.001 |
SD: Standard deviation. PFDI-20: Pelvic Floor Distress Inventory-20, POPDI-6: Pelvic organ prolapse distress inventory-6, CRAD-8: Colorectal-Anal Distress Inventory, UDI-6: Urinary distress inventory 6
Figure 1.
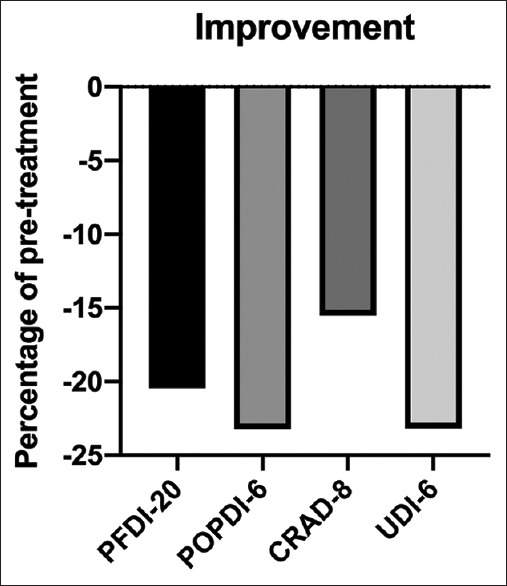
Changes (percentage of pretreatment) in the Pelvic Floor Distress Inventory-20, pelvic organ prolapse distress inventory-6, Colorectal-Anal Distress Inventory-8, and urinary distress inventory-6 scores after conservative treatment with biofeedback and electrostimulation for pelvic floor disorders. PFDI-20: Pelvic Floor Distress Inventory-20, POPDI-6: pelvic organ prolapse distress inventory-6, CRAD-8: colorectal-Anal Distress Inventory, UDI-6: urinary distress inventory 6
Subgroup analyses
We performed a subgroup analysis for age and menopause status [Table 3]. The scores of all scales significantly decreased after the intervention regardless of the patient’s age or menopausal status. There was no significant difference in the extent of score improvement between patients younger and older than 50 years and between those who had undergone menopause and those who had not.
Table 3.
Pre- and post-treatment : Pelvic Floor Distress Inventory-20 scores were stratified by age, menopausal status, and body mass index
| Item | n | Mean±SD | Within-group P | Between-group P | ||
|---|---|---|---|---|---|---|
|
| ||||||
| Before treatment | After treatment | Difference | ||||
| AGE ≤50 years | 26 | 33.12±10.53 | 26.35±10.63 | −6.77±5.07 | <0.001 | 0.876 |
| AGE >50 years | 25 | 32.20±9.73 | 25.62±8.62 | −6.58±5.11 | <0.001 | |
| Not menopausal | 27 | 33.11±11.52 | 25.96±10.82 | −7.15±5.57 | <0.001 | 0.501 |
| Menopausal | 16 | 30.81±9.38 | 24.59±9.48 | −6.22±5.10 | <0.001 | |
| BMI <25 kg/m2 | 7 | 40.00±6.73 | 33.29±2.29 | −6.71±5.62 | 0.018 | <0.001 |
| BMI ≥25 kg/m2 | 6 | 30.50±15.96 | 21.33±15.78 | −9.17±6.91 | 0.028 | |
BMI: Body mass index, SD: Standard deviation, PFDI-20: Pelvic Floor Distress Inventory-20
We also performed a subgroup analysis based on BMI [Table 3]. We divided the patients into BMI <25 kg/m2 (n = 7) and ≥25 kg/m2 (n = 6). We observed a significant improvement in the PFDI-20 scores after treatment compared to scores before treatment in the two groups. A significant difference in the PFDI-20 scores was also noted between the two groups.
Next, we performed a subgroup analysis based on the mode of delivery [Table 4]. The patients were divided into vaginal delivery (VD), cesarean section (C/S), and mixed (VD + C/S) subgroups after conservative treatment; PFDI-20, POPDI-6, and UDI-6 scores were significantly decreased in all groups [Table 4]. However, there was no significant reduction in the CRAD-8 score in C/S and NSD + C/S after treatment. No significant difference in the extent of improvement in scores among all the subgroups [Table 4].
Table 4.
Pre- and post-treatment pelvic floor distress inventory-20 scores stratified by mode of delivery (n=40)
| Item | n | Mean±SD | Within-group P | Between-group P | ||
|---|---|---|---|---|---|---|
|
| ||||||
| Before | After | Difference | ||||
| PFDI-20 | ||||||
| NSD | 26 | 30.46±11.33 | 24.85±10.87 | −5.62±4.68 | <0.001 | 0.744 (vs. C/S) |
| C/S | 6 | 38.17±8.66 | 30.00±5.59 | −8.17±5.64 | <0.001 | >0.99 (vs. both) |
| NSD+C/S | 6 | 37.50±9.87 | 29.08±9.75 | −8.42±4.43 | 0.0277 | 0.617 (vs. NSD) |
| POPDI-6 | ||||||
| NSD | 26 | 8.89±3.94 | 7.04±3.34 | −1.85±2.07 | <0.001 | >0.99 (vs. C/S) |
| C/S | 6 | 11.83±2.64 | 9.33±1.51 | −2.50±1.22 | 0.0256 | >0.99 (vs. both) |
| NSD+C/S | 6 | 13.17±4.62 | 9.58±4.57 | −3.58±1.74 | 0.0277 | 0.164 (vs. NSD) |
| CRAD-8 | ||||||
| NSD | 26 | 11.04±5.29 | 9.50±4.97 | −1.54±2.08 | 0.001 | 0.846 (vs. C/S) |
| C/S | 6 | 12.83±7.31 | 10.17±5.56 | −2.67±2.94 | 0.0656 | >0.99 (vs. both) |
| NSD+C/S | 6 | 13.00±3.03 | 11.00±2.61 | −2.00±2.45 | 0.0656 | >0.99 (vs. NSD) |
| UDI-6 | ||||||
| NSD | 26 | 10.54±3.67 | 8.31±3.47 | −2.23±2.12 | <0.001 | >0.99 (vs. C/S) |
| C/S | 6 | 13.50±2.26 | 10.5±1.64 | −3.00±2.53 | 0.0422 | >0.99 (vs. both) |
| NSD+C/S | 6 | 11.33±3.67 | 8.50±2.66 | −2.83±2.14 | 0.0269 | >0.99 (vs. NSD) |
PFDI-20: Pelvic floor distress inventory-20, POPDI-6: Pelvic organ prolapse distress inventory-6, CRAD-8: Colorectal-Anal Distress Inventory, UDI-6: Urinary distress inventory 6, SD: Standard deviation, NSD: Normal spontaneous delivery, C/S: Cesarean section
Finally, the GEE model was employed to identify factors linked with the different scores [Table 5]. Notably, scores for various parameters were notably higher in the C/S group compared to the nulliparity group.On adjusting for several variables (age, menopause, mode of delivery, and indications), there was a significant enhancement in scores (PFDI-20, POPDI-6, CRAD-8, and UDI-6) after treatment compared to before treatment. In conclusion, women experiencing PFD exhibited symptom improvement following BF and electrostimulation interventions.
Table 5.
Factors associated with various scores through the Generalized estimating equations model
| Predictor | PFDI-20 | POPDI-6 | CRAD-8 | UDI-6 | ||||
|---|---|---|---|---|---|---|---|---|
|
|
|
|
|
|||||
| β (95% CI) | P | β (95% CI) | P | β (95% CI) | P | β(95% CI) | P | |
| Intercept | 33.40 (23.57–43.23) | <0.001* | 10.06 (6.24–13.88) | <0.001* | 14.48 (8.93–20.02) | <0.001* | 8.86 (5.69–12.03) | <0.001* |
| Age | −0.11 (−0.32–0.11) | 0.343 | −0.04 (−0.12–0.04) | 0.336 | −0.09 (−0.21–0.02) | 0.121 | 0.03 (−0.04–0.10) | 0.478 |
| Menopause (yes versus. no) | −0.35 (−10.35–9.66) | 0.946 | 0.19 (−2.94–3.32) | 0.905 | 0.32 (−4.65–5.30) | 0.898 | −0.86 (−4.34–2.62) | 0.627 |
| Parity | ||||||||
| Nulliparity | Reference | Reference | Reference | Reference | ||||
| NSD | 4.12 (−4.74–12.98) | 0.362 | 0.82 (−1.97–3.61) | 0.565 | 1.46 (−2.77–5.69) | 0.499 | 1.84 (−0.51–4.19) | 0.124 |
| C/S | 10.75 (3.56–17.95) | 0.003* | 2.58 (0.60–4.57) | 0.011* | 4.44 (0.73–8.15) | 0.019* | 3.73 (1.57–5.89) | 0.001* |
| NSD+C/S | 9.19 (−4.75–23.12) | 0.196 | 4.17 (−2.33–10.66) | 0.208 | 2.63 (−1.31–6.58) | 0.191 | 2.39 (−1.84–6.61) | 0.269 |
| Indication | ||||||||
| Stress urinary incontinence | Reference | Reference | Reference | Reference | ||||
| Frequency or urgency or nocturia | 1.78 (−5.95–9.52) | 0.651 | 0.80 (−1.72–3.31) | 0.535 | 0.64 (−3.01–4.30) | 0.730 | 0.34 (−2.53–3.22) | 0.814 |
| Pelvic organ prolapse | −6.51 (−21.03–8.01) | 0.380 | −1.18 (−7.76–5.40) | 0.725 | −1.64 (−6.04–2.77) | 0.466 | −3.69 (−8.25–0.87) | 0.112 |
| Pelvic pain | −3.93 (−12.42–4.55) | 0.363 | −0.43 (−3.22–2.35) | 0.760 | −1.49 (−5.50–2.51) | 0.465 | −2.01 (−4.44–0.43) | 0.107 |
| Treatment (after versus before) | −6.74 (−8.37–−5.12) | <0.001* | −2.30 (−2.91–−1.70) | <0.001* | −1.76 (−2.46–−1.05) | <0.001* | −2.68 (−3.39–−1.98) | <0.001* |
*P<0.05 was considered statistically significant after the test. CI: Confidence interval, PFDI-20: Pelvic floor distress inventory-20, POPDI-6: Pelvic organ prolapse distress inventory-6, CRAD-8: Colorectal-Anal Distress Inventory, UDI-6: Urinary distress inventory 6, NSD: Normal spontaneous delivery, C/S: Cesarean section
DISCUSSION
PFD is a common condition that affects women of all ages. It can cause various symptoms, including urinary and fecal incontinence, POP, and sexual dysfunction [15]. Conservative treatments for PFD, including BF and electrostimulation, have gained attention in recent years as effective options [16]. Our study aimed to investigate the effectiveness of PFMT combined with electromyography BF (EMG-BF) and electrostimulation therapy in women with PFD. We found that conservative treatments, including BF and electrostimulation, significantly reduced PFD symptoms in the entire cohort, as measured by the PFDI-20 questionnaire, which includes the POPDI-6, CRAD-8, and UDI-6 subscales. Our results are supported by a systematic review and meta-analysis of 21 studies, which suggested that PFMT combined with EMG-BF achieved better outcomes than PFMT alone for managing SUI or PFD [16].
Although the previous research has suggested that menopause may increase the incidence of PFD [17], other studies, such as one conducted by Quiroz et al., have found no significant association between menopause and PFD [18]. However, biological evidence supports the notion that menopause can cause PFD through a decrease in estrogen, which is known to affect estrogen receptor expression in the female genital tract and surrounding muscle and connective tissue [19,20]. The previous studies have demonstrated the effectiveness of PFMT with or without BF in improving the quality of life for postmenopausal women with SUI [21], as well as the benefits of combining PFMT with estrogen therapy for perimenopausal women who have received hysterectomies [22]. Our study found that menopause status was not significantly associated with the effectiveness of PFMT plus EMG-BF combined with electrostimulation therapy for PFD in women. However, we found that PFMT plus EMG-BF therapy effectively improved PFD symptoms for all women, regardless of menopause status.
The prevalence of PFD may increase with age, and several studies suggest that age is a significant risk factor for developing PFD. For instance, one study found that the prevalence of urinary incontinence (a common form of PFD) increased with age in women, with postmenopausal women being more likely to experience urinary incontinence than premenopausal women [23]. Another study identified age as a significant risk factor for developing POP, another form of PFD, with women over the age of 40 years being more likely to develop POP than younger women [24]. In addition, a study reported a reverse relationship between age and pelvic floor muscle strength, with increased age associated with weaker pelvic muscle strength [25]. Overall, there is evidence suggesting that age may affect PFD. However, we found no significant association between age and the effectiveness of PFMT plus EMG-BF combined with electrostimulation therapy for PFD in women. Regardless of age, PFMT plus EMG-BF therapy effectively improved PFD symptoms for all women.
We found no significant difference in the extent of CRAD-8 score improvement in patients with different BMIs. We hypothesize that this is because fecal incontinence may not be strongly associated with obesity [26]. Although some studies suggest that anal sphincteroplasty may be less successful in obese patients [27], a large-scale study examining the relationship between fecal incontinence and obesity is needed to understand this association better.
A study by van Veelen et al. found that pelvic floor distensibility increased after the first childbirth, which could contribute to pelvic floor dysfunction, regardless of the delivery mode [28]. We found no significant difference in the extent of score improvement between women who delivered through CS and those who had a VD (P = 0.744, >0.99, 0.846, and > 0.99 for the PFDI-20, POPDI-6, CRAD-8, and UDI-6 scores, respectively). Therefore, our findings suggest that EMG-BF combined with electrostimulation therapy may be effective in improving pelvic floor function regardless of the mode of delivery.
A previous study examining why BF has a significant effect on PFDs found that patients who responded to BF had a significant deactivation of the dorsal anterior cingulate cortex (dACC)/supplementary motor area (SMA), which is located in the prefrontal area [29]. When there is a threat of leakage in a patient with urinary incontinence, the dACC/SMA are further activated, and the patient has urinary urgency along with sphincter tightening [29], which does not occur in healthy individuals. Therefore, the deactivation of the dACC/SMA improves the symptoms of individuals with urinary incontinence [29].
Limitations
The major limitation of our study is the small number of participants, which limits the generalizability of our findings. Further randomized controlled trials with larger sample sizes should be performed to confirm our results. Second, the current study solely assessed outcomes through questionnaires, without delving into objective parameters such as bladder volume and POP stage. Third, the inquiry into the sustainability of the therapeutic effect was omitted from this study. In addition, patients with PFD commonly manifest a combination of lower urinary tract symptoms, pelvic pain, POP, and bowel issues, which may stem from distinct underlying pathophysiology. Aggregating such diverse cases could impede robust clinical judgment. Furthermore, certain participants in our study did not undergo an adequate treatment duration (the recommended 3 months), and there might have been a placebo effect in play. Finally, due to the limited cases with a low BMI, cautious interpretation of the data is warranted.
CONCLUSIONS
The study’s implications for the scientific community and clinical practice lie in its demonstration of the effectiveness of BF and electrostimulation for treating women with PFDs. The findings contribute to understanding treatment duration, patient characteristics, and the potential benefits of a multimodal approach. Moreover, the study’s diverse participant population and the use of validated outcome measures enhance the generalizability and scientific rigor of the findings. Further large-scale prospective trials are required to substantiate the findings of our study.
Data availability statement
The dataset is not available for public access but is available from the corresponding author upon reasonable request.
Financial support and sponsorship
This study was supported by the Hualien Tzu Chi Hospital (student–doctor research project) and Buddhist Tzu Chi Medical Foundation.
Conflicts of interest
Dr.Dah-Ching Ding, an editorial board member at Tzu Chi Medical Journal, had no role in the peer review process of or decision to publish this article. The other authors declared no conflicts of interest in writing this paper.
Acknowledgment
The authors thank Hualien Tzu Chi Hospital, the Department of Medical Research, and the Statistical Consultation Center for providing statistical consultation assistance.
REFERENCES
- 1.Wu JM, Vaughan CP, Goode PS, Redden DT, Burgio KL, Richter HE, et al. Prevalence and trends of symptomatic pelvic floor disorders in U. S. Women. Obstet Gynecol. 2014;123:141–8. doi: 10.1097/AOG.0000000000000057. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 2.Benti Terefe A, Gemeda Gudeta T, Teferi Mengistu G, Abebe Sori S. Determinants of pelvic floor disorders among women visiting the gynecology outpatient department in Wolkite University Specialized Center, Wolkite, Ethiopia. Obstet Gynecol Int 2022. 2022 doi: 10.1155/2022/6949700. 6949700. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.Kenne KA, Wendt L, Brooks Jackson J. Prevalence of pelvic floor disorders in adult women being seen in a primary care setting and associated risk factors. Sci Rep. 2022;12:9878. doi: 10.1038/s41598-022-13501-w. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 4.Hallock JL, Handa VL. The epidemiology of pelvic floor disorders and childbirth: An update. Obstet Gynecol Clin North Am. 2016;43:1–13. doi: 10.1016/j.ogc.2015.10.008. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 5.Beketie ED, Tafese WT, Assefa ZM, Berriea FW, Tilahun GA, Shiferaw BZ, et al. Symptomatic pelvic floor disorders and its associated factors in South-Central Ethiopia. PLoS One. 2021;16:e0254050. doi: 10.1371/journal.pone.0254050. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 6.Friedman B. Conservative treatment for female stress urinary incontinence: Simple, reasonable and safe. Can Urol Assoc J. 2012;6:61–3. doi: 10.5489/cuaj.12021. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 7.Kopańska M, Torices S, Czech J, Koziara W, Toborek M, Dobrek Ł. Urinary incontinence in women: Biofeedback as an innovative treatment method. Ther Adv Urol. 2020;12 doi: 10.1177/1756287220934359. 1756287220934359. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 8.Cho ST, Kim KH. Pelvic floor muscle exercise and training for coping with urinary incontinence. J Exerc Rehabil. 2021;17:379–87. doi: 10.12965/jer.2142666.333. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 9.Herderschee R, Hay-Smith EJ, Herbison GP, Roovers JP, Heineman MJ. Feedback or biofeedback to augment pelvic floor muscle training for urinary incontinence in women. Cochrane Database Syst Rev. 2011;7 doi: 10.1002/14651858.CD009252. CD009252. [DOI] [PubMed] [Google Scholar]
- 10.Li W, Hu Q, Zhang Z, Shen F, Xie Z. Effect of different electrical stimulation protocols for pelvic floor rehabilitation of postpartum women with extremely weak muscle strength: Randomized control trial. Medicine (Baltimore) 2020;99:e19863. doi: 10.1097/MD.0000000000019863. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 11.Sarmento AL, Sá BS, Vasconcelos AG, Arcanjo DD, Durazzo A, Lucarini M, et al. Perspectives on the therapeutic effects of pelvic floor electrical stimulation: A systematic review. Int J Environ Res Public Health. 2022;19:14035. doi: 10.3390/ijerph192114035. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 12.Wiegersma M, Panman CM, Berger MY, De Vet HC, Kollen BJ, Dekker JH. Minimal important change in the pelvic floor distress inventory-20 among women opting for conservative prolapse treatment. Am J Obstet Gynecol. 2017;216:397.e1–7. doi: 10.1016/j.ajog.2016.10.010. [DOI] [PubMed] [Google Scholar]
- 13.Utomo E, Blok BF, Steensma AB, Korfage IJ. Validation of the pelvic floor distress inventory (PFDI-20) and pelvic floor impact questionnaire (PFIQ-7) in a Dutch population. Int Urogynecol J. 2014;25:531–44. doi: 10.1007/s00192-013-2263-z. [DOI] [PubMed] [Google Scholar]
- 14.Burgio KL, Goode PS, Locher JL, Umlauf MG, Roth DL, Richter HE, et al. Behavioral training with and without biofeedback in the treatment of urge incontinence in older women: A randomized controlled trial. JAMA. 2002;288:2293–9. doi: 10.1001/jama.288.18.2293. [DOI] [PubMed] [Google Scholar]
- 15.Nygaard I, Barber MD, Burgio KL, Kenton K, Meikle S, Schaffer J, et al. Prevalence of symptomatic pelvic floor disorders in US women. JAMA. 2008;300:1311–6. doi: 10.1001/jama.300.11.1311. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16.Wu X, Zheng X, Yi X, Lai P, Lan Y. Electromyographic biofeedback for stress urinary incontinence or pelvic floor dysfunction in women: A systematic review and meta-analysis. Adv Ther. 2021;38:4163–77. doi: 10.1007/s12325-021-01831-6. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 17.Alperin M, Burnett L, Lukacz E, Brubaker L. The mysteries of menopause and urogynecologic health: Clinical and scientific gaps. Menopause. 2019;26:103–11. doi: 10.1097/GME.0000000000001209. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 18.Quiroz LH, White DE, Juarez D, Shobeiri SA. Age effects on pelvic floor symptoms in a cohort of nulliparous patients. Female Pelvic Med Reconstr Surg. 2012;18:325–8. doi: 10.1097/SPV.0b013e3182720255. [DOI] [PubMed] [Google Scholar]
- 19.Blakeman PJ, Hilton P, Bulmer JN. Oestrogen and progesterone receptor expression in the female lower urinary tract, with reference to oestrogen status. BJU Int. 2000;86:32–8. doi: 10.1046/j.1464-410x.2000.00724.x. [DOI] [PubMed] [Google Scholar]
- 20.Miyagawa S, Iguchi T. Epithelial estrogen receptor 1 intrinsically mediates squamous differentiation in the mouse vagina. Proc Natl Acad Sci U S A. 2015;112:12986–91. doi: 10.1073/pnas.1513550112. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 21.Bertotto A, Schvartzman R, Uchôa S, Wender MC. Effect of electromyographic biofeedback as an add-on to pelvic floor muscle exercises on neuromuscular outcomes and quality of life in postmenopausal women with stress urinary incontinence: A randomized controlled trial. Neurourol Urodyn. 2017;36:2142–7. doi: 10.1002/nau.23258. [DOI] [PubMed] [Google Scholar]
- 22.Jin J, Wang M. Effects of pelvic floor muscle training combined with estriol on pelvic floor dysfunction after total hysterectomy applied in perimenopause. Appl Bionics Biomech 2022. 2022 doi: 10.1155/2022/6962542. 6962542. [DOI] [PMC free article] [PubMed] [Google Scholar] [Retracted]
- 23.Sensoy N, Dogan N, Ozek B, Karaaslan L. Urinary incontinence in women: Prevalence rates, risk factors and impact on quality of life. Pak J Med Sci. 2013;29:818–22. doi: 10.12669/pjms.293.3404. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 24.Obsa MS, Worji TA, Kedir NA, Kute NG. Risk factors of pelvic organ prolapse at Asella teaching and referral hospital: Unmatched case control study. Front Glob Womens Health. 2022;3:833823. doi: 10.3389/fgwh.2022.833823. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 25.Fang J, Ye J, Huang Q, Lin Y, Weng Y, Wang M, et al. Risk factors of pelvic floor muscle strength in South Chinese women: A retrospective study. BMC Pregnancy Childbirth. 2022;22:624. doi: 10.1186/s12884-022-04952-0. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 26.Burgio KL, Richter HE, Clements RH, Redden DT, Goode PS. Changes in urinary and fecal incontinence symptoms with weight loss surgery in morbidly obese women. Obstet Gynecol. 2007;110:1034–40. doi: 10.1097/01.AOG.0000285483.22898.9c. [DOI] [PubMed] [Google Scholar]
- 27.Greer WJ, Richter HE, Bartolucci AA, Burgio KL. Obesity and pelvic floor disorders: A systematic review. Obstet Gynecol. 2008;112:341–9. doi: 10.1097/AOG.0b013e31817cfdde. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 28.van Veelen GA, Schweitzer KJ, van der Vaart CH. Ultrasound imaging of the pelvic floor: Changes in anatomy during and after first pregnancy. Ultrasound Obstet Gynecol. 2014;44:476–80. doi: 10.1002/uog.13301. [DOI] [PubMed] [Google Scholar]
- 29.Griffiths D, Clarkson B, Tadic SD, Resnick NM. Brain mechanisms underlying urge incontinence and its response to pelvic floor muscle training. J Urol. 2015;194:708–15. doi: 10.1016/j.juro.2015.03.102. [DOI] [PMC free article] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Data Availability Statement
The dataset is not available for public access but is available from the corresponding author upon reasonable request.