



Keywords: gut microbiome, insulin resistance, metabolic health, next-generation sequencing, spinal cord injury
Abstract
Accumulating evidence has revealed that alterations in the gut microbiome following spinal cord injury (SCI) exhibit similarities to those observed in metabolic syndrome. Considering the causal role of gut dysbiosis in metabolic syndrome development, SCI-induced gut dysbiosis may be a previously unidentified contributor to the increased risk of cardiometabolic diseases, which has garnered attention. With a cross-sectional design, we evaluated the correlation between gut microbiome composition and functional potential with indicators of metabolic health among 46 individuals with chronic SCI. Gut microbiome communities were profiled using next-generation sequencing techniques. Indices of metabolic health, including fasting lipid profile, glucose tolerance, insulin resistance, and inflammatory markers, were assessed through fasting blood tests and an oral glucose tolerance test. We used multivariate statistical techniques (i.e., regularized canonical correlation analysis) to identify correlations between gut bacterial communities, functional pathways, and metabolic health indicators. Our findings spotlight bacterial species and functional pathways associated with complex carbohydrate degradation and maintenance of gut barrier integrity as potential contributors to improved metabolic health. Conversely, those correlated with detrimental microbial metabolites and gut inflammatory pathways demonstrated associations with poorer metabolic health outcomes. This cross-sectional investigation represents a pivotal initial step toward comprehending the intricate interplay between the gut microbiome and metabolic health in SCI. Furthermore, our results identified potential targets for future research endeavors to elucidate the role of the gut microbiome in metabolic syndrome in this population.
NEW & NOTEWORTHY Spinal cord injury (SCI) is accompanied by gut dysbiosis and the impact of this on the development of metabolic syndrome in this population remains to be investigated. Our study used next-generation sequencing and multivariate statistical analyses to explore the correlations between gut microbiome composition, function, and metabolic health indices in individuals with chronic SCI. Our results point to potential gut microbial species and functional pathways that may be implicated in the development of metabolic syndrome.
INTRODUCTION
As a result of the physiological and lifestyle changes following spinal cord injury (SCI), individuals with SCI are at increased risk of cardiovascular diseases, which is the most common cause of mortality in SCI (1). Metabolic syndrome, a constellation of risk factors for cardiovascular diseases, such as obesity, glucose intolerance, dyslipidemia, and a proinflammatory state, develops at an earlier age in individuals with SCI compared with their nondisabled counterparts (2–7). It is estimated that up to 50% of individuals with SCI have metabolic syndrome (8). As a result, these SCI-related health complications and adverse economic impacts could further lead to progressive decreases in their quality of life.
Previous research suggests that muscle atrophy, adiposity, and neurological and hormonal changes contribute to the development of metabolic syndrome in SCI (9). Emerging evidence in non-SCI literature, based on research using animal or human models, revealed that a balanced gut microbiome has significant impacts on maintaining the host’s metabolic health (10, 11). Specifically, observational studies repeatedly and reproducibly showed that gut dysbiosis, a disruption of the normal microbial communities and their functions in the gastrointestinal tract, occurs in individuals with obesity, diabetes, and gut inflammation (12–14). Importantly, interventional studies using fecal matter transplant or gnotobiotic animal models, as well as those using the Mendelian randomization approach (15–17), further support a causal relationship between gut dysbiosis and the development of metabolic syndrome. Although the exact mechanisms remain to be elucidated, gut dysbiosis could exert a negative impact 1) locally in the gastrointestinal tract via direct interaction with host cells, impairing gut epithelial layer integrity and causing local inflammatory responses (18), and 2) through the release of bacteria or harmful microbial-derived metabolites into the circulation or distant organs, which could induce systemic inflammation and impair signaling pathways involved in maintaining metabolic health (19–21).
In SCI, not only does the neurological impairment in the gastrointestinal system result in bowel dysfunction but also in gut dysbiosis, increased gut permeability, and local and systemic inflammation (22). A closer examination of the bacterial taxa changes following SCI suggests a potential link between gut dysbiosis and metabolic impairment. For example, both animal (22) and human (23) studies showed that SCI-related gut microbiome changes resemble those observed in metabolic syndrome or cardiovascular diseases, such as increased Firmicutes (24, 25) and decreased butyrate-producing bacteria (26). These pioneering studies suggest that gut dysbiosis may be involved in the accelerated development of metabolic syndrome among individuals with SCI. However, there is a paucity of studies that evaluate the relationship between gut microbiome composition and function and indices of metabolic health in SCI. Furthermore, existing studies mostly used the 16-s rRNA sequencing technique, the results of which may be limited due to its low taxonomical resolution (i.e., identifying bacteria at the genus level) (27). To address these gaps in knowledge, we utilized the shotgun metagenomics sequencing technique, which sequences the whole genome and can identify bacteria at the species level and provide insight on the functional potential of the gut microbial communities (27). We further assessed important metabolic health indices, such as glucose metabolism (e.g., insulin resistance, glucose tolerance), lipid profile, and systemic inflammation, which allowed us to explore the connection between the gut microbiome and metabolic health.
METHODS
We analyzed samples collected from 46 participants who were screened and recruited for two separate studies. Participants were considered eligible for this analysis if they 1) were between 18 and 65 yr old; 2) had a traumatic SCI at the cervical, thoracic, or lumbar level (C4–L2) classified by the American Spinal Injury Association impairment (AIS) scale as A, B, C, or D; 3) were at least 3-yr postinjury; 4) did not have active pressure ulcers; 5) did not have type 2 diabetes; 6) had not participated in a weight loss program for the last 6 mo; and 7) had not been on antibiotics for at least 4 wk prior to the study. The 4-wk period was selected because gut microbiome composition closely resembles baseline composition 4 wk after antibiotic treatment cessation (28). Therefore, the acute impact of antibiotics on gut microbiome composition among our participants should be limited. A medical history questionnaire was used to inquire about each participant’s current medical conditions, and none of them reported gastrointestinal issues or were taking medications for the management of blood markers assessed in the current study. The studies were approved by the University of Alabama at Birmingham (UAB) Institutional Review Board. Each participant provided informed consent and was provided monetary compensation. Participants were recruited from August 2017 through August 2022.
Participants underwent an oral glucose tolerance test (OGTT) at the UAB clinical research unit after a 10- to 12-h fast. For the OGTT, each participant consumed a 75-g oral glucose load within 5 min. Blood samples were collected immediately before and at 10, 30, 60, 90, and 120 min after glucose ingestion to measure serum glucose, insulin, and C-peptide concentrations. Glucose assays were performed using an automated Sirrus Stanbio colorimetric chemical analyzer. Serum insulin concentration was measured using an immunofluorescence method with an AIA-600 II analyzer. Each participant’s type 2 diabetes status was determined using their blood glucose concentration at minute 120 during the OGTT, according to the American Diabetes Association guidelines (i.e., >200 mg/dL) (29).
Glucose and Lipid Metabolism Indicators
Various indicators of glucose metabolism were calculated using the OGTT data. Whole-body insulin sensitivity was estimated using the Matsuda index (a formula based on insulin and glucose values measured during the OGTT) (30). Individuals with type 2 diabetes were excluded as the Matsuda index does not have a robust correlation with insulin sensitivity in individuals with type 2 diabetes assessed using the euglycemic insulin clamp (30). Homeostatic model assessment-insulin resistance (HOMA-IR) was calculated using the equation: (31). Glucose-stimulated insulin secretion (GSIS) was calculated by dividing the insulin increment by the glucose increment within 30 min of the OGTT (ΔInsulin30/ΔGlucose30) (32). The disposition index, a pancreatic β-cell function index adjusted for insulin sensitivity, was calculated as GSIS * 1/fasting insulin. The incremental area under the curve (AUC) was calculated using the trapezoid rule for various indices. Hepatic insulin extraction (HIE) was calculated using the equation [1 − (incremental AUCinsulin/incremental AUCC-peptide)]×100% (33). Previous studies showed that the HIE is highly correlated with insulin sensitivity (i.e., the higher the HIE, the more insulin sensitive) (34).
The fasting blood sample obtained from the OGTT was used for lipid analysis [i.e., total cholesterol, triglyceride, high-density lipoprotein cholesterol (HDL-c), and low-density lipoprotein cholesterol (LDL-c). Total cholesterol, HDL-c, and TG are measured with the Sirrus analyzer. LDL-c levels are estimated using the formula LDL-c = total cholesterol − HDL-c − triglyceride/5] (35).
Inflammation Panel
Serum cytokines, including interferon (IFN)-γ, interleukins (ILs; IL-6, IL-8, and IL-10), and tumor necrosis factor (TNF)-α, were analyzed in duplicate using the MesoScale Discovery Pro-inflammatory kit. C-reactive protein was analyzed on a Sirrua Stanbio analyzer.
Stool Sample Collection and Processing
Stool sample collection and DNA extraction were performed using established protocols (36). Briefly, participants or their caregivers were provided with a Para-Pak vial for sample preservation and a stool collection container. A stool sample was collected at the participant’s home during their regular bowel program. The Para-Pak vials were picked up by FedEx on the day of collection and returned to our laboratory by 3:00 PM the next day. The Para-Pak vials contain a non-nutritive solution that preserves the bacteria at ambient temperature. Stool bacterial DNA was extracted using the Zymo Quick-DNA Fecal/Soil Microbe Kit.
DNA Sequencing
The Metagenomics library was prepared using the Qiagen FX kit following the manufacturer’s instructions. The libraries were assessed for quality using the Agilent BioAnalyzer 2100 and quantitated by quantitative PCR (qPCR) following standard protocols using Kapa Biosystems. The libraries were then sequenced on the Illumina NovaSeq 6000 system with paired-end 250 bp sequencing following the manufacturer’s standard protocols.
Bioinformatics Analysis
Upon completion of sequencing, quality control and preprocessing were performed on the raw FASTQ data to remove low-quality reads, short reads, Illumia adapters, and human DNA contaminants (Bowtie 2) using the KneadData tool (37). The sequences that passed quality control were then analyzed using the bioBakery environment for taxonomic profiling (MetaPhlAn 4.0) (38) and functional analysis (HUMAnN 3.0) (39) with default parameters using the MetaCyc pathway databases (40). MetaPhlAn 4 leverages ∼5.1M unique clade-specific marker genes identified from ∼1M microbial genomes spanning 26,970 species-level genome bins (38). HUMAnN 3.0 can efficiently and accurately profile the abundance of microbial metabolic pathways and other molecular functions from metagenomic sequencing data (39). During functional profiling, unmapped reads were aligned against the Uniref90 database using the DIAMOND function (41).
Statistical Analysis
Correlations between the indices of metabolic health and alpha diversity were assessed using the Spearman’s correlation analysis. The relationship between the main component of variation in the gut microbiome composition (e.g., Bray–Curtis dissimilarity metric) and the indices of metabolic health was assessed using the envfit function in the R vegan package (42). Alpha diversity reflects the richness and evenness within a single sample and beta diversity illuminates differences in microbial composition between samples, offering insights into the uniqueness or similarity of microbial communities across individuals, groups, or conditions.
Correlations between the indices of metabolic health and gut microbial abundance at the species level or functional pathway abundance were explored using regularized canonical correlation analysis (rCCA) in the mixOmics library within the R statistical package (43, 44). Abundance data underwent preprocessing steps, which included the application of an offset, filtering low abundance data (at 0.01%), and centered log ratio transformation prior to subsequent statistical analysis (45). The regularization parameters were determined using the shrinkage method. The rCCA correlation scores between a given pair of variables (one from the metabolic health data set, one from the microbiome data set) were plotted as heatmaps using the clustered image maps (cim) function (46). A cut-off value of |r| = 0.2 was arbitrarily chosen to reveal only those with at least a small-medium correlation effect size. This allows us to 1) limit potentially negotiable relationships and 2) reduce the size of the cluster image map to make the figures more legible and interpretable. Hierarchical clustering (complete linkage, Euclidean distance) was used to obtain the order of the variables. The rCCA method was used as it is appropriate to perform on datasets of high dimensions and with high collinearities, such as the microbiome composition data set used in this study. The rCCA does not provide traditional P values due to the multivariate nature of the analysis, where traditional statistical assumptions do not hold. Instead, the primary goal of the rCCA method is to capture the overall relationships between sets of high-dimension data, rather than conducting hypothesis tests on individual variables (47, 48).
RESULTS
Participants’ Characteristics
Participants’ basic demographic information is shown in Table 1. The average fasting glucose concentration and glucose concentration at 2 h during an oral glucose tolerance test are within the normal range. The average values of the Matsuda index and HOMA-IR, indicators of insulin resistance, are in the insulin-resistant range. The average lipid profile parameters are within the normal or optimal range.
Table 1.
Characteristics of study participants with chronic spinal cord injury (sample size: n = 46)
| Variables | Reference Range | |
|---|---|---|
| Age, yr | 45 ± 11 | NAa |
| Sex | 13 F/33 M | NA |
| Race | Non-Hispanic Black: 28 Non-Hispanic White: 17 Asian: 1 |
NA |
| Level of injury | Cervical: 15 Thoracic: 31 |
NA |
| Completeness of injuryb | Complete: 34 Incomplete: 12 |
NA |
| Duration of injury, yr | 20.60 ± 12.55 | NA |
| Fasting glucose, mg/dL | 93.70 ± 9.79 | ≤99 |
| GlucoseOGTT120min, mg/dL | 120.53 ± 28.37 | <140 |
| Matsuda index, au | 3.69 ± 2.37 | >4.3 |
| HOMA-IR, au | 2.86 ± 2.21 | <2 |
| Cholesterol, mg/dL | 190.74 ± 41.35 | <200 |
| Triglyceride, mg/dL | 111.98 ± 69.76 | <150 |
| High-density lipoprotein cholesterol, mg/dL | 50.48 ± 10.69 | ≥50 for females ≥40 for males |
| Low-density lipoprotein cholesterol, mg/dL | 117.87 ± 36.61 | <100 |
| Interferon-γ, pg/dL | 5.54 ± 7.41 | NA |
| Tumor necrosis factor-α, pg/dL | 2.28 ± 1.02 | NA |
| Interleukin-6, pg/dL | 1.65 ± 1.06 | NA |
| Interleukin-8, pg/dL | 12.25 ± 4.32 | NA |
| Interleukin-10, pg/dL | 0.56 ± 1.67 | NA |
Data are means ± SD. HOMA-IR, Homeostatic Model Assessment for Insulin Resistance; NA, not applicable; OGTT, oral glucose tolerance test.
aReference not applicable or not available.
bMotor complete: American Spinal Injury Association Impairment scale: A and B.
Gut Microbiome Composition and Function Correlate With Metabolic Health
Alpha diversity.
Microbiome alpha diversity indices calculated from MetaPhlAn taxonomy output are summarized in Table 2. Spearman’s correlation analyses (Fig. 1) showed that the alpha diversity indices (i.e., Shannon, Gini Simpson, and Observed) were positively correlated with HIE, and Dominance Gini was negatively correlated with HIE. Shannon and Gini Simpson were correlated with lower fasting insulin/insulin concentrations at OGTT 2 h (P < 0.05). In addition, a trend was observed for 1) positive correlations between alpha diversity and Matsuda index, IL-10, and glucose AUC, and 2) negative correlation between alpha diversity and insulin AUC during the OGTT and HOMA-IR (0.05 < P < 0.1).
Table 2.
Gut microbiome alpha diversity indices estimated from next-generation sequencing among participants with chronic spinal cord injury
| Shannon, au | 3.23 ± 0.54 |
| Gini Simpson, au | 0.91 ± 0.07 |
| Observed, au | 97.76 ± 37.08 |
| Dominance Gini, au | 0.97 ± 0.01 |
Data are means ± SD derived from n = 46 participants with chronic spinal cord injury. Biobakery MetaPhlAn 4 package was used to estimate various alpha diversity indices. Shannon index captures both the richness and evenness of the microbial species within each sample. Gini Simpson is similar to Shannon index, but more sensitive to the abundance of dominant species. The observed index reflects the richness (number of unique species) in a sample. The dominance Gini index reflects the evenness of the microbial community in a sample, with higher the value indicating less even distribution of the microbial species in a given sample.
Figure 1.

Spearman’s correlations between indices of gut microbiome alpha diversity and metabolic health in individuals with chronic spinal cord injury. CAUC, c-peptide area under the curve during an OGTT; Cpep0, fasting c-peptide; Cpep120, c-peptide at 2 h during an OGTT; CRP, C-reactive proteins; DI, disposition index; GAUC, OGTT glucose area under the curve; Glu0, fasting glucose; Glu120, glucose concentration at 2 h during an oral glucose tolerance test (OGTT); GSIS, glucose-stimulated insulin secretion; HDL, high-density lipoprotein cholesterol; HIE, hepatic insulin extraction; HOMA, Homeostatic Model Assessment for Insulin Resistance; iCAUC, incremental area under the curve during an OGTT; IFN-g, interferon-γ; iGAUC, OGTT incremental area under the curve; IL, interleukin; Ins0, fasting insulin; Ins120, insulin concentration at 2 h during an OGTT; LDL, low-density lipoprotein cholesterol, MI, Matsuda Index; TNF-a, tumor necrosis factor-α. *P < 0.05, #P < 0.1.
Metabolic indices and community structure.
Insulin AUCs (total and incremental) demonstrated statistically significant associations with the two-dimensional NMDS ordination (based on Bray–Curtis dissimilarity, R2 = 0.13 for both, P = 0.05 for total AUC, P = 0.04 for incremental AUC, respectively). None of the other indices of metabolic health showed a significant association with the NMDS ordination (Fig. 2).
Figure 2.

Nonmetric multidimensional scaling (NMDS) plot of the Bray–Curtis dissimilarities with metabolic health variables in individuals with chronic spinal cord injury. Each black dot represents each participant. The blue arrow shows the direction of the (increasing) value of each of metabolic health indicators, and the length of the line is proportional to the correlation between the variable and the NMDS score. A longer arrow indicates a stronger association. Only the insulin areas under the curve (AUC, total and incremental) are significantly correlated with the NMDS score (P < 0.05). CAUC, c-peptide area under the curve during an OGTT; Cpep0, fasting c-peptide; Cpep120, c-peptide at 2 hour during an OGTT; CRP, C-reactive proteins; DI, disposition index; GAUC, OGTT glucose area under the curve; Glu0, fasting glucose; Glu120, glucose concentration at 2 h during an oral glucose tolerance test (OGTT); GSIS, glucose-stimulated insulin secretion; HDL, high-density lipoprotein cholesterol; HIE, hepatic insulin extraction; HOMA, Homeostatic Model Assessment for Insulin Resistance; iCAUC, incremental area under the curve during an OGTT; IFN-g, interferon-γ; iGAUC, OGTT incremental area under the curve; IL, interleukin; Ins0, fasting insulin; Ins120, insulin concentration at 2 h during an OGTT; LDL, low-density lipoprotein cholesterol; MI, Matsuda Index; TNF-a, tumor necrosis factor-α.
Gut microbiome function potential.
We used regularized canonical correlation analyses and clustered image maps (Fig. 3) to show how metabolic indices and gut microbiome functional pathways abundances are connected. The heatmap is generated to visualize the clustering of features (both metabolic indices and functional pathways) and their correlation patterns, which is particularly helpful, and allows us to evaluate the overall patterns and trends of correlations, rather than each individual parameter. Specifically, several microbial functional pathways related to complex carbohydrate metabolism have favorable correlations with glucose metabolism (e.g., the higher the abundance, the lower insulin resistance), including the β-(1,4)-mannan degradation pathway (positively correlated with HIE; negatively correlated with insulin AUC, 0.20 < |r| < 0.30), GALACT-GLUCUROCAT-PWY: superpathway of hexuronide and hexuronate degradation (i.e., superpathway of galacturonate and glucuronate degradation; positively correlated with HIE and MI; negatively correlated with HOMA-IR, fasting C-peptide/insulin, and their AUCs, 0.20 < |r| < 0.30). In addition, a cluster of several other lesser-known pathways showed favorable correlations with indices of metabolic health, including PENTOSE-P-PWY: pentose phosphate pathway (negatively correlated with fasting triglyceride and glucose AUC, 0.20 < |r| < 0.30), PWY-6703: preQ0 biosynthesis (positively correlated with MI, negatively correlated with fasting triglyceride, fasting C-peptide, C-peptide/glucose/insulin AUCs, 0.20 < |r| < 0.30), FUCCAT-PWY: fucose degradation pathway (positively correlated with MI; negatively correlated with fasting triglyceride, fasting C-peptide, C-peptide/glucose/insulin AUCs, 0.20 < |r| < 0.30), FUC-RHAMCAT-PWY: super pathway of fucose and rhamnose degradation (positively correlated with MI and HDL; negatively correlated with HOMA-IR, triglyceride, fasting glucose/C-peptide, C-peptide/glucose/insulin AUCs, 0.25 < |r| < 0.35), POLYISOPRENSYN-PWY: polyisoprenoid biosynthesis (positively correlated with MI and HDL; negatively correlated with HOMA-IR, triglyceride, fasting glucose/C-peptide, C-peptide/glucose/insulin AUCs, 0.25 < |r| < 0.35), GLYCOCAT-PWY: glycogen degradation I (positively correlated with HIE, r = 0.25), and PWY-5845: superpathway of menaquinol-9 biosynthesis/PWY-5862: superpathway of demethylmenaquinol-9 biosynthesis (positively correlated with HIE and MI; negatively correlated with HOMA-IR, triglyceride, fasting C-peptide/insulin, C-peptide/insulin AUCs, 0.25 < |r| < 0.35).
Figure 3.
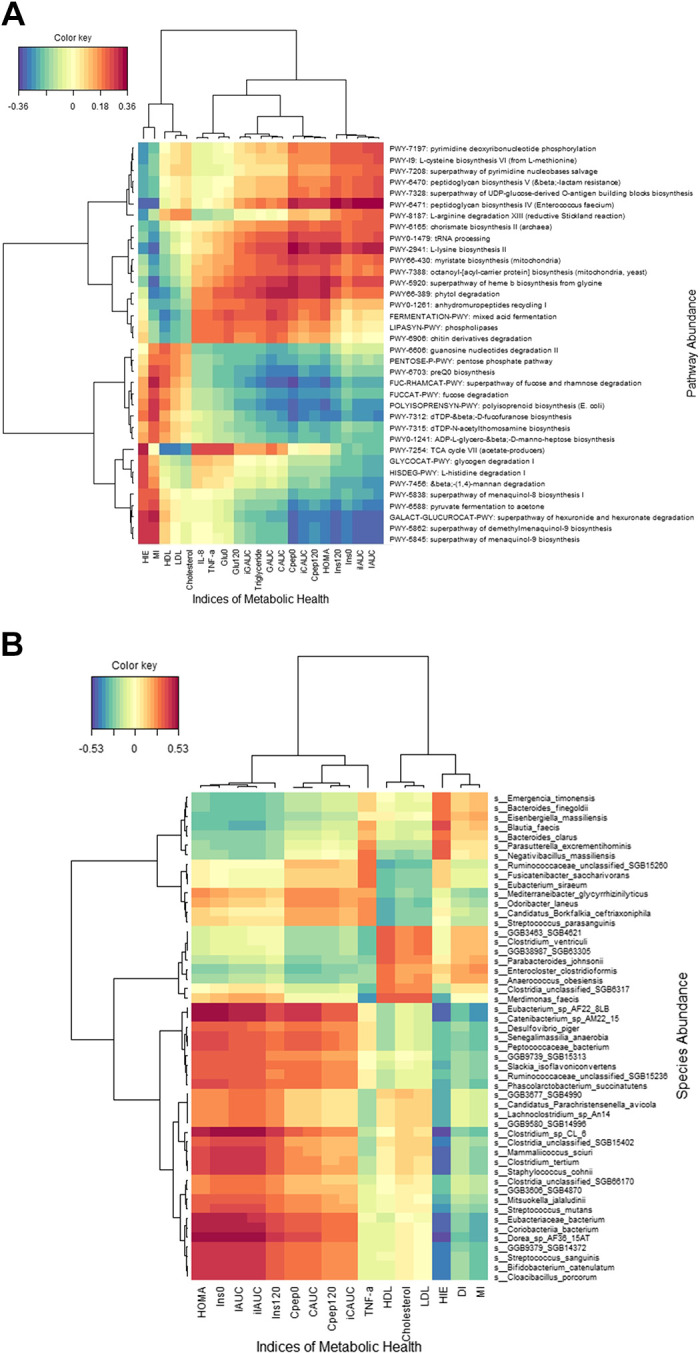
Heatmap showing correlations between gut microbiome function (A) or composition (B) and metabolic health using the regularized canonical correlation analysis method. An arbitrary cut-off of |r| = 0.2 was applied to limit potentially negligible correlations and make the figures more legible and interpretable. CAUC, c-peptide area under the curve during an OGTT; Cpep0, fasting c-peptide; Cpep120, c-peptide at 2 h during an OGTT; CRP, C-reactive proteins; DI, disposition index; Glu0, fasting glucose; Glu120, glucose concentration at 2 h during an oral glucose tolerance test (OGTT); GSIS, glucose-stimulated insulin secretion; HDL, high-density lipoprotein cholesterol; HIE, hepatic insulin extraction; HOMA, Homeostatic Model Assessment for Insulin Resistance; LDL, low-density lipoprotein cholesterol; iCAUC, incremental area under the curve during an OGTT; IFN-g, interferon-γ; iGAUC, incremental area under the curve during an OGTT; IL, interleukin; Ins0, fasting insulin; Ins120, insulin concentration at 2 h during an OGTT; MI, Matsuda Index.
Several functional pathways had unfavorable correlations with metabolic health (i.e., the higher the abundance, the poorer metabolic health reflected by measured indicators), including PWY-6471: peptidoglycan biosynthesis IV (negatively correlated with MI/HIE; positively correlated with HOMA-IR, fasting insulin/C-peptide and their AUCs, 0.25 < |r| < 0.40), PWY0-1261: anhydromuropeptides recycling I (positively correlated with triglycerides, glucose/C-peptide AUCs, 0.2 < |r| < 0.3), PWY-I9: l-cysteine biosynthesis VI (from l-methionine; negatively correlated with HIE; positively correlated with insulin AUCs, 0.2 < |r| < 0.3), PWY-8187: l-arginine degradation XIII pathway (negatively correlated with HIE, r = −0.25), PWY66-389: phytol degradation (negatively correlated with HDL and MI; positively correlated with triglyceride, HOMA-IR, fasting glucose/C-peptide and their AUCs, 0.2 < |r| < 0.35), pyrimidine deoxyribonucleotide phosphorylation (negatively correlated with HIE; positively correlated with insulin AUCs, 0.2 < |r| < 0.3), PWY-2941: l-lysine biosynthesis II (negatively correlated with HIE and MI; positively correlated with triglyceride, HOMA-IR, fasting glucose/insulin/C-peptide and their AUCs, 0.25 < |r| < 0.35), PWY0-1479: tRNA processing (negatively correlated with MI; positively correlated with fasting C-peptide, C-peptide/insulin AUCs, 0.2 < |r| < 0.3), PWY-7388: octanoyl-[acyl-carrier protein] biosynthesis (mitochondria, yeast; negatively correlated with MI; positively correlated with triglyceride, C-peptide/glucose AUCs, 0.2 < |r| < 0.3), PWY66-430: myristate biosynthesis (mitochondria) (negatively correlated with MI; positively correlated with triglyceride, fasting C-peptide, C-peptide/glucose AUCs, 0.2 < |r| < 0.3), PWY-5920: superpathway of heme b biosynthesis from glycine (negatively correlated with MI; positively correlated with triglyceride, HOMA-IR, fasting C-peptide/insulin, C-peptide/glucose/insulin AUCs, 0.2 < |r| < 0.35), FERMENTATION-PWY: mixed acid fermentation (negatively correlated with HDL; positively correlated with triglyceride, glucose AUC, 0.2 < |r| < 0.3), and LIPASYN-PWY: phospholipases (negatively correlated with HDL; positively correlated with triglyceride, 0.2 < |r| < 0.3).
At the species level, we observed favorable correlations between clusters of indices of glucose metabolism (e.g., positive correlation with HIE; negative correlation with HOMA-IR, fasting insulin, and insulin AUCs, shown in Fig. 3B) and microbes (0.25 < |r| < 0.4), including Emergencia timonensis, Bacteroides finegoldii, Eisenbergiella massiliensis, Blautia faecis, Bacteroides clarus, Parasutterella excrementihominis, and Negativibacillus massiliensis.
In addition, we identified clusters of microbes with unfavorable correlation with metabolic health (e.g., the higher the abundance, the more insulin resistant and the higher cholesterol concentrations). These microbes include Eubacterium sp. AF22, Catenibacterium sp. AM22 15, Desulfovibrio piger, Senegalimassilia anaerobia, Peptococcaceae bacterium, GGB9739 SGB15313, Slackia isoflavoniconvertens, Phascolarctobacterium succinatutens, GGB3677 SGB4990, Candidatus Parachristensenella avicola, Lachnoclostridium sp. An14, GGB9580 SGB14996, Clostridia unclassified SGB15402, Mammaliicoccus sciuri, Clostridium tertium, Staphylococcus cohnii, Clostridia unclassified SGB66170, GGB3606 SGB4870, Mitsuokella jalaludinii, Streptococcus mutans, Eubacteriaceae bacterium, Coriobacteriia bacterium, Dorea sp. AF36 15AT, GGB9379 SGB14372, Streptococcus sanguinis, Bifidobacterium catenulatum, Cloacibacillus porcorum, Enterocloster clostridioformis, Anaerococcus obesiensis (0.25 < |r| < 0.4).
In contrast, we observed a cluster of microbes that have opposite correlations with indices of lipid metabolism and inflammation, where they are negatively correlated with several indices of lipid metabolism (e.g., cholesterol, triglyceride, LDL) and positively correlated with indices of inflammation (e.g., TNF-α, IL-8, IFN-γ). These species include Eubacterium siraeum, Odoribacter laneus, Candidatus Borkfalkia ceftriaxoniphila, Streptococcus parasanguinis, GGB3463 SGB4621, Clostridium ventriculi, GGB38987 SGB63305, Parabacteroides johnsonii, Clostridia unclassified SGB6317, Merdimonas faecis, and Ruminococcaceae unclassified SGB15236 (0.25 < |r| < 0.4).
DISCUSSIONS
Using metagenomic sequencing techniques, not only are we able to capture the global microbiome composition, but we also gained first insights into the functional and compositional structure of the gut microbiome in individuals with SCI. Our study used multivariate analysis methods well suited to the Omics data set, where the number of variables is much higher than the number of samples, to explore the relationship between the gut microbiome composition (taxonomy and functional potential) and metabolic health. Our cross-sectional study identified functional pathways and microbial species correlated with indices of metabolic health and serves as the first evidence and scientific foundation for investigating how gut dysbiosis contributes to metabolic syndrome in individuals with SCI.
We first characterized the microbial communities using two of the fundamental indices, alpha and beta diversity. Shifts in these microbiome diversity indices are often observed between health and disease conditions, such as obesity and diabetes (49–51). However, the absence of which, such as the limited association between these indices and metabolic health outcomes observed in the current study, is not uncommon (51, 52). Regardless, these indices are commonly reported to provide an overview of the global changes in gut microbiome composition, followed by analyses of the microbial community composition data, which offer insights on the detailed changes in a disease condition.
A healthy and balanced gut microbiome is pivotal for maintaining gut integrity, immune modulation, and providing helpful metabolites for maintaining host health (53). Disruption of these critical functions is implicated in the development of many chronic diseases, that is, obesity, diabetes, and cardiovascular diseases (12). Dietary fibers serve as an important energy source for the gut microbial community, which digest complex carbohydrates (e.g., dietary fibers) to produce short-chain fatty acids essential for gut health, intestinal integrity, and cardiometabolic health (54). In our study, several functional pathways related to plant/fiber metabolism positively correlate with insulin sensitivity. β-(1,4)-d-Mannans are one of the major constituents of the hemicellulose present in the cell walls and tissues of higher plants. Previous research showed that a higher dietary fiber intake was associated with the enrichment of the β-(1,4)-mannan degradation pathway (55), and transitioning to western diets from non-western nations led to the loss of the β-(1,4)-mannan degradation pathway (56). These lines of research support the positive correlation between the β-(1,4)-mannan pathway and insulin sensitivity, as a higher abundance of the β-(1,4)-mannan degradation pathway may indicate a higher dietary fiber intake. Another complex carbohydrate, d-galacturonate, is the main monomeric constituent of pectin and a heteropolymer very common in plant tissue. The GALACT-GLUCUROCAT-PWY: superpathway of hexuronide and hexuronate degradation pathways are depleted in type 1 (57) and type 2 diabetes (58). Although the mechanism has not been studied, our finding on the positive correlation between the GALACT-GLUCUROCAT-PWY and insulin sensitivity is consistent with these studies. Furthermore, we observed that a higher abundance of the pathway PWY-6588: pyruvate fermentation to acetone is associated with insulin sensitivity. A recent research study showed that refined grain consumption led to a decrease in this pathway, compared with whole grain wheat consumption (59). Collectively, these existing pieces of evidence suggest a positive involvement of gut microbial complex carbohydrate metabolism in glucose homeostasis and support the observed correlations between these pathways and insulin sensitivity.
We identified several functional pathways negatively correlated with insulin sensitivity, and existing literature suggests that these pathways may contribute to impaired insulin sensitivity due to their negative impact on intestinal inflammation and intestinal permeability. Specifically, these pathways are 1) pathways related to the biosynthesis of peptidoglycans and their recycling (PWY-6471: peptidoglycan biosynthesis IV, PWY0-1261: anhydromuropeptides recycling I): peptidoglycans are bacteria cell wall components that are sensed by the host’s multiple pattern-recognition receptors. A series of downstream signaling pathways could induce inflammatory responses, which are implicated in the development of insulin resistance, translocation of bacterial components, and vascular and adipose tissue inflammation (60). In support of our results, peptidoglycan biosynthesis was elevated in youth with nonalcoholic fatty liver disease (NAFLD) compared with those without NAFLD (61), and positively correlated with HOMA-IR in children (62). 2) PWY-I9: l-cysteine biosynthesis VI (from l-methionine): methionine and cysteine are sulfur-containing amino acids, and the process of cysteine synthesis from methionine is called transsulfuration. Cysteine is one of the preferred sulfur sources for the gut microbiota, and cysteine metabolism by the gut microbiota produces H2S in the gut. A higher intestinal luminal H2S concentration negatively affects mucosal integrity, promotes proinflammatory responses, and inhibits colonocyte butyrate oxidation (63, 64). 3) l-Arginine degradation XIII pathway: although the exact mechanism is unknown, l-arginine exerts protective effects on gut integrity and inflammation. An increased arginine degradation was documented in colitis and inflammatory bowel disease (IBD) (65), and reduced arginine availability slowed down colitis resolution in an animal model (66). Given that compromised gut barrier integrity could lead to metabolic endotoxemia, where gut microbiome-derived toxins enter the blood stream and induce low-grade systemic inflammation central to metabolic diseases (67), these pieces of evidence support our observations that these pathways correlate with poorer metabolic health.
When examining specific gut microbes and their relationship with indices of metabolic health, we identified species related to short-chain fatty acid production, production of harmful microbial metabolites, immune modulation, and, surprisingly, dental problems. We found favorable correlations between metabolic health and bacterial species, including 1) Fusicatenibacter saccharivorans (68) and Blautia faecis (69), which are butyrate producers, and their abundances are reduced in patients with IBD with impaired gut integrity and intestinal inflammation compared with healthy controls (13, 69). Butyrate is the product of microbial fermentation of nondigestible fiber. It promotes gut health via several mechanisms, such as being an energy source for colonocytes, modulating inflammatory responses, maintaining the intestinal epithelial barrier, etc. (70). In addition, butyrate may benefit glucose and lipid metabolism by regulating gene expression and intracellular signaling pathways in extraintestinal tissues. 2) Parasutterella excrementihominis: it presents the majority of the Parasutterella genus, whose abundance was significantly reduced in response to a high-fat diet in both animals and humans, accompanied by worsened metabolic health (71). Increases in Parasutterella are correlated with improved LDL-cholesterol among adults consuming resistant starch (72). It is also proposed that Parasutterella confers its benefits via modulation of bile acid metabolism and reducing harmful microbial metabolites (e.g., p-Cresol and p-Cresol sulfate) (71). These studies support the positive role of Parasutterella in metabolic health and our observations.
We identified several bacteria species with unfavorable correlations with metabolic health (e.g., Cloacibacillus porcorum, Clostridium tertium, Desulfovibrio piger, and Streptococcus mutans), and existing literature revealed that they may elicit negative impacts on host health by reducing gut integrity, generating harmful metabolites (i.e., hydrogen sulfide), and causing systematic inflammation. Gut integrity is critical for maintaining the gut microbiome-host homeostasis, and the mucus layer contributes to this homeostasis by protecting against mechanical, chemical, and biological attacks on the epithelial surface (73, 74). Mucins are the critical structure and functional protein components of mucus. Some gut bacteria contain enzymes that cleave glycan linkages in mucin proteins and utilize mucins as energy source. Cloacibacillus porcorum (75) and Clostridium tertium (76) are mucin-degrading bacteria that could impair the mucus layer and increase host susceptibility to intestinal inflammation and infection (74). In addition to such direct microbial attack on mucus, microbial metabolites, such as H2S produced by D. piger (77), could also induce gut permeability by chemically breaking the disulfide bonds connecting mucins (78). The negative impact of D. piger on gut integrity can be further supported by the fact that increased D. piger abundance has been documented in IBD (79). In addition to microbes commonly found in the lower intestinal tract, we identified oral bacteria pathogens correlated with insulin resistance (e.g., higher HOMA-IR), S. mutans. S. mutans can translocate to extraoral tissues and is implicated in cardiovascular diseases, IBD, and colorectal cancer (80). Although the exact mechanism for these bacteria is not known, oral pathogenic bacteria in the GI tract may induce intestinal inflammation and consequently impair gut integrity (81).
The study has several limitations. First, the interpretation of the results is limited by the cross-sectional nature of the study design. No causal effects can be concluded for the identified functional pathways and microbes, and we can only rely on existing literature to speculate on their potential involvements in metabolic health among our participants. Second, due to the limited sample size, we could not further delineate how other potential confounders, such as the level/severity of the injury, age, race, gender, diet, etc., may individually or collectively mediate the relationship between the gut microbiome and metabolic health. For example, racial differences in diet quality are well documented (82), which may collectively or individually affect the gut microbiome composition and metabolic health. To what degree the relationship between gut microbiome and metabolic health is mediated by diet remains largely an ongoing investigation (83). Emerging studies evaluating personalized health showed that habitual diet explained a smaller proportion of variations in postprandial glucose and insulin responses than the gut microbiome composition (84). Similarly, in SCI, accumulating evidence showed that glucose metabolism and gut microbiome differ with different levels of injury, and gut microbiome may mediate the relationship between level of injury and metabolic health. However, the evaluation of such effects warrants future investigations, as it is beyond the scope of this project and requires significantly larger sample sizes (85, 86). Third, the paucity of studies using metagenomic sequencing techniques limits our interpretation of the results. Despite its advantages and continued falling cost, metagenomic sequencing remains prohibitively pricy and requires more extensive computing/analytical resources. As such, limited to no existing literature examined the impacts of several microbial pathways and species identified in our study.
Conclusions
Our cross-sectional analysis is a crucial first step in understanding the relationship between the gut microbiome and metabolic health in individuals with SCI. We identified functional pathways and microbes correlated with metabolic health, and the directions of the correlations are thematically consistent with evidence from existing literature. Specifically, microbes/functions related to complex carbohydrate degradation and maintenance of gut integrity are implicated in better metabolic health, whereas harmful microbial metabolites and gut inflammation are linked with worse metabolic health. Future studies utilizing larger sample sizes, interventional trial, or longitudinal designs are warranted to establish the relationship between gut microbiome changes and metabolic health in SCI.
DATA AVAILABILITY
The microbiome sequence data and metadata are available upon reasonable request.
GRANTS
The study was supported by Craig H. Neilsen Foundation Postdoctoral Fellowship Research Grant 19 (Grant 599449, to J.L.), the National Institute on Disability, Independent Living, and Rehabilitation Research (Grant NIDILRR-90SI5019), the National Center for Advancing Translational Sciences of the National Institutes of Health (Grant UL1TR003096), and the National Institute of Health S10 Instrumentation program (Grants 1S10OD032422-01 and S10RR027822).
DISCLOSURES
No conflicts of interest, financial or otherwise, are declared by the authors.
AUTHOR CONTRIBUTIONS
J.L., S.B., E.L., and C.Y.-F. conceived and designed research; J.L. performed experiments; J.L. analyzed data; J.L. interpreted results of experiments; J.L. prepared figures; J.L. drafted manuscript; J.L. and C.Y.-F. edited and revised manuscript; J.L., S.B., E.L., and C.Y.-F. approved final version of manuscript.
ACKNOWLEDGMENTS
The authors thank the participants for their time and effort and Landon Wilson from the targeted metabolomics and proteomics laboratory at the University of Alabama at Birmingham.
REFERENCES
- 1. Myers J, Lee M, Kiratli J. Cardiovascular disease in spinal cord injury: an overview of prevalence, risk, evaluation, and management. Am J Phys Med Rehabil 86: 142–152, 2007. doi: 10.1097/PHM.0b013e31802f0247. [DOI] [PubMed] [Google Scholar]
- 2. Bauman WA, Spungen AM. Disorders of carbohydrate and lipid metabolism in veterans with paraplegia or quadriplegia: a model of premature aging. Metabolism 43: 749–756, 1994. doi: 10.1016/0026-0495(94)90126-0. [DOI] [PubMed] [Google Scholar]
- 3. Bauman WA, Spungen AM. Carbohydrate and lipid metabolism in chronic spinal cord injury. J Spinal Cord Med 24: 266–277, 2001. doi: 10.1080/10790268.2001.11753584. [DOI] [PubMed] [Google Scholar]
- 4. Bauman WA, Spungen AM. Metabolic changes in persons after spinal cord injury. Phys Med Rehabil Clin N Am 11: 109–140, 2000. doi: 10.1016/S1047-9651(18)30150-5. [DOI] [PubMed] [Google Scholar]
- 5. Inskip J, Plunet W, Ramer L, Ramsey JB, Yung A, Kozlowski P, Ramer M, Krassioukov A. Cardiometabolic risk factors in experimental spinal cord injury. J Neurotrauma 27: 275–285, 2010. doi: 10.1089/neu.2009.1064. [DOI] [PubMed] [Google Scholar]
- 6. Nash MS, Tractenberg RE, Mendez AJ, David M, Ljungberg IH, Tinsley EA, Burns-Drecq PA, Betancourt LF, Groah SL. Cardiometabolic syndrome in people with spinal cord injury/disease: guideline-derived and nonguideline risk components in a pooled sample. Arch Phys Med Rehabil 97: 1696–1705, 2016. doi: 10.1016/j.apmr.2016.07.002. [DOI] [PubMed] [Google Scholar]
- 7. Grundy SM. Metabolic syndrome scientific statement by the American Heart Association and the National Heart, Lung, and Blood Institute. Arterioscler Thromb Vasc Biol 25: 2243–2244, 2005. doi: 10.1161/01.ATV.0000189155.75833.c7. [DOI] [PubMed] [Google Scholar]
- 8. Gater DR Jr, Farkas GJ, Berg AS, Castillo C. Prevalence of metabolic syndrome in veterans with spinal cord injury. J Spinal Cord Med 42: 86–93, 2019. doi: 10.1080/10790268.2017.1423266. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 9. Ko H-Y. Metabolic disorders in spinal cord injuries. In: Management and Rehabilitation of Spinal Cord Injuries, edited by Ko H-Y. Singapore: Springer Nature Singapore, 2022. p. 541–558. [Google Scholar]
- 10. Fan Y, Pedersen O. Gut microbiota in human metabolic health and disease. Nat Rev Microbiol 19: 55–71, 2021. doi: 10.1038/s41579-020-0433-9. [DOI] [PubMed] [Google Scholar]
- 11. Régnier M, Van Hul M, Knauf C, Cani PD. Gut microbiome, endocrine control of gut barrier function and metabolic diseases. J Endocrinol 248: R67–R82, 2021. doi: 10.1530/JOE-20-0473. [DOI] [PubMed] [Google Scholar]
- 12. Miele L, Giorgio V, Alberelli MA, De Candia E, Gasbarrini A, Grieco A. Impact of gut microbiota on obesity, diabetes, and cardiovascular disease risk. Curr Cardiol Rep 17: 120, 2015. doi: 10.1007/s11886-015-0671-z. [DOI] [PubMed] [Google Scholar]
- 13. Rapozo DC, Bernardazzi C, de Souza HS. Diet and microbiota in inflammatory bowel disease: the gut in disharmony. World J Gastroenterol 23: 2124–2140, 2017. doi: 10.3748/wjg.v23.i12.2124. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 14. Franzosa EA, Sirota-Madi A, Avila-Pacheco J, Fornelos N, Haiser HJ, Reinker S, Vatanen T, Hall AB, Mallick H, McIver LJ, Sauk JS, Wilson RG, Stevens BW, Scott JM, Pierce K, Deik AA, Bullock K, Imhann F, Porter JA, Zhernakova A, Fu J, Weersma RK, Wijmenga C, Clish CB, Vlamakis H, Huttenhower C, Xavier RJ. Gut microbiome structure and metabolic activity in inflammatory bowel disease. Nat Microbiol 4: 293–305, 2019. [Erratum in Nat Microbiol 4: 898, 2019]. doi: 10.1038/s41564-018-0306-4. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 15. Jia J, Dou P, Gao M, Kong X, Li C, Liu Z, Huang T. Assessment of causal direction between gut microbiota-dependent metabolites and cardiometabolic health: a bidirectional Mendelian randomization analysis. Diabetes 68: 1747–1755, 2019. doi: 10.2337/db19-0153. [DOI] [PubMed] [Google Scholar]
- 16. Guo G, Wu Y, Liu Y, Wang Z, Xu G, Wang X, Liang F, Lai W, Xiao X, Zhu Q, Zhong S. Exploring the causal effects of the gut microbiome on serum lipid levels: a two-sample Mendelian randomization analysis. Front Microbiol 14: 1113334, 2023. doi: 10.3389/fmicb.2023.1113334. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 17. Xu Q, Zhang S-S, Wang R-R, Weng Y-J, Cui X, Wei X-T, Ni J-J, Ren H-G, Zhang L, Pei Y-F. Mendelian randomization analysis reveals causal effects of the human gut microbiota on abdominal obesity. J Nutr 151: 1401–1406, 2021. doi: 10.1093/jn/nxab025. [DOI] [PubMed] [Google Scholar]
- 18. Rizzetto L, Fava F, Tuohy KM, Selmi C. Connecting the immune system, systemic chronic inflammation and the gut microbiome: the role of sex. J Autoimmun 92: 12–34, 2018. doi: 10.1016/j.jaut.2018.05.008. [DOI] [PubMed] [Google Scholar]
- 19. Saad MJ, Santos A, Prada PO. Linking gut microbiota and inflammation to obesity and insulin resistance. Physiology (Bethesda) 31: 283–293, 2016. doi: 10.1152/physiol.00041.2015. [DOI] [PubMed] [Google Scholar]
- 20. Brown JM, Hazen SL. The gut microbial endocrine organ: bacterially derived signals driving cardiometabolic diseases. Annu Rev Med 66: 343–359, 2015. doi: 10.1146/annurev-med-060513-093205. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 21. Utzschneider KM, Kratz M, Damman CJ, Hullar M. Mechanisms linking the gut microbiome and glucose metabolism. J Clin Endocrinol Metab 101: 1445–1454, 2016. [Erratum in J Clin Endocrinol Metab 101: 2622, 2016]. doi: 10.1210/jc.2015-4251. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 22. Kigerl KA, Hall JC, Wang L, Mo X, Yu Z, Popovich PG. Gut dysbiosis impairs recovery after spinal cord injury. J Exp Med 213: 2603–2620, 2016. doi: 10.1084/jem.20151345. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 23. Li J, Van Der Pol W, Eraslan M, McLain A, Cetin H, Cetin B, Morrow C, Carson T, Yarar-Fisher C. Comparison of the gut microbiome composition among individuals with acute or long-standing spinal cord injury vs. able-bodied controls. J Spinal Cord Med 45: 91–99, 2022. doi: 10.1080/10790268.2020.1769949. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 24. Turnbaugh PJ, Ley RE, Mahowald MA, Magrini V, Mardis ER, Gordon JI. An obesity-associated gut microbiome with increased capacity for energy harvest. Nature 444: 1027–1031, 2006. doi: 10.1038/nature05414. [DOI] [PubMed] [Google Scholar]
- 25. Chakraborti CK. New-found link between microbiota and obesity. World J Gastrointest Pathophysiol 6: 110–119, 2015. doi: 10.4291/wjgp.v6.i4.110. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 26. Gungor B, Adiguzel E, Gursel I, Yilmaz B, Gursel M. Intestinal microbiota in patients with spinal cord injury. PLoS One 11: e0145878, 2016. doi: 10.1371/journal.pone.0145878. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27. Muhamad Rizal NS, Neoh HM, Ramli R, Alkp PR, Hanafiah A, Abdul Samat MN, Tan TL, Wong KK, Nathan S, Chieng S, Saw SH, Khor BY. Advantages and limitations of 16S rRNA next-generation sequencing for pathogen identification in the diagnostic microbiology laboratory: perspectives from a middle-income country. Diagnostics (Basel) 10: 816, 2020. doi: 10.3390/diagnostics10100816. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 28. Dethlefsen L, Huse S, Sogin ML, Relman DA. The pervasive effects of an antibiotic on the human gut microbiota, as revealed by deep 16S rRNA sequencing. PLoS Biol 6: e280, 2008. doi: 10.1371/journal.pbio.0060280. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 29.American Diabetes Association. Classification and diagnosis of diabetes. Diabetes Care 38, Suppl: S8–S16, 2015. doi: 10.2337/dc15-S005. [DOI] [PubMed] [Google Scholar]
- 30. Matsuda M, DeFronzo RA. Insulin sensitivity indices obtained from oral glucose tolerance testing: comparison with the euglycemic insulin clamp. Diabetes Care 22: 1462–1470, 1999. doi: 10.2337/diacare.22.9.1462. [DOI] [PubMed] [Google Scholar]
- 31. Matthews DR, Hosker JP, Rudenski AS, Naylor BA, Treacher DF, Turner RC. Homeostasis model assessment: insulin resistance and beta-cell function from fasting plasma glucose and insulin concentrations in man. Diabetologia 28: 412–419, 1985. doi: 10.1007/bf00280883. [DOI] [PubMed] [Google Scholar]
- 32. Phillips DI, Clark PM, Hales CN, Osmond C. Understanding oral glucose tolerance: comparison of glucose or insulin measurements during the oral glucose tolerance test with specific measurements of insulin resistance and insulin secretion. Diabet Med 11: 286–292, 1994. doi: 10.1111/j.1464-5491.1994.tb00273.x. [DOI] [PubMed] [Google Scholar]
- 33. Tura A, Kautzky-Willer A, Pacini G. Insulinogenic indices from insulin and C-peptide: comparison of beta-cell function from OGTT and IVGTT. Diabetes Res Clin Pract 72: 298–301, 2006. doi: 10.1016/j.diabres.2005.10.005. [DOI] [PubMed] [Google Scholar]
- 34. Utzschneider KM, Kahn SE, Polidori DC. Hepatic insulin extraction in NAFLD is related to insulin resistance rather than liver fat content. J Clin Endocrinol Metab 104: 1855–1865, 2019. doi: 10.1210/jc.2018-01808. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 35. Friedewald WT, Levy RI, Fredrickson DS. Estimation of the concentration of low-density lipoprotein cholesterol in plasma, without use of the preparative ultracentrifuge. Clin Chem 18: 499–502, 1972. doi: 10.1093/clinchem/18.6.499. [DOI] [PubMed] [Google Scholar]
- 36. Kumar R, Eipers P, Little RB, Crowley M, Crossman DK, Lefkowitz EJ, Morrow CD. Getting started with microbiome analysis: sample acquisition to bioinformatics. Curr Protoc Hum Genet 82: 18.8.1–18.8.29, 2014. doi: 10.1002/0471142905.hg1808s82. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 37.The Huttenhower Lab. Kneaddata [Online]. https://huttenhower.sph.harvard.edu/kneaddata/ [Accessed 4 March 2024].
- 38. Blanco-Míguez A, Beghini F, Cumbo F, McIver LJ, Thompson KN, Zolfo M, Manghi P, Dubois L, Huang KD, Thomas AM, Nickols WA, Piccinno G, Piperni E, Punčochář M, Valles-Colomer M, Tett A, Giordano F, Davies R, Wolf J, Berry SE, Spector TD, Franzosa EA, Pasolli E, Asnicar F, Huttenhower C, Segata N. Extending and improving metagenomic taxonomic profiling with uncharacterized species using MetaPhlAn 4. Nat Biotechnol 41: 1633–1644, 2023. doi: 10.1038/s41587-023-01688-w. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 39. Beghini F, McIver LJ, Blanco-Míguez A, Dubois L, Asnicar F, Maharjan S, Mailyan A, Manghi P, Scholz M, Thomas AM, Valles-Colomer M, Weingart G, Zhang Y, Zolfo M, Huttenhower C, Franzosa EA, Segata N. Integrating taxonomic, functional, and strain-level profiling of diverse microbial communities with bioBakery 3. eLife 10: e65088, 2021. doi: 10.7554/eLife.65088. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 40. Caspi R, Billington R, Keseler IM, Kothari A, Krummenacker M, Midford PE, Ong WK, Paley S, Subhraveti P, Karp PD. The MetaCyc database of metabolic pathways and enzymes–a 2019 update. Nucleic Acids Res 48: D445–D453, 2020. doi: 10.1093/nar/gkz862. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 41. Suzek BE, Huang H, McGarvey P, Mazumder R, Wu CH. UniRef: comprehensive and non-redundant UniProt reference clusters. Bioinformatics 23: 1282–1288, 2007. doi: 10.1093/bioinformatics/btm098. [DOI] [PubMed] [Google Scholar]
- 42. Oksanen JB, Friendly M, Kindt R, Legendre P, McGlinn D, Minchin PR, O’Hara RB, Simpson GL, Solymos P, Stevens MHH, Wagner H, Barbour M, Bedward M, Bolker B, Borcard D, Carvalho G, Chirico M, De Caceres M, Durand S, Evangelista HBA, FitzJohn R, Friendly M, Furneaux B, Hannigan G, Hill MO, Lahti L, McGlinn D, Ouellette M-H, Cunha ER, Smith T, Stier A, Ter Braak CJF, Weedon J. Vegan: Community Ecology Package. R Package Version 2.2-0 [Online]. http://CRAN.Rproject.org/package=vegan [Accessed 1 March 2023].
- 43. González I, Déjean S, Martinh PGP, Baccini A. CCA: an R package to extend canonical correlation analysis. J Stat Soft 23: 1–14, 2008. doi: 10.18637/jss.v023.i12. [DOI] [Google Scholar]
- 44. Rohart F, Gautier B, Singh A, Le Cao KA. mixOmics: an R package for ‘omics’ feature selection and multiple data integration. PLoS Comput Biol 13: e1005752, 2017. doi: 10.1371/journal.pcbi.1005752. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 45.Omics Data Integration Project. MixMC Pre-processing [Online]. http://mixomics.org/mixmc/mixmc-preprocessing/ [Accessed 21 January 2023].
- 46. González I, Cao K-AL, Davis MJ, Déjean S. Visualising associations between paired ‘omics’ data sets. BioData Min 5: 19, 2012. doi: 10.1186/1756-0381-5-19. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 47. Leurgans SE, Moyeed RA, Silverman BW. Canonical correlation analysis when the data are curves. J R Stat Soc Series B Methodol 55: 725–740, 1993. doi: 10.1111/j.2517-6161.1993.tb01936.x. [DOI] [Google Scholar]
- 48. Vinod HD. Canonical ridge and econometrics of joint production. J Econ 4: 147–166, 1976. doi: 10.1016/0304-4076(76)90010-5. [DOI] [Google Scholar]
- 49. Maskarinec G, Raquinio P, Kristal BS, Setiawan VW, Wilkens LR, Franke AA, Lim U, Le Marchand L, Randolph TW, Lampe JW, Hullar MAJ. The gut microbiome and type 2 diabetes status in the Multiethnic Cohort. PLoS One 16: e0250855, 2021. doi: 10.1371/journal.pone.0250855. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 50. Zhang X, Shen D, Fang Z, Jie Z, Qiu X, Zhang C, Chen Y, Ji L. Human gut microbiota changes reveal the progression of glucose intolerance. PLoS One 8: e71108, 2013. doi: 10.1371/journal.pone.0071108. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 51. Pinart M, Dötsch A, Schlicht K, Laudes M, Bouwman J, Forslund SK, Pischon T, Nimptsch K. Gut microbiome composition in obese and non-obese persons: a systematic review and meta-analysis. Nutrients. 14: 12, 2021. doi: 10.3390/nu14010012. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 52. Lambeth SM, Carson T, Lowe J, Ramaraj T, Leff JW, Luo L, Bell CJ, Shah VO. Composition, diversity and abundance of gut microbiome in prediabetes and type 2 diabetes. J Diabetes Obes 2: 1–7, 2015. doi: 10.15436/2376-0949.15.031. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 53. Hou K, Wu Z-X, Chen X-Y, Wang J-Q, Zhang D, Xiao C, Zhu D, Koya JB, Wei L, Li J, Chen Z-S. Microbiota in health and diseases. Signal Transduct Target Ther 7: 135, 2022. doi: 10.1038/s41392-022-00974-4. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 54. Amiri P, Hosseini SA, Ghaffari S, Tutunchi H, Ghaffari S, Mosharkesh E, Asghari S, Roshanravan N. Role of butyrate, a gut microbiota derived metabolite, in cardiovascular diseases: a comprehensive narrative review. Front Pharmacol 12: 837509, 2021. doi: 10.3389/fphar.2021.837509. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 55. Ma W, Nguyen LH, Song M, Wang DD, Franzosa EA, Cao Y, Joshi A, Drew DA, Mehta R, Ivey KL, Strate LL, Giovannucci EL, Izard J, Garrett W, Rimm EB, Huttenhower C, Chan AT. Dietary fiber intake, the gut microbiome, and chronic systemic inflammation in a cohort of adult men. Genome Med 13: 102, 2021. doi: 10.1186/s13073-021-00921-y. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 56. Vangay P, Johnson AJ, Ward TL, Al-Ghalith GA, Shields-Cutler RR, Hillmann BM, Lucas SK, Beura LK, Thompson EA, Till LM, Batres R, Paw B, Pergament SL, Saenyakul P, Xiong M, Kim AD, Kim G, Masopust D, Martens EC, Angkurawaranon C, McGready R, Kashyap PC, Culhane-Pera KA, Knights D. US immigration westernizes the human gut microbiome. Cell 175: 962–972.e10, 2018. doi: 10.1016/j.cell.2018.10.029. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 57. Shilo S, Godneva A, Rachmiel M, Korem T, Bussi Y, Kolobkov D, Karady T, Bar N, Wolf BC, Glantz-Gashai Y, Cohen M, Zuckerman-Levin N, Shehadeh N, Gruber N, Levran N, Koren S, Weinberger A, Pinhas-Hamiel O, Segal E. The gut microbiome of adults with type 1 diabetes and its association with the host glycemic control. Diabetes Care 45: 555–563, 2022. doi: 10.2337/dc21-1656. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 58. Kwan S-Y, Sabotta CM, Joon A, Wei P, Petty LE, Below JE, Wu X, Zhang J, Jenq RR, Hawk ET, McCormick JB, Fisher-Hoch SP, Beretta L. Gut microbiome alterations associated with diabetes in Mexican Americans in South Texas. mSystems 7: e0003322, 2022. doi: 10.1128/msystems.00033-22. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 59. van Trijp MPH, Schutte S, Esser D, Wopereis S, Hoevenaars FPM, Hooiveld GJEJ, Afman LA. Minor changes in the composition and function of the gut microbiota during a 12-week whole grain wheat or refined wheat intervention correlate with liver fat in overweight and obese adults. J Nutr 151: 491–502, 2021. doi: 10.1093/jn/nxaa312. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 60. Yuan X, Chen R, Zhang Y, Lin X, Yang X, McCormick KL. Gut microbiota of Chinese obese children and adolescents with and without insulin resistance. Front Endocrinol (Lausanne) 12: 636272, 2021. doi: 10.3389/fendo.2021.636272. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 61. Testerman T, Li Z, Galuppo B, Graf J, Santoro N. Insights from shotgun metagenomics into bacterial species and metabolic pathways associated with NAFLD in obese youth. Hepatol Commun 6: 1962–1974, 2022. doi: 10.1002/hep4.1944. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 62. Orsso CE, Peng Y, Deehan EC, Tan Q, Field CJ, Madsen KL, Walter J, Prado CM, Tun HM, Haqq AM. Composition and functions of the gut microbiome in pediatric obesity: relationships with markers of insulin resistance. Microorganisms 9: 1490, 2021. doi: 10.3390/microorganisms9071490. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 63. Braccia DJ, Jiang X, Pop M, Hall AB. The capacity to produce hydrogen sulfide (H2S) via cysteine degradation is ubiquitous in the human gut microbiome. Front Microbiol 12: 705583, 2021. doi: 10.3389/fmicb.2021.705583. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 64. Walker A, Schmitt-Kopplin P. The role of fecal sulfur metabolome in inflammatory bowel diseases. Int J Med Microbiol 311: 151513, 2021. doi: 10.1016/j.ijmm.2021.151513. [DOI] [PubMed] [Google Scholar]
- 65. Brand EC, Klaassen MAY, Gacesa R, Vich Vila A, Ghosh H, de Zoete MR, Boomsma DI, Hoentjen F, Horjus Talabur Horje CS, van de Meeberg PC, Willemsen G, Fu J, Wijmenga C, van Wijk F, Zhernakova A, Oldenburg B, Weersma RK; Dutch TWIN-IBD consortium and the Dutch Initiative on Crohn and Colitis. Healthy cotwins share gut microbiome signatures with their inflammatory bowel disease twins and unrelated patients. Gastroenterology. 160: 1970–1985, 2021. doi: 10.1053/j.gastro.2021.01.030. [DOI] [PubMed] [Google Scholar]
- 66. Nüse B, Mattner J. L-arginine as a novel target for clinical intervention in inflammatory bowel disease. Exploration Immunol 80–89, 2021. doi: 10.37349/ei.2021.00008. 37358082 [DOI] [Google Scholar]
- 67. Chelakkot C, Ghim J, Ryu SH. Mechanisms regulating intestinal barrier integrity and its pathological implications. Exp Mol Med 50: 1–9, 2018. doi: 10.1038/s12276-018-0126-x. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 68. Jin M, Kalainy S, Baskota N, Chiang D, Deehan EC, McDougall C, Tandon P, Martínez I, Cervera C, Walter J, Abraldes JG. Faecal microbiota from patients with cirrhosis has a low capacity to ferment non-digestible carbohydrates into short-chain fatty acids. Liver Int 39: 1437–1447, 2019. doi: 10.1111/liv.14106. [DOI] [PubMed] [Google Scholar]
- 69. Takahashi K, Nishida A, Fujimoto T, Fujii M, Shioya M, Imaeda H, Inatomi O, Bamba S, Sugimoto M, Andoh A. Reduced abundance of butyrate-producing bacteria species in the fecal microbial community in Crohn’s disease. Digestion 93: 59–65, 2016. [Erratum in Digestion 93: 174, 2016]. doi: 10.1159/000441768. [DOI] [PubMed] [Google Scholar]
- 70. Hiseni P, Snipen L, Wilson RC, Furu K, Hegge FT, Rudi K. Prediction of high fecal propionate-to-butyrate ratios using 16S rRNA-based detection of bacterial groups with liquid array diagnostics. BioTechniques 74: 9–21, 2023. doi: 10.2144/btn-2022-0045. [DOI] [PubMed] [Google Scholar]
- 71. Ju T, Kong JY, Stothard P, Willing BP. Defining the role of Parasutterella, a previously uncharacterized member of the core gut microbiota. ISME J 13: 1520–1534, 2019. doi: 10.1038/s41396-019-0364-5. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 72. Bush JR, Alfa MJ. Increasing levels of Parasutterella in the gut microbiome correlate with improving low-density lipoprotein levels in healthy adults consuming resistant potato starch during a randomised trial. BMC Nutr 6: 72, 2020. doi: 10.1186/s40795-020-00398-9. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 73. Otani S, Coopersmith CM. Gut integrity in critical illness. J Intensive Care 7: 17, 2019. doi: 10.1186/s40560-019-0372-6. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 74. Paola P, Patrice DC. Mucus barrier, mucins and gut microbiota: the expected slimy partners? Gut 69: 2232, 2020. [Erratum in Gut 72: e7, 2023]. doi: 10.1136/gutjnl-2020-322260. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 75. Uppakarn K, Bangpanwimon K, Hongpattarakere T, Wanitsuwan W. Comparison of the human gut microbiota between normal control subjects and patients with colonic polyps and colorectal cancer (Preprint). Res Sq 2021. doi: 10.21203/rs.3.rs-1172479/v1. [DOI] [Google Scholar]
- 76. Raimondi S, Musmeci E, Candeliere F, Amaretti A, Rossi M. Identification of mucin degraders of the human gut microbiota. Sci Rep 11: 11094, 2021. doi: 10.1038/s41598-021-90553-4. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 77. Loubinoux J, Bronowicki J-P, Pereira IAC, Mougenel J-L, Faou AE. Sulfate-reducing bacteria in human feces and their association with inflammatory bowel diseases. FEMS Microbiol Ecol 40: 107–112, 2002. doi: 10.1111/j.1574-6941.2002.tb00942.x. [DOI] [PubMed] [Google Scholar]
- 78. Ijssennagger N, van der Meer R, van Mil SWC. Sulfide as a mucus barrier-breaker in inflammatory bowel disease? Trends Mol Med 22: 190–199, 2016. doi: 10.1016/j.molmed.2016.01.002. [DOI] [PubMed] [Google Scholar]
- 79. Kushkevych I, Dordević D, Vítězová M. Toxicity of hydrogen sulfide toward sulfate-reducing bacteria Desulfovibrio piger Vib-7. Arch Microbiol 201: 389–397, 2019. doi: 10.1007/s00203-019-01625-z. [DOI] [PubMed] [Google Scholar]
- 80. Kunath BJ, Hickl O, Queirós P, Martin-Gallausiaux C, Lebrun LA, Halder R, Laczny CC, Schmidt TSB, Hayward MR, Becher D, Heintz-Buschart A, de Beaufort C, Bork P, May P, Wilmes P. Alterations of oral microbiota and impact on the gut microbiome in type 1 diabetes mellitus revealed by integrated multi-omic analyses. Microbiome 10: 243, 2022. doi: 10.1186/s40168-022-01435-4. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 81. Qi Y, Wu H-M, Yang Z, Zhou Y-F, Jin L, Yang M-F, Wang F-Y. New insights into the role of oral microbiota dysbiosis in the pathogenesis of inflammatory bowel disease. Dig Dis Sci 67: 42–55, 2022. doi: 10.1007/s10620-021-06837-2. [DOI] [PubMed] [Google Scholar]
- 82. Yau A, Adams J, White M, Nicolaou M. Differences in diet quality and socioeconomic patterning of diet quality across ethnic groups: cross-sectional data from the HELIUS Dietary Patterns study. Eur J Clin Nutr 74: 387–396, 2020. doi: 10.1038/s41430-019-0463-4. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 83. Borrello K, Lim U, Park S-Y, Monroe KR, Maskarinec G, Boushey CJ, Wilkens LR, Randolph TW, Le Marchand L, Hullar MA, Lampe JW. Dietary intake mediates ethnic differences in gut microbial composition. Nutrients 14: 660, 2022. doi: 10.3390/nu14030660. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 84. Berry SE, Valdes AM, Drew DA, Asnicar F, Mazidi M, Wolf J, Capdevila J, Hadjigeorgiou G, Davies R, Al Khatib H, Bonnett C, Ganesh S, Bakker E, Hart D, Mangino M, Merino J, Linenberg I, Wyatt P, Ordovas JM, Gardner CD, Delahanty LM, Chan AT, Segata N, Franks PW, Spector TD. Human postprandial responses to food and potential for precision nutrition. Nat Med 26: 964–973, 2020. doi: 10.1038/s41591-020-0934-0. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 85. Fritz MS, Mackinnon DP. Required sample size to detect the mediated effect. Psychol Sci 18: 233–239, 2007. doi: 10.1111/j.1467-9280.2007.01882.x. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 86. Sim M, Kim S-Y, Suh Y. Sample size requirements for simple and complex mediation models. Educ Psychol Meas 82: 76–106, 2021. doi: 10.1177/00131644211003261. [DOI] [PMC free article] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Data Availability Statement
The microbiome sequence data and metadata are available upon reasonable request.
