



Abstract
Nearly every mammalian cell division is accompanied by a mutational event that becomes fixed in a daughter cell. When carried forward to additional cell progeny, a clone of variant cells can emerge. As a result, mammals are complex mosaics of clones that are genetically distinct from one another. Recent high-throughput sequencing studies have revealed that mosaicism is common, clone sizes often increase with age and specific variants can affect tissue function and disease development. Variants that are acquired during early embryogenesis are shared by multiple cell types and can affect numerous tissues. Within tissues, variant clones compete, which can result in their expansion or elimination. Embryonic mosaicism has clinical implications for genetic disease severity and transmission but is likely an under-recognized phenomenon. To better understand its implications for mosaic individuals, it is essential to leverage research tools that can elucidate the mechanisms by which expanded embryonic variants influence development and disease.
Introduction
The remarkable genetic variation across humans is due to both genetic changes acquired in the germline and those acquired post-zygotically (Fig. 1). Mutations occur constantly in mammalian cells but are usually efficiently repaired. Nevertheless, most cell divisions are accompanied by the permanent acquisition of at least one single-nucleotide substitution or small insertion or deletion (indel)1–6, which can be propagated to cellular progeny, generating a clone of related variant cells. This phenomenon is known as somatic mosaicism or post-zygotic mosaicism. In other words, mosaicism refers to any mutation that is acquired in the nuclear genome after the zygote stage of embryogenesis, meaning that the resulting genetic variant is present in some, but not all, cells of the organism.
Fig. 1 |. Mosaicism is defined by the timing and lineage of variant acquisition.
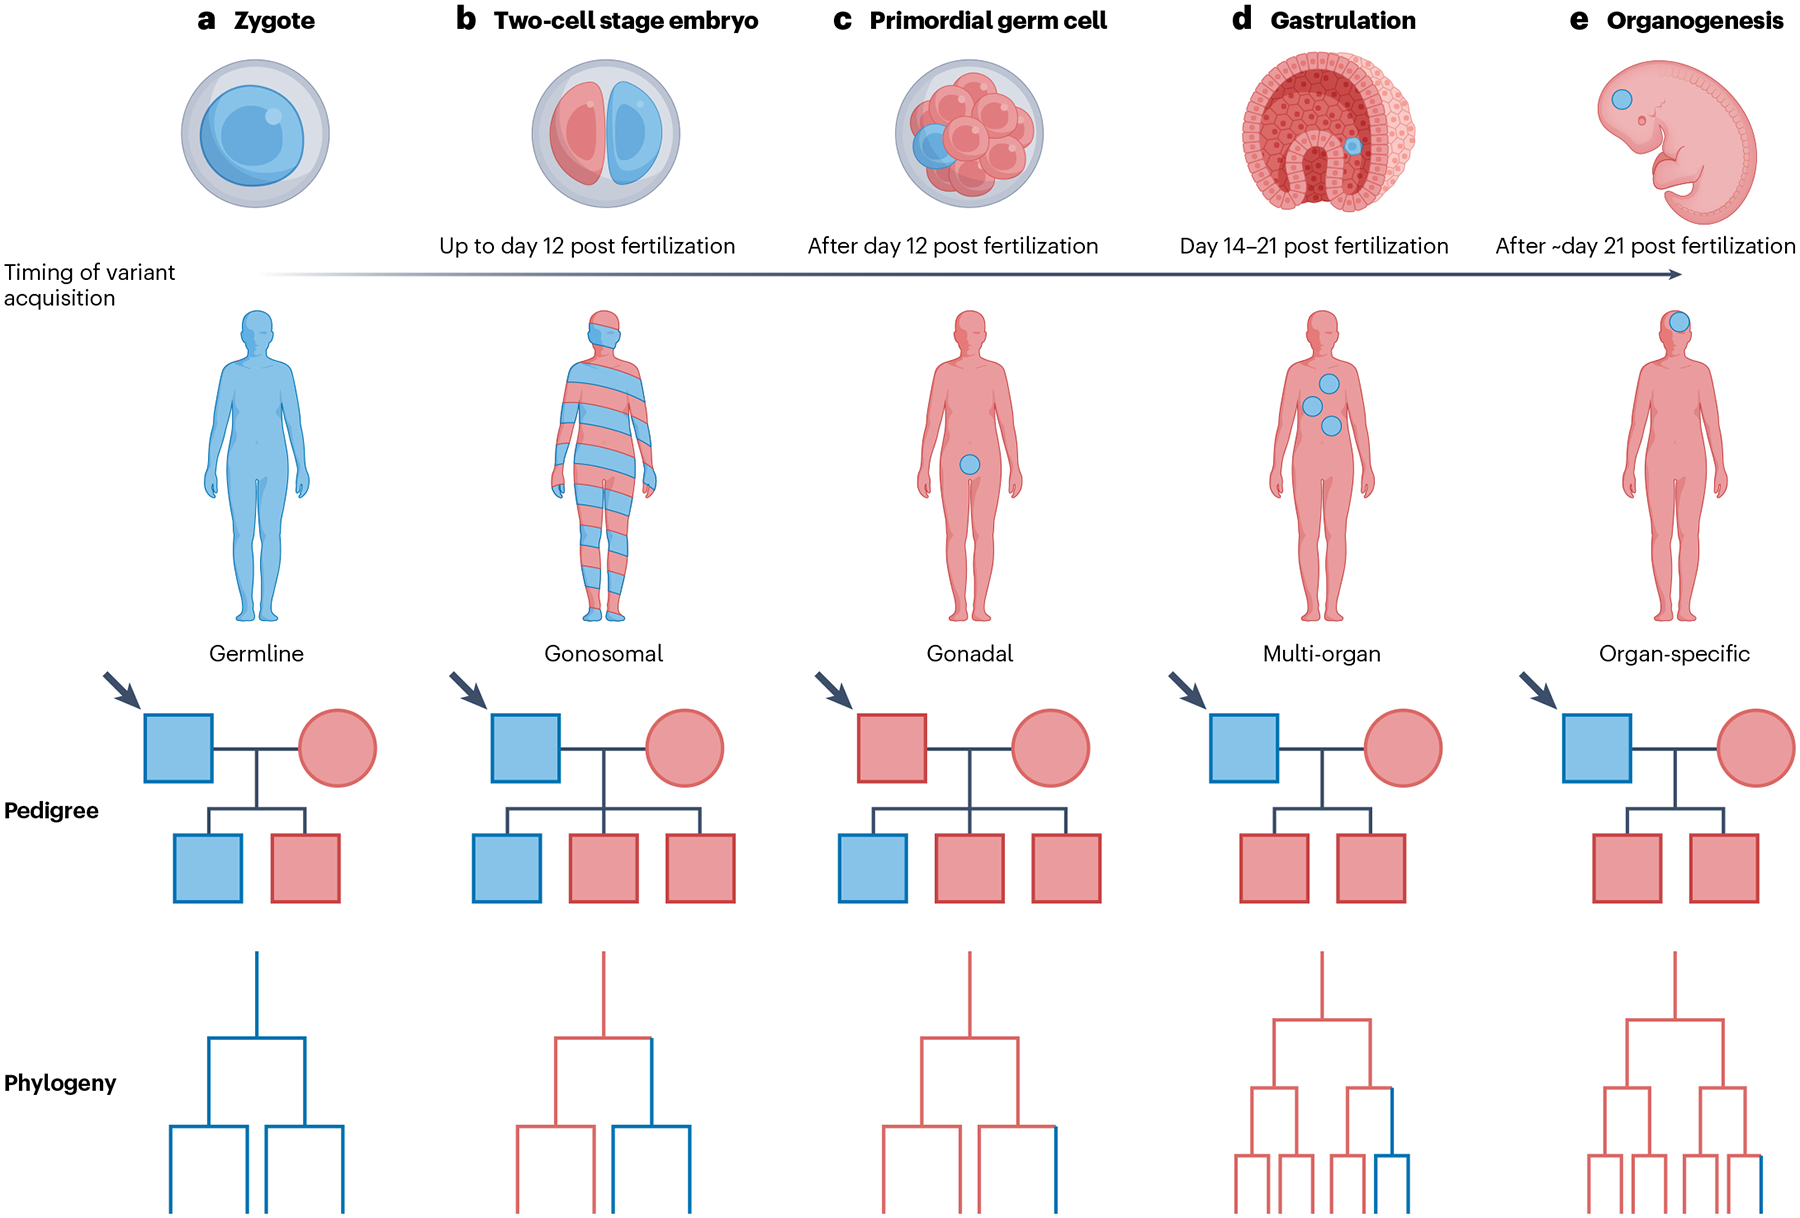
Variants can be acquired at different stages of embryo development, and this timing is partially responsible for the ultimate distribution of the variant. This transmission of a heterozygous variant driving a dominant disease trait is shown, including cells carrying a variant or individuals potentially affected by the disease (blue). The proband represented by the human figure is the male at the top left of the pedigrees (indicated by the arrow). a, If the variant is acquired at or before fertilization, it will be present in all cells of the individual. Transmission to the next generation follows the rules of Mendelian genetics, and the phylogeny of cells in the individual shows the variant present at all branchpoints. Transmission rate is 50%. b, If the variant occurs in the very early embryo, before specification of the primordial germ cells, it will be present in both somatic and germ cell tissue. The individual may be phenotypically affected (depending on the impacted tissues and degree of mosaicism) and can pass the variant to his or her offspring. The variant occurs in a branchpoint of the phylogeny that represents a shared ancestor of somatic and germ cells. Transmission rate may be less than 50%. c, If the variant occurs in a primordial germ cell, it will be limited to the germ cells and can be transmitted to offspring, but the mosaic individual is unlikely to exhibit a phenotype. The last common phylogenetic cellular ancestor was already confined to the germ cell lineage. Transmission rate may be lower than 50%. d, If a variant arises during gastrulation, the variant will be confined to the tissues derived from that specific germ layer, but it may be seen in multiple cell types from that germ layer depending on the timing of acquisition. The last common phylogenetic ancestor is confined to the ectoderm, mesoderm or endoderm. The individual may be phenotypically affected, depending on the variant and the organ. e, If the variant arises later during embryogenesis, it is likely limited to one organ. The individual may be phenotypically affected, depending on the variant and the organ. The variant appears at a late branchpoint of the phylogenetic tree.
Depending on the type of variant, the affected gene and the timing, and the affected cell lineage during development, somatic mosaicism can affect organismal health. Recent studies have revealed the ubiquity of mosaicism across many tissues of older adults, suggesting that it plays an important role in adult physiology, disease, ageing and cancer5,7–12. Until recently, research has focused largely on clusters of variant cells that are confined to a particular tissue, such as those that lead to clonal haematopoiesis7–12. However, variants that are acquired much earlier in life, during embryogenesis, have the potential to affect many different tissues of an organism, with distinct pathologic consequences.
During the massive cellular expansion of embryonic and fetal development, there is ample opportunity for an embryo to acquire variants and for clones to emerge. By the time a human baby is born, its genetic landscape resembles a mosaic tile artwork, with clusters of related cells sharing variants that were acquired at some earlier time point. Embryonically acquired variants have the propensity to affect large proportions of cells in multiple tissues (Fig. 1). A variant that is acquired between the 2-cell to 4-cell stage and gastrulation will likely be found in diverse downstream progeny, including germ cells and somatic cells (gonosomal mosaicism)13–15. A variant that is embryonically acquired but after gastrulation can be shared by several tissues with a common embryonic origin, or may be tissue-specific if acquired after the onset of organogenesis6,13–16. A variant may also be confined to the germ cell compartment (gonadal mosaicism)13–15.
Large-scale sequencing projects have revealed the prevalence of embryonic mosaicism and its potential to contribute to the genetic disease burden17–22. Recent work has suggested that early embryonic cell divisions are uniquely vulnerable to mutational events2–6,16,23,24. Furthermore, the size of variant clones during development has been shown to deviate from expected proportions owing to the dynamic nature of cellular competition. For example, cells with deleterious variants can be outcompeted by wild-type cells, or a variant can confer an advantage that allows its progeny to expand even if the variant may be harmful to organismal health25. These findings highlight that genetic variants acquired during early embryogenesis undergo a highly dynamic developmental process influenced by multiple factors, with implications for disease outcomes.
Here, we review the phenomenon of embryonic mosaicism, current knowledge about the frequency of embryonic mosaic variants and their contribution to genetic disorders, the mechanisms through which mosaic clones can have an outsized impact on specific tissues due to cell competition, and the functional consequences of mosaicism for embryo viability and the health of the organism. We also describe model systems for studying mosaicism. The whole range of genetic variation can contribute to mosaicism, including base substitutions, indels, structural variants and aneuploidies14,26. However, detecting structural variants in large-scale datasets remains challenging; as a result, rates of mosaicism resulting from base substitutions and indels are better understood than those for structural variants. Moreover, because structural variation can affect more than one gene, its biological impact is often ambiguous. To enable an in-depth discussion of the mechanisms of selection and cell competition, we provide only a brief overview of aneuploidy mosaicism (Box 1) and focus this Review on mosaicism arising from base substitutions and indels. For additional discussions of mosaicism caused by aneuploidies or structural variants, we refer readers to other reviews27–31.
Box 1. Aneuploidy — a special case of mosaicism.
Numerous types of mosaic variants can affect embryo viability, but mosaic aneuploidy is one area of early embryonic mosaicism that has been more thoroughly investigated due to its immediate relevance for in vitro fertilization. Concerns about the health of children born from mosaic aneuploid embryos and the likelihood of successful pregnancy meant that for years most of these embryos were not transferred in in vitro fertilization clinics146. However, several studies have found that mosaic aneuploid embryos can develop into healthy, euploid offspring146 and have found either no difference in outcomes147 or a slightly higher miscarriage rate148. More specifically, clinical outcomes are similar when the embryos that are transferred have low to medium-grade mosaicism (<50% aneuploid cells), whereas embryos with high-grade mosaicism seem to be extensively affected in the inner-cell mass (cells in the blastocyst that will eventually differentiate to form the embryo) as well as the extra-embryonic lineages (those that develop into structures that support the developing embryo, such as the placenta and the umbilical cord) and are thus likely to be miscarried or result in aneuploid offspring147. Studies of pregnancies lost in the first trimester also suggest that extensive mosaicism that affects the extra-embryonic mesoderm and is not confined to the chorionic villi is associated with adverse outcomes149. Furthermore, direct observation of apparently healthy human embryos demonstrates that the first cell division produces high rates of mosaic aneuploidy150. Sex chromosomal anomalies, such as Turner syndrome, are some of the most common mosaic chromosomal alterations and have been reviewed elsewhere151,152.
In some cases, aneuploidy causes such dire consequences to the embryo that only mosaic embryos survive; this is a form of obligate mosaicism. For example, full triploidy is compatible with life only in the mosaic state, and triploid cells may be outcompeted in dynamic tissues such as the blood over time153. Additionally, trisomy rescue is essentially a reversion event in aneuploid cells, in which one of the three chromosome copies is lost during cell division to restore the diploid genome in at least a portion of the cells of the organism154. Aneuploid cells may not be at such a disadvantage in the placenta where they are more tolerated155. Along these lines, the impact of aneuploidy has also been observed in human gastruloids, in which aneuploid cells undergo apoptosis and are depleted from embryonic lineages but are able to survive in extra-embryonic lineages156. In the pre-gastrulation mouse embryo, aneuploid cells exhibit higher levels of proteotoxic stress and undergo p53-dependent, autophagy-mediated apoptosis, whereas healthy diploid cells compensate for the loss of their aneuploid neighbours by increasing their proliferation rates157 (Fig. 4).
Finally, mosaic aneuploidy has also been observed in cell culture where there is less negative selection against such cells, demonstrating the context dependence of the consequences of mosaicism. For example, human pluripotent stem cells that acquire aneuploidies in cell culture have an advantage over wild-type cells, which are eliminated via mechanical compression and relocalization of YAP158.
In addition to numerical chromosome anomalies, genomic rearrangement of one or more chromosome segments can occur. Of these structural variants, copy number variants (CNVs) such as deletions or duplications are among the most prevalent. CNVs contribute substantially to new mutational events and have been estimated to occur at rates 100–10,000 times higher than single-nucleotide variants on average, although the rate is locus-specific159. Whereas recurrent CNVs are typically mediated by non-allelic homologous recombination and thus largely limited to meiosis, post-zygotic non-recurrent CNVs have been reported at rates ranging from ~0.5% to 5.0% in the diagnostic setting160,161. The observation of mosaic CNVs in rare diseases — for example, segmental neurofibromatosis type 1 resulting from deletions encompassing NF1 — underscores the clinical relevance of these post-zygotic mutational events162.
The landscape of embryonic mosaicism
The human body consists of trillions of cells that have been amplified from a single fertilized egg32. Given this enormous expansion, the rates and context of variant acquisition, which vary across tissue types12, are important to consider. Moreover, variant acquisition rates vary temporally in the early embryo, as it undergoes a dramatic transition from the transcriptional silence of a germ cell to the vigorous transcriptional environment of early development. Several approaches to estimate variant acquisition rates and timing, using either adult or fetal tissue samples, are discussed in the following section.
Variant acquisition rates during development
Embryonic variant acquisition rates are highest during the first few cell divisions, even before cells undergo fate specification or execute their own intrinsic transcriptional programmes1–6,16,23,24. This phenomenon could be due to the suppression of cell cycle checkpoints and apoptosis and the tolerance of replication fork stress that are required by rapid early cell divisions (reviewed elsewhere33,34). The results of this elevated early variant acquisition rate have been demonstrated through multiple approaches, including phylogenetic reconstructions from genome sequencing data of ex vivo grown tissue colonies or microbiopsy samples, bulk genome sequencing or transcriptomic sequencing of tissue samples (Fig. 2). In some cases, a combinatorial approach with multiple techniques may yield additional insight into relationships between variants and the timing of their acquisition.
Fig. 2 |. The timing of variant acquisition and the variant allele frequency can be estimated from adult or fetal tissue.
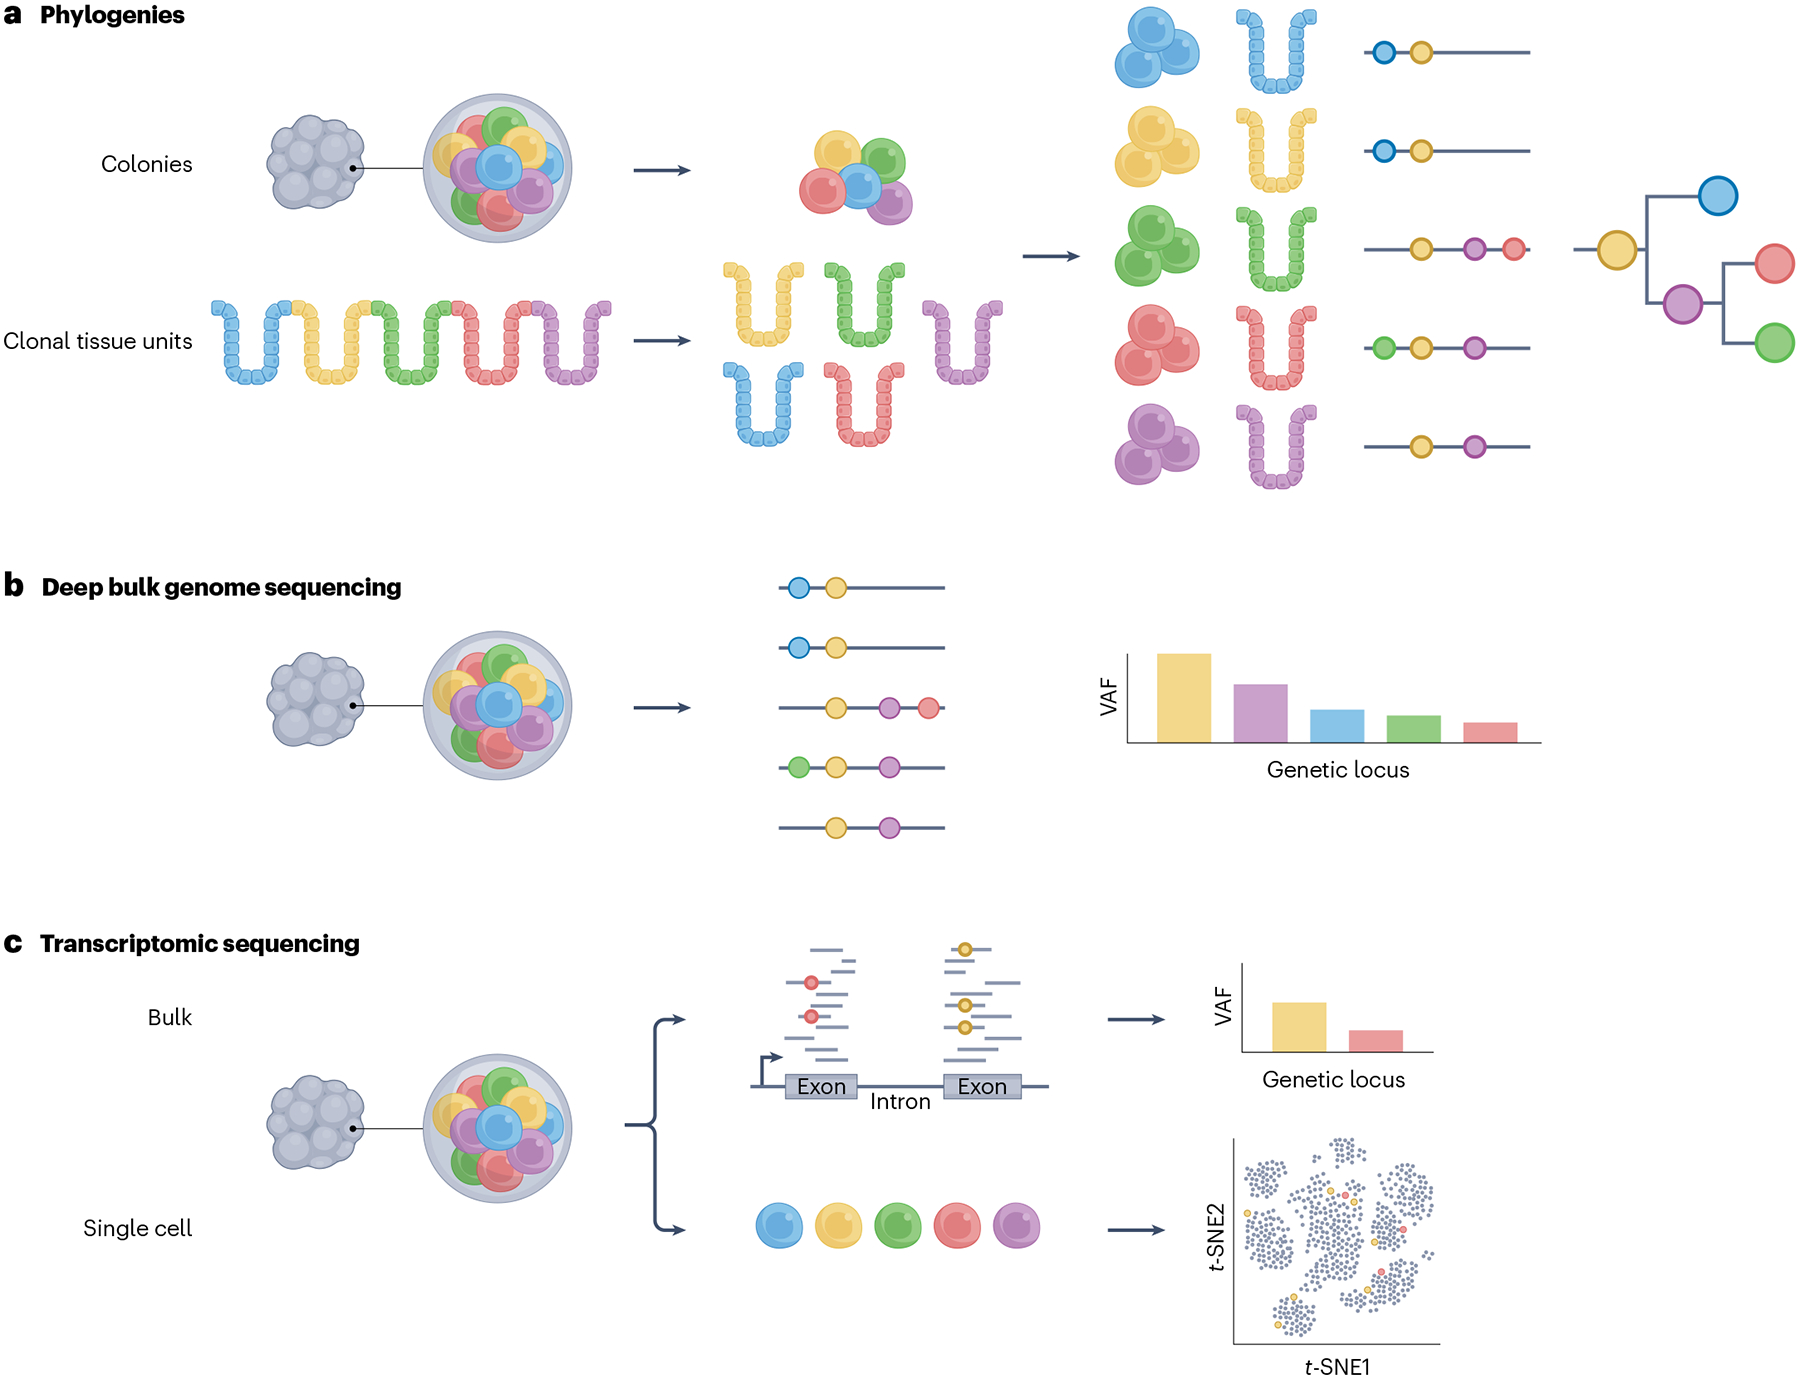
Numerous sequencing techniques can be used to reconstruct early cell lineages and determine the variant allele frequency (VAF) of mosaic variants. a, Genome sequencing is performed on individual single cell-derived colonies or clonal tissue units such as colonic crypts (obtained using a strategy that can capture a clean clone, such as laser capture microdissection). The shared variants between the clonal genomes are used to construct a phylogenetic tree of clone relationships. This can help infer timing of variant acquisition. For example, if the variant arose early in development of that tissue or region, the variant will be present in all or most clones. b, Genome sequencing is performed on bulk tissue samples. The percentage of sequencing reads that contain a particular variant is used to calculate the VAF. The VAF can be used to infer the proportion of cells within the bulk sample that carry the variant. Because most variants will be heterozygous, the proportion of cells harbouring the variant is calculated to be double that of the VAF. c, Bulk RNA sequencing (RNA-seq) data can be used to determine the VAF of variants that are present in the exons of expressed genes in a particular tissue. Because mRNAs can be expressed at high or low levels, deep sequencing is usually needed to identify variants. Furthermore, some variant-containing RNAs are degraded rapidly, making it difficult to identify the variant. If variants are at the 5′ end of the transcript, sensitivity may be reduced as RNA-seq is usually biased towards the 3′ end. Single-cell RNA sequencing (scRNA-seq) can also provide information about the identity of cells carrying a variant, although it has limited sensitivity due to the requirement for high coverage of transcripts.
For phylogenetic reconstruction using variants acquired by single cells, numerous single cell-derived colonies are grown from a tissue of interest. Genome sequencing is performed on each colony, and variants that differ among the colonies are used as barcodes; colonies which share variants have a common ancestor, and the number of shared and distinct variants among colonies can be used to infer variant acquisition rates. Colony sequencing of haematopoietic tissues from an 8-week-old and an 18-week-old human fetus revealed that even at these early developmental time points, stem and progenitor cells carry dozens of variants, many of which are shared with diverse non-haematopoietic tissues4. These phylogenies suggest that the single-nucleotide variant acquisition rate during the first three cell divisions in the embryo is 2.4 variants per division, with the rate dropping to <0.9 variants per division after the 8-cell to 16-cell stage4, a result consistent with previous mathematical modelling2,3. In general, multiple studies relying on phylogenies from either fetal or adult tissue estimate the variant acquisition rate during the first few cell divisions to be between 1.3 and 3.8 per cell division4,16,24,35.
Colony sequencing can also be performed on non-haematopoietic tissues, such as induced pluripotent stem cells from reprogrammed fibroblasts, which also generate single-cell clones36, or on single-cell isolations from warm autopsy tissue specimens16. Indeed, colony sequencing of clones derived from neural progenitor cells from post-mortem human fetuses suggested that variant acquisition in neural progenitors during neurogenesis might be even higher, occurring at a rate of 5.1 single-nucleotide variants per day, suggesting that certain lineages may exhibit unique variant acquisition properties during their rapid expansion35.
Phylogenies can also be reconstructed by sequencing microbe-opsies across a tissue sample. Clonal units, such as colonic crypts, function similarly to ex vivo-derived colonies. Early applications of this approach in mice demonstrated the feasibility of reconstructing phylogenies back to the very first cell division in the embryo and suggested elevated early embryonic variant acquisition rates1. Phylogenies constructed from adult human tissues give nearly identical estimates of early embryonic variant acquisition rates5.
Deep sequencing of non-clonal bulk populations can also lend insight into clone proportions and variant acquisition timing. If a variant was acquired at the 2-cell or 4-cell stage and is present in one allele (that is, heterozygous in those cells) the variant will theoretically appear in 25% or 12% of sequencing reads, resulting in a variant allele frequency (VAF) of 0.25 or 0.12, respectively. (This is distinct from the VAF of a heterozygous variant inherited from a parent, which will be represented in 50% of the reads (VAF 0.5).) If the same mosaic variant is observed in additional tissues at a similar VAF, it is indicative of a shared cellular origin, thus allowing inferences concerning acquisition timing. Application of this approach to multiple tissues from a fetus with polycystic kidney disease revealed eight variants that were present across all tissues, suggesting a very early development origin; all exhibited VAFs were consistent with acquisition at the 2-cell or 4-cell stage23. This approach is also feasible with ultradeep sequencing of adult tissues, such as the brain, where it has been used to validate elevated early embryonic variant acquisition and demonstrated that about half of individuals carry a likely pathogenic variant at a VAF of at least 1% in brain cells24. In some cases, targeted deep sequencing may be combined with colony sequencing, known as the capture–recapture approach, to characterize the VAF of early embryonic variants identified in the phylogenies16,37.
RNA sequencing (RNA-seq) data are also being used to examine mosaicism. A recent analysis queried the massive RNA-seq dataset in the Genotype Tissue Expression (GTEx) project, which includes samples of >50 tissues from almost 1,000 individuals. This dataset revealed that an estimated 41% of prenatal variants are acquired in either the zygote to gastrula phase or during the development of the neural ectoderm6, although this analysis is limited to variants that occur within transcriptionally active genes for a particular adult tissue, and also would miss variants under-represented in sequenced RNA due to nonsense-mediated decay. Single-cell RNA sequencing (scRNA-seq) is a potential option for identifying both a variant and the cell types in which it is present38. However, detection is limited by the low depth of scRNA-seq and, similar to bulk RNA-seq, the requirement that the variant be located within an expressed transcript. Some groups have attempted to overcome the challenges of genotyping with scRNA-seq by first amplifying specific regions of interest in the scRNA-seq library39 or by pairing it with bulk deep genome sequencing40.
Variant characteristics during development
Variants that are acquired at different stages of embryogenesis exhibit distinct genetic features. Variants predicted to be acquired pre gastrulation tend to be represented in higher proportions of cells (higher VAFs) than those acquired post gastrulation and are typically found in multiple organs2,6,41, as expected. They also exhibit a lower proportion of non-synonymous (leading to protein-coding changes) compared with synonymous (silent) variants. This lower dN/dS ratio suggests that early embryonic variants are subject to stronger negative selective pressures. Stronger negative selection would be more likely to decrease embryo survival. Thus, the early embryonic variants observed in living individuals are more likely to be found in genes in which loss of function is well tolerated41.
Selective pressures on embryonic variants also seem to vary based on observed VAFs. In the GTEx dataset, low-VAF embryonic variants have the highest score for likely deleterious variants, based on the combined annotation-dependent deletion (CADD) score, compared with high-VAF embryonic variants or postnatal variants6. This observation suggests that these variants have a negative effect on organismal viability. Paradoxically, the low-VAF embryonic variants have a modestly positive dN/dS ratio, suggesting that despite their presumed deleteriousness at the level of the organism, they are subjected to positive selection in the context of embryonic development when present at low-level mosaic states, although limited numbers of donors and the novelty of this bioinformatics approach mean that this ratio must be interpreted with caution6 (Fig. 3). The fact that ‘deleterious’ variants, or variants that are overall harmful to human health, may confer a fitness advantage in some embryonic contexts explains why these cells are not always eliminated and contribute to multiple tissues of the resulting organism.
Fig. 3 |. The features of mosaic variants vary from early to late embryogenesis.
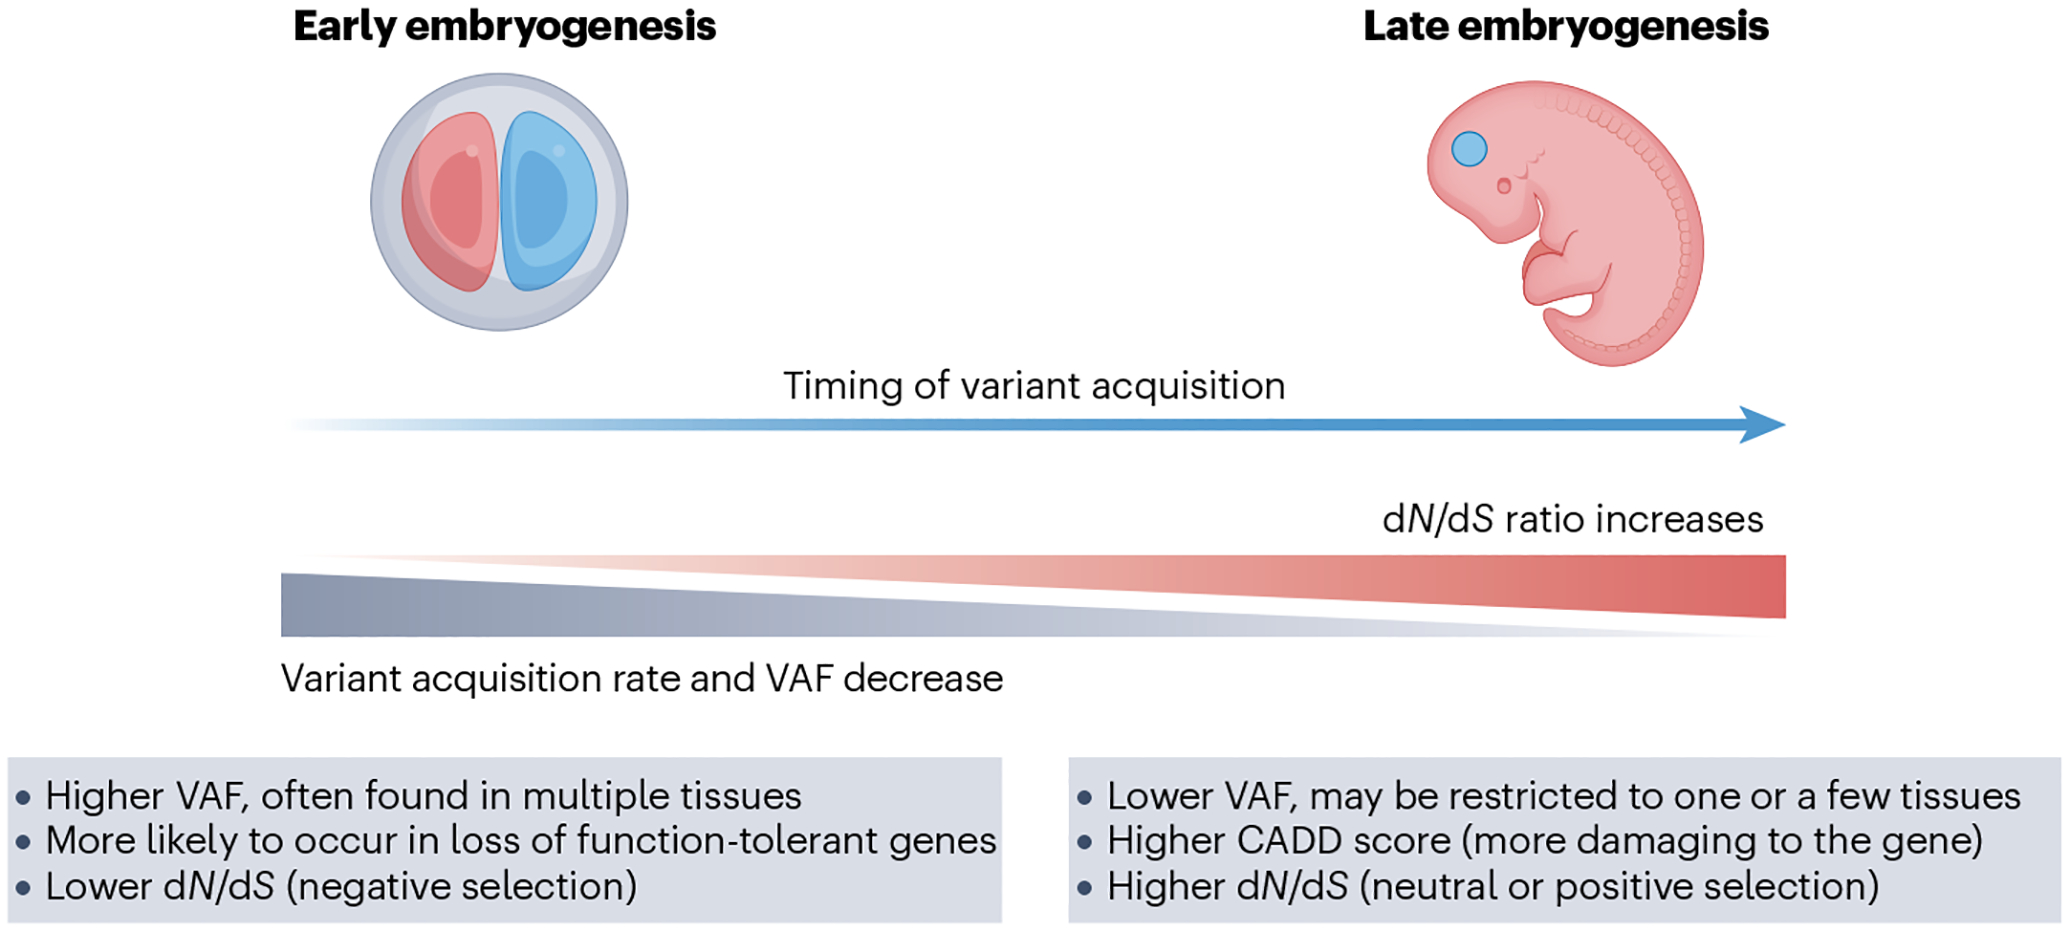
The first few cell divisions in the early embryo are the most mutagenic. Mosaic variants acquired during early embryogenesis are generally present at higher variant allele frequencies (VAFs) in the resulting individual. They are subjected to stronger negative selective pressures, with a lower ratio of non-synonymous to synonymous variants (dN/dS ratio), indicating negative selection against deleterious variants. By contrast, mosaic variants acquired later in embryogenesis are generally found at lower VAFs and are confined to a smaller number of tissues. Because of this, they may have a higher combined annotation-dependent deletion (CADD) score, suggesting a higher degree of damage to the gene, and thus deleteriousness at the population level. However, in aggregate, they exhibit a higher dN/dS ratio, suggesting positive selection, because genes that are deleterious at the population level or harmful if they occur in a very high proportion of embryonic cells may be favourable in certain tissues or embryonic contexts when present in a mosaic state at low VAF.
Contribution to the genetic disease burden
Embryonic mosaicism for non-disease-causing variants is ubiquitous due to intrinsic variant acquisition rates throughout the many cell divisions required to generate an organism. However, a relatively large number of disease-causing variants are also acquired post-zygotically in the proband or inherited from an apparently unaffected parent with low-level mosaicism. The recent availability of genome sequencing and exome sequencing in clinical settings has facilitated the discovery of low-VAF variants, and mosaicism is increasingly recognized as a contributor to the genetic disease burden. Estimates of mosaicism rates vary across studies depending on the sequencing sensitivity, cohort size and inclusion criteria. Most studies of parent–proband trio cohorts suggest that 3.0–6.5% of variants previously characterized as de novo heterozygous variants, or variants present in every cell of the proband, are instead post-zygotic mosaic variants17–19. Additionally, in 0.5–3.0% of trios in a cohort, the disease-causing variant can be identified at low levels in the blood or other somatic tissues of one parent18–22,31,42, implying that the parent exhibits gonosomal mosaicism.
Large-scale cohort studies to quantify mosaicism rates across multiple genetic diseases have only recently become feasible17–22; however, case reports and studies within specific diseases or related groups of diseases present a diverse landscape of the contribution of mosaic variants to genetic disorders (Table 1).
Table 1 |.
Mosaic genetic disorders
| Disorder | Gene | Cases (n) | Tissue bias | Phenotypic effect | Refs. |
|---|---|---|---|---|---|
| Non-obligate mosaics | |||||
| Alport syndrome | COL4A5 | 6 | No | Milder, delayed renal failure, mild deafness | 105 |
| ASXL3-related syndrome | ASXL3 | 3 (2 parents with gonadal mosaicism, one proband) | Unknown | Unknown | 106 |
| Beckwith–Wiedemann syndrome | 11p15 | 95 (ref. 107), 20 twin pairs108, 5 twin pairs109 | Unknown | Mosaics more likely to have lateralized overgrowth; monozygotic twins may have discordant phenotype; mosaicism attenuates clinical severity score | 107–109 |
| Chromosome 15q11.2-q13.1 deletion syndrome | 15q11.2-q13.1 | 1 | Enriched in tumour | Milder autism phenotype | 110 |
| Collagen VI-related dystrophies and myopathies | COL6A | 4 | Higher in fibroblasts than blood | Symptoms scale with VAF | 61 |
| Cornelia de Lange syndrome | NIBPL, SMC1A, SMC3 | 15 (10 in ref. 59, 5 in ref. 111) | Possible selection against NIBPL pathogenic variants in peripheral blood | None | 59,111 |
| Dravet syndrome | SCN1A | 2 parents45, 20 parents46, 26 parents47, 2 patients48 | Unknown | Higher VAF more likely to have epilepsy | 45–48 |
| Epilepsy | CDKL5, GABRA1, GABRG2, GRIN2B, MECP2, PCDH19, SCN1A, SCN2A, SCN8A, STXBP1 | 31 probands112, 53 parents112, 5 parents98 | Unknown | Higher VAF more likely to have epilepsy | 98,112 |
| Epilepsy, female restricted (EFMR) | PCDH19 | 1 | Higher in blood and saliva, lower in epithelial tissues | Mosaic patient apparently unaffected | 113 |
| Freeman–Sheldon syndrome | MYH3 | 1 | Unknown | Mosaic patient apparently unaffected | 114 |
| Hyper IgE syndrome | STAT3 | 1 (ref. 115), 2 (ref. 116) | 1 confined to B cells | Milder phenotype | 115,116 |
| Hypothalamic hamartoma | Sonic hedgehog signalling genes and cilia genes, including PRKACA, GLI3, OFD1, DYNC2I1, DYNC2H1, IFT140 and SMO | 14 (ref. 117), 15 (ref. 118) | Very rarely found in the blood | More severe/syndromic presentation is described when variants are either germline (GLI3 pathogenic variants leading to Pallister–Hall syndrome) or present at detectable blood VAF; note that PRKACA variants have only been described in the mosaic state and may represent obligate mosaicism | 117–119 |
| Li–Fraumeni syndrome | TP53 | 1 (ref. 120), 7 (ref. 53) | Possible negative selection in the blood unless treated with chemotherapy | Phenotype not attenuated | 53,120 |
| Neurofibromatosis | NF1 | 1 (ref. 121), 1 (ref. 122), frequency of segmental NF1 estimated at 0.0014–0.0027%123 | Variant most often identified in affected lesions, only rarely in leukocytes and unaffected fibroblasts, may be confined to a specific body region (segmental); gonadal mosaicism is rare but possible. | Rate of complications much lower in segmental NF1 than generalized NF1; generalized mosaics clinically resemble non-mosaic individuals | 121–123, Reviewed in ref. 124 |
| NF2-related schwannomatosis | NF2 | 4 (ref. 125), 232 cases (22% of cohort)126 | Detectable in blood in addition to tumour more often than mosaic NF1 (ref. 126) | Ref. 125 suggests milder phenotype in NF2 mosaics | 125,126 |
| Primary immunodeficiency | NLRP3, BTK, ELANE, IL2RG, NOD2, FAS, NRAS, PIK3CD, STAT3, WAS, TLR8 | 30 (ref. 44) 5 (ref. 49), 1 (ref. 127) | None detected | Low-intermediate VAFs were associated with milder presentation, except for novel variants, which were severe regardless of VAF | 44,49,127 |
| Rubinstein–Taybi syndrome | CREBBP | 1 | None detected | Mildly affected | 128 |
| Sotos syndrome | NSD1 | 1 | Unknown | Mosaic was apparently unaffected | 129 |
| β-Propeller protein-associated neurodegeneration | WDR45 | 1 proband130, 1 parent131 | Unknown | Likely attenuates early lethality in males | 130,131 |
| Rett syndrome | MECP2 | 2 | Unknown | Attenuates severity, as non-mosaic hemizygous variant is lethal in males by age 2 years | 132 |
| Tatton–Brown–Rahman syndrome | DNMT3A | 2 | Blood-biased expansion to 100%, low levels in epithelial tissues | Mild mosaic paternal phenotype | 51,133 |
| Thanatophoric dysplasia | FGFR3 | 1 (ref. 134), 1 (ref. 135) | Unknown134; VAF 43% in blood, 11% in hair root135 | Atypical presentation of FGFR3-related disorder | 134,135 |
| Tuberous sclerosis | TSC1, TSC2 | 95 (ref. 50), 10–15% of cases overall, 26 (ref. 136) | Mosaicism more common with TSC2 variants than TSC1, higher VAF with TSC1, absent in blood in 18% of cases | Most clinical features attenuated or absent in mosaics, severity correlated with VAF | 50,136 |
| Obligate mosaics a | |||||
| CLOVES | PIK3CA | 19 | Unknown | Unknown | 137 |
| Encephalocraniocutaneous lipomatosis | FGFR1 | 3 | Highest in fibroblasts | Unknown | 138 |
| Focal cortical dysplasia | MTOR | 39 | Higher in brain, occasionally detectable at low VAF in blood | Some correlation between higher VAF at seizure onset centre than surrounding zone | 139 |
| Focal epilepsy | Chromosome 1qgain | 7 (ref. 140), 6 (ref. 141) | Unknown | Unknown | 140,141 |
| Maffucci syndrome | IDH1 | 54 | Unknown | Unknown | 142 |
| McCune–Albright syndrome | GNAS1 | 4 | Unknown | N/A | 77 |
| Pacak–Zhuang syndrome | EPAS1 | 9 | High in tumours, low elsewhere | N/A | 143,144 |
| Pallister–Killian syndrome | Tetrasomy 12p | 15 | Rare detection of tetrasomy in lymphocytes; tetrasomy readily detected in fibroblasts | Potentially correlated with severity, as stillborn case had 100% VAF in fibroblasts and 60% in buccal mucosa | 54 |
| Patterned spiny hyperkeratosis | GJB2 | 1 | Limited to involved skin | N/A | 79 |
| Proteus syndrome | AKT1 | 26 | Mostly absent from blood | No correlation between proportion and phenotype | 60 |
| Schimmelpenning syndrome | HRAS, KRAS | 2 | Mosaic variant is absent in lymphocytes and non-lesional skin | Presence of variant in locations beyond the skin lesions led to phenotype of Schimmelpenning rather than more limited nevus sebaceous | 145 |
| Sturge–Weber syndrome | GNAQ | 35 | Identified in affected brain and skin | N/A | 76 |
| VEXAS syndrome | UBA1 | 25 | Variant identified in myeloid lineage, but not in mature lymphocytes | Patients with VEXAS all had high VAF (>71%) | 56 |
Examples of syndromes in which mosaicism has been reported. N/A, not available; VAF, variant allele frequency.
Obligate mosaics are cases in which the genetic variant is only seen in the context of mosaicism. This indicates the syndrome would be lethal otherwise.
Cell competition in mosaicism
If a variant is acquired early in embryogenesis before cellular fate specification and has no effect on relative cell fitness, it would be expected to distribute equally throughout all tissues of the resulting organism. However, some variants exhibit biased tissue distribution (Table 1), suggesting selective advantage or disadvantage within certain tissues when in competition with other clones. This landscape implies distinct ‘fitness’ of certain clones in different contexts and likely varies by variant, tissue, age and environment. In this section, we discuss the evidence that mosaicism can vary across time and tissues within the same individual, the molecular mechanisms of mosaic cell competition and competitive genetic rescue of deleterious variants.
Mosaicism dynamics across time and tissues
Although embryonically acquired mosaic variants often seem to be equally distributed across tissues, some are present at different proportions (measured by VAFs) within the same individual depending on the tissue that is sampled (Table 1). Some differences, such as complete absence from a particular cell lineage, may reflect the timing of variant acquisition, suggesting that the variant was acquired after the specification of that lineage38. Some differences may also reflect stochastic asymmetric contribution from cells of the very early emb ryo1,2,4,5,16,36–38, in which bottlenecks occur by chance, and only a small number of progenitor cells contribute to a particular lineage. However, tissue-specific effects, changes in VAF over time within the same individual or consistent exclusion from a particular cell type across multiple individuals may also occur due to the intrinsic properties of specific variants, as discussed below.
The effect of a variant may be tissue-specific, even if the variant cells are present in multiple tissues. For example, in a cohort of patients with autism spectrum disorder, which included several cases with mosaic variants, affected genes were most highly expressed in the amygdala, explaining why the patients’ main clinical manifestation was autism spectrum disorder despite the presence of variant cells in other tissues43. Conversely, mosaicism is common in primary immunodeficiency disorders, in which the variant affects the function of haematopoietic cells. Although the manifestations, such as auto-inflammation, may seem to affect non-haematopoietic tissues where the variant cells are also found, the clinical phenotype is driven by the aberrant immune cells attacking the solid tissues44. Additionally, for some disorders, there is a correlation between the proportion of cells bearing a variant in a tissue (inferred via VAF) and phenotype severity, which is particularly apparent in studies with higher patient numbers, such as epilepsy and primary immunodeficiency cohorts44–50 (Table 1).
Investigating the tissue-specific effects of embryonically acquired mosaic variants requires sampling numerous tissues from the same individual and may require serial sampling over time, which is one reason why studies investigating these effects are rare and often limited to easily accessible tissues. Changes in clone contributions over time have been typically monitored in peripheral blood, as it provides large amounts of high-quality DNA. However, it is also a highly dynamic tissue with ample opportunities for cell competition. Embryonic variants with a competitive advantage in blood, such as DNMT3A variants51, which cause a syndrome of overgrowth, obesity and intellectual disability, expand specifically in the blood, but not in fibroblasts. In one mosaic individual, they reached a variant proportion of nearly 100% in the blood while remaining much lower in other tissues51. They thus may appear fully heterozygous by most sequencing strategies. In utero acquisition of variants in cancer-associated genes such as DNMT3A and TP53 can result not just in expansion but in outright malignancy52,53. Conversely, variants with a disadvantage in blood may be outcompeted and missed if only blood is sequenced, despite clinically relevant proportions of variant cells in other tissues, as can occur in Pallister–Killian syndrome54. Some variants are depleted in specific blood lineages due to impaired differentiation, despite their presence in progenitor cells55,56. The haematopoietic system may be particularly prone to dynamic selection due to continued cell proliferation throughout life, which facilitates cell competition. Importantly, when compared with more than 40 other tissues, blood had the lowest yield for mosaicism detection6, possibly due to its dynamic nature.
Examples of competitive selection also exist outside the haematopoietic system. In mouse models of Duchenne muscular dystrophy, CRISPR–Cas9 editing produced mice that were mosaics for the corrected Dmd gene, and the proportion of corrected skeletal muscle cells increased over time, ultimately abrogating the muscle phenotype57. Similar findings have been reported in humans with mosaic DMD variants58, attributed to replacement of variant cells by wild-type cells over time. However, correction is not observed in the heart, which lacks a stem cell-driven regenerative mechanism58. Other mosaic disorders that show differential tissue distribution, such as Cornelia de Lange syndrome59, Proteus syndrome60 and the collagen VI-related dystrophies and myopathies61 (Table 1), have unclear mechanisms regulating cellular fate decisions. Mechanisms of cell competition in the context of these specific variants and many others remain to be explored.
Molecular mechanisms underlying cell competition
Molecular mechanisms explaining the persistence or elimination of mosaic clones have mostly been investigated in model organisms under the conceptual umbrella of cell competition. Apoptosis is one pathway that has been repeatedly implicated (Fig. 4a). Drosophila melanogaster with mosaic patches of cells carrying ‘minute’ mutations, which synthesize lower quantities of ribosomal proteins, revealed that mutant cells were outcompeted by wild-type cells not simply due to differential growth rates but because mutants undergo apoptosis when in contact with wild-type cells, and then the wild-type cells engulf them62. Mouse models and mammalian cell culture systems have revealed similar phenomena. In mosaic mouse embryos, epiblast cells with low Myc expression undergo apoptosis and are engulfed by neighbouring cells with higher Myc expression63. Similarly, MYC-low cells are outcompeted in both the developing and mature mouse epidermis64.
Fig. 4 |. Cell competition in mosaicism occurs through separate but interrelated mechanisms.
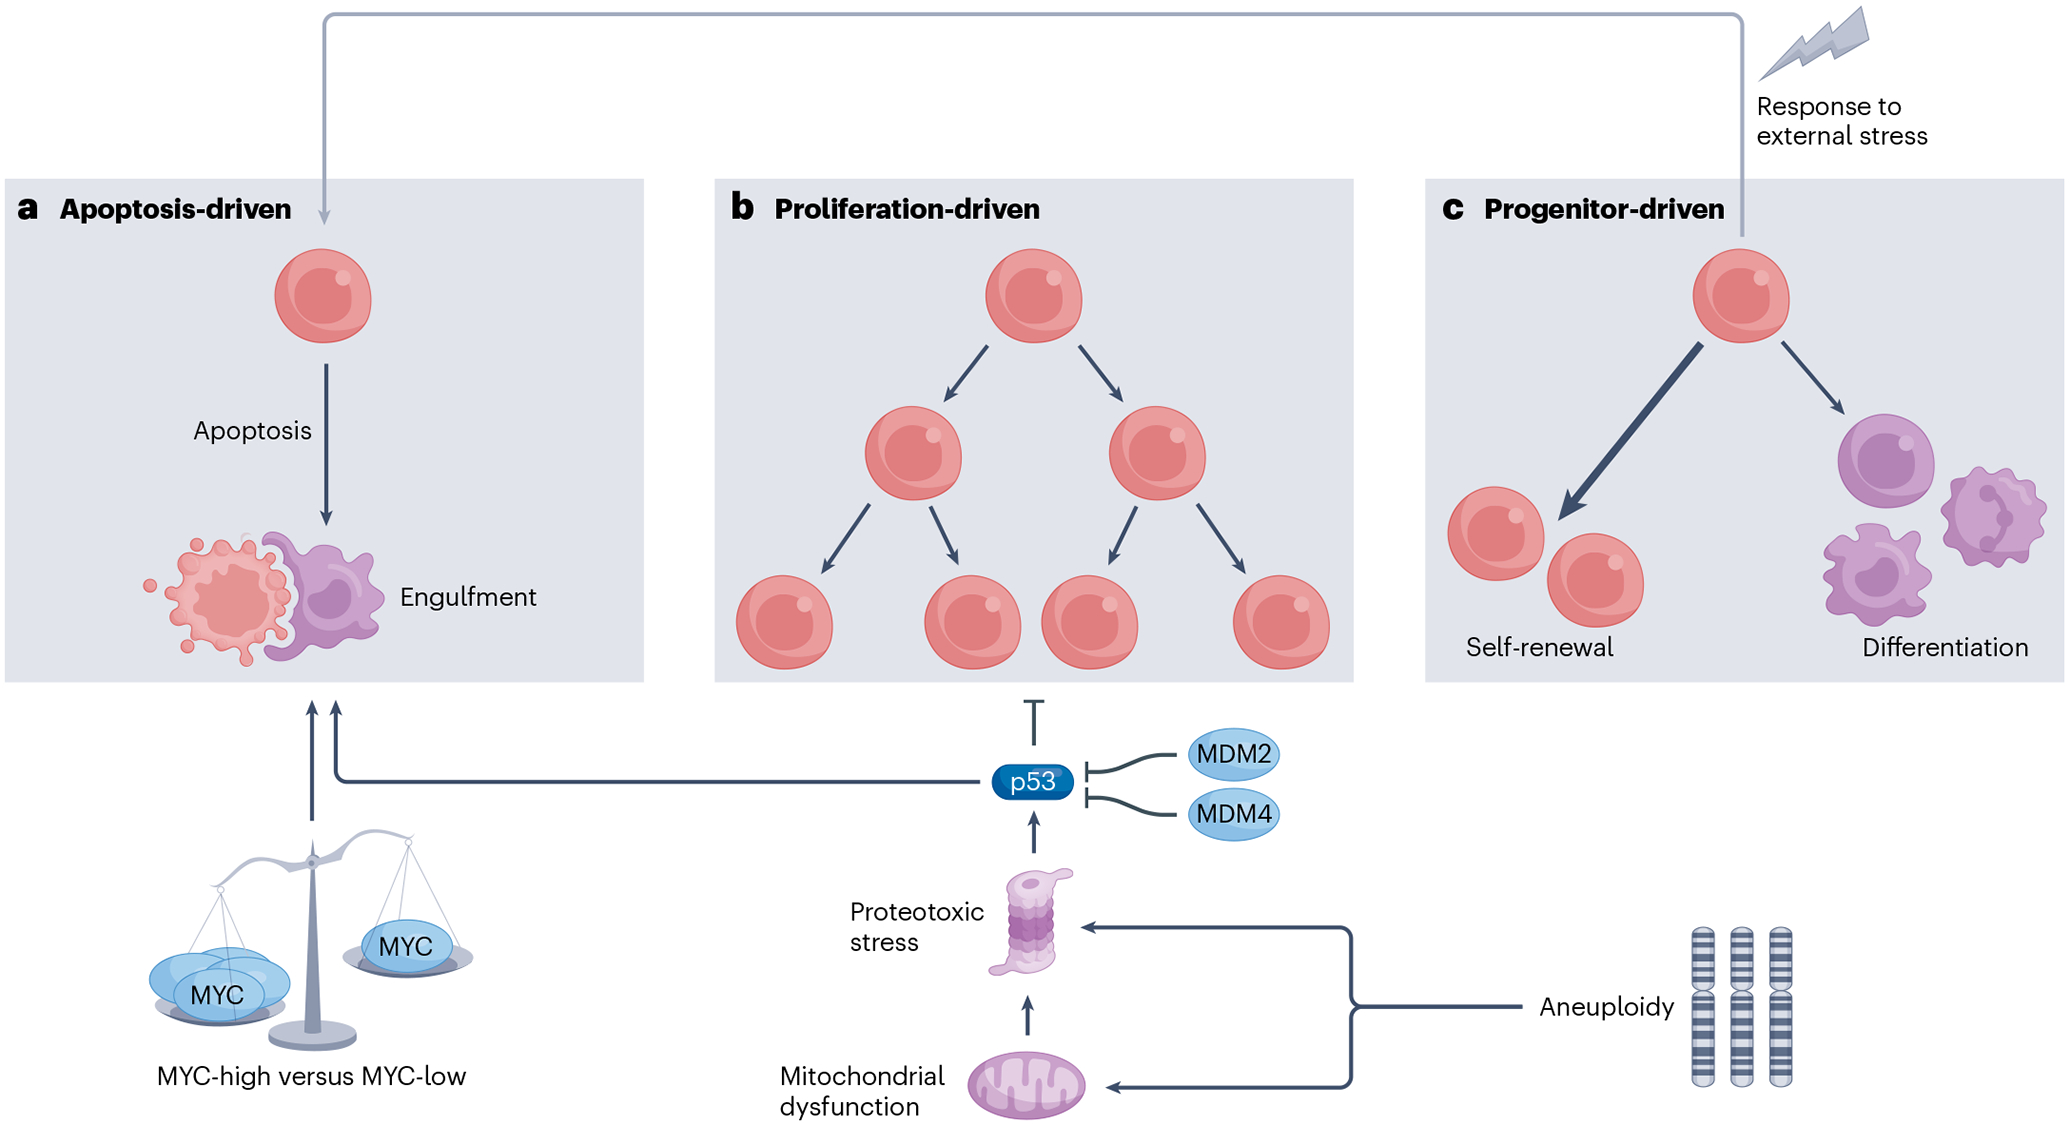
Wild-type and variant cells in a mosaic individual compete via multiple pathways that converge on three main processes. a, Apoptosis-driven: aneuploid cells, cells with mitochondrial defects, cells with higher levels of proteotoxic stress, cells with higher levels of p53 or cells with low levels of MYC are more likely to undergo apoptosis when competed against their wild-type counterparts. Following initiation of apoptosis, ‘winner’ cells may engulf ‘loser’ cells. b, Proliferation-driven: cells with higher levels of p53 or lower levels of the p53 negative regulators MDM2 and MDM4 outcompete wild-type cells by increasing their proliferation rates. c, Progenitor-driven: variant progenitor cells may exhibit a self-renewal advantage, leading to their enrichment in the stem cell pool. They may exhibit decreased differentiation potential, or a bias towards certain cell types. They may also have a decreased tendency to undergo apoptosis when subjected to environmental stresses.
Another mechanism of cell competition involves regulators of cell proliferation (Fig. 4b). For example, cells with mildly increased levels of p53 due to haploinsufficiency of the p53 negative regulators Mdm2 and Mdm4 are depleted from mosaic mouse embryos and are strikingly under-represented in adult mouse tissues with high turnover rates, such as the bone marrow65. This observation indicates that mutant cells can simply be outcompeted by cells with higher proliferation rates.
Mitochondrial dysfunction has also been shown to have a role in embryonic cell competition. Cells with mitochondrial mutations are purged from the early mouse embryo and embryonic stem cell co-culture systems66. It is possible that mitochondrial dysfunction also plays a role in the elimination of aneuploid cells or other forms of cell competition via apoptosis66. Finally, stem and progenitor dynamics may play a role in the outgrowth or elimination of a mosaic clone (Fig. 4c) through enhanced stem cell self-renewal67 or increased ability to tolerate environmental stressors68.
Together, these mechanisms provide a framework for understanding how mutant and wild-type cells in a mosaic organism may directly eliminate or outcompete one another. It remains to be investigated which mechanisms are most important for specific mosaic mutations and how different environmental contexts may alter the fitness landscape to favour mutant cells in some cases but not others.
Revertant mosaicism
Revertant mosaicism (also known as reversion or somatic genetic rescue) is a type of mosaicism in which all cells of the embryo originally carry a deleterious variant, and a subsequent mutational event either directly reverts the variant allele back to the wild-type form or compensates indirectly, such as by conferring loss of function on a gain-of-function variant. If the reversion happens early enough in embryogenesis, it may be detectable throughout the organism and is subject to the same forces of competition as any other mosaic variant. This phenomenon seems to be particularly common (or at least most commonly detected) in the haematopoietic system (reviewed elsewhere69). For example, in dyskeratosis congenita, a syndrome caused by variants in the genes involved in telomere protection and maintenance, independent mosaic reversion events that rescued telomere protection and the haematopoietic phenotype were described in six individuals70. These events were limited to the bone marrow and not detected in other tissues, suggesting a tissue-specific advantage for the reverted allele, despite the multi-system nature of the disease.
Reversion that occurs in the haematopoietic system can also sometimes rescue extra-haematologic symptoms of a disorder. For example, an asymptomatic man who fathered two children with GATA2 deficiency was found to have a constitutional GATA2 variant detectable in his sperm and skin fibroblasts. GATA2 deficiency normally causes severe haematologic symptoms, but this man exhibited a reversion of the GATA2 variant exclusively in his haematopoietic system71; the circulating normal haematopoietic cells also seemed to abate other phenotypes such that he exhibited no extra-haematologic symptoms.
Reversion also occurs in non-haematopoietic contexts. For example, a patient with attenuated symptoms of Hutchinson–Gilford progeria syndrome had two different variants in LMNA: one that caused the severe version of the syndrome and a mosaic reversion variant for a less severe form of the syndrome72. In vitro fibroblast culture revealed that fibroblasts with the less severe variant had a growth advantage over those with the more severe variant, and Sanger sequencing of the patient’s fibroblasts showed that only the milder variant was detectable. However, both variants were detected in the blood, potentially because LMNA is expressed at very low levels in blood cells, and the two populations are therefore not in competition72.
Another context in which revertant mosaicism is common is MIRAGE syndrome, a growth, endocrine and immune disorder that results from SAMD9 gain-of-function variants. Cells with lower SAMD9 expression have such a significant growth advantage that, in numerous patients, monosomy 7 or SAMD9 loss-of-function variants arise and expand73–75. However, although acquisition of mosaic monosomy 7 seems to be necessary for survival past infancy in patients with MIRAGE syndrome, it also predisposes them to myelodysplastic syndrome74,75, highlighting that mosaic phenotypic rescue may be a double-edged sword.
These cases in which genetic mosaicism contributes to phenotypic reversion or disease amelioration are of interest to understand mechanisms of cell competition, but, even more importantly, give clinical insight into possible gene therapy strategies. For example, abatement of Duchenne muscular dystrophy in patients presenting rare mosaicism suggests that correcting even a small proportion of cells could have an outsized impact if the corrected cells can overtake a tissue57.
Functional consequences
The effects of embryonic mosaicism span the full spectrum, from early lethality to complete neutrality, to rescue of a deleterious germline phenotype. In this section, we discuss the direct effects of different types of mosaicism on embryo viability, the importance of detecting mosaicism in the clinical setting and the potential for germline transmission.
Embryo viability
Numerous types of mosaic variants can affect embryo viability. For example, the effects of aneuploidy have been well studied (Box 1). Some constitutional genetic variants are so catastrophic for the organism that they are only observed in the context of a mosaic embryo with some wild-type cells. Such obligate mosaicism commonly involves activating variants in key growth signalling pathways, which lead to such severe growth dysregulation that the organism can only survive when they are confined to smaller areas of the body. Examples include Sturge–Weber syndrome (GNAQ variants)76, Proteus syndrome (AKT1 variants)60, McCune–Albright syndrome (GNAS1 variants)77, focal cortical dysplasia type II (MTOR variants)78 and patterned spiny hyperkeratosis (GJB2 variants)79, which often exhibit patterned cutaneous findings and/or stereotypical tumours (Table 1).
In some cases, mosaicism may improve embryo viability. As discussed above, somatic genetic rescue can improve viability and abrogate severe phenotypes, although sometimes with additional adverse effects, such as increased cancer risk74,75.
Clinical implications
The wide range of genetic disease that can be mosaic or that only presents in mosaic form (obligate mosaicism) suggests that mosaicism should always be considered when evaluating a patient with an apparent Mendelian disorder. Mosaicism in either a proband or a parent has profound clinical implications. The presence of mosaicism in parents can increase the recurrence risk of genetic disorders in their children by orders of magnitude80,81 and thus, if better understood, could influence family-planning decisions. Mosaicism in probands can have an impact on the sample-tissue type and approach needed for molecular diagnosis, and can alter the course and severity of diseases, and therefore is of marked interest for anticipating future clinical needs.
Despite the clinical relevance of mosaicism, current clinical pipelines are largely not built to detect it. As discussed above, mosaicism can vary with time and across tissues, as well as throughout the duration of an environmental exposure68. Moreover, automated analysis of Sanger sequencing data can lead to errors in mosaic variant detection13,14,82 (Fig. 5). Although exome sequencing and genome sequencing are increasingly applied in the clinical setting, they are performed at relatively low depth (100–150× and ~30–60×, respectively)83 due to costs, usually missing variants below their limit of detection. For example, standard exome sequencing will only detect variant alleles down to a VAF of around 5%84, which corresponds to mosaicism in about 10% of cells. Targeted, high-depth amplicon sequencing85 or digital droplet PCR86 is required to validate low-VAF variants14, requiring specialized expertise and funding. Because of these limitations, suspected low-VAF variants are mostly pursued in the research setting. Current clinical practice guidelines make little mention of mosaicism, and issues such as affected tissue, tissue availability, variant type and the availability of trio samples or paired affected and unaffected tissue can all influence which detection techniques are most appropriate. Current best practices for variant calling to detect mosaicism in both the clinical and research settings, as well as novel technologies such as single-cell genomics that hold promise for cell type-specific and spatial resolution of mosaicism, are reviewed elsewhere83,87–93.
Fig. 5 |. Differences in VAF across time, tissues and environmental exposures affect clinical detection of mosaicism.
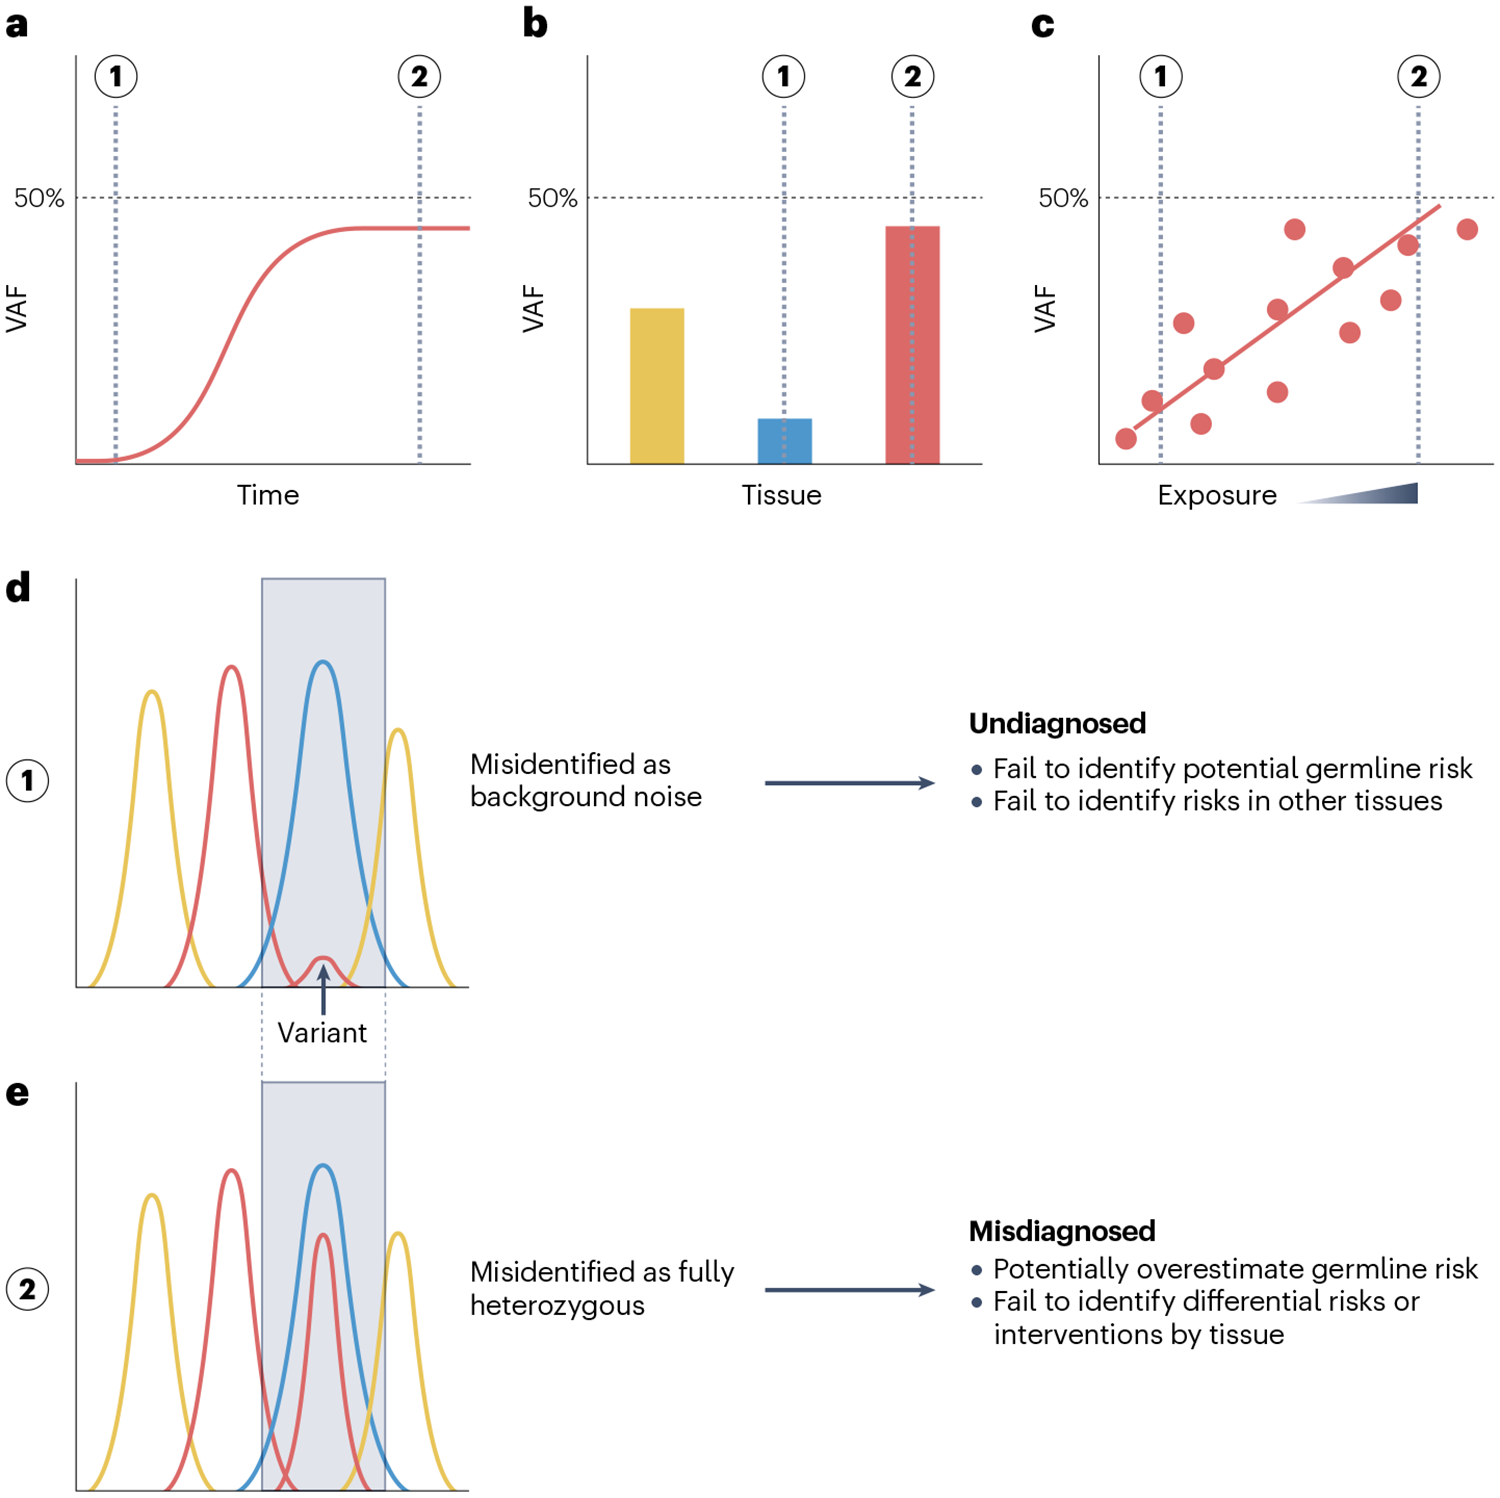
Depending on which sample is collected (1 versus 2), a completely different clinical result may be identified and reported to a patient. a, Variant allele frequency (VAF) in a particular tissue, such as the blood, can vary over time due to selection for or against cells carrying that variant within the sampled tissue. b, VAF can be high in some tissues and low in others within the same individual, so sampling of one particular tissue can obscure the mosaic state. c, VAF can change with increasing exposure to an environmental insult, such as smoking, infection or chemotherapy. d, In sample 1, mosaicism is not detected because the VAF is low and is interpreted as background noise (arrow). e, In sample 2, mosaicism is misdiagnosed as a germline heterozygous variant because the VAF is high and is read as 50%, suggesting that the variant is present in all cells when it is actually mosaic. This scenario could occur if a variant-containing clone dominated the sampled tissue (even if it was rare in other tissues).
Transmission of genetic disorders in the context of mosaicism
The potential for germline transmission is a key consequence of embryonic mosaicism. If an embryonic mosaic variant is acquired before specification of the primordial germ cells (around day 12 after fertilization94), the mosaicism may be gonosomal or gonadal (Fig. 1). In this case, the individual may not be phenotypically affected by the variant (depending on mosaicism in other tissues) but still have the potential to pass it to his or her offspring. Contribution to the germline is likely underestimated and yet highly relevant to families.
Importantly, the likelihood of contribution to germ cells is influenced by the sex of the parent. Male gametes undergo many mitoses throughout life. Therefore, the overall variant burden in the male germline increases with age, but the contribution of a particular variant to the pool is generally low because it most likely occurred during a downstream mitosis event rather than during the early seeding of the germline80. The situation is reversed in the female germline, in which clonal expansion occurs from a pool of progenitors that arrest early in development80. Consequently, low-VAF gonadal variants are less common in females. However, variants that occurred during early development are more likely to be shared by many germ cells80,81. Probabilistic modelling has demonstrated that recurrence risk is therefore higher if the variant came from the mother80.
Nevertheless, parental risk assessment is also influenced by the age of the parent when a variant is transmitted. If a mother transmits a variant at any age, recurrence risk in future offspring is approximately doubled80. However, if a young father transmits a variant, the risk of recurrence increases more than 50-fold because it indicates that the mutational event likely occurred during early specification of the germline rather than a late, downstream mitosis event80. In support of this model for men, variants that are found in both paternal blood and sperm exhibit higher VAFs95, which is suggestive of an early mutational event and a higher likelihood of transmission. It is therefore important to consider that the father might exhibit gonosomal mosaicism rather than low-VAF gonadal mosaicism.
More recently, de novo variants shared by siblings were identified in a large cohort of families and were used to build a risk calculator that takes into account parent of origin, parental age, parental mosaicism and presence of the variant in other siblings81. This calculator gives a risk of recurrence that ranges from 0.011% to 28.5%, highlighting how essential it is to look for parental mosaicism when counselling parents about recurrence risk81. Monozygotic twins are a special case — they can be discordant for any variant acquired after the twinning occurred, or they can exhibit the same variant at different VAFs across tissues96. Indeed, recurrence risk was recently quantified in a large autism cohort, and 2.5% of variants from the offspring were detectable in the paternal sperm97. Those with the highest sperm VAF were also detectable in the blood of the fathers and had the highest recurrence risk97. Similarly, high percentages of parents with affected children in several genetic epilepsy cohorts were found to be mosaic, and many of the parents with higher VAFs were themselves affected by epilepsy47,98.
An additional class of mosaic variants with potential for germline transmission are those that exhibit the paternal age effect. These variants confer a selective advantage to spermatogonial stem cells, and consequently increase in proportion in the male germline over time. Some examples include Apert syndrome (FGFR2 variants)99, achondroplasia (FGFR3 variants)100, Noonan syndrome (PTPN11 variants)101, multiple endocrine neoplasia type 2B (RET variants)102 and other components of the RAS–MAPK signalling pathway103. Seminiferous tubules exhibit mosaic clusters of spermatogonia with growth advantages that carry the causative variants of these syndromes104, and these distribution patterns are best explained by selection models rather than hot spot mutational event models, suggesting that they are indeed under positive selection rather than randomly occurring100,102.
Conclusions and future directions
Mosaicism that arises in the early embryo has the potential to affect many tissues in high proportions and can be transmitted to the next generation. However, unlike constitutional variants, a mixture of wild-type and variant cells can lead to competition and dynamic shifts in proportions over time. The very early embryo seems uniquely vulnerable to variant acquisition, particularly pre gastrulation and during specification of the neuroectoderm, meaning that embryonically established mosaicism likely contributes substantially to human genetic variation.
The tools to identify mosaic variants in patients are evolving rapidly, as the clinical relevance of mosaic conditions such as clonal haematopoiesis becomes clear. Re-evaluation of numerous sets of exome sequencing and genome sequencing trios using informatics pipelines tailored to detect mosaicism has revealed the prevalence of embryonic mosaicism across many different disorders (Table 1). Novel approaches for variant calling in RNA-seq data6 are also creating new opportunities to observe mosaicism. Single-cell genomics approaches allow for genotyping of individually sequenced cells, with the potential to overlay patterns of genetic mosaicism on single-cell RNA-seq or ATAC-seq datasets91. Transitioning these tools from research to the clinical setting will help provide more realistic risk assessments for mosaic parents and their children and will reveal new examples of mosaicism.
Finally, there are many questions about the dynamics and molecular mechanisms of mosaic clone outgrowth and elimination that are difficult to answer in humans. Tissues such as peripheral blood, skin and sperm that are easily accessible are also those in which most questions about human embryonic mosaicism have been addressed. Sampling the brain, the heart or even the female germline in living humans is rarely practical or ethical; however, comparisons across many different tissue types are essential for investigating the lineage fate decisions of cells with embryonically acquired variants. Biobanks and repositories that can store longitudinal samples across multiple tissue types will play an essential role in studies of embryonic mosaicism. Additionally, the field should leverage cell culture and animal models to systematically evaluate the dynamics of specific mosaic variants (Box 2). In addition to understanding the cell fate decisions that lead to differential tissue distribution of mosaic variants, model systems provide a unique opportunity to explore the tissue-specific role of individual genes, as wild-type and mutant cells have coexisted in the same organism under the same environmental conditions. Taking a multifaceted approach will further our understanding of the origins and impact of genetic variants acquired in early embryogenesis, which will be essential for elucidating the genetic basis of development and disease.
Box 2. Modelling mosaicism.
Mosaicism that occurs in the early embryo presents many challenges to systematic studies. Numerous systems exist in both fruitflies and mice for lineage-tracing studies that rely on random induction of different fluorescent reporters so that neighbouring cells can be distinguished from one another, and their progeny can be tracked over time163–166. However, studies investigating embryonic mosaicism require not just labelling but embryonic induction of a specific mutation in tandem with a marker that can be traced by immunofluorescence or cost-effective sequencing (see the table).
Early studies attempting to address some of these questions relied on chimeras rather than true mosaics, in which cells from two different organisms are mixed rather than inducing a mutation in a subset of cells within a single organism167,168. Similarly, mouse embryonic stem cells bearing a mutation and a reporter can be injected into blastocysts and traced throughout the resulting organism169,170.
Inducing a mutation along with expression of a reporter gene using the Cre–loxP system offers new opportunities to trace the fate of specific variant cells. A mouse with loxP sites flanking a gene of interest and a reporter, in combination with a drug-inducible Cre, allows induction of mosaicism in the mouse embryo when the drug, such as doxycycline or tamoxifen, is administered to the pregnant dam65. Low doses of the drug generate mosaic embryos rather than knockout mice. However, mosaicism can only be induced with these strategies after formation of the placenta around embryonic day 5.5; before this time point, the drug will not reach the embryos. Studies that depend on an inducible Cre can be fraught with leaky Cre expression or low-level induction, both of which can complicate interpretation of the dynamics of mosaicism over time. One study avoided this issue by microinjecting cre mRNA into one cell of the 2-cell stage mouse embryo to generate mosaics; this transient form of Cre could not leak after the injection171.
Finally, gene editing strategies can be leveraged to generate mosaic embryos. Many gene therapy strategies, such as transplacental lipid nanoparticle delivery172 and intrauterine adeno-associated virus delivery173, lead to incomplete editing. Although this can be problematic for their intended gene therapy purposes, it is ideal if the goal is to generate mosaic animals. Recent studies have used low-dose adeno-associated virus administration to provide single guide RNA libraries for CRISPR–Cas9-mediated knockout to specific tissues in adult mice, such as the liver174. These in vivo CRISPR screens can determine which genes promote or inhibit growth under normal and pathological conditions174. Similar screens could be conducted in embryos at different developmental stages.
| Method of generating mosaics | Advantages | Disadvantages |
|---|---|---|
| Embryo aggregation | Avoids genetic crosses No potential for leaky expression or loss of transgene over time |
Difficult to control resulting cell ratios Performed after some degree of fate specification has occurred Chimerism, not mosaicism Requires embryo manipulation |
| Stem cell injection into blastocysts | Avoids genetic crosses Customization of embryonic stem cells and markers |
Difficult to control resulting ratios Embryonic stem cells may acquire additional unknown variants or properties in culture |
| Inducible Cre–loxP | No embryo manipulation No specialized equipment Dose titration can modulate the percentage of mosaicism Can be tissue-specific |
Toxicity of inducing agent (such as tamoxifen in pregnant mice) Difficult to induce in early embryos (pre-placenta) Cre leakage over time in the absence of inducing agent Genetic crosses needed |
| Injection of Cre mRNA | Requires embryo manipulation Mosaicism is induced extremely early in development, before fate specification No Cre leakage |
Requires specialized skills and equipment Cannot modulate levels of mosaicism |
| Nanoparticle delivery | Dose titration can modulate the percentage of mosaicism Can deliver transient cargo, such as RNA, to prevent leakage over time |
May be difficult to control what tissues are affected Difficult to deliver to early embryos |
| Gene delivery via virus | Dose titration can modulate the percentage of mosaicism Can be tissue-specific Fluorescent label can be delivered with genetic cargo |
Viral toxicity and off-target effects Tissue tropism may be undesirable |
Acknowledgements
The authors acknowledge funding from the Eunice Kennedy Shriver National Institute of Child Health and Human Development (NICHD) F30HD111129 (S.M.W.), the Robert and Janice McNair Foundation M.D./Ph.D. Scholars programme (S.M.W.) and Baylor Research Advocates for Student Scientists (S.M.W.). The Goodell laboratory is supported by CA183252, CA237291, DK092883, AG036695 and CA265748. J.E.P is supported by a McGregor Foundation grant.
Glossary
- Amplicon sequencing
Extremely deep sequencing of a short PCR product (amplicon) that lowers the limit of detection for variants in the specific region of interest
- Aneuploidy
A number of chromosomes that is either greater than or lower than a complete diploid set (for example, in humans, a number of chromosomes that does not equal 46)
- Clonal haematopoiesis
A condition in which a haematopoietic stem cell acquires a variant that confers a selective advantage, leading to the outgrowth of the variant cell population in the bone marrow and blood over time. Clonal haematopoiesis is associated with an increased risk of various adverse health outcomes, including cancer, cardiovascular disease and all-cause mortality
- de novo
A term to denote a variant that is not inherited from a parent but, instead, appears spontaneously in the proband (the patient or individual under study)
- Digital droplet PCR
An alternative to quantitative PCR that provides absolute rather than relative quantification of a DNA sequence of interest, such as a variant sequence
- dN/dS ratio
The ratio of non-synonymous to synonymous variants in a protein-coding gene. Non-synonymous variants change the amino acid codon and are more likely to be deleterious. This ratio serves as a measure of natural selection, with a ratio >1 indicating positive selection and a ratio <1 indicating negative selection against the cell(s) bearing the variant
- Exome sequencing
A type of next-generation sequencing that focuses on the exons (including exon–intron boundaries), or protein-coding regions, of the genome to achieve higher depth at lower cost
- Gastrulation
The process of embryonic development during which the three germ layers (ectoderm, mesoderm and endoderm) are specified. Each germ layer will later give rise to specific groups of organs
- Genetic variant
The specific genetic sequence that differs from the reference sequence found in the majority of a population
- Genome sequencing
A type of next-generation sequencing that covers both protein-coding and non-coding regions of the genome, including intragenic, regulatory and intronic regions
- Mutant
A pathogenic or benign variant in the context of a non-human animal model or a cell culture system
- Mutational events
The biochemical processes of variant acquisition that alter the DNA sequence
- Mutations
Any permanent alterations in the DNA sequence of an organism
- Obligate mosaicism
A condition in which some cells of an organism carry a variant that is lethal when present in all cells
- Primordial germ cells
A group of stem cells in the embryo that differentiate to form sperm or eggs
- Proband
In genetics, the affected patient who initially presents for evaluation
- Variant allele frequency
(VAF). The percentage of sequencing reads that are composed of the variant sequence. A germline heterozygous variant has a VAF of 50%, whereas a homozygous variant has a VAF of 100%
- Zygote
The first cell of a vertebrate embryo, formed when an egg is fertilized by a sperm
Footnotes
Competing interests
The authors declare no competing interests.
References
- 1.Behjati S et al. Genome sequencing of normal cells reveals developmental lineages and mutational processes. Nature 513, 422–425 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]; This study is one of the first to use colony sequencing from a multicellular organism to reconstruct phylogenies based on shared variants.
- 2.Ju YS et al. Somatic mutations reveal asymmetric cellular dynamics in the early human embryo. Nature 543, 714–718 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.Ye AY et al. A model for postzygotic mosaicisms quantifies the allele fraction drift, mutation rate, and contribution to de novo mutations. Genome Res. 28, 943–951 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 4.Spencer Chapman M et al. Lineage tracing of human development through somatic mutations. Nature 595, 85–90 (2021). [DOI] [PubMed] [Google Scholar]
- 5.Coorens THH et al. Extensive phylogenies of human development inferred from somatic mutations. Nature 597, 387–392 (2021). [DOI] [PubMed] [Google Scholar]
- 6.Rockweiler NB et al. The origins and functional effects of postzygotic mutations throughout the human life span. Science 380, eabn7113 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]; This study demonstrates the potential to use widely available bulk RNA-seq databases for mosaic variant discovery and to reveal insights about embryonic variant acquisition.
- 7.Jaiswal S et al. Age-related clonal hematopoiesis associated with adverse outcomes. N. Engl. J. Med 371, 2488–2498 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]; In this study, the authors provide one of the first demonstrations of the ubiquity of somatic mosaicism in the blood of aged individuals and link it to adverse health outcomes.
- 8.Genovese G et al. Clonal hematopoiesis and blood-cancer risk inferred from blood DNA sequence. N. Engl. J. Med 371, 2477–2487 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 9.Coombs CC et al. Therapy-related clonal hematopoiesis in patients with non-hematologic cancers is common and associated with adverse clinical outcomes. Cell Stem Cell 21, 374–382.e4 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 10.Martincorena I et al. Somatic mutant clones colonize the human esophagus with age. Science 362, 911–917 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 11.Watson CJ et al. The evolutionary dynamics and fitness landscape of clonal hematopoiesis. Science 367, 1449–1454 (2020). [DOI] [PubMed] [Google Scholar]
- 12.Moore L et al. The mutational landscape of human somatic and germline cells. Nature 597, 381–386 (2021). [DOI] [PubMed] [Google Scholar]
- 13.Aluri J & Cooper MA Genetic mosaicism as a cause of inborn errors of immunity. J. Clin. Immunol 41, 718–728 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 14.Campbell IM, Shaw CA, Stankiewicz P & Lupski JR Somatic mosaicism: implications for disease and transmission genetics. Trends Genet. 31, 382–392 (2015). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 15.Martinez-Glez V et al. A six-attribute classification of genetic mosaicism. Genet. Med 22, 1743–1757 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16.Park S et al. Clonal dynamics in early human embryogenesis inferred from somatic mutation. Nature 597, 393–397 (2021). [DOI] [PubMed] [Google Scholar]
- 17.Acuna-Hidalgo R et al. Post-zygotic point mutations are an underrecognized source of de novo genomic variation. Am. J. Hum. Genet 97, 67–74 (2015). [DOI] [PMC free article] [PubMed] [Google Scholar]; This study is one of the earliest to use trio sequencing to demonstrate that a substantial portion of variants presumed to be germline are in fact mosaic.
- 18.Cook CB et al. Somatic mosaicism detected by genome-wide sequencing in 500 parent–child trios with suspected genetic disease: clinical and genetic counseling implications. Cold Spring Harb. Mol. Case Stud 7, a006125 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 19.Wright CF et al. Clinically-relevant postzygotic mosaicism in parents and children with developmental disorders in trio exome sequencing data. Nat. Commun 10, 2985 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 20.Gambin T et al. Low-level parental somatic mosaic SNVs in exomes from a large cohort of trios with diverse suspected Mendelian conditions. Genet. Med 22, 1768–1776 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 21.Domogala DD et al. Detection of low-level parental somatic mosaicism for clinically relevant SNVs and indels identified in a large exome sequencing dataset. Hum. Genomics 15, 72 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 22.Sasani TA et al. Large, three-generation human families reveal post-zygotic mosaicism and variability in germline mutation accumulation. eLife 8, e46922 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 23.Lee H et al. Characterization of early postzygotic somatic mutations through multi-organ analysis. J. Hum. Genet 66, 777–784 (2021). [DOI] [PubMed] [Google Scholar]
- 24.Rodin RE et al. The landscape of somatic mutation in cerebral cortex of autistic and neurotypical individuals revealed by ultra-deep whole-genome sequencing. Nat. Neurosci 24, 176–185 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 25.Gallini S et al. Injury prevents Ras mutant cell expansion in mosaic skin. Nature 619, 167–175 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 26.Thorpe J, Osei-Owusu IA, Avigdor BE, Tupler R & Pevsner J Mosaicism in human health and disease. Annu. Rev. Genet 54, 487–510 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]; In this review, the authors discuss the genetic mechanisms of mosaic variant acquisition and details about various detection techniques.
- 27.van Echten-Arends J et al. Chromosomal mosaicism in human preimplantation embryos: a systematic review. Hum. Reprod. Update 17, 620–627 (2011). [DOI] [PubMed] [Google Scholar]
- 28.Taylor TH et al. The origin, mechanisms, incidence and clinical consequences of chromosomal mosaicism in humans. Hum. Reprod. Update 20, 571–581 (2014). [DOI] [PubMed] [Google Scholar]
- 29.Levy B, Hoffmann ER, McCoy RC & Grati FR Chromosomal mosaicism: origins and clinical implications in preimplantation and prenatal diagnosis. Prenat. Diagn 41, 631–641 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 30.Vorsanova SG, Yurov YB & Iourov IY Dynamic nature of somatic chromosomal mosaicism, genetic–environmental interactions and therapeutic opportunities in disease and aging. Mol. Cytogenet 13, 16 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 31.Campbell IM et al. Parental somatic mosaicism is underrecognized and influences recurrence risk of genomic disorders. Am. J. Hum. Genet 95, 173–182 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 32.Hatton IA et al. The human cell count and size distribution. Proc. Natl Acad. Sci. USA 120, e2303077120 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 33.Munisha M & Schimenti JC Genome maintenance during embryogenesis. DNA Repair. 106, 103195 (2021). [DOI] [PubMed] [Google Scholar]
- 34.Kermi C, Aze A & Maiorano D Preserving genome integrity during the early embryonic DNA replication cycles. Genes 10, 398 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 35.Bae T et al. Different mutational rates and mechanisms in human cells at pregastrulation and neurogenesis. Science 359, 550–555 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 36.Fasching L et al. Early developmental asymmetries in cell lineage trees in living individuals. Science 371, 1245–1248 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 37.Lee-Six H et al. Population dynamics of normal human blood inferred from somatic mutations. Nature 561, 473–478 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]; This study pioneers the capture–recapture technique to reconstruct phylogenies of human haematopoiesis.
- 38.Bizzotto S et al. Landmarks of human embryonic development inscribed in somatic mutations. Science 371, 1249–1253 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 39.Nam AS et al. Somatic mutations and cell identity linked by genotyping of transcriptomes. Nature 571, 355–360 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 40.Huang AY et al. Parallel RNA and DNA analysis after deep sequencing (PRDD-seq) reveals cell type-specific lineage patterns in human brain. Proc. Natl Acad. Sci. USA 117, 13886–13895 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 41.Kim JH et al. Analysis of low-level somatic mosaicism reveals stage and tissue-specific mutational features in human development. PLoS Genet. 18, e1010404 (2022). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 42.Liu Q et al. Parental somatic mosaicism for CNV deletions—a need for more sensitive and precise detection methods in clinical diagnostics settings. Genomics 112, 2937–2941 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 43.Lim ET et al. Rates, distribution and implications of postzygotic mosaic mutations in autism spectrum disorder. Nat. Neurosci 20, 1217–1224 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 44.Mensa-Vilaro A et al. Unexpected relevant role of gene mosaicism in patients with primary immunodeficiency diseases. J. Allergy Clin. Immunol 143, 359–368 (2019). [DOI] [PubMed] [Google Scholar]; In this study, the authors demonstrate that an unexpectedly large number of families with primary immunodeficiency disorders exhibit mosaicism.
- 45.Depienne C et al. Parental mosaicism can cause recurrent transmission of SCN1A mutations associated with severe myoclonic epilepsy of infancy. Hum. Mutat 27, 389 (2006). [DOI] [PubMed] [Google Scholar]
- 46.Xu X et al. Amplicon resequencing identified parental mosaicism for approximately 10% of “de novo” SCN1A mutations in children with Dravet syndrome. Hum. Mutat 36, 861–872 (2015). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 47.Yang X et al. Genomic mosaicism in paternal sperm and multiple parental tissues in a Dravet syndrome cohort. Sci. Rep 7, 15677 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 48.Nakayama T et al. Somatic mosaic deletions involving SCN1A cause Dravet syndrome. Am. J. Med. Genet. A 176, 657–662 (2018). [DOI] [PubMed] [Google Scholar]
- 49.Aluri J et al. Immunodeficiency and bone marrow failure with mosaic and germline TLR8 gain of function. Blood 137, 2450–2462 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 50.Klonowska K et al. Comprehensive genetic and phenotype analysis of 95 individuals with mosaic tuberous sclerosis complex. Am. J. Hum. Genet 110, 979–988 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 51.Tovy A et al. Tissue-biased expansion of DNMT3A-mutant clones in a mosaic individual is associated with conserved epigenetic erosion. Cell Stem Cell 27, 326–335.e4 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 52.Williams N et al. Life histories of myeloproliferative neoplasms inferred from phylogenies. Nature 602, 162–168 (2022). [DOI] [PubMed] [Google Scholar]
- 53.Castillo D et al. Clonal hematopoiesis and mosaicism revealed by a multi-tissue analysis of constitutional TP53 status. Cancer Epidemiol. Biomark. Prev 31, 1621–1629 (2022). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 54.Karaman B et al. Pallister–Killian syndrome: clinical, cytogenetic and molecular findings in 15 cases. Mol. Cytogenet 11, 45 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 55.Holzelova E et al. Autoimmune lymphoproliferative syndrome with somatic Fas mutations. N. Engl. J. Med 351, 1409–1418 (2004). [DOI] [PubMed] [Google Scholar]
- 56.Beck DB et al. Somatic mutations in UBA1 and severe adult-onset autoinflammatory disease. N. Engl. J. Med 383, 2628–2638 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 57.Long C et al. Prevention of muscular dystrophy in mice by CRISPR/Cas9-mediated editing of germline DNA. Science 345, 1184–1188 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]; This study demonstrates that a fraction of cells with a corrected Dmd allele can expand and abrogate the muscular dystrophy phenotype in a mouse model.
- 58.Kesari A et al. Somatic mosaicism for Duchenne dystrophy: evidence for genetic normalization mitigating muscle symptoms. Am. J. Med. Genet. A 149A, 1499–1503 (2009). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 59.Huisman SA, Redeker EJ, Maas SM, Mannens MM & Hennekam RC High rate of mosaicism in individuals with Cornelia de Lange syndrome. J. Med. Genet 50, 339–344 (2013). [DOI] [PubMed] [Google Scholar]
- 60.Lindhurst MJ et al. A mosaic activating mutation in AKT1 associated with the Proteus syndrome. N. Engl. J. Med 365, 611–619 (2011). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 61.Donkervoort S et al. Mosaicism for dominant collagen 6 mutations as a cause for intrafamilial phenotypic variability. Hum. Mutat 36, 48–56 (2015). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 62.Li W & Baker NE Engulfment is required for cell competition. Cell 129, 1215–1225 (2007). [DOI] [PubMed] [Google Scholar]
- 63.Claveria C, Giovinazzo G, Sierra R & Torres M Myc-driven endogenous cell competition in the early mammalian embryo. Nature 500, 39–44 (2013). [DOI] [PubMed] [Google Scholar]
- 64.Ellis SJ et al. Distinct modes of cell competition shape mammalian tissue morphogenesis. Nature 569, 497–502 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 65.Zhang G et al. p53 pathway is involved in cell competition during mouse embryogenesis. Proc. Natl Acad. Sci. USA 114, 498–503 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 66.Lima A et al. Cell competition acts as a purifying selection to eliminate cells with mitochondrial defects during early mouse development. Nat. Metab 3, 1091–1108 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 67.Challen GA et al. Dnmt3a is essential for hematopoietic stem cell differentiation. Nat. Genet 44, 23–31 (2011). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 68.Hsu JI et al. PPM1D mutations drive clonal hematopoiesis in response to cytotoxic chemotherapy. Cell Stem Cell 23, 700–713.e6 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 69.Revy P, Kannengiesser C & Fischer A Somatic genetic rescue in Mendelian haematopoietic diseases. Nat. Rev. Genet 20, 582–598 (2019). [DOI] [PubMed] [Google Scholar]; In this review, the authors describe in detail mosaic reversion events occurring in the hematopoietic system, where they have been most commonly described.
- 70.Jongmans MC et al. Revertant somatic mosaicism by mitotic recombination in dyskeratosis congenita. Am. J. Hum. Genet 90, 426–433 (2012). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 71.Catto LFB et al. Somatic genetic rescue in hematopoietic cells in GATA2 deficiency. Blood 136, 1002–1005 (2020). [DOI] [PubMed] [Google Scholar]
- 72.Bar DZ et al. A novel somatic mutation achieves partial rescue in a child with Hutchinson–Gilford progeria syndrome. J. Med. Genet 54, 212–216 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 73.Narumi S et al. SAMD9 mutations cause a novel multisystem disorder, MIRAGE syndrome, and are associated with loss of chromosome 7. Nat. Genet 48, 792–797 (2016). [DOI] [PubMed] [Google Scholar]
- 74.Buonocore F et al. Somatic mutations and progressive monosomy modify SAMD9-related phenotypes in humans. J. Clin. Invest 127, 1700–1713 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 75.Veitia RA MIRAGE syndrome: phenotypic rescue by somatic mutation and selection. Trends Mol. Med 25, 937–940 (2019). [DOI] [PubMed] [Google Scholar]
- 76.Shirley MD et al. Sturge–Weber syndrome and port-wine stains caused by somatic mutation in GNAQ. N. Engl. J. Med 368, 1971–1979 (2013). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 77.Weinstein LS et al. Activating mutations of the stimulatory G protein in the McCune–Albright syndrome. N. Engl. J. Med 325, 1688–1695 (1991). [DOI] [PubMed] [Google Scholar]
- 78.Lim JS et al. Brain somatic mutations in MTOR cause focal cortical dysplasia type II leading to intractable epilepsy. Nat. Med 21, 395–400 (2015). [DOI] [PubMed] [Google Scholar]
- 79.Eskin-Schwartz M et al. Somatic mosaicism for a “lethal” GJB2 mutation results in a patterned form of spiny hyperkeratosis without eccrine involvement. Pediatr. Dermatol 33, 322–326 (2016). [DOI] [PubMed] [Google Scholar]
- 80.Campbell IM et al. Parent of origin, mosaicism, and recurrence risk: probabilistic modeling explains the broken symmetry of transmission genetics. Am. J. Hum. Genet 95, 345–359 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]; This study demonstrates that recurrence risk in offspring varies based on the presence of parental mosaicism and the sex of the mosaic parent.
- 81.Jonsson H et al. Multiple transmissions of de novo mutations in families. Nat. Genet 50, 1674–1680 (2018). [DOI] [PubMed] [Google Scholar]
- 82.Jamuar SS et al. Somatic mutations in cerebral cortical malformations. N. Engl. J. Med 371, 733–743 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 83.Koboldt DC Best practices for variant calling in clinical sequencing. Genome Med. 12, 91 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 84.Yan YH et al. Confirming putative variants at ≤5% allele frequency using allele enrichment and Sanger sequencing. Sci. Rep 11, 11640 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 85.Doan RN et al. MIPP-Seq: ultra-sensitive rapid detection and validation of low-frequency mosaic mutations. BMC Med. Genomics 14, 47 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 86.Zhou B et al. Detection and quantification of mosaic genomic DNA variation in primary somatic tissues using ddPCR: analysis of mosaic transposable-element insertions, copy-number variants, and single-nucleotide variants. Methods Mol. Biol 1768, 173–190 (2018). [DOI] [PubMed] [Google Scholar]
- 87.Ha YJ et al. Comprehensive benchmarking and guidelines of mosaic variant calling strategies. Nat. Methods 20, 2058–2067 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 88.Dou Y et al. Accurate detection of mosaic variants in sequencing data without matched controls. Nat. Biotechnol 38, 314–319 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 89.Huang AY & Lee EA Identification of somatic mutations from bulk and single-cell sequencing data. Front. Aging 2, 800380 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 90.Glessner JT et al. MONTAGE: a new tool for high-throughput detection of mosaic copy number variation. BMC Genomics 22, 133 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 91.Muyas F et al. De novo detection of somatic mutations in high-throughput single-cell profiling data sets. Nat. Biotechnol 10.1038/s41587-023-01863-z (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 92.Salk JJ, Schmitt MW & Loeb LA Enhancing the accuracy of next-generation sequencing for detecting rare and subclonal mutations. Nat. Rev. Genet 19, 269–285 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 93.King DA et al. Detection of structural mosaicism from targeted and whole-genome sequencing data. Genome Res. 27, 1704–1714 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 94.Chen D et al. Human primordial germ cells are specified from lineage-primed progenitors. Cell Rep. 29, 4568–4582.e5 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 95.Yang X et al. Developmental and temporal characteristics of clonal sperm mosaicism. Cell 184, 4772–4783.e15 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 96.Jonsson H et al. Differences between germline genomes of monozygotic twins. Nat. Genet 53, 27–34 (2021). [DOI] [PubMed] [Google Scholar]
- 97.Breuss MW et al. Autism risk in offspring can be assessed through quantification of male sperm mosaicism. Nat. Med 26, 143–150 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 98.Moller RS et al. Parental mosaicism in epilepsies due to alleged de novo variants. Epilepsia 60, e63–e66 (2019). [DOI] [PubMed] [Google Scholar]
- 99.Goriely A et al. Gain-of-function amino acid substitutions drive positive selection of FGFR2 mutations in human spermatogonia. Proc. Natl Acad. Sci. USA 102, 6051–6056 (2005). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 100.Shinde DN et al. New evidence for positive selection helps explain the paternal age effect observed in achondroplasia. Hum. Mol. Genet 22, 4117–4126 (2013). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 101.Yoon SR et al. Age-dependent germline mosaicism of the most common noonan syndrome mutation shows the signature of germline selection. Am. J. Hum. Genet 92, 917–926 (2013). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 102.Choi SK, Yoon SR, Calabrese P & Arnheim N Positive selection for new disease mutations in the human germline: evidence from the heritable cancer syndrome multiple endocrine neoplasia type 2B. PLoS Genet. 8, e1002420 (2012). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 103.Maher GJ et al. Selfish mutations dysregulating RAS–MAPK signaling are pervasive in aged human testes. Genome Res. 28, 1779–1790 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 104.Lim J et al. Selfish spermatogonial selection: evidence from an immunohistochemical screen in testes of elderly men. PLoS ONE 7, e42382 (2012). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 105.Fu XJ et al. Somatic mosaicism and variant frequency detected by next-generation sequencing in X-linked Alport syndrome. Eur. J. Hum. Genet 24, 387–391 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 106.Schirwani S et al. Mosaicism in ASXL3-related syndrome: description of five patients from three families. Eur. J. Med. Genet 63, 103925 (2020). [DOI] [PubMed] [Google Scholar]
- 107.Baker SW et al. Improved molecular detection of mosaicism in Beckwith–Wiedemann syndrome. J. Med. Genet 58, 178–184 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 108.Weksberg R et al. Discordant KCNQ1OT1 imprinting in sets of monozygotic twins discordant for Beckwith–Wiedemann syndrome. Hum. Mol. Genet 11, 1317–1325 (2002). [DOI] [PubMed] [Google Scholar]
- 109.Cohen JL et al. Diagnosis and management of the phenotypic spectrum of twins with Beckwith–Wiedemann syndrome. Am. J. Med. Genet. A 179, 1139–1147 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 110.Urraca N et al. A rare inherited 15q11.2-q13.1 interstitial duplication with maternal somatic mosaicism, renal carcinoma, and autism. Front. Genet 7, 205 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 111.Ansari M et al. Genetic heterogeneity in Cornelia de Lange syndrome (CdLS) and CdLS-like phenotypes with observed and predicted levels of mosaicism. J. Med. Genet 51, 659–668 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 112.Stosser MB et al. High frequency of mosaic pathogenic variants in genes causing epilepsy-related neurodevelopmental disorders. Genet. Med 20, 403–410 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 113.Terracciano A et al. Somatic mosaicism of PCDH19 mutation in a family with low-penetrance EFMR. Neurogenetics 13, 341–345 (2012). [DOI] [PubMed] [Google Scholar]
- 114.Hague J et al. Molecularly proven mosaicism in phenotypically normal parent of a girl with Freeman–Sheldon syndrome caused by a pathogenic MYH3 mutation. Am. J. Med. Genet. A 170, 1608–1612 (2016). [DOI] [PubMed] [Google Scholar]
- 115.Alcantara-Montiel JC et al. Somatic mosaicism in B cells of a patient with autosomal dominant hyper IgE syndrome. Eur. J. Immunol 46, 2438–2443 (2016). [DOI] [PubMed] [Google Scholar]
- 116.Hsu AP et al. Intermediate phenotypes in patients with autosomal dominant hyper-IgE syndrome caused by somatic mosaicism. J. Allergy Clin. Immunol 131, 1586–1593 (2013). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 117.Hildebrand MS et al. Mutations of the sonic hedgehog pathway underlie hypothalamic hamartoma with gelastic epilepsy. Am. J. Hum. Genet 99, 423–429 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 118.Green TE et al. Sporadic hypothalamic hamartoma is a ciliopathy with somatic and bi-allelic contributions. Hum. Mol. Genet 31, 2307–2316 (2022). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 119.Green TE et al. Brain mosaicism of hedgehog signalling and other cilia genes in hypothalamic hamartoma. Neurobiol. Dis 185, 106261 (2023). [DOI] [PubMed] [Google Scholar]
- 120.Prochazkova K et al. Somatic TP53 mutation mosaicism in a patient with Li–Fraumeni syndrome. Am. J. Med. Genet. A 149A, 206–211 (2009). [DOI] [PubMed] [Google Scholar]
- 121.Consoli C et al. Gonosomal mosaicism for a nonsense mutation (R1947X) in the NF1 gene in segmental neurofibromatosis type 1. J. Invest. Dermatol 125, 463–466 (2005). [DOI] [PubMed] [Google Scholar]
- 122.Friedman DP Segmental neurofibromatosis (NF-5): a rare form of neurofibromatosis. AJNR Am. J. Neuroradiol 12, 971–972 (1991). [PMC free article] [PubMed] [Google Scholar]
- 123.Ruggieri M & Polizzi A Segmental neurofibromatosis. J. Neurosurg 93, 530–532 (2000). [DOI] [PubMed] [Google Scholar]
- 124.Boyd KP, Korf BR & Theos A Neurofibromatosis type 1. J. Am. Acad. Dermatol 61, 1–14 (2009). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 125.Kluwe L & Mautner VF Mosaicism in sporadic neurofibromatosis 2 patients. Hum. Mol. Genet 7, 2051–2055 (1998). [DOI] [PubMed] [Google Scholar]
- 126.Evans DG et al. Incidence of mosaicism in 1055 de novo NF2 cases: much higher than previous estimates with high utility of next-generation sequencing. Genet. Med 22, 53–59 (2020). [DOI] [PubMed] [Google Scholar]
- 127.Kim HJ, Song MJ, Lee KO, Kim SH & Kim HJ Paternal somatic mosaicism of a novel frameshift mutation in ELANE causing severe congenital neutropenia. Pediatr. Blood Cancer 62, 2229–2231 (2015). [DOI] [PubMed] [Google Scholar]
- 128.Bartsch O et al. Inheritance and variable expression in Rubinstein–Taybi syndrome. Am. J. Med. Genet. A 152A, 2254–2261 (2010). [DOI] [PubMed] [Google Scholar]
- 129.Kamien B et al. Somatic-gonadal mosaicism causing Sotos syndrome. Am. J. Med. Genet. A 170, 3360–3362 (2016). [DOI] [PubMed] [Google Scholar]
- 130.Spiegel R et al. Severe infantile male encephalopathy is a result of early post-zygotic WDR45 somatic mutation. Clin. Genet 90, 560–562 (2016). [DOI] [PubMed] [Google Scholar]
- 131.Nakashima M et al. WDR45 mutations in three male patients with West syndrome. J. Hum. Genet 61, 653–661 (2016). [DOI] [PubMed] [Google Scholar]
- 132.Cooley Coleman JA et al. Mosaicism of common pathogenic MECP2 variants identified in two males with a clinical diagnosis of Rett syndrome. Am. J. Med. Genet. A 188, 2988–2998 (2022). [DOI] [PubMed] [Google Scholar]
- 133.Xin B et al. Novel DNMT3A germline mutations are associated with inherited Tatton–Brown–Rahman syndrome. Clin. Genet 91, 623–628 (2017). [DOI] [PubMed] [Google Scholar]
- 134.Hyland VJ et al. Somatic and germline mosaicism for a R248C missense mutation in FGFR3, resulting in a skeletal dysplasia distinct from thanatophoric dysplasia. Am. J. Med. Genet. A 120A, 157–168 (2003). [DOI] [PubMed] [Google Scholar]
- 135.Takagi M, Kaneko-Schmitt S, Suzumori N, Nishimura G & Hasegawa T Atypical achondroplasia due to somatic mosaicism for the common thanatophoric dysplasia mutation R248C. Am. J. Med. Genet. A 158A, 247–250 (2012). [DOI] [PubMed] [Google Scholar]
- 136.Tyburczy ME et al. Mosaic and intronic mutations in TSC1/TSC2 explain the majority of TSC patients with no mutation identified by conventional testing. PLoS Genet. 11, e1005637 (2015). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 137.Venot Q et al. Targeted therapy in patients with PIK3CA-related overgrowth syndrome. Nature 558, 540–546 (2018). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 138.Bennett JT et al. Mosaic activating mutations in FGFR1 cause encephalocraniocutaneous lipomatosis. Am. J. Hum. Genet 98, 579–587 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 139.Baldassari S et al. Dissecting the genetic basis of focal cortical dysplasia: a large cohort study. Acta Neuropathol. 138, 885–900 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 140.Kobow K et al. Mosaic trisomy of chromosome 1q in human brain tissue associates with unilateral polymicrogyria, very early-onset focal epilepsy, and severe developmental delay. Acta Neuropathol. 140, 881–891 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 141.Miller KE et al. Post-zygotic rescue of meiotic errors causes brain mosaicism and focal epilepsy. Nat. Genet 55, 1920–1928 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 142.Prokopchuk O et al. Maffucci syndrome and neoplasms: a case report and review of the literature. BMC Res. Notes 9, 126 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 143.Zhuang Z et al. Somatic HIF2A gain-of-function mutations in paraganglioma with polycythemia. N. Engl. J. Med 367, 922–930 (2012). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 144.Wang H, Zhuang Z, Rosenblum JS & Pacak K Somatic mosaicism of EPAS1 mutations in Pacak–Zhuang syndrome. Endocr. Pract 28, 734–735 (2022). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 145.Groesser L et al. Postzygotic HRAS and KRAS mutations cause nevus sebaceous and Schimmelpenning syndrome. Nat. Genet 44, 783–787 (2012). [DOI] [PubMed] [Google Scholar]
- 146.Greco E, Minasi MG & Fiorentino F Healthy babies after intrauterine transfer of mosaic aneuploid blastocysts. N. Engl. J. Med 373, 2089–2090 (2015). [DOI] [PubMed] [Google Scholar]
- 147.Capalbo A et al. Mosaic human preimplantation embryos and their developmental potential in a prospective, non-selection clinical trial. Am. J. Hum. Genet 108, 2238–2247 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 148.Zhang YX et al. The pregnancy outcome of mosaic embryo transfer: a prospective multicenter study and meta-analysis. Genes 11, 973 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 149.Essers R et al. Prevalence of chromosomal alterations in first-trimester spontaneous pregnancy loss. Nat. Med 29, 3233–3242 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 150.Currie CE et al. The first mitotic division of human embryos is highly error prone. Nat. Commun 13, 6755 (2022). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 151.Debo B, Van Loocke M, De Groote K, De Leenheer E & Cools M Multidisciplinary approach to the child with sex chromosomal mosaicism including a Y-containing cell line. Int. J. Environ. Res. Public Health 18, 917 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 152.Huang AC, Olson SB & Maslen CL A review of recent developments in Turner syndrome research. J. Cardiovasc. Dev. Dis 8, 138 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 153.Posey JE et al. Triploidy mosaicism (45,X/68,XX) in an infant presenting with failure to thrive. Am. J. Med. Genet. A 170, 694–698 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 154.Balbeur S et al. Trisomy rescue mechanism: the case of concomitant mosaic trisomy 14 and maternal uniparental disomy 14 in a 15-year-old girl. Clin. Case Rep 4, 265–271 (2016). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 155.Coorens THH et al. Inherent mosaicism and extensive mutation of human placentas. Nature 592, 80–85 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 156.Yang M et al. Depletion of aneuploid cells in human embryos and gastruloids. Nat. Cell Biol 23, 314–321 (2021). [DOI] [PubMed] [Google Scholar]
- 157.Singla S, Iwamoto-Stohl LK, Zhu M & Zernicka-Goetz M Autophagy-mediated apoptosis eliminates aneuploid cells in a mouse model of chromosome mosaicism. Nat. Commun 11, 2958 (2020). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 158.Price CJ et al. Genetically variant human pluripotent stem cells selectively eliminate wild-type counterparts through YAP-mediated cell competition. Dev. Cell 56, 2455–2470. e10 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 159.Zhang F, Gu W, Hurles ME & Lupski JR Copy number variation in human health, disease, and evolution. Annu. Rev. Genomics Hum. Genet 10, 451–481 (2009). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 160.Pham J et al. Somatic mosaicism detected by exon-targeted, high-resolution aCGH in 10,362 consecutive cases. Eur. J. Hum. Genet 22, 969–978 (2014). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 161.Ballif BC et al. Detection of low-level mosaicism by array CGH in routine diagnostic specimens. Am. J. Med. Genet. A 140, 2757–2767 (2006). [DOI] [PubMed] [Google Scholar]
- 162.Messiaen L et al. Mosaic type-1 NF1 microdeletions as a cause of both generalized and segmental neurofibromatosis type-1 (NF1). Hum. Mutat 32, 213–219 (2011). [DOI] [PubMed] [Google Scholar]
- 163.Allen SE et al. Versatile CRISPR/Cas9-mediated mosaic analysis by gRNA-induced crossing-over for unmodified genomes. PLoS Biol. 19, e3001061 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 164.Zong H, Espinosa JS, Su HH, Muzumdar MD & Luo L Mosaic analysis with double markers in mice. Cell 121, 479–492 (2005). [DOI] [PubMed] [Google Scholar]
- 165.Henner A, Ventura PB, Jiang Y & Zong H MADM-ML, a mouse genetic mosaic system with increased clonal efficiency. PLoS ONE 8, e77672 (2013). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 166.Livet J et al. Transgenic strategies for combinatorial expression of fluorescent proteins in the nervous system. Nature 450, 56–62 (2007). [DOI] [PubMed] [Google Scholar]
- 167.Mintz B & Silvers WK “Intrinsic” immunological tolerance in allophenic mice. 1967. J. Immunol 178, 4007–4010 (2007). [PubMed] [Google Scholar]
- 168.Sakaue M et al. DNA methylation is dispensable for the growth and survival of the extraembryonic lineages. Curr. Biol 20, 1452–1457 (2010). [DOI] [PubMed] [Google Scholar]
- 169.Ueno H & Weissman IL Clonal analysis of mouse development reveals a polyclonal origin for yolk sac blood islands. Dev. Cell 11, 519–533 (2006). [DOI] [PubMed] [Google Scholar]
- 170.Kinoshita M et al. Disabling de novo DNA methylation in embryonic stem cells allows an illegitimate fate trajectory. Proc. Natl Acad. Sci. USA 118, e2109475118 (2021). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 171.Wang L et al. CRISPR–Cas9-mediated genome editing in one blastomere of two-cell embryos reveals a novel Tet3 function in regulating neocortical development. Cell Res. 27, 815–829 (2017). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 172.Nakamura S, Watanabe S, Ando N, Ishihara M & Sato M Transplacental gene delivery (TPGD) as a noninvasive tool for fetal gene manipulation in mice. Int. J. Mol. Sci 20, 5926 (2019). [DOI] [PMC free article] [PubMed] [Google Scholar]
- 173.Lipshutz GS et al. In utero delivery of adeno-associated viral vectors: intraperitoneal gene transfer produces long-term expression. Mol. Ther 3, 284–292 (2001). [DOI] [PubMed] [Google Scholar]
- 174.Wang Z et al. Positive selection of somatically mutated clones identifies adaptive pathways in metabolic liver disease. Cell 186, 1968–1984.e20 (2023). [DOI] [PMC free article] [PubMed] [Google Scholar]