


Key Points
Question
What clinical factors predict death or severe neurodevelopmental impairment (NDI) among infants treated with hypothermia for hypoxic-ischemic encephalopathy (HIE)?
Findings
This prognostic study including 424 neonates and using recursive binary partitioning identified key factors within 24 hours after birth (including severely abnormal electroencephalogram [EEG], pH of 7.11 or below, and 5-minute Apgar score of 0) and after cooling (2 of 3 deep gray regions injured on magnetic resonance imaging [MRI] and severely abnormal 24-hour EEG) that, when present, were specific and had high positive predictive value for death or severe NDI in internal and external validation data.
Meaning
These results suggest that among infants with HIE clinical, EEG and MRI have high specificity to predict death or severe NDI at age 2 years.
This prognostic study of neonates with moderate-severe hypoxic-ischemic encephalopathy enrolled in a large US clinical trial examines clinical characteristics that may predict death or severe neurodevelopmental impairment.
Abstract
Importance
Outcomes after hypoxic-ischemic encephalopathy (HIE) are variable. Predicting death or severe neurodevelopmental impairment (NDI) in affected neonates is crucial for guiding management and parent communication.
Objective
To predict death or severe NDI in neonates who receive hypothermia for HIE.
Design, Setting, and Participants
This prognostic study included participants enrolled in a large US clinical trial conducted in US neonatal intensive care units who were born between January 2017 and October 2019 and followed up to age 2 years. Eligible participants were neonates with moderate-severe HIE born at 36 weeks or more gestation and with 2-year outcome data. Data were analyzed June 2023. External validation was performed with a UK cohort.
Exposure
Clinical, electroencephalography (EEG), and magnetic resonance imaging (MRI) variables were curated and examined at 24 hours and following cooling.
Main Outcome and Measures
Death or severe NDI at age 2 years. Severe NDI was defined as Bayley Scales of Infant Toddler Development cognitive score below 70, Gross Motor Function Classification System score of 3 or higher, or quadriparesis. Model performance metrics were derived from training, internal, and external validation datasets.
Results
Among 424 neonates (mean [SD] gestational age, 39.1 [1.4] weeks; 192 female [45.3%]; 28 Asian [6.6%], 50 Black [11.8%], 311 White [73.3%]), 105 (24.7%) had severe encephalopathy at enrollment. Overall, 59 (13.9%) died and 46 (10.8%) had severe NDI. In the 24-hour model, the combined presence of 3 clinical characteristics—(1) severely abnormal EEG, (2) pH level of 7.11 or below, and (3) 5-minute Apgar score of 0—had a specificity of 99.6% (95% CI, 97.5%-100%) and a positive predictive value (PPV) of 95.2% (95% CI, 73.2%-99.3%). Validation model metrics were 97.9% (95% CI, 92.7%-99.8%) for internal specificity, with a PPV of 77.8% (95% CI, 43.4%-94.1%), and 97.6% (95% CI, 95.1%-99.0%) for external specificity, with a PPV of 46.2% (95% CI, 23.3%-70.8%). In the postcooling model, specificity for T1, T2, or diffusion-weighted imaging (DWI) abnormality in at least 2 of 3 deep gray regions (ie, thalamus, caudate, putamen and/or globus pallidus) plus a severely abnormal EEG within the first 24 hours was 99.1% (95% CI, 96.8%-99.9%), with a PPV of 91.7% (95% CI, 72.8%-97.8%). Internal specificity in this model was 98.9% (95% CI, 94.1%-100%), with a PPV of 92.9% (95% CI, 64.2%-99.0%); external specificity was 98.6% (95% CI, 96.5%-99.6%), with a PPV of 83.3% (95% CI, 64.1%-93.4%).
Conclusions and Relevance
In this prognostic study of neonates with moderate or severe HIE who were treated with therapeutic hypothermia, simple models using readily available clinical, EEG, and MRI results during the hospital admission had high specificity and PPV for death or severe NDI at age 2 years.
Introduction
Perinatal hypoxic-ischemic encephalopathy (HIE) occurs in approximately 1.5 per 1000 live births and is a leading cause of morbidity and mortality in the US and worldwide.1 Outcome is variable, with nearly half of infants having normal neurodevelopment at age 2 years, and the remainder sustaining a spectrum of neurodevelopmental impairment (NDI) or early death. Timely and accurate prediction of death or severe NDI in affected neonates is crucial for guiding management and communication.
Existing tools to predict outcome in neonates with HIE are limited by single-center studies, small study size, and limited types of predictors (eg, using biomarkers or imaging techniques that are not widely available,2,3,4,5 or using only clinical,6,7,8,9,10,11,12,13,14 neurophysiology,15,16 or neuroimaging results,17,18,19,20,21 or combining 2 of the 322,23,24,25,26). A 2023 systematic review27 concluded that existing models are of insufficient quality to be incorporated into clinical practice.
To overcome limitations of prior studies, we used data from the High-Dose Erythropoietin for Asphyxia and Encephalopathy (HEAL) trial (ClinicalTrials.org identifier, NCT02811263),28 and a prospective, population-based cohort of neonates with encephalopathy from the UK to train, test, and validate models. The HEAL trial was a randomized, double-masked trial of erythropoeitin (5 doses of 1000 IU per kilogram of body weight administered intravenously over the first week after birth) compared with placebo that showed no neuroprotective effect in 500 neonates with moderate to severe HIE. We hypothesized that readily available data from clinical, neurophysiology, and magnetic resonance imaging (MRI) reports could be used to develop a decision tree to predict neonates with at least 85% likelihood of death or severe NDI.
Methods
Overview
The HEAL protocol29 and primary results of 500 infants born January 2017 to October 2019 with moderate to severe HIE who received therapeutic hypothermia were previously published.28 This study was approved by the institutional review boards at all sites and participants were enrolled after written informed consent obtained prenatally. The approach toward building and reporting clinical prediction models adhered to the most recent Transparent Reporting of a multivariable prediction model for Individual Prognosis Or Diagnosis (TRIPOD+AI) guidance statement for prognostic studies using artificial intelligence.
Neonates were eligible for the HEAL Trial if they: (1) were at 36 weeks’ gestation or more at birth; (2) had 1 or more signs of perinatal depression (ie, Apgar score below 5 at 10 minutes; cardiorespiratory resuscitation beyond 10 minutes of age; pH level below 7.00 or with a base deficit of 15 mmol/L or more in a cord or infant gas within 60 minutes of age); (3) moderate or severe encephalopathy; and (4) hypothermia started within 6 hours of birth. Exclusion criteria for the HEAL Trial were birthweight below 1800 g, head circumference smaller than 30 cm, identified genetic or congenital condition affecting neurodevelopment, hematocrit above 65.0%, considering redirection of care, encephalopathy attributed to a postnatal event, and unlikely to be receive follow-up.28 Participants were additionally excluded from the current analysis a priori if they were later diagnosed with a congenital or genetic condition known to affect neurodevelopment before age 2 years, if they required extracorporeal membrane oxygenation (ECMO), or if neurophysiology results or outcome were not available.
Clinical Predictors
Maternal and neonatal variables were collected from the medical record. Race and ethnicity (Hispanic or Latino, non-Hispanic) were determined by self-report; categories for race included American Indian or Alaskan Native, Asian, Black or African American, Native Hawaiian or other Pacific Islander, White, unknown, and not reported. Race and ethnicity were included because they have been shown to be a factor in birth outcomes. Severity of encephalopathy was classified as moderate or severe based on a modified Sarnat examination.29
Electroencephalogram
For neonates with electroencephalogram (EEG) (97%) or amplitude-integrated EEG (aEEG) (3%) within 24 hours after birth, the clinical report was used to determine the presence of seizures and to classify the first described background at onset of recording as normal, excessively discontinuous, or severely abnormal using American Clinical Neurophysiology Society criteria.30 For 135 neonates (31%), EEG acquired throughout therapeutic hypothermia was reviewed by 2 pediatric neurophysiologists and the background scored at 5 time points as part of an ancillary study.16 The predominant background pattern was determined using the mean of the 5 EEG background ratings.16
Magnetic Resonance Imaging
MRI was performed at 5 days of age (recommended imaging timing 96 to 144 hours after birth) using 3T MR scanners and standardized T1, T2, and diffusion-weighted imaging (DWI) sequences that were harmonized across sites.31 Two of 3 independent readers independently reviewed the images to determine the severity, location, and pattern of brain injury using a standardized scoring system,32 with discrepancies resolved by consensus.31
Outcome
Examiners were trained and certified annually. Cognitive outcome was determined using the Bayley Scales of Infant Toddler Development, third edition (BSID-III) cognitive subscale. Motor outcome included cerebral palsy according to a standardized neurologic examination33 and the Gross Motor Function Classification System (GMFCS) score, modified for infants. GMFCS was assigned to describe the degree of functional disability and whether or not the infant had cerebral palsy (CP) by examination.34 Due to circumstances related to the COVID-19 pandemic, the assessment window was expanded, from the planned ages 22 to 26 months to ages 22 to 36 months.
The primary outcome was death or severe NDI (BSID-III cognitive score below 70, GMFCS 3 or higher, or quadriparesis with GMFCS 1 or higher) at age 2 years. A 5-level secondary outcome was defined as: no NDI, mild NDI, moderate NDI, severe NDI (as defined previously), or death, where severity was assigned using the worst of cognitive or motor outcome. BSID-III cognitive outcome was defined as: normal (≥90); mild (85-89); moderate (70-84). For motor outcome, hemiparesis or diparesis with GMFCS below 1 or no CP with GMFCS of 1 considered mild. Quadriparesis with GMFCS below 1, hemiparesis or diparesis with GMFCS 1 or 2, or no CP with GMFCS of 2 was considered moderate.
Data Curation
From a study-wide dataset of 1404 variables, dates, study drug, adverse events, family history, placenta, outcome, and comments or descriptive variables were removed a priori (eFigure 1 in Supplement 1). We next removed 659 variables that were missing in 10% of participants or more, 481 variables with sparsity (ie, present in less than 10%), and 78 variables with low correlation (ρ < 0.1) with the primary outcome. When 2 or more variables were highly correlated, the most clinically relevant and widely accessible variable was retained. We derived 69 new variables to enhance clinical applicability.
Statistical Analysis
Two recursive partitioning decision tree prediction models were developed (CTree method using the party library in R version 4.3.1 [R Project for Statistical Computing]) based on data available within the first day (for the 24 hour model) and after rewarming and MRI (postcooling model) (eTable 1 in Supplement 1).35 Data were split 70:30 into training and validation datasets with equal proportions of the primary outcome. Within the training dataset, 10-fold cross-validation was implemented to determine the simplest decision tree resulting in at least 1 group experiencing greater than 85% death or severe NDI (for both models). Infants not identified in the death or severe NDI group in the 24 hour model and who survived to the end of rewarming were included in the postcooling model. Performance metrics—sensitivity, specificity, positive and negative predictive values (PPV, NPV), and accuracy—with 95% CIs were assessed in both the training and validation datasets. CIs were derived using the Clopper-Pearson method for binomial distributions with the bdpv library in R using the actual prevalence of the outcome in each 2 × 2 table.36 CIs for multilevel outcomes were determined using the Wilson method in the binom library in R.
External Validation
For external validation, we analyzed a prospectively collected population-based UK cohort of 365 neonates at 36 weeks gestation or more fulfilling local guidelines for therapeutic hypothermia: (1) at least 1 of 10-minute Apgar score 5 or below, assisted ventilation 10 minutes after birth, pH level below 7.0, or base excess of −16 mmol/L or less in the first hour; (2) moderate or severe encephalopathy; or (3) moderately or severely abnormal aEEG or 3 or more minutes of aEEG seizures per hour within 6 hours of birth. Model variables were similar between cohorts except aEEG, which was only available for less than 6 hours after birth. Burst suppression, low amplitude, and flat trace were defined as severely abnormal. MRI basal ganglia or thalamus injury was scored according to Rutherford et al37 using T1, T2, and DWI when available, which was similar to the HEAL methods.38 BSID-III motor or cognitive subscale below 70 or GMFCS above 2 at ages 18 to 24 months was considered severe NDI.
Missing clinical data were imputed with the median value. Missing MRI values for infants who survived to day 5 (8 training, 8 internal validation, and 11 external validation) were imputed with the highest (worst) scores, assuming clinical instability as the reason for missing imaging data.
Sensitivity Analyses
We performed sensitivity analyses to examine the predictive accuracy of the final decision tree based on the following: (1) timing of MRI (within or after 7 days after birth), (2) ignoring the 24-hour model (ie, including all neonates who survived to the end of cooling), (3) using only the available MRI data without imputation, and (4) combining the HEAL and UK datasets for the postcooling model only on infants who survived to discharge.
Results
Among 500 neonates enrolled in the HEAL trial, 424 (84.8%) were included in the predictive modeling dataset (mean [SD] gestational age, 39.1 [1.4] weeks; 192 female [45.3%]; 28 Asian [6.6%], 50 Black [11.8%], 311 White [73.3%]); 105 infants (24.7%) had severe encephalopathy at enrollment. A priori exclusions were as follows: loss to follow-up (38 infants [7.6%]), ECMO (22 infants [4.4%]), diagnosis of a congenital or genetic condition known to affect neurodevelopment (21 infants [4.2%]), and no EEG or aEEG available (13 infants [2.6%]). The primary outcome of death or severe NDI was present in 105 infants (24.8%): 59 (13.9%) died and 46 (10.8%) had severe NDI. Multiple clinical, EEG, and imaging factors were associated with death or severe NDI (Table 1).
Table 1. Clinical, EEG, and MRI Characteristics of 424 Neonates With Hypoxic-Ischemic Encephalopathy With and Without Death or Severe NDI at Age 2 Years.
| Characteristics | No. (%) | P valuea | ||
|---|---|---|---|---|
| Total (N = 424) | NDI | |||
| Death or severe (n = 105) | None, mild, or moderate (n = 319) | |||
| Delivery and resuscitation | ||||
| Sentinel eventb | 129 (30.4) | 38 (36.1) | 91 (28.5) | .14 |
| Urgent or emergent cesarean section delivery | 268 (63.2) | 75 (71.4) | 193 (60.5) | .04 |
| Epinephrine or resuscitation >10 min | 385 (90.8) | 102 (97.1) | 283 (89.7) | .01 |
| Infant clinical characteristics | ||||
| Sex | ||||
| Female | 192 (45.3) | 49 (46.7) | 143 (44.8) | .74 |
| Male | 232 (54.7) | 56 (53.3) | 176 (55.2) | |
| Hispanic ethnicity | 100 (23.6) | 22 (20.9) | 78 (24.4) | .46 |
| Race | ||||
| Asian | 28 (6.6) | 3 (2.8) | 25 (7.9) | .17 |
| Black or African American | 50 (11.8) | 14 (13.3) | 36 (11.3) | |
| White | 311 (73.3) | 76 (72.3) | 235 (73.7) | |
| Other or multiplec | 35 (8.2) | 12 (11.4) | 23 (7.3) | |
| Birth weight, mean (SD), g | 3374 (591) | 3369 (605) | 3376 (588) | .92 |
| Gestational age, mean (SD), wk | 39.1 (1.4) | 39.0 (1.5) | 39.2 (1.4) | .26 |
| 5-min Apgar score, median (IQR) | 3 (2-5) | 2 (0-3) | 4 (2-5) | <.001 |
| Lowest pH, mean (SD)d | 6.9 (0.2) | 6.8 (0.2) | 7.0 (0.2) | <.001 |
| Worst base deficit, mean (SD), mmol/Ld | 18.3 (5.6) | 21.5 (7.2) | 17.4 (5.6) | <.001 |
| Severe encephalopathy at enrollmente | 105 (24.8) | 61 (58.1) | 44 (13.8) | <.001 |
| No. of severe Sarnat exam categories at enrollment, median (IQR) | 1 (1-3) | 3 (2-5) | 1 (0-2) | <.001 |
| Maximum glucose first 24 h mean (SD), mg/dL | 174.5 (74.4) | 219.9 (88.9) | 159.6 (62.4) | <.001 |
| Minimum glucose first 24 h mean (SD), mg/dL | 91.1 (40.1) | 106.3 (49.9) | 85.7 (34.5) | <.001 |
| Intubated or ventilated | 339 (80.0) | 100 (95.2) | 239 (74.9) | <.001 |
| ALT ≥100, U/L | 178 (42.0) | 73 (69.5) | 105 (32.9) | <.001 |
| Creatinine >1.5 mg/DL | 41 (9.7) | 26 (24.8) | 15 (4.7) | <.001 |
| Clinical EEG report | ||||
| EEG background, first 24 hf | ||||
| Normal | 172 (40.6) | 7 (6.7) | 165 (51.7) | <.001 |
| Discontinuous | 141 (33.3) | 19 (18.1) | 122 (38.2) | |
| Severely abnormal | 111 (26.2) | 79 (75.2) | 32 (10.0) | |
| Seizures within first 24 h | 96 (22.6) | 48 (45.7) | 48 (15.0) | <.001 |
| MRI | ||||
| Patients, No. | 402 | 86 | 316 | |
| MRI day of life, median (IQR) | 4.9 (4.5-5.6) | 4.8 (4.2-5.4) | 5.0 (4.5-5.6) | .19 |
| Thalamus T1, T2, DWI abnormality | 170 (42.3) | 79 (91.9) | 91 (28.8) | <.001 |
| Caudate T1, T2, DWI abnormality | 71 (17.7) | 56 (65.1) | 15 (4.7) | <.001 |
| Putamen/globus pallidus T1, T2, DWI abnormality | 181 (45.0) | 77 (89.5) | 104 (32.6) | <.001 |
| Post-MRI Sarnat examination | ||||
| Patients, No. | 401 | 90 | 311 | |
| No. of severe Sarnat examination category results, median (IQR) | 0 (0-1) | 2 (1-5) | 0 (0-0) | <.001 |
Abbreviations: ALT, alanine transferase; DWI, diffusion weighted imaging; EEG, electroencephalogram; MRI, magnetic resonance imaging; NDI, neurodevelopmental impairment.
SI conversion factor: To convert ALT to microkats per liter, multiply by 0.0167; creatinine to micromoles per liter, multiply by 88.4; glucose to millimoles per liter, multiply by 0.0555.
Unadjusted P values were calculated using 2-sample t test for continuous variables and χ2 tests for categorical variables, or Fisher exact tests when tabulated counts were 5 or less.
Sentinel event indicates placental abruption, shoulder dystocia, uterine rupture, or prolapsed cord.
Other included American Indian or Alaska Native, unknown, and not reported.
Lowest pH and worst base deficit among cord arterial, cord venous, and arterial blood gas samples taken before 60 minutes of age.
Severe encephalopathy as defined by modified Sarnat score.
Severely abnormal EEG defined as burst suppression, low voltage suppressed, or status epilepticus.
Twenty-Four–Hour Model
We first created a recursive partitioning model using the curated set of 12 variables that were available at 24 hours of age. Three factors were highly predictive of death or severe NDI: (1) severely abnormal EEG (burst suppression, flat tracing, or status epilepticus) within the first 24 hours, (2) lowest cord or 60-minute pH level of 7.11 or lower, and (3) 5-minute Apgar equal to 0 (Figure 1). The presence of all 3 of these factors had a specificity of 99.6% (95% CI, 97.5%-100%) and a PPV 95.2% (95% CI, 73.2%-99.3%) for death or severe NDI in the training dataset, and a specificity of 97.9% (95% CI, 92.7%-99.8%) with a PPV 77.8% (95% CI, 43.4%-94.1%) in the internal validation dataset (Table 2).
Figure 1. Models Predicting Death or Severe Neurodevelopmental Impairment (NDI) at Age 2 Years With Hypoxic-Ischemic Encephalopathy.

DWI indicates diffusion-weighted imaging; EEG, electroencephalogram.
Table 2. Training and Validation Test Metrics for 24-Hour and Postcooling Models for Death or Severe Neurodevelopmental Impairment at Age 2 Years.
| Dataset or metric | 24-h model, % (95% CI) (N = 424) | Postcooling model, % (95% CI) (n = 387) |
|---|---|---|
| Training | ||
| Sensitivity | 27.4 (17.6-39.1) | 45.8 (31.4-60.8) |
| Specificity | 99.6 (97.5-100) | 99.1 (96.8-99.9) |
| Positive predictive value | 95.2 (73.2-99.3) | 91.7 (72.8-97.8) |
| Negative predictive value | 80.6 (78.3-82.7) | 89.4 (86.7-91.7) |
| Accuracy | 81.7 (76.8-85.9) | 89.6 (85.4-93.0) |
| Internal validation | ||
| Sensitivity | 21.9 (9.3-40.0) | 56.5 (34.5-76.8) |
| Specificity | 97.9 (92.7-99.8) | 98.9 (94.2-100) |
| Positive predictive value | 77.8 (43.4-94.1) | 92.9 (64.2-99.0) |
| Negative predictive value | 79.0 (75.8-81.9) | 90.3 (85.4-93.7) |
| Accuracy | 78.9 (70.8-85.6) | 90.6 (83.8-95.2) |
| External validation a | ||
| Sensitivity | 6.6 (2.5-13.8) | 38.5 (25.3-53.0) |
| Specificity | 97.6 (95.1-99.0) | 98.6 (96.5-99.6) |
| Positive predictive value | 46.2 (23.3-70.8) | 83.3 (64.1-93.4) |
| Negative predictive value | 77.1 (76.1-78.1) | 89.8 (87.7-91.6) |
| Accuracy | 76.0 (71.5-80.2) | 89.4 (85.6-92.5) |
The external validation cohort was a prospectively collected UK cohort of 365 neonates at ≥36 weeks gestation.
Postcooling Model
We then created a recursive partitioning model using a curated set of 40 variables that were available after therapeutic hypothermia and MRI (Figure 1). Seven children who were not predicted to have death or severe NDI in the 24-hour model died prior to rewarming and MRI and, therefore, were excluded from the postcooling model (5 of 275 [0.7%] in the training dataset and 2 of 119 [1.7%] in the validation dataset).
In the postcooling model, T1, T2, or diffusion-weighted imaging (DWI) abnormality on MRI in at least 2 of 3 deep gray regions (ie, thalamus, caudate, and putamen or globus pallidus) combined with a severely abnormal EEG in the first 24 hours had a specificity of 99.1% (95% CI, 96.8%-99.9%) and PPV of 91.7% (95% CI, 72.8%-97.8%) for death or severe NDI within the training dataset, and a specificity of 98.9% (95% CI, 94.1%-100%) and PPV of 92.9% (95% CI, 64.2%-99.0%) in the internal validation dataset (Table 2).
Individual outcomes of the surviving infants who were predicted to have death or severe NDI are presented in eTable 2 in Supplement 1. Stratified analyses for the 5-level outcome by MRI and 24-hour EEG background (Figure 2) and by predominant EEG background throughout cooling (Figure 3) provide additional information about likelihood of each outcome. Review of the MRI results among children predicted to but who did not have death or severe NDI (ie, false-positive MRI) demonstrated either very small areas of injury that spanned multiple scored regions (2 infants; eFigure 2 in Supplement 1) or had abnormal signal that could be interpreted as pre-Wallerian or secondary degeneration (eg, reduced diffusion in the dorsal thalami instead of the ventrolateral thalami (1 infant).
Figure 2. Neurodevelopmental Outcome Among the Neonates Not Predicted to Sustain Death or Severe Neurodevelopmental Impairment (NDI) and for the Full Cohort.
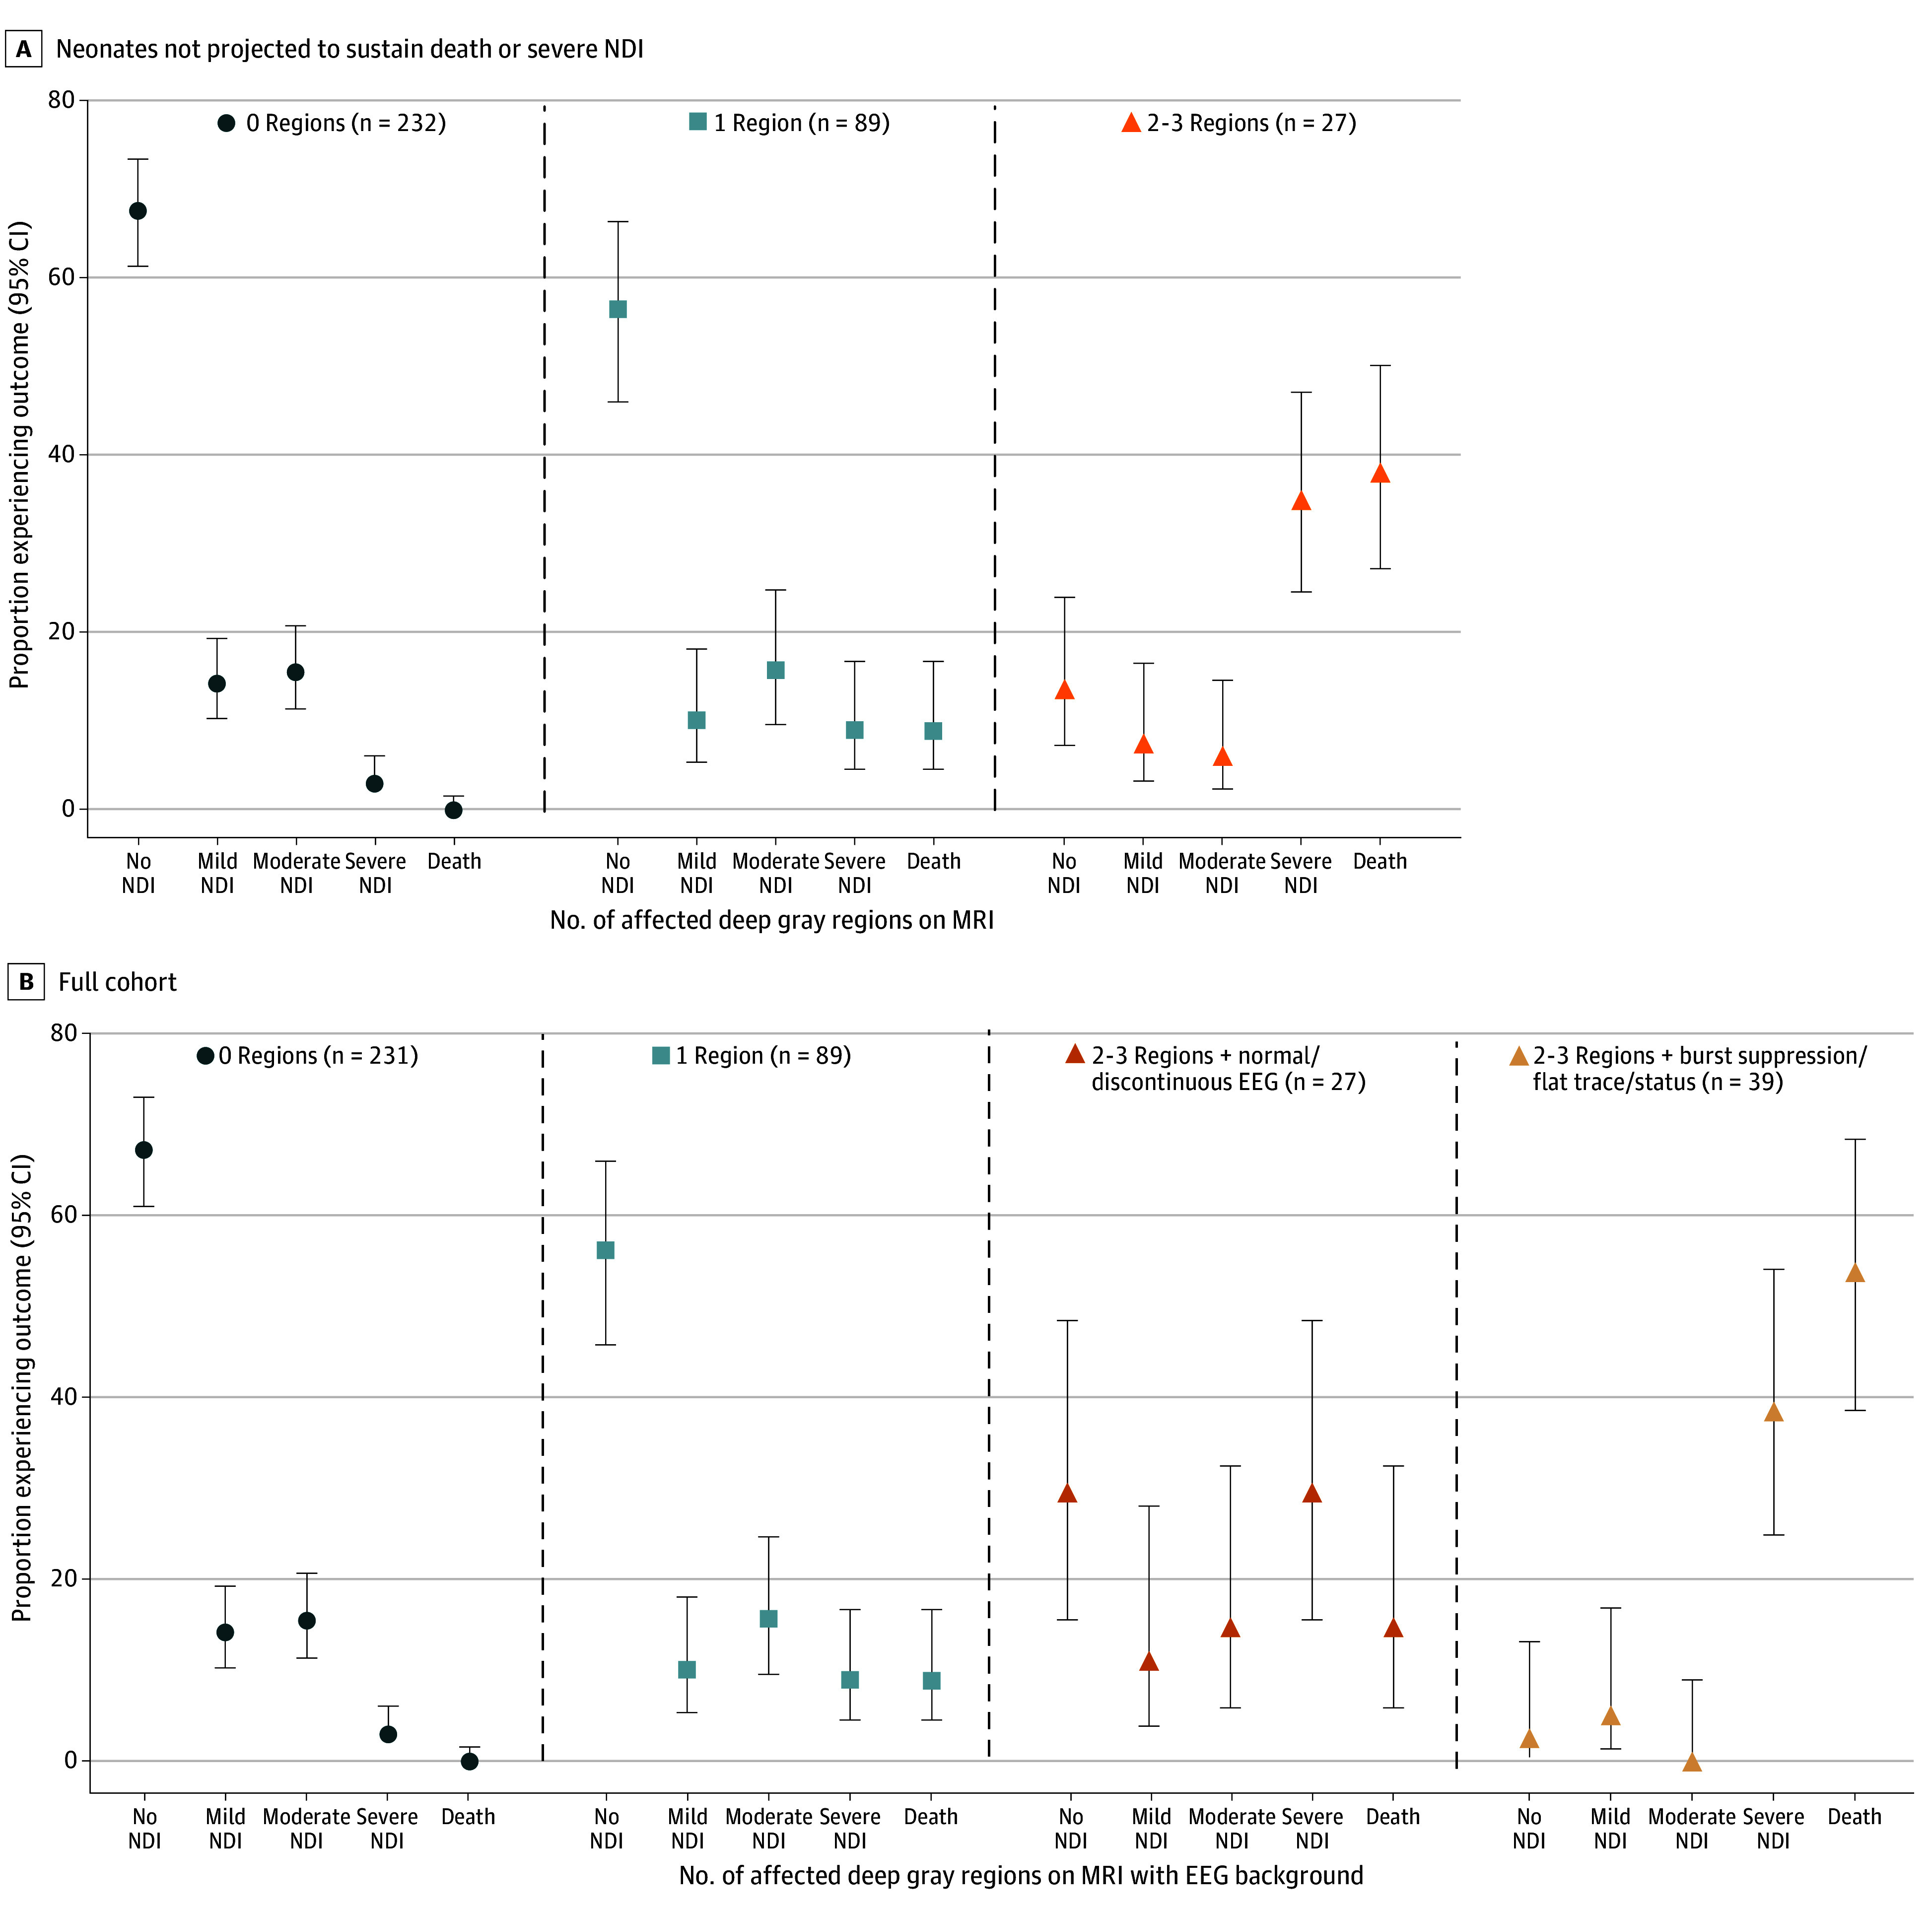
In panel A, a total of 349 neonates who were alive after cooling and magnetic resonance imaging and not predicted to sustain death or severe NDI by number of deep gray regions (thalamus, caudate, globus pallidus/putamen) with injury on T1, T2, or diffusion-weighted imaging; B, includes the full cohort and adds 24-hour electroencephalogram (EEG) background results.
Figure 3. Neurodevelopment Among Neonates Not Predicted to Sustain Death or Severe Neurodevelopmental Disability (NDI) by Electroencephalography (EEG) Throughout Cooling.
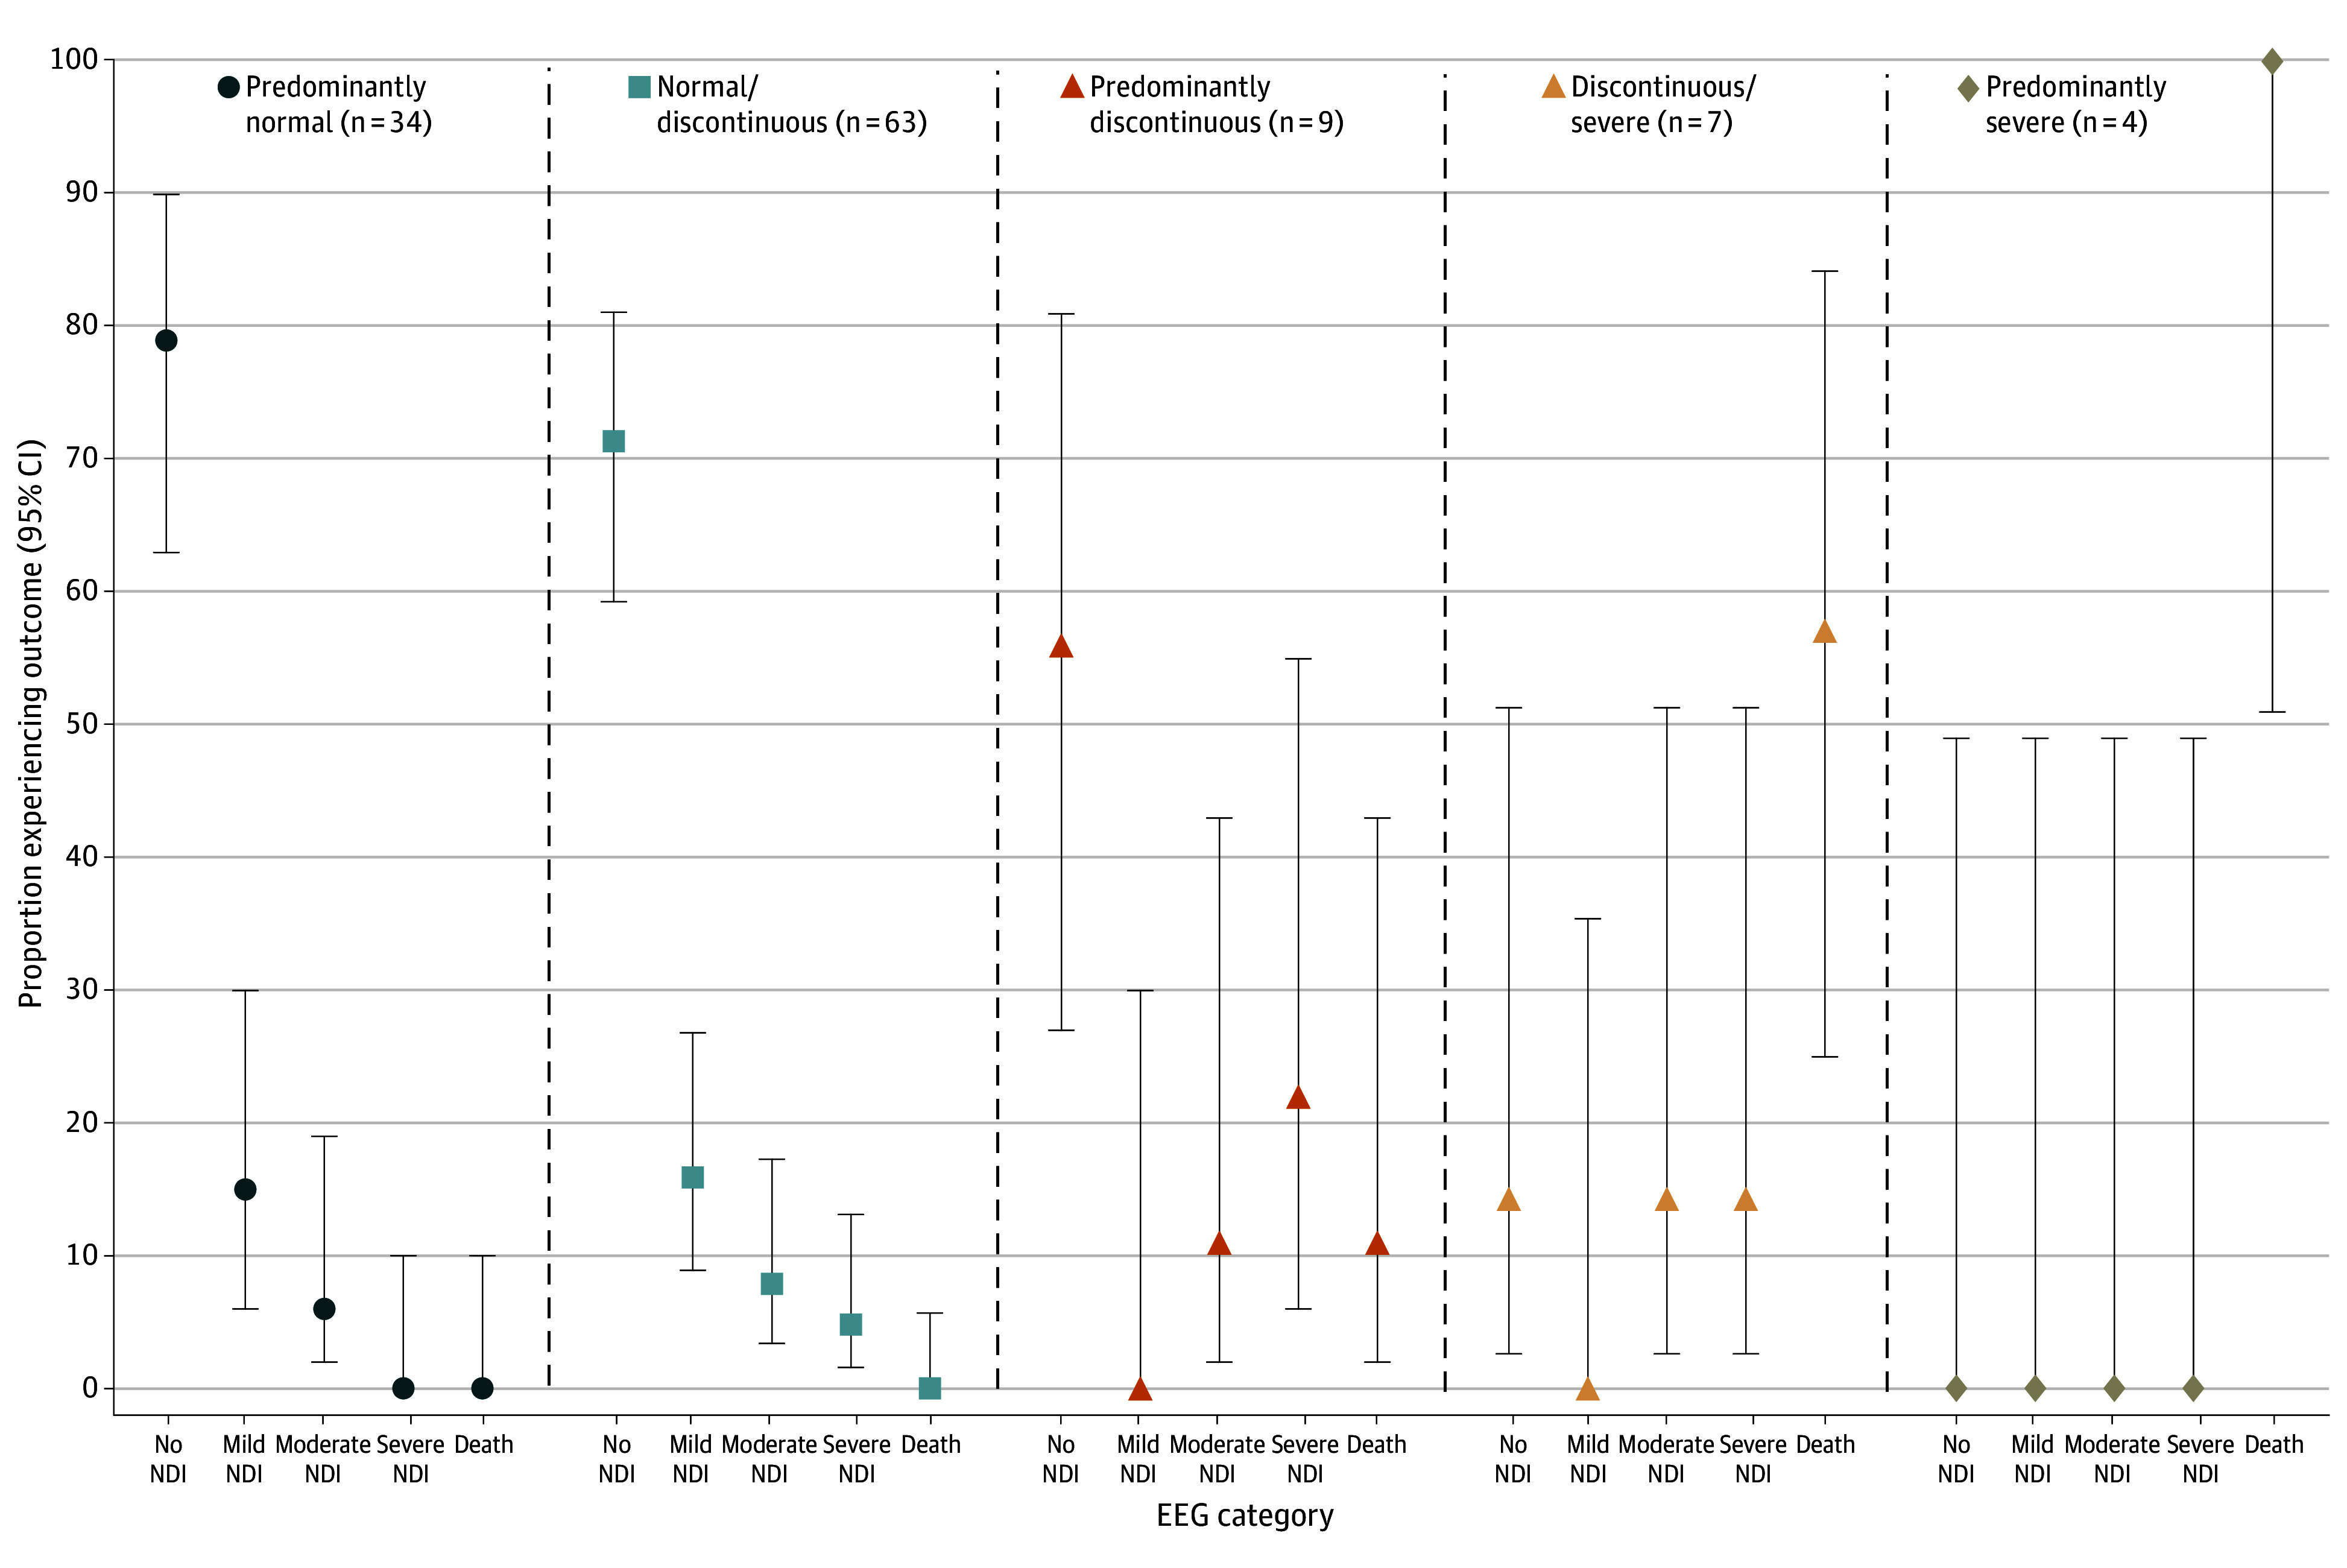
A total of 117 neonates are included in the cohort not predicted to sustain death or severe NDI.
Sensitivity Analyses
Three sensitivity analyses of the postcooling model used the training and validation datasets combined: MRI before vs after day 7 (144 hours) among neonates who were not predicted to experience death or severe NDI by the 24-hour model, infants who survived to the end of cooling (ie, including those with predicted death or severe NDI in the 24-hour model, using complete MRI data only without imputation). An additional sensitivity analysis included only the infants who survived to hospital discharge from the HEAL and UK datasets. Specificity and positive predictive value were between 88% and 100% in the sensitivity analyses (eTable 3 in Supplement 1).
External Validation
In the external validation dataset, 34 or 365 died (9.3%) and 37 had severe NDI (10.1%). Specificity was above 97.6% in both the 24-hour and postcooling models, whereas PPV was 46.2% in the 24-hour model and 83.3% in the postcooling model (Table 2).
Discussion
Using data from the HEAL trial, we found that several clinically available findings, when used in combination, provided excellent specificity and positive predictive value for death or severe NDI at age 2 years in infants with perinatal HIE treated with hypothermia. Our models improve upon prior studies by using an agnostic recursive partitioning approach in a large, multicenter dataset to develop a comprehensive predictive model that combines clinical, neurophysiology, and neuroimaging factors at 2 distinct and clinically relevant time points. The models retained excellent model metrics in an independent dataset, particularly for the postcooling model, suggesting strong external validity.
Although numerous prior studies have identified factors that are associated with adverse neurodevelopmental outcomes in neonates with HIE,2,3,4,5,6,7,8,9,10,11,12,13,14,15,16,17,18,19,20,21,22,23,24,25,26 few have attempted to combine clinical, neurophysiology, and imaging factors to develop a validated, comprehensive, and simple to interpret predictive model that can be used at the bedside. Our recursive partitioning model identified that a severely abnormal EEG along with low pH and 5-minute Apgar of 0 (variables that are widely available in the first 24 hours after birth) and MRI injury to at least 2 deep gray regions (findings that are typically available within 4-5 days of birth), had excellent specificity and PPV for death or severe NDI.
The association between EEG metrics and neurodevelopmental outcome in neonates with HIE has been recognized for decades.39,40,41,42 In a 2023 study,16 we showed that severity and duration of EEG background abnormalities are associated with neurodevelopmental outcome. Multiple prior studies have shown that MRI is associated with adverse outcomes in infancy and childhood.17,37,38,43,44,45,46 The automated model selected injury to the deep gray nuclei but not white matter or cortical injury. A watershed pattern of injury typically manifests clinically later in development as impaired language and cognition,47,48 and so injury to the watershed areas including white matter and cortex may be more relevant to prediction models for school age or adolescent outcomes.
The models were not designed to predict children with no or mild NDI. However, we present outcomes stratified by MRI and EEG severity, which show that between 75% and 95% had normal neurodevelopment or only mild NDI at age 2 years if MRI or EEG were normal or only mildly abnormal (ie, without injury to or with only 1 area of affected area of the deep gray nuclei; normal or discontinuous EEG). This information may be reassuring to families.
Death in the intensive care unit (ICU) can involve a decision not to initiate or to withdraw life-sustaining treatment in the context of anticipated poor neurologic prognosis.49,50,51 An inherent limitation of any model predicting death is the possibility of a self-fulfilling prophecy, as life-sustaining treatment may be withdrawn for patients with severe prognostic indicators.52 Although we speculate that neonates in this cohort with severely abnormal EEG or MRI injury who died following withdrawal of life-sustaining treatment would have sustained severe NDI if they were maintained on life-sustaining treatments, we cannot be certain. Also, the composite outcome of death or severe NDI weights death and severe NDI equally, despite each component being valued differently by many clinicians and parents.53,54,55
Limitations
Although we present models with high internal and external validation, our results are not without limitations. First, we developed models to optimize specificity rather than selecting models that balance sensitivity and specificity. The decision was made to allow the bedside clinician to provide a likelihood of death or disability with a high degree of certainty, although this approach limits the ability to counsel families about the anticipated outcome among children without the risk factors identified in the models, particularly at 24 hours where sensitivity was low. For these children, we provide guidance regarding the likelihood and severity of NDI based on EEG and MRI results (Figures 2 and 3). Second, our data were bound by exclusion criteria for the parent HEAL Trial (particularly anticipated transition to palliative care). The high specificity and PPV of the postcooling model in the external validation dataset suggests this limitation had a negligible impact on model validity. Third, the external validation data element definition for aEEG was different from the HEAL Trial (external validation dataset used only aEEG within the first 6 hours after birth rather than the first 24 hours), which may account for lower specificity since aEEG recovery during this time is associated with a favorable prognosis among neonates who undergo hypothermia.56,57 Fourth, sensitivity analyses combined the training and validation datasets. However, as these analyses pertain to factors that might affect MRI in the postcooling model and performance of the postcooling model was very similar in the training and validation datasets, combining them is unlikely to have resulted in an artificial improvement in performance in the sensitivity analyses. Fifth, only the results from the initial 24 hours of EEG were available for the recursive partitioning models. While some studies have shown that 48-hour EEG is most predictive for neurodevelopment,58 we recently showed that 24-hour EEG is also highly associated with death and severe disability.16 Multiday EEG results may be important to further refine the models for death or severe NDI and to develop predictive models for mild or moderate disability. Sixth, MR spectroscopy (MRS) may improve model metrics.18 However, since MRS is not routinely acquired, we did not include it in the model. Also, the MRI scoring system did not assess the exact location within deep gray nuclei, nor differentiate between whether signal abnormality is thought to be due to primary injury or secondary degeneration. This led to a small number of false positive cases. Expert neuroradiology interpretation remains important. Finally, what is considered severe NDI may differ based on clinician and family experience, culture, and values. For this study, severe NDI was defined a priori according to definitions developed for the HEAL trial.28
The predictive models in this paper should not be used as definitive forecast of an individual child’s developmental outcome. Rather, they are 1 tool that can facilitate prognostic communication within the health care team and with families. Prognostic models should be used within a clear communication strategy, for example, the ALIGN framework and our-HOPE, which were developed for use with families of infants with neurologic conditions.59,60 Communication with families must also acknowledge that developmental prediction using data collected during the neonatal admission is inherently uncertain. Increasing evidence points to the importance of the home environment for neurodevelopment; intensive, targeted, and goal-directed therapies can impact developmental trajectory in infants at risk for disability.61 Furthermore, socioeconomic status, parental language preference, parent well-being, and parental education are associated with brain growth and development,62 and neurodevelopmental outcome63,64 in diverse high-risk populations. Altogether, these data suggest that neurodevelopmental outcome is, to at least some degree, modifiable, and every effort must be made to enable a developmentally supportive environment.
Conclusions
In this prognostic study, we developed a predictive model with high specificity and PPV for death or severe NDI using simple, readily available clinical, EEG, and MRI results in 2 independent datasets. These models may be used to counsel families of newborns with HIE about anticipated death or severe NDI within days after birth.
eTable 1. Variables Considered for Inclusion in the 24h and Postcooling Models
eTable 2. Outcome at Age 2 Years for All Surviving Infants Who Were Predicted to Have Death or Severe NDI for the 24h Model and the Postcooling Model
eTable 3. Sensitivity Analyses to Evaluate Test Metrics for the Postcooling Model Based on Timing of MRI (Within or After 7 Days After Birth), Ignoring the 24 Hours Model (ie, Including All Neonates Who Survived to the End of Cooling), Using Only the Available MRI Data Without Imputation, and Including Only the Infants That Survived to Hospital Discharge
eFigure 1. HEAL Trial Candidate Prediction Variable Selection Flow Diagram
eFigure 2. Imaging From a False Positive MRI Results
Data Sharing Statement
References
- 1.Wu Y. Clinical features, diagnosis, and treatment of neonatal encephalopathy. UpToDate. Updated January 30, 2024. Accessed July 29, 2024. https://www.uptodate.com/contents/clinical-features-diagnosis-and-treatment-of-neonatal-encephalopathy
- 2.Calabrese E, Wu Y, Scheffler AW, et al. Correlating quantitative MRI-based apparent diffusion coefficient metrics with 24-month neurodevelopmental outcomes in neonates from the HEAL Trial. Radiology. 2023;308(3):e223262. doi: 10.1148/radiol.223262 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.Temko A, Doyle O, Murray D, Lightbody G, Boylan G, Marnane W. Multimodal predictor of neurodevelopmental outcome in newborns with hypoxic-ischaemic encephalopathy. Comput Biol Med. 2015;63:169-177. doi: 10.1016/j.compbiomed.2015.05.017 [DOI] [PubMed] [Google Scholar]
- 4.O’Sullivan MP, Looney AM, Moloney GM, et al. Validation of altered umbilical cord blood microRNA expression in neonatal hypoxic-ischemic encephalopathy. JAMA Neurol. 2019;76(3):333-341. doi: 10.1001/jamaneurol.2018.4182 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 5.Juul SE, Voldal E, Comstock BA, et al. ; HEAL consortium . Association of high-dose erythropoietin with circulating biomarkers and neurodevelopmental outcomes among neonates with hypoxic ischemic encephalopathy: a secondary analysis of the HEAL randomized clinical trial. JAMA Netw Open. 2023;6(7):e2322131. doi: 10.1001/jamanetworkopen.2023.22131 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 6.Presacco A, Chirumamilla VC, Vezina G, et al. Prediction of outcome of hypoxic-ischemic encephalopathy in newborns undergoing therapeutic hypothermia using heart rate variability. J Perinatol. 2024;44(4):521-527. doi: 10.1038/s41372-023-01754-w [DOI] [PMC free article] [PubMed] [Google Scholar]
- 7.Langeslag J, Onland W, Visser D, et al. ; PharmaCool Study Group . Predictive performance of multiple organ dysfunction in asphyxiated newborns treated with therapeutic hypothermia on 24-month outcome: a cohort study. Arch Dis Child Fetal Neonatal Ed. 2023;109(1):41-45. doi: 10.1136/archdischild-2023-325585 [DOI] [PubMed] [Google Scholar]
- 8.Kelly R, Ramaiah SM, Sheridan H, et al. Dose-dependent relationship between acidosis at birth and likelihood of death or cerebral palsy. Arch Dis Child Fetal Neonatal Ed. 2018;103(6):F567-F572. doi: 10.1136/archdischild-2017-314034 [DOI] [PubMed] [Google Scholar]
- 9.Persson M, Razaz N, Tedroff K, Joseph KS, Cnattingius S. Five and 10 minute Apgar scores and risks of cerebral palsy and epilepsy: population based cohort study in Sweden. BMJ. 2018;360:k207. doi: 10.1136/bmj.k207 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 10.Murray DM, Boylan GB, Fitzgerald AP, Ryan CA, Murphy BP, Connolly S. Persistent lactic acidosis in neonatal hypoxic-ischaemic encephalopathy correlates with EEG grade and electrographic seizure burden. Arch Dis Child Fetal Neonatal Ed. 2008;93(3):F183-F186. doi: 10.1136/adc.2006.100800 [DOI] [PubMed] [Google Scholar]
- 11.Shankaran S, Laptook AR, Tyson JE, et al. ; Eunice Kennedy Shriver National Institute of Child Health and Human Development Neonatal Research Network . Evolution of encephalopathy during whole body hypothermia for neonatal hypoxic-ischemic encephalopathy. J Pediatr. 2012;160(4):567-572.e3. doi: 10.1016/j.jpeds.2011.09.018 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 12.Mietzsch U, Kolnik SE, Wood TR, et al. ; HEAL Trial Study Group . Evolution of the Sarnat exam and association with 2-year outcomes in infants with moderate or severe hypoxic-ischaemic encephalopathy: a secondary analysis of the HEAL Trial. Arch Dis Child Fetal Neonatal Ed. 2024;109(3):308-316. doi: 10.1136/archdischild-2023-326102 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 13.Chalak LF, Adams-Huet B, Sant’Anna G. A total Sarnat score in mild hypoxic-ischemic encephalopathy can detect infants at higher risk of disability. J Pediatr. 2019;214:217-221.e1. doi: 10.1016/j.jpeds.2019.06.026 [DOI] [PubMed] [Google Scholar]
- 14.Thorsen P, Jansen-van der Weide MC, Groenendaal F, et al. The Thompson Encephalopathy Score and short-term outcomes in asphyxiated newborns treated with therapeutic hypothermia. Pediatr Neurol. 2016;60:49-53. doi: 10.1016/j.pediatrneurol.2016.03.014 [DOI] [PubMed] [Google Scholar]
- 15.Kharoshankaya L, Stevenson NJ, Livingstone V, et al. Seizure burden and neurodevelopmental outcome in neonates with hypoxic-ischemic encephalopathy. Dev Med Child Neurol. 2016;58(12):1242-1248. doi: 10.1111/dmcn.13215 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16.Glass HC, Numis AL, Comstock BA, et al. Association of EEG background and neurodevelopmental outcome in neonates with hypoxic-ischemic encephalopathy receiving hypothermia. Neurology. 2023;101(22):e2223-e2233. doi: 10.1212/WNL.0000000000207744 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 17.Bach AM, Fang AY, Bonifacio S, et al. Early magnetic resonance imaging predicts 30-month outcomes after therapeutic hypothermia for neonatal encephalopathy. J Pediatr. 2021;238:94-101.e1. doi: 10.1016/j.jpeds.2021.07.003 [DOI] [PubMed] [Google Scholar]
- 18.Thayyil S, Chandrasekaran M, Taylor A, et al. Cerebral magnetic resonance biomarkers in neonatal encephalopathy: a meta-analysis. Pediatrics. 2010;125(2):e382-e395. doi: 10.1542/peds.2009-1046 [DOI] [PubMed] [Google Scholar]
- 19.Mastrangelo M, Di Marzo G, Chiarotti F, et al. Early post-cooling brain magnetic resonance for the prediction of neurodevelopmental outcome in newborns with hypoxic-ischemic encephalopathy. J Pediatr Neurosci. 2019;14(4):191-202. doi: 10.4103/jpn.JPN_25_19 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 20.Chang PD, Chow DS, Alber A, Lin YK, Youn YA. Predictive values of location and volumetric MRI injury patterns for neurodevelopmental outcomes in hypoxic-ischemic encephalopathy neonates. Brain Sci. 2020;10(12):991. doi: 10.3390/brainsci10120991 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 21.Wu YW, Wisnowski JL, Glass HC, et al. Advancing brain MRI as a prognostic indicator in hypoxic-ischemic encephalopathy. Pediatr Res. 2024;95(3):587-589. [DOI] [PubMed] [Google Scholar]
- 22.Steiner M, Urlesberger B, Giordano V, et al. Outcome prediction in neonatal hypoxic-ischaemic encephalopathy using neurophysiology and neuroimaging. Neonatology. 2022;119(4):483-493. doi: 10.1159/000524751 [DOI] [PubMed] [Google Scholar]
- 23.Huang HZ, Hu XF, Wen XH, Yang LQ. Serum neuron-specific enolase, magnetic resonance imaging, and electrophysiology for predicting neurodevelopmental outcomes of neonates with hypoxic-ischemic encephalopathy: a prospective study. BMC Pediatr. 2022;22(1):290. doi: 10.1186/s12887-022-03329-8 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 24.Chiang MC, Lien R, Chu SM, et al. Serum lactate, brain magnetic resonance imaging and outcome of neonatal hypoxic ischemic encephalopathy after therapeutic hypothermia. Pediatr Neonatol. 2016;57(1):35-40. doi: 10.1016/j.pedneo.2015.04.008 [DOI] [PubMed] [Google Scholar]
- 25.Ancora G, Maranella E, Grandi S, et al. Early predictors of short term neurodevelopmental outcome in asphyxiated cooled infants. A combined brain amplitude integrated electroencephalography and near infrared spectroscopy study. Brain Dev. 2013;35(1):26-31. doi: 10.1016/j.braindev.2011.09.008 [DOI] [PubMed] [Google Scholar]
- 26.Estiphan T, Sturza J, Shellhaas RA, Carlson MD. A novel clinical risk scoring system for neurodevelopmental outcomes among survivors of neonatal hypoxic-ischemic encephalopathy (HIE). Pediatr Neonatol. 2024;65(4):354-358. doi: 10.1016/j.pedneo.2023.07.006 [DOI] [PubMed] [Google Scholar]
- 27.Langeslag JF, Berendse K, Daams JG, et al. Clinical prediction models and predictors for death or adverse neurodevelopmental outcome in term newborns with hypoxic-ischemic encephalopathy: a systematic review of the literature. Neonatology. 2023;120(6):776-788. doi: 10.1159/000530411 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 28.Wu YW, Comstock BA, Gonzalez FF, et al. ; HEAL Consortium . Trial of erythropoietin for hypoxic-ischemic encephalopathy in newborns. N Engl J Med. 2022;387(2):148-159. doi: 10.1056/NEJMoa2119660 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 29.Juul SE, Comstock BA, Heagerty PJ, et al. High-Dose Erythropoietin for Asphyxia and Encephalopathy (HEAL): a randomized controlled trial—background, aims, and study protocol. Neonatology. 2018;113(4):331-338. doi: 10.1159/000486820 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 30.Tsuchida TN, Wusthoff CJ, Shellhaas RA, et al. ; American Clinical Neurophysiology Society Critical Care Monitoring Committee . American clinical neurophysiology society standardized EEG terminology and categorization for the description of continuous EEG monitoring in neonates: report of the American Clinical Neurophysiology Society critical care monitoring committee. J Clin Neurophysiol. 2013;30(2):161-173. doi: 10.1097/WNP.0b013e3182872b24 [DOI] [PubMed] [Google Scholar]
- 31.Wisnowski JL, Bluml S, Panigrahy A, et al. ; HEAL Study Group . Integrating neuroimaging biomarkers into the multicentre, high-dose erythropoietin for asphyxia and encephalopathy (HEAL) trial: rationale, protocol and harmonisation. BMJ Open. 2021;11(4):e043852. doi: 10.1136/bmjopen-2020-043852 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 32.Trivedi SB, Vesoulis ZA, Rao R, et al. A validated clinical MRI injury scoring system in neonatal hypoxic-ischemic encephalopathy. Pediatr Radiol. 2017;47(11):1491-1499. doi: 10.1007/s00247-017-3893-y [DOI] [PMC free article] [PubMed] [Google Scholar]
- 33.Kuban KC, Allred EN, O’Shea M, Paneth N, Pagano M, Leviton A; ELGAN Study Cerebral Palsy-Algorithm Group . An algorithm for identifying and classifying cerebral palsy in young children. J Pediatr. 2008;153(4):466-472. doi: 10.1016/j.jpeds.2008.04.013 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 34.Palisano R, Rosenbaum P, Walter S, Russell D, Wood E, Galuppi B. Development and reliability of a system to classify gross motor function in children with cerebral palsy. Dev Med Child Neurol. 1997;39(4):214-223. doi: 10.1111/j.1469-8749.1997.tb07414.x [DOI] [PubMed] [Google Scholar]
- 35.Hothorn T, Hornik K, Zeileis A. Unbiased Recursive Partitioning: A Conditional Interference Framework. J Comput Graph Stat. 2006;15(3):651-674. doi: 10.1198/106186006X133933 [DOI] [Google Scholar]
- 36.Mercaldo ND, Lau KF, Zhou XH. Confidence intervals for predictive values with an emphasis to case-control studies. Stat Med. 2007;26(10):2170-2183. doi: 10.1002/sim.2677 [DOI] [PubMed] [Google Scholar]
- 37.Rutherford M, Ramenghi LA, Edwards AD, et al. Assessment of brain tissue injury after moderate hypothermia in neonates with hypoxic-ischaemic encephalopathy: a nested substudy of a randomised controlled trial. Lancet Neurol. 2010;9(1):39-45. doi: 10.1016/S1474-4422(09)70295-9 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 38.Thoresen M, Jary S, Walløe L, et al. MRI combined with early clinical variables are excellent outcome predictors for newborn infants undergoing therapeutic hypothermia after perinatal asphyxia. EClinicalMedicine. 2021;36:100885. doi: 10.1016/j.eclinm.2021.100885 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 39.Pressler RM, Boylan GB, Morton M, Binnie CD, Rennie JM. Early serial EEG in hypoxic ischaemic encephalopathy. Clin Neurophysiol. 2001;112(1):31-37. doi: 10.1016/S1388-2457(00)00517-4 [DOI] [PubMed] [Google Scholar]
- 40.Selton D, André M. Prognosis of hypoxic-ischaemic encephalopathy in full-term newborns–value of neonatal electroencephalography. Neuropediatrics. 1997;28(5):276-280. doi: 10.1055/s-2007-973714 [DOI] [PubMed] [Google Scholar]
- 41.Murray DM, Boylan GB, Ryan CA, Connolly S. Early EEG findings in hypoxic-ischemic encephalopathy predict outcomes at 2 years. Pediatrics. 2009;124(3):e459-e467. doi: 10.1542/peds.2008-2190 [DOI] [PubMed] [Google Scholar]
- 42.Hamelin S, Delnard N, Cneude F, Debillon T, Vercueil L. Influence of hypothermia on the prognostic value of early EEG in full-term neonates with hypoxic ischemic encephalopathy. Neurophysiol Clin. 2011;41(1):19-27. doi: 10.1016/j.neucli.2010.11.002 [DOI] [PubMed] [Google Scholar]
- 43.Barkovich AJ, Hajnal BL, Vigneron D, et al. Prediction of neuromotor outcome in perinatal asphyxia: evaluation of MR scoring systems. AJNR Am J Neuroradiol. 1998;19(1):143-149. [PMC free article] [PubMed] [Google Scholar]
- 44.Barkovich AJ, Miller SP, Bartha A, et al. MR imaging, MR spectroscopy, and diffusion tensor imaging of sequential studies in neonates with encephalopathy. AJNR Am J Neuroradiol. 2006;27(3):533-547. [PMC free article] [PubMed] [Google Scholar]
- 45.Wu YW, Monsell SE, Glass HC, et al. How well does neonatal neuroimaging correlate with neurodevelopmental outcomes in infants with hypoxic-ischemic encephalopathy? Pediatr Res. 2023;94(3):1018-1025. doi: 10.1038/s41390-023-02510-8 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 46.Lambing H, Gano D, Li Y, et al. Using neonatal magnetic resonance imaging to predict gross motor disability at four years in term-born children with neonatal encephalopathy. Pediatr Neurol. 2023;144:50-55. doi: 10.1016/j.pediatrneurol.2023.03.011 [DOI] [PubMed] [Google Scholar]
- 47.Steinman KJ, Gorno-Tempini ML, Glidden DV, et al. Neonatal watershed brain injury on magnetic resonance imaging correlates with verbal IQ at 4 years. Pediatrics. 2009;123(3):1025-1030. doi: 10.1542/peds.2008-1203 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 48.Lee BL, Gano D, Rogers EE, et al. Long-term cognitive outcomes in term newborns with watershed injury caused by neonatal encephalopathy. Pediatr Res. 2022;92(2):505-512. doi: 10.1038/s41390-021-01526-2 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 49.Lemmon ME, Boss RD, Bonifacio SL, Foster-Barber A, Barkovich AJ, Glass HC. Characterization of death in neonatal encephalopathy in the hypothermia era. J Child Neurol. 2017;32(4):360-365. doi: 10.1177/0883073816681904 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 50.Lemmon ME, Bonifacio SL, Shellhaas RA, et al. ; Neonatal Seizure Registry . Characterization of death in infants with neonatal seizures. Pediatr Neurol. 2020;113:21-25. doi: 10.1016/j.pediatrneurol.2020.08.002 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 51.Vassar R, Mehta N, Epps L, Jiang F, Amorim E, Wietstock S. Mortality and timing of withdrawal of life-sustaining therapies after out-of-hospital cardiac arrest: two-center retrospective pediatric cohort study. Pediatric Crit Care Med. 2024;25(3):241-249. doi: 10.1097/PCC.0000000000003412 [DOI] [PubMed] [Google Scholar]
- 52.Hemphill JC III, White DB. Clinical nihilism in neuroemergencies. Emerg Med Clin North Am. 2009;27(1):27-37. doi: 10.1016/j.emc.2008.08.009 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 53.Lam HS, Wong SP, Liu FY, Wong HL, Fok TF, Ng PC. Attitudes toward neonatal intensive care treatment of preterm infants with a high risk of developing long-term disabilities. Pediatrics. 2009;123(6):1501-1508. doi: 10.1542/peds.2008-2061 [DOI] [PubMed] [Google Scholar]
- 54.Janvier A, Farlow B, Baardsnes J, Pearce R, Barrington KJ. Measuring and communicating meaningful outcomes in neonatology: a family perspective. Semin Perinatol. 2016;40(8):571-577. doi: 10.1053/j.semperi.2016.09.009 [DOI] [PubMed] [Google Scholar]
- 55.Lemmon ME, Ubel PA, Janvier A. Estimating neurologic prognosis in children: high stakes, poor data. JAMA Neurol. 2019;76(8):879-880. doi: 10.1001/jamaneurol.2019.1157 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 56.Thoresen M, Hellström-Westas L, Liu X, de Vries LS. Effect of hypothermia on amplitude-integrated electroencephalogram in infants with asphyxia. Pediatrics. 2010;126(1):e131-e139. doi: 10.1542/peds.2009-2938 [DOI] [PubMed] [Google Scholar]
- 57.Nash KB, Bonifacio SL, Glass HC, et al. Video-EEG monitoring in newborns with hypoxic-ischemic encephalopathy treated with hypothermia. Neurology. 2011;76(6):556-562. doi: 10.1212/WNL.0b013e31820af91a [DOI] [PMC free article] [PubMed] [Google Scholar]
- 58.Chandrasekaran M, Chaban B, Montaldo P, Thayyil S. Predictive value of amplitude-integrated EEG (aEEG) after rescue hypothermic neuroprotection for hypoxic ischemic encephalopathy: a meta-analysis. J Perinatol. 2017;37(6):684-689. doi: 10.1038/jp.2017.14 [DOI] [PubMed] [Google Scholar]
- 59.Lemmon ME, Barks MC, Bansal S, et al. The ALIGN Framework: a parent-informed approach to prognostic communication for infants with neurologic conditions. Neurology. 2023;100(8):e800-e807. doi: 10.1212/WNL.0000000000201600 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 60.Racine E, Bell E, Farlow B, et al. The ‘ouR-HOPE’ approach for ethics and communication about neonatal neurological injury. Dev Med Child Neurol. 2017;59(2):125-135. doi: 10.1111/dmcn.13343 [DOI] [PubMed] [Google Scholar]
- 61.Novak I, Morgan C, Fahey M, et al. State of the Evidence Traffic Lights 2019: systematic review of interventions for preventing and treating children with cerebral palsy. Curr Neurol Neurosci Rep. 2020;20(2):3. doi: 10.1007/s11910-020-1022-z [DOI] [PMC free article] [PubMed] [Google Scholar]
- 62.Leijser LM, Siddiqi A, Miller SP. Imaging evidence of the effect of socio-economic status on brain structure and development. Semin Pediatr Neurol. 2018;27:26-34. doi: 10.1016/j.spen.2018.03.004 [DOI] [PubMed] [Google Scholar]
- 63.Benavente-Fernández I, Siddiqi A, Miller SP. Socioeconomic status and brain injury in children born preterm: modifying neurodevelopmental outcome. Pediatr Res. 2020;87(2):391-398. doi: 10.1038/s41390-019-0646-7 [DOI] [PubMed] [Google Scholar]
- 64.Guez-Barber D, Eisch AJ, Cristancho AG. Developmental brain injury and social determinants of health: opportunities to combine preclinical models for mechanistic insights into recovery. Dev Neurosci. 2023;45(5):255-267. doi: 10.1159/000530745 [DOI] [PMC free article] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Supplementary Materials
eTable 1. Variables Considered for Inclusion in the 24h and Postcooling Models
eTable 2. Outcome at Age 2 Years for All Surviving Infants Who Were Predicted to Have Death or Severe NDI for the 24h Model and the Postcooling Model
eTable 3. Sensitivity Analyses to Evaluate Test Metrics for the Postcooling Model Based on Timing of MRI (Within or After 7 Days After Birth), Ignoring the 24 Hours Model (ie, Including All Neonates Who Survived to the End of Cooling), Using Only the Available MRI Data Without Imputation, and Including Only the Infants That Survived to Hospital Discharge
eFigure 1. HEAL Trial Candidate Prediction Variable Selection Flow Diagram
eFigure 2. Imaging From a False Positive MRI Results
Data Sharing Statement
