



Abstract
Cardiac allograft vasculopathy (CAV) is a type of coronary artery disease unique to heart transplant recipients that can result from chronic rejection of the transplanted heart. CAV is a major cause of morbidity and mortality after the first year of transplantation. Both immune and nonimmune mechanisms contribute to the initiation and progression of CAV and result in intimal thickening, fibrosis with luminal stenosis, chronic myocardial ischemia and eventual graft failure. Recent advances in imaging modalities—including invasive intracoronary imaging and noninvasive imaging with cardiac positron emission tomography—have improved the early detection of CAV and may allow for optimization of CAV-targeted therapies to reduce CAV progression and ultimately preserve graft function.
Keywords: heart transplant, rejection, vasculopathy, mTORi, coronary angiography, IVUS, PET
Introduction
Cardiac allograft vasculopathy (CAV), coronary disease unique to heart transplant recipients, is characterized by progressive fibroproliferative changes to the coronary vasculature. Both immune and nonimmune mechanisms contribute to endothelial damage, vascular fibrosis, and vascular smooth muscle hyperplasia. This ultimately leads to luminal stenosis and subsequently myocardial ischemia, systolic and diastolic dysfunction, and even death.
CAV remains a significant cause of mortality and graft failure beyond the first year after transplantation, and progression of CAV portends increased risk for mortality and the need for heart re-transplantation. Therefore, early detection of CAV is paramount as modified immunosuppressive regimens that include antiproliferative agents can reduce progression of established CAV. Invasive coronary angiography with intracoronary imaging remains the gold standard for the diagnosis of CAV. However, advances in other imaging modalities including cardiac positron emission tomography and cardiac magnetic resonance imaging provide noninvasive means to detect CAV and have technical characteristics that may allow for early identification of CAV.
Epidemiology and Risk Factors
The incidence of cardiac allograft vasculopathy increases steadily post-transplantation, with an occurrence of nearly 10% at 1 year, 30% at 5 years, and 50% at 10 years after transplant.1 Presence of CAV is associated with lower long-term post-transplant survival.1 Overall, CAV remains a leading cause of mortality for transplant patients after 1 year, with CAV and late graft failure as the primary cause of mortality after 5 to 10 years followed by malignancy and infection.1,2
Multiple factors influence the development and progression of cardiac allograft vasculopathy; these include both immune and nonimmune risk factors.3 Immune risk factors include recurrent cellular and antibody-mediated rejection, presence of donor-specific antibodies, and cytomegalovirus infection. Donor-related risk factors include donor age and ischemia-reperfusion injury to the transplant heart.4 Nonimmune risk factors include those traditionally associated with coronary artery disease, including hypertension, hyperlipidemia, obesity, smoking, and diabetes, all of which are associated with vascular endothelial cell injury (Figure 1).5
Figure 1.
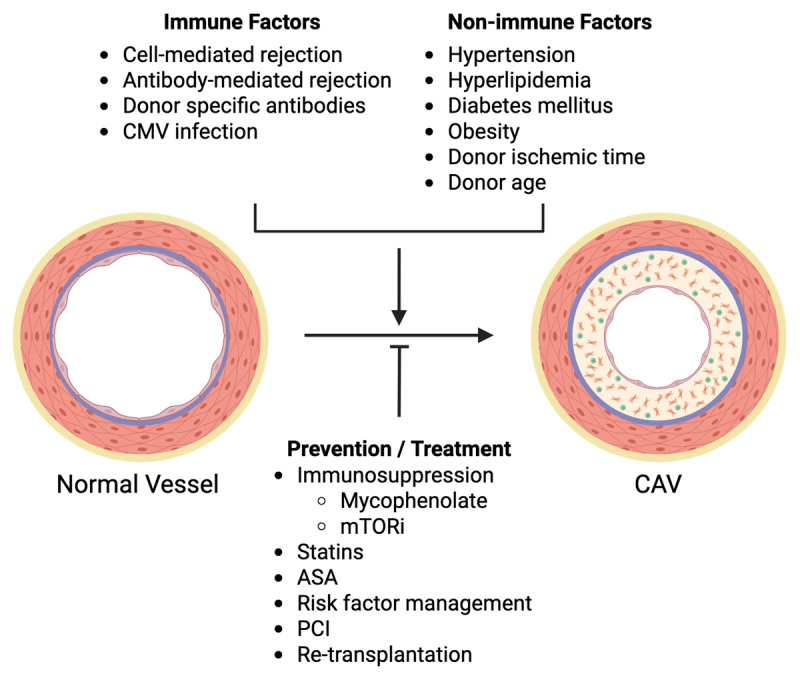
Risk factors and treatment of cardiac allograft vasculopathy. Multiple immune risk factors and nonimmune risk factors contribute to the development and progression of cardiac allograft vasculopathy (CAV), which is defined by intimal hyperplasia due to immune infiltration and immune signaling/activity, myofibroblast proliferation, and collagen deposition, ultimately restricting coronary luminal diameter. CMV: cytomegalovirus; mTORi: mammalian target of rapamycin inhibitors (including sirolimus and everolimus); ASA: aspirin; PCI: percutaneous coronary intervention. Image created with Biorender
Due to denervation of the transplanted heart and incomplete reinnervation, patients may not present with anginal chest pain despite having myocardial ischemia. Presenting symptoms may be vague and include weakness, fatigue, nausea, and abdominal pain. Patients may ultimately present with clinical heart failure—such as pulmonary edema, peripheral edema, orthopnea, and biomarkers of elevated ventricular filling pressures, with either reduced or preserved left ventricular systolic ejection fraction. More dramatic presentations may include new-onset arrhythmia, silent myocardial infarction, and sudden cardiac death. As such, surveillance imaging to detect CAV is standard post-transplantation through at least the first 4 to 5 years, although the specific screening modality may vary depending on individual institutional expertise.
Pathophysiology
Cardiac allograft vasculopathy is defined by diffuse, concentric luminal narrowing of the coronary arteries (and veins) in response to chronic endothelial cell damage, immune activation, and smooth muscle hyperplasia and fibrosis. This subsequently leads to transplant graft ischemia and dysfunction. Autopsy studies and studies of explanted hearts at the time of re-transplantation have demonstrated heterogeneous arterial pathology associated with CAV. In a study of explanted hearts from re-transplantation recipients, arteriosclerosis (intimal hyperplasia), atherosclerosis, and chronic inflammation (vasculitis) were found within epicardial arteries and their branches.6 Importantly, these different pathologies could be found within the same artery or in different arteries within the same patient, indicating a degree of heterogeneity of CAV as a disease entity and suggesting a spectrum of disease. Distinct findings of coronary artery intimal hyperplasia, inflammation (vasculitis), or intimal fibrosis were seen at autopsy,7 again indicating a spectrum of disease within CAV that would dictate different therapies to target different pathological mechanisms.
The pathogenic mechanisms driving the initiation and progression of CAV are complex, but ultimately graft endothelial cells become targets for the activated host immune system, initiating cellular and humoral immune responses that drive vascular smooth muscle proliferation and fibrosis. Immune profiling of coronary arteries with CAV demonstrated predominantly activated CD4+ Th1 memory cells with high levels of interferon-gamma (IFN-γ) production.8 In a murine model of heart transplant, genetic-mediated or antibody-mediated disruption of IFN-γ prevented vasculopathy, thus providing mechanistic plausibility for this pathway.9 Furthermore, grafting porcine or human artery segments into immunodeficient mice and subsequent treatment with IFN-γ induced intimal hyperplasia.10 Interferon-gamma activates vascular smooth muscle cell proliferation via mammalian target of rapamycin (mTOR), providing mechanistic rationale for the use of mTOR inhibitors (mTORi) in reducing CAV progression.11 Ultimately, this work and others suggest a central role of IFN-γ in the pathogenesis of CAV.12
The role of antibody-mediated immunity (ie, allosensitization with antibodies against donor proteins) in the development and progression of CAV is highlighted by the discovery that transplant recipients with CAV frequently have antibodies to donor human leukocyte antigen–DR isotype (HLA-DR) or DQ regions as well as other less common antigens.13 Engraftment of human arterial samples into immunodeficient mice and subsequent treatment with HLA antibodies provoked a CAV-like response, even in the absence of immune cells, suggesting a direct effect of autoantibodies on vascular smooth muscle cells.14 Additionally, donor-specific antibodies activate NK cells to produce IFN-γ and drive a CAV-like vasculopathy.15 Non-HLA antibodies may also drive vasculopathy preferentially in the coronary microvasculature.16 Together, these results suggest that both cellular and humoral immunity contribute to CAV pathogenesis in complex ways, and further understanding of this pathobiology may allow for targeted molecular therapies to treat CAV.
Diagnosis
Biomarkers
The identification of a biomarker that could serve as a noninvasive or non-imaging-based method for early detection of subclinical CAV and allow for optimization of medical therapy to slow progression of CAV would provide great benefit to the field. To date, no single biomarker to predict CAV has been adopted into widespread clinical practice.
Brain natriuretic peptide (BNP) and C-reactive protein (CRP) are elevated in patients with CAV; however, they are nonspecific due to other causes of ventricular pressure overload and inflammation, respectively.17,18 Multiple microRNAs, including miR-125-5p, miR-92a-3p, and miR-628-5p, were found to be predictive of CAV as they represent endothelial and vascular inflammation.19,20 Since alloimmunity is central to CAV pathogenesis, circulating cytokine levels could serve as biomarkers. A panel of circulating cytokines including IL-4, IL-6, IL-10, IL-21, IL-23, IL-31, IL-33, tumor necrosis factor alpha, IFN-γ, and soluble CD40 ligand generated a CAV prediction score that could identify patients at risk for advanced CAV.21 The clinical utility of this panel is unknown because it is unclear whether this panel can predict early, intervenable CAV, and some cytokines may not be routinely available in all pathology labs. Serum proteomics has also identified potential protein biomarkers for CAV. Fourteen proteins involved in inflammation, apoptosis, and platelet aggregation/activation were identified in patients with CAV22; four of these proteins—intercellular adhesion molecule-2, peptidylprolyl-isomerase D, SPARC/osteonectin, cwcv and kazal-like domains proteoglycan 1 (SPOCK1), and N (6)-adenine-specific DNA methyl-transferase—showed the ability to discriminate for mild-moderate CAV, suggesting these could be clinically useful indicators of early, intervenable CAV. Profiling of serum exosomal proteins may also provide biomarker evidence of CAV.23 Overall, there are currently no biomarkers that have been assessed in a prospective, randomized trial to guide targeted therapy to reduce the progression of CAV.
Coronary Angiography
Coronary angiography is considered the gold standard for surveillance and monitoring of CAV and is recommended by the International Society for Heart and Lung Transplantation (ISHLT) guidelines.24 The ISHLT CAV grading scale is based on angiographic features and allograft function, ranging from CAV0 to CAV3 with increasing severity by grade (Table 1). Grading by these standards has prognostic implications, with higher grades (CAV2-3) imposing greater risk for major adverse cardiovascular events (MACE).25 Furthermore, the presence of angiographic CAV, particularly severe CAV, portends 5-year major adverse cardiovascular events and need for re-transplantation.26 Unfortunately, standard coronary angiography lacks sufficient sensitivity to detect early CAV, particularly when compared to intracoronary imaging modalities such as intravascular ultrasound.27 Early CAV may include both luminal narrowing from vascular smooth muscle hyperplasia and fibrosis as well as outward remodeling that may limit identification of CAV on standard angiography prior to the development of severe luminal stenosis.28
Table 1.
Guideline-based grading of CAV by coronary angiography and intravascular ultrasound.
|
| ||
|---|---|---|
| CAV SEVERITY | ISHLT GRADING BY CA* | STANFORD CLASSIFICATION BY IVUS-DERIVED INTIMAL THICKNESS** |
|
| ||
| None/Minimal | CAV0: No lesion with normal allograft function | I: < 0.3 mm and < 180° |
|
| ||
| Mild | CAV1: LM < 50% or primary vessel < 70% or branch stenosis < 70% with normal allograft function | II: < 0.3 mm and > 180° |
|
| ||
| Moderate | CAV2: LM < 50% and single primary vessel > 70% or at least 2 branch vessels > 70% with normal allograft function | III: 0.3-0.5 mm or > 0.5 mm and < 180° |
|
| ||
| Severe | CAV3: LM > 50% or 2 primary vessels > 70% or branch vessels > 70% in all coronary distributions; or CAV1 or CAV2 with allograft dysfunction | IV: > 1.0 mm or > 0.5 mm and > 180° |
|
| ||
Intracoronary Imaging with Intravascular Ultrasound and Optical Coherence Tomography
Intracoronary imaging with intravascular ultrasound (IVUS) and optical coherence tomography (OCT) have emerged as invasive imaging modalities to detect CAV. While intravascular ultrasound received a guideline recommendation (class 2a) for the assessment of CAV in select patients,24 OCT remains investigational at this time, although recent data as described below may support the use of OCT to detect early CAV.
One of the major limitations of coronary angiography is reduced sensitivity in detecting early CAV due to its inability to image vessel lumen and vessel wall morphology. IVUS, however, is able to overcome this limitation, as demonstrated in a critical study comparing the sensitivity of IVUS with coronary angiography for identifying CAV. 28,29 In this study, 42 patients with angiographically normal coronary arteries had moderate-severe intimal thickening by intracoronary ultrasound, and nearly all patients had some degree of intimal thickening at 1-year post-transplantation. These results led to the creation of the Stanford Classification of CAV by intracoronary ultrasound (Table 1).
Identification of CAV by IVUS has clear prognostic implications. Two early trials demonstrated that increased intimal thickness is associated with major adverse cardiovascular events and mortality outcomes. Mehra and colleagues demonstrated that maximal intimal thickness > 0.5 mm was associated with increased risk for myocardial infarction, need for revascularization, or sudden cardiac death,30 even in the setting of angiographically normal coronary arteries. Similarly, a separate study reported that intimal thickness > 0.3 mm (measured at a mean 3.1 years post-transplant) was associated with reduced survival and reduced freedom from cardiac death or re-transplantation.31 Subsequently, a 2005 multicenter study showed that patients with progression of intimal thickness to > 0.5 mm at 1-year (compared to baseline imaging 4-6 weeks post-transplant), were more likely to experience death or graft failure, non-fatal MACE, or progression to angiographic CAV,32 and similar results were seen in a single-center study.33 While these trials were conducted in an era prior to routine use of mTORi, statin therapy, and more modern immunosuppressive agents (tacrolimus and mycophenolate), it is evident that early, progressive CAV as defined by intracardiac ultrasound is associated with worse outcomes and requires intensification of CAV-directed therapy,24 although the exact change in intimal thickness that defines early, progressive CAV in the modern immunosuppressive era may need further elucidation.28
OCT is a more recent intracoronary imaging modality that uses infrared light to image the coronary vessel wall and demonstrates improved spatial resolution when compared to IVUS.34 OCT can detect early CAV, and one small study (n = 15) suggested an intima/media ratio > 1 as a cutoff to define abnormal intimal thickening suggestive of CAV.35 More recently, a single-center study that used comprehensive anatomic/physiological phenotyping of early post-transplant patients demonstrated that the presence of fibrotic plaque by OCT was predictive of progression of CAV at 1-year post-transplantation.36 Prospective studies are needed to define actionable OCT parameters and cutoff values that would identify early CAV and lead to changes in management that lower the risk of subsequent death, graft failure, MACE, and need for re-transplantation. OCT generally uses more iodinated contrast than IVUS, and more centers are familiar with IVUS than with OCT. As a result, IVUS remains the more widely used method for invasive intracoronary imaging.
Intracoronary Physiological Assessment
Invasive assessment of coronary physiology, including fractional flow reserve (FFR), coronary flow reserve (CFR), and index of microvascular resistance (IMR) provides additional information regarding the physiological consequences of epicardial CAV and microvascular CAV.37 Multiple studies have shown that invasive coronary physiology markers predict progression of CAV and long-term transplant outcomes.37,38,39 In the largest, multicenter prospective trial of intracoronary assessment in CAV,37 patients with reduced FFR (≤ 0.80) and evidence of microvascular dysfunction (IMR > 25 or coronary flow reserve ≤ 2.0 with FFR ≥ 0.80) were at higher risk of death or re-transplantation at 10 years.37 A more recent study showed that IMR predicts the progression of CAV.36 The results from these trials suggest that early assessment of coronary physiology may identify patients in which CAV-targeted therapy may provide long-term benefit; however, the optimal cutoffs for these parameters may need to be updated for transplant patients when compared to nontransplant patients.37
Cardiac Positron Emission Tomography
Cardiac positron emission tomography (cPET) is an emerging modality for the detection of CAV that uses short-lived radiotracers combined with pharmacological stress (typically regadenoson) to evaluate both epicardial and microvascular coronary physiology.40 Over the past decade, multiple studies have demonstrated the ability of cPET to identify CAV and provide prognostic information.41 In general, studies have found a relationship between stress myocardial blood flow and myocardial flow reserve and ISHLT CAV grade by coronary angiography. Reductions in stress myocardial blood flow and myocardial flow reserve correlate with more severe CAV by coronary angiography.40 Chih et al. compared the performance of cPET with coronary angiography/IVUS and invasive flow reserve measurements in 40 patients following transplantation.42 CAV was identified by IVUS in 80% of patients, and PET markers of coronary physiology, such as cPET myocardial flow reserve, correlated with invasive coronary flow reserve. cPET relative flow reserve (vessel territory) correlated with invasive FFR and cPET coronary vascular resistance correlated with invasive index of microcirculatory resistance.42 Patients with IVUS-determined CAV had reduced cPET myocardial flow reserves, reduced cPET stress myocardial blood flow, and increased coronary resistance indices,42 and the authors proposed optimal diagnostic cutoffs for cPET diagnosis of CAV as myocardial flow reserve < 2.9, stress myocardial blood flow < 2.3 mL/min/g, and coronary vascular resistance > 55 mm Hg/mL/min/g.
Additional studies have sought to determine the prognostic capability of PET for CAV and transplant outcomes. Bravo et al. showed that using multiple cPET parameters refined the detection and noninvasive staging of CAV, and that moderate-severe CAV by cPET imaging is predictive of MACE.43 Konerman et al. demonstrated that reduced cPET myocardial flow reserve was associated with MACE at a median follow-up time of 1.4 years, and they provided further evidence that reduced cPET myocardial flow reserve and stress myocardial blood flow were associated with higher CAV stage by invasive coronary angiography.44 A recent single-center study of patients with ISHLT stage 0 or 1 CAV who underwent cPET imaging demonstrated that a myocardial flow reserve < 2.0 was associated with an increase in death or re-transplantation, particularly in patients with ISHLT stage 1 CAV.45 Finally, cPET achieves longitudinal monitoring of coronary physiology parameters such as myocardial flow reserve and stress myocardial blood flow without the need for an invasive procedure. Evaluation of longitudinal cPET data from 183 heart transplant recipients who underwent 658 cPET studies showed that myocardial flow reserve initially rises in the first 3 years following transplant and then declines over time.46 Decline was abrogated by treatment with mTORi and by higher intensity statin therapy.
Multiple risk factors for decline in myocardial flow reserve were identified and included acute rejection, time from transplant, hypertension, diabetes mellitus, antibody-mediated rejection, and cytomegalovirus infection.46,47 Reduced myocardial flow reserve and cPET-identified epicardial ischemia were predictors of the composite of death, heart failure hospitalizations, acute coronary syndrome, need for revascularization, and re-transplantation. In sum, cardiac PET shows sensitivity and specificity for the diagnosis of CAV, including early CAV, and is prognostic for important clinical outcomes post-transplantation. Additionally, it can be used to assess response to CAV-targeted therapies. Thus, cardiac PET can be considered an alternative to invasive testing for the screening and management of CAV.48 Further studies are needed to identify the optimal cPET coronary physiology parameter cutoffs that would indicate the need to intensify CAV-directed therapy.
Cardiac Magnetic Resonance Imaging
Cardiac magnetic resonance imaging (cMRI) is an alternative noninvasive imaging modality that can be used to evaluate CAV.48 Muehling et al. determined that when left ventricular hypertrophy and/or prior rejection were excluded, then resting endocardial/epicardial perfusion ratio > 1.3 could exclude CAV.49 However, patients with CAV were identified by invasive coronary angiography and had extensive transplant vasculopathy; as such, these cutoffs may not readily identify mild CAV. Miller et al. showed that cMRI could detect moderate and severe CAV, as defined by invasive coronary angiography and IVUS.50 In this study, reduced myocardial perfusion reserve predicted both epicardial and microvascular disease (the latter defined by invasive index of microvascular resistance), although the ability to detect mild CAV was not assessed. cMRI also has prognostic implications for CAV. Hughes et al. found that transplant patients with CAV defined by ISHLT CAV staging guidelines had progressive myocardial fibrosis with increasing CAV stage, and that increasing myocardial fibrosis correlated with mortality and MACE.51 Stress CMRI may also have predictive value in transplant recipients.52,53 Overall, and when compared to cPET, cMRI presently lacks the ability to detect early CAV, limiting its use as a therapeutic target.
Ultimately, the aforementioned work led to ISHLT guideline recommendations for OCT, cPET, and cMRI in the detection of CAV (Figure 1).54 Stress echocardiography and coronary computed tomography angiography (CCTA) are alternative modalities that can be used to detect CAV (Table 2). Briefly, dobutamine stress echocardiography has low sensitivity in the detection of CAV and provides limited prognostic information.55,56 CCTA has adequate sensitivity, specificity, and negative predictive value to detect epicardial stenosis > 50% when referenced to invasive coronary angiography57 but cannot detect microvascular CAV. Nevertheless, CCTA can be considered as an alternative to invasive coronary angiography in patients unable to undergo invasive testing for epicardial disease in vessels > 2 mm in diameter.
Table 2.
Imaging modalities for the detection of cardiac allograft vasculopathy.
|
| ||||
|---|---|---|---|---|
| MODALITY | ADVANTAGE | DISADVANTAGE | GUIDELINE INDICATION* | GUIDELINE RECOMMENDATION* |
|
| ||||
| Invasive | ||||
|
| ||||
| Coronary angiography | Widely available Traditional gold standard for epicardial CAV |
Low sensitivity for early CAV Iodinated contrast Procedural risk |
Diagnosis and grading based on ISHLT guidelines | Class 1 |
|
| ||||
| Intravascular ultrasound | Improved detection of early CAV Vessel anatomy |
Moderate resolution (compared to OCT) Increased cost Procedural risk |
Early detection of donor-derived CAD and early progressive CAV | Class 2a |
|
| ||||
| Optical coherence tomography | Improved detection of early CAV Detailed vessel anatomy with highest resolution |
Additional iodinated contrast Increased cost Procedural risk |
Early detection of donor-derived CAD | Class 2a |
|
| ||||
| Coronary physiology | Improved sensitivity for small vessel CAV | Increased cost and time Procedural risk |
Intracoronary flow to detect small vessel CAV | Class 2a |
|
| ||||
| Noninvasive | ||||
|
| ||||
| Cardiac positron emission tomography | Lower radiation than coronary angiography No iodinated contrast Accuracy to diagnose moderate-severe CAV, and possibly early mild CAV |
Lower availability than other modalities Requires expertise for interpretation |
Noninvasive detection of CAV and prognostication | Class 2a |
|
| ||||
| Cardiac magnetic resonance imaging | No radiation or iodinated contrast Accuracy to diagnose moderate-severe CAV Early detection of myocardial fibrosis |
Low sensitivity for mild CAV Lower availability than other modalities Requires significant expertise for interpretation Gadolinium-based contrast may be discouraged in ESRD |
Noninvasive detection of CAV and prognostication | Class 2b |
|
| ||||
| Stress echocardiography | Widely available Low cost No radiation or iodinated contrast |
Low sensitivity for the detection of CAV | Prognostication | Class 2a |
|
| ||||
| Coronary computed tomography angiography | Alternative to ICA for epicardial disease Able to detect moderate-severe CAV |
No information on small vessel disease Requires lower heart rate for optimal images Iodinated contrast |
CAV detection in ≥ 2 mm epicardial vessels | Class 2a |
|
| ||||
*Based on the 2023 ISHLT guidelines for the care of heart transplant recipients;54 CAD: coronary artery disease; CAV: cardiac allograft vasculopathy; OCT: optical coherence tomography; ESRD: end-stage renal disease; ICA: invasive coronary angiography
CAV Prevention and Management
Preventative strategies to reduce the progression of CAV include the routine use of statin therapy and the inclusion of mTORi and mycophenolate mofetil as part of immunosuppressive therapy (Figure 1). Antiplatelet therapy with aspirin may reduce the rate of CAV progression and mortality and is commonly used to prevent CAV progression.58,59,60 Antioxidant vitamins (vitamins C and E) appeared to reduce CAV progression by IVUS at 1 year in a small cohort of patients; however, whether antioxidant vitamins change clinical outcomes is unknown.61 Percutaneous coronary intervention and re-transplantation are options for advanced CAV; however, their outcomes are generally unfavorable, as detailed below.
Statins and Other Lipid Lowering Therapies
Two clinical trials and their follow-up studies have shown benefits of statins to reduce CAV incidence. Pravastatin initiated early after transplant improved survival and lowered incidence of CAV at 1 year;62 this effect extended to 10 years despite crossover of patients from placebo to pravastatin, indicating that early treatment with statins has a durable, positive impact on CAV progression.63 Simvastatin showed similar reduction in mortality at 4 years,64 with preservation of effect at 8 years.65 Two retrospective analyses of statin intensity and incident CAV failed to show that higher intensity statin therapy reduces CAV incidence.66,67 The optimal low-density-lipoprotein cholesterol goal (LDLc) is unclear, although one retrospective study suggests that LDLc < 100 mg/dL is associated with reduced CAV incidence.68 Proprotein convertase subtilisin/kexin type 9 inhibition, in addition to statin therapy after transplant, lowered LDLc levels by approximately 50% but did not change intimal thickness at 1 year, suggesting that aggressive LDLc lowering does not necessarily improve CAV incidence or progression.69 Taken together, current data on lipid lowering therapies to reduce CAV support use of statins to lower LDLc and access immunomodulatory effects of statins. Additional randomized, prospective studies are needed to determine optimal LDLc goal and whether high intensity statin therapy benefits CAV prevention when initiated early.
mTOR Inhibition
Mammalian target of mTORi (such as everolimus and sirolimus) are antiproliferative agents that reduce immunoproliferation as well as fibroblast and smooth muscle cell proliferation, which can ultimately reduce CAV incidence and progression. In a randomized trial comparing everolimus to azathioprine, everolimus reduced the incidence of vasculopathy and intimal thickness by intracoronary ultrasound.70 Slower increase in intimal thickness by intracoronary ultrasound was confirmed in a later clinical trial comparing everolimus to mycophenolate mofetil.71 Similar results, including reduced CAV incidence and intimal and medial thickness by intracoronary ultrasound, were demonstrated with sirolimus compared to azathioprine.72 Additionally, sirolimus has been shown to reduce progression of established CAV.73,74 mTORi have a narrow therapeutic window, and their use is limited by renal dysfunction, impaired wound healing, effusions, interaction with calcineurin inhibitors, proteinuria, and cytopenias. Despite this, mTORi may be beneficial in the prevention of CAV progression and are one of very few agents shown to prevent progression. Indeed, early conversion to sirolimus reduced CAV progression and lowered long-term transplant mortality without significant or limiting side effects compared to continued treatment with tacrolimus.75
Percutaneous Coronary Intervention and Re-transplantation
Percutaneous coronary intervention (PCI) with balloon angioplasty with or without stent placement is an option for severe vasculopathy with focal disease. Angioplasty has a high immediate success rate and may be beneficial in patients without significant distal arteriopathy.76 Stenting is safe and generally well-tolerated in CAV.77,78,79 Drug-eluting stents are generally preferred to bare metal stents.80 PCI is considered palliative even when there is an obvious focal lesion amenable to angioplasty and stent placement, as outcomes remain poor for patients with CAV who require PCI.81 Re-transplantation is definitive therapy for CAV; however, survival following re-transplantation is inferior to primary heart transplant.82,83 Yet, patients undergoing re-transplant for CAV have greater 1-year survival than those re-transplanted for other reasons,83 and re-transplant may be superior to medical management in patients with systolic dysfunction due to CAV.84 Indeed, Goldraich et al. demonstrated that patients with severe CAV who underwent re-transplantation faired similarly to those who were maintained on medical therapy alone, and subsequent subgroup analysis suggested a mortality benefit in patients with severe CAV and systolic dysfunction. Therefore, the current ISHLT guidelines recommend consideration for re-transplantation in patients with ISHLT severe CAV and concomitant systolic dysfunction.54
Management of Ventricular Arrhythmia and Sudden Cardiac Death
Risk of sudden cardiac death (SCD) due to ventricular arrhythmia or pulseless electrical activity is increased in patients with CAV. Patients with severe CAV and graft dysfunction had a 5.4% risk of SCD 2 years after the diagnosis of CAV, while those without graft dysfunction had a 3.2% risk of SCD in the same time period.85 Treated rejection increased the risk to 4.9% in patients with normal graft function and 8% in those with graft dysfunction. Despite this, the benefit of implantable cardioverter-defibrillators (ICDs) in patients with CAV, particularly for primary prevention, is unclear, and there is little evidence to support routine use of ICDs in this population. A retrospective analysis of heart transplant recipients who received ICDs showed that CAV was present in all patients that received appropriate ICD treatment for ventricular tachycardia or ventricular fibrillation,86 suggesting that CAV and associated ischemia predisposes patients to ventricular arrhythmias that can terminate with appropriate ICD therapy; however, no prospective trials have evaluated whether routine use of ICDs would improve outcomes in patients with CAV. Thus, current ISHLT guidelines recommend consideration for ICD placement only when severe CAV with systolic dysfunction is present and there is a chance for meaningful longevity (ie, > 1 year).54,87
Conclusions and Future Directions
Cardiac allograft vasculopathy remains a significant limitation to long-term heart transplant survival. Over the last decades, significant advances have been made in both invasive and noninvasive diagnosis of CAV, particularly early CAV where patients are most likely to derive benefit from current and future CAV-targeted therapies. Additional prospective studies that incorporate novel invasive and noninvasive diagnostic modalities to determine the ideal initiation of CAV-directed therapy (ie, introduction of mTORi as part of immunosuppressive strategy) are needed. Our current diagnostic algorithm for CAV screening and management is presented in Figure 2. Ultimately, therapies to prevent and treat CAV remain limited. Targeting novel pathways in CAV such as the endothelin-1 pathway (NCT05373108), using photopheresis for CAV (NCT06899828, NCT04226521), or using targeted genetics to guide treatment (NCT02082821) may provide novel approaches to CAV management. As understanding of the pathological mechanisms within the immune system, endothelium, and vascular smooth muscle that drive CAV improves, new therapeutic approaches such as CRISPR/Cas9, siRNA, device-based therapies, and novel pharmaceuticals may become available to prevent or treat CAV and improve long-term heart transplant outcomes.
Figure 2.
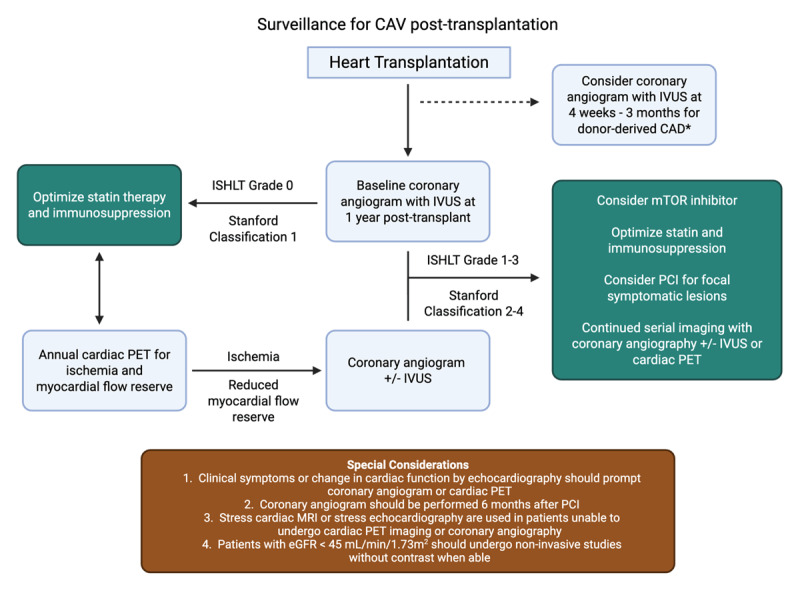
Diagnostic algorithm for the surveillance of cardiac allograft vasculopathy (CAV) post-transplantation. This is an adaptation of the CAV surveillance protocol at our institution. Following heart transplantation, CAV screening typically starts at 1-year post-transplantation with coronary angiography with IVUS to assess for early CAV. Early coronary angiography between 4 weeks and 3 months post-transplantation can be considered if there are risk factors for donor-derived coronary artery disease. For patients with ISHLT grade 0 or Stanford classification 1 CAV (see Table 1), optimization of statin therapy and immunosuppression is preferred. These patients are screened for progression of CAV with serial noninvasive imaging, such as cardiac PET (alternatives include cardiac MRI or stress echocardiography, depending on institutional expertise). If serial cardiac PET imaging reveals ischemia or reduced myocardial flow reserves, patients undergo coronary angiography with or without IVUS. When ISHLT grade 1-3 or Stanford classification 2-4 CAV is detected, mTOR inhibition is considered, PCI may be performed for symptomatic, focal, lesions, and serial imaging is continued with either coronary angiography or cardiac PET imaging. Certain special considerations are listed above. CAV: cardiac allograft vasculopathy; IVUS: intravascular ultrasound; ISHLT: International Society for Heart and Lung Transplantation; PET: positron emission tomography; mTOR: mammalian target of rapamycin; PCI: percutaneous coronary intervention. Image created with Biorender
Key Points
Cardiac allograft vasculopathy (CAV) is a leading cause of graft loss and mortality after heart transplant.
Coronary angiography remains the gold standard for detection of CAV yet lacks sensitivity to detect early CAV.
Cardiac positron emission tomography with functional testing demonstrates sensitivity and specificity for the diagnosis of CAV, is prognostic for important clinical transplant-related events, and can potentially serve as a therapeutic target.
Statins are the only therapy shown to reduce mortality and progression of CAV in a randomized clinical trial.
Mammalian target of rapamycin inhibitors (mTOR), such as everolimus and sirolimus, slow the progression of CAV and early conversion to mTOR inhibitor therapy may reduce mortality.
Competing Interests
The authors have no competing interests to declare.
References
- 1.Khush KK, Cherikh WS, Chambers DC, et al. The International Thoracic Organ Transplant Registry of the International Society for Heart and Lung Transplantation: Thirty-sixth adult heart transplantation report - 2019; focus theme: Donor and recipient size match. J Heart Lung Transplant. 2019. Oct;38(10):1056-66. doi: 10.1016/j.healun.2019.08.004 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 2.Pober JS, Chih S, Kobashigawa J, Madsen JC, Tellides G. Cardiac allograft vasculopathy: current review and future research directions. Cardiovasc Res. 2021. Nov 22;117(13):2624-38. doi: 10.1093/cvr/cvab259 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.Chang A, Martin KA, Colvin M, Bellumkonda L. Role of ascorbic acid in cardiac allograft vasculopathy. lin Transplant. 2023. Dec;37(12):e15153. doi: 10.1111/ctr.15153 [DOI] [PubMed] [Google Scholar]
- 4.Day JD, Rayburn BK, Gaudin PB, et al. Cardiac allograft vasculopathy: the central pathogenetic role of ischemia-induced endothelial cell injury. J Heart Lung Transplant. 1995. Nov-Dec;14(6 Pt 2):S142-9. PMID: 8719476 [PubMed] [Google Scholar]
- 5.Valantine H, Rickenbacker P, Kemna M, et al. Metabolic abnormalities characteristic of dysmetabolic syndrome predict the development of transplant coronary artery disease: a prospective study. Circulation. 2001. May 1;103(17):2144-52. doi: 10.1161/01.cir.103.17.2144 [DOI] [PubMed] [Google Scholar]
- 6.Lu WH, Palatnik K, Fishbein GA, et al. Diverse morphologic manifestations of cardiac allograft vasculopathy: a pathologic study of 64 allograft hearts. J Heart Lung Transplant. 2011. Sep;30(9):1044-50. doi: 10.1016/j.healun.2011.04.008 [DOI] [PubMed] [Google Scholar]
- 7.Huibers MM, Vink A, Kaldeway J, et al. Distinct phenotypes of cardiac allograft vasculopathy after heart transplantation: a histopathological study. Atherosclerosis. 2014. Oct;236(2):353-9. doi: 10.1016/j.atherosclerosis.2014.07.016 [DOI] [PubMed] [Google Scholar]
- 8.van Loosdregt J, van Oosterhout MF, Bruggink AH, et al. The chemokine and chemokine receptor profile of infiltrating cells in the wall of arteries with cardiac allograft vasculopathy is indicative of a memory T-helper 1 response. Circulation. 2006. Oct;114(15):1599-607. doi: 10.1161/CIRCULATIONAHA.105.597526 [DOI] [PubMed] [Google Scholar]
- 9.Nagano H, Mitchell RN, Taylor MK, Hasegawa S, Tilney NL, Libby P. Interferon15 gamma deficiency prevents coronary arteriosclerosis but not myocardial rejection in transplanted mouse hearts. J Clin Invest. 1997. Aug 1;100(3):550-7. doi: 10.1172/JCI119564 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 10.Tellides G, Tereb DA, Kirkiles-Smith NC, et al. Interferon-gamma elicits arteriosclerosis in the absence of leukocytes. Nature. 2000. Jan 13;403(6766):207-11. doi: 10.1038/35003221 [DOI] [PubMed] [Google Scholar]
- 11.Wang Y, Bai Y, Qin L, et al. Interferon-gamma induces human vascular smooth muscle cell proliferation and intimal expansion by phosphatidylinositol 3-kinase dependent mammalian target of rapamycin raptor complex activation. Circ Res. 2007. Sep 14;101(6):560-9. doi: 10.1161/CIRCRESAHA.107.151068 [DOI] [PubMed] [Google Scholar]
- 12.Tellides G, Pober JS. Interferon-gamma axis in graft arteriosclerosis. Circ Res. 2007. Mar 16;100(5):622-32. doi: 10.1161/01.RES.0000258861.72279.29 [DOI] [PubMed] [Google Scholar]
- 13.Zhang Q, Cecka JM, Gjertson DW, et al. HLA and MICA: targets of antibody-mediated rejection in heart transplantation. Transplantation. 2011. May 27;91(10):1153-8. doi: 10.1097/TP.0b013e3182157d60 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 14.Galvani S, Auge N, Calise D, et al. HLA class I antibodies provoke graft arteriosclerosis in human arteries transplanted into SCID/beige 12 mice. Am J Transplant. 2009. Nov;9(11):2607-14. doi: 10.1111/j.1600-6143.2009.02804.x [DOI] [PubMed] [Google Scholar]
- 15.Hirohashi T, Chase CM, Della Pelle P, et al. A novel pathway of chronic allograft rejection mediated by NK cells and 16 alloantibody. Am J Transplant. 2012. Feb;12(2):313-21. doi: 10.1111/j.1600-6143.2011.03836.x [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16.Hiemann NE, Meyer R, Wellnhofer E, et al. Non-HLA antibodies targeting vascular receptors enhance alloimmune response and microvasculopathy after heart transplantation. Transplantation. 2012. Nov 15;94(9):919-24. doi: 10.1097/TP.0b013e3182692ad2 [DOI] [PubMed] [Google Scholar]
- 17.Shaw SM, Williams SG. Is brain natriuretic peptide clinically 1 useful after cardiac transplantation? J Heart Lung Transplant. 2006. Dec;25(12):1396-401. doi: 10.1016/j.healun.2006.10.001 [DOI] [PubMed] [Google Scholar]
- 18.Labarrere CA, Lee JB, Nelson DR, Al-Hassani M, Miller SJ, Pitts DE. C-reactive protein, arterial endothelial activation, and development of transplant coronary artery disease: a prospective study. Lancet. 2002. Nov 9;360(9344):1462-7. doi: 10.1016/S0140-6736(02)11473-5. [DOI] [PubMed] [Google Scholar]
- 19.Singh N, Heggermont W, Fieuws S, Vanhaecke J, Van Cleemput J, De Geest B. Endothelium-enriched microRNAs as diagnostic biomarkers for cardiac allograft vasculopathy. J Heart Lung Transplant. 2015. Nov;34(11):1376-84. Epub 20150617. doi: 10.1016/j.healun.2015.06.008 [DOI] [PubMed] [Google Scholar]
- 20.Neumann A, Napp LC, Kleeberger JA, et al. MicroRNA 628-5p as a Novel Biomarker for Cardiac Allograft Vasculopathy. Transplantation. 2017. Jan;101(1):e26-e33. doi: 10.1097/TP.0000000000001477 [DOI] [PubMed] [Google Scholar]
- 21.Przybylek B, Boethig D, Neumann A, et al. Novel Cytokine Score and Cardiac Allograft Vasculopathy. Am J Cardiol. 2019. Apr 1;123(7):1114-9. doi: 10.1016/j.amjcard.2018.12.034 [DOI] [PubMed] [Google Scholar]
- 22.Almufleh A, Zhang L, Mielniczuk LM, et al. Biomarker discovery in cardiac allograft vasculopathy using targeted aptamer proteomics. Clin Transplant. 2020. Jan;34(1):e13765. doi: 10.1111/ctr.13765 [DOI] [PubMed] [Google Scholar]
- 23.Kennel PJ, Saha A, Maldonado DA, et al. Serum exosomal protein profiling for the non-invasive detection of cardiac allograft rejection. J Heart Lung Transplant. 2018. Mar;37(3):409-17. doi: 10.1016/j.healun.2017.07.012 [DOI] [PubMed] [Google Scholar]
- 24.Costanzo MR, Dipchand A, Starling R, et al. The International Society of Heart and Lung Transplantation Guidelines for the care of heart transplant recipients. J Heart Lung Transplant. 2010. Aug;29(8):914-56. doi: 10.1016/j.healun.2010.05.034 [DOI] [PubMed] [Google Scholar]
- 25.Prada-Delgado O, Estevez-Loureiro R, Paniagua-Martin MJ, Lopez-Sainz A, Crespo-Leiro MG. Prevalence and prognostic value of cardiac allograft vasculopathy 1 year after heart transplantation according to the ISHLT recommended nomenclature. J Heart Lung Transplant. 2012. Mar;31(3):332-3. doi: 10.1016/j.healun.2011.12.006 [DOI] [PubMed] [Google Scholar]
- 26.Costanzo MR, Naftel DC, Pritzker MR, et al. Heart transplant coronary artery disease detected by coronary angiography: a multiinstitutional study of preoperative donor and recipient risk factors. Cardiac Transplant Research Database. J Heart Lung Transplant. 1998. Aug;17(8):744-53. PMID: 9730422 [PubMed] [Google Scholar]
- 27.Tuzcu EM, Hobbs RE, Rincon G, et al. Occult and frequent transmission of atherosclerotic coronary disease with cardiac transplantation. Insights from intravascular ultrasound. Circulation. 1995. Mar 15;91(6):1706-13. doi: 10.1161/01.cir.91.6.1706 [DOI] [PubMed] [Google Scholar]
- 28.Shahandeh N, Kashiyama K, Honda Y, et al. Invasive Coronary Imaging Assessment for Cardiac Allograft Vasculopathy: State-of-the-Art Review. J Soc Cardiovasc Angiogr Interv. 2022. May 13;1(4):100344. doi: 10.1016/j.jscai.2022.100344 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 29.St Goar FG, Pinto FJ, Alderman EL, et al. Intracoronary ultrasound in cardiac transplant recipients. In vivo evidence of “angiographically silent” intimal thickening. Circulation. 1992. Mar;85(3):979-87. doi: 10.1161/01.cir.85.3.979 [DOI] [PubMed] [Google Scholar]
- 30.Mehra MR, Ventura HO, Stapleton DD, Smart FW, Collins TC, Ramee SR. Presence of severe intimal thickening by intravascular ultrasonography predicts cardiac events in cardiac allograft vasculopathy. J Heart Lung Transplant. 1995;14(4):632-9. PMID: 7578168 [PubMed] [Google Scholar]
- 31.Rickenbacher PR, Pinto FJ, Lewis NP, et al. Prognostic importance of intimal thickness as measured by intracoronary ultrasound after cardiac transplantation. Circulation. 1995. Dec 15;92(12):3445-52. doi: 10.1161/01.cir.92.12.3445 [DOI] [PubMed] [Google Scholar]
- 32.Kobashigawa JA, Tobis JM, Starling RC, et al. Multicenter intravascular ultrasound validation study among heart transplant recipients: outcomes after five years. J Am Coll Cardiol. 2005. May 3;45(9):1532-7. doi: 10.1016/j.jacc.2005.02.035 [DOI] [PubMed] [Google Scholar]
- 33.Tuzcu EM, Kapadia SR, Sachar R, et al. Intravascular ultrasound evidence of angiographically silent progression in coronary atherosclerosis predicts long-term morbidity and mortality after cardiac 1 transplantation. J Am Coll Cardiol. 2005. May 3;45(9):1538-42. doi: 10.1016/j.jacc.2004.12.076 [DOI] [PubMed] [Google Scholar]
- 34.Hou J, Lv H, Jia H, et al. OCT assessment of allograft vasculopathy in heart transplant recipients. JACC Cardiovasc Imaging. 2012. Jun;5(6):662-3. doi: 10.1016/j.jcmg.2012.01.018 [DOI] [PubMed] [Google Scholar]
- 35.Khandhar SJ, Yamamoto H, Teuteberg JJ, et al. Optical coherence tomography for characterization of cardiac allograft vasculopathy after heart transplantation (OCTCAV study). J Heart Lung Transplant. 2013. Jun;32(6):596- 602. doi: 10.1016/j.healun.2013.02.005 [DOI] [PubMed] [Google Scholar]
- 36.Chih S, Chong AY, Dzavik V, et al. Fibrotic Plaque and Microvascular Dysfunction Predict Early Cardiac Allograft Vasculopathy Progression After Heart Transplantation: The Early Post Transplant Cardiac Allograft Vasculopathy Study. Circ Heart Fail. 2023. Jun;16(6):e010173. doi: 10.1161/CIRCHEARTFAILURE.122.010173 [DOI] [PubMed] [Google Scholar]
- 37.Ahn JM, Zimmermann FM, Arora S, et al. Prognostic value of comprehensive intracoronary physiology assessment early after heart transplantation. Eur Heart J. 2021. Dec 21;42(48):4918-29. doi: 10.1093/eurheartj/ehab568 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 38.Lee JH, Okada K, Khush K, et al. Coronary Endothelial Dysfunction and the Index of Microcirculatory Resistance as a Marker of Subsequent Development of Cardiac Allograft Vasculopathy. Circulation. 2017. Mar 14;135(11):1093-5. doi: 10.1161/Circulationaha.116.025268 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 39.Yang HM, Khush K, Luikart H, et al. Invasive Assessment of Coronary Physiology Predicts Late Mortality After Heart Transplantation. Circulation. 2016. May 17;133(20):1945-50. doi: 10.1161/CIRCULATIONAHA.115.018741 [DOI] [PubMed] [Google Scholar]
- 40.Feher A, Miller EJ. PET Myocardial Blood Flow for Post-transplant Surveillance and Cardiac Allograft Vasculopathy in Heart Transplant Recipients. Curr Cardiol Rep. 2022. Oct 24;24(12):1865-71. doi: 10.1007/s11886-022-01804-3 [DOI] [PubMed] [Google Scholar]
- 41.Ajluni SC Jr., Mously H, Chami T, et al. Non-invasive Imaging in the Evaluation of Cardiac Allograft Vasculopathy in Heart Transplantation: A Systematic Review. Curr Probl Cardiol. 2022. Aug;47(8):101103. doi: 10.1016/j.cpcardiol.2022.101103 [DOI] [PubMed] [Google Scholar]
- 42.Chih S, Chong AY, Erthal F, et al. PET Assessment of Epicardial Intimal Disease and Microvascular Dysfunction in Cardiac Allograft Vasculopathy. J Am Coll Cardiol. 2018. Apr 3;71(13):1444-56. doi: 10.1016/j.jacc.2018.01.062 [DOI] [PubMed] [Google Scholar]
- 43.Bravo PE, Bergmark BA, Vita T, et al. Diagnostic and prognostic value of myocardial blood flow quantification as non-invasive indicator of cardiac allograft vasculopathy. Eur Heart J. 2018;39(4):316-23. doi: 10.1093/eurheartj/ehx683 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 44.Konerman MC, Lazarus JJ, Weinberg RL, Shah RV, Ghannam M, Hummel SL, et al. Reduced Myocardial Flow Reserve by Positron Emission Tomography Predicts Cardiovascular Events After Cardiac Transplantation. Circ Heart Fail. 2018. Jan 21;11(6):e004473. doi: 10.1161/CIRCHEARTFAILURE.117.004473 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 45.Prasad N, Harris E, Yuzefpolskaya M, et al. Can the grading of mild cardiac allograft vasculopathy be further refined? An angiographic and physiologic assessment of heart transplant recipients with ISHLT CAV 1. J Heart Lung Transplant. 2024. Dec 30:S1053-2498(24)02028-X. doi: 10.1016/j.healun.2024.12.013 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 46.Gondi KT, Hammer Y, Yosef M, et al. Longitudinal Change and Predictors of Myocardial Flow Reserve by Positron Emission Tomography for the Evaluation of Cardiac Allograft Vasculopathy Following Heart Transplantation. J Card Fail. 2024. Jul;30(7):915-25. doi: 10.1016/j.cardfail.2023.09.013 [DOI] [PubMed] [Google Scholar]
- 47.Gondi KT, Kaul DR, Gregg KS, et al. Cytomegalovirus infection is associated with impaired myocardial flow reserve after heart transplantation. J Heart Lung Transplant. 2024. Mar;43(3):432-41. doi: 10.1016/j.healun.2023.10.005 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 48.Madamanchi C, Konerman MC, Murthy VL. Imaging Coronary Allograft Vasculopathy with Cardiac PET and Cardiac MRI. Curr Cardiol Rep. 2021. Oct 16;23(12):175. doi: 10.1007/s11886-021-01606-z [DOI] [PubMed] [Google Scholar]
- 49.Muehling OM, Wilke NM, Panse P, et al. Reduced myocardial perfusion reserve and transmural perfusion gradient in heart transplant arteriopathy assessed by magnetic resonance imaging. J Am Coll Cardiol. 2003. Sep 17;42(6):1054-60. doi: 10.1016/s0735-1097(03)00924-0 [DOI] [PubMed] [Google Scholar]
- 50.Miller CA, Sarma J, Naish JH, et al. Multiparametric cardiovascular magnetic resonance assessment of cardiac allograft vasculopathy. J Am Coll Cardiol. 2014. Mar 4;63(8):799-808. doi: 10.1016/j.jacc.2013.07.119 [DOI] [PubMed] [Google Scholar]
- 51.Hughes A, Okasha O, Farzaneh-Far A, et al. Myocardial Fibrosis and Prognosis in Heart Transplant Recipients. Circ Cardiovasc Imaging. 2019;12(10):e009060. doi: 10.1161/CIRCIMAGING.119.009060 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 52.Kazmirczak F, Nijjar PS, Zhang L, Hughes A, Chen KA, Okasha O, et al. Safety and prognostic value of regadenoson stress cardiovascular magnetic resonance imaging in heart transplant recipients. J Cardiovasc Magn Reson. 2019. Oct;21(1):9. doi: 10.1186/s12968-018-0515-2 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 53.Erbel C, Mukhammadaminova N, Gleissner CA, et al. Myocardial Perfusion Reserve and Strain-Encoded CMR for Evaluation of Cardiac Allograft Microvasculopathy. JACC Cardiovasc Imaging. 2016. Mar;9(3):255-66. doi: 10.1016/j.jcmg.2015.10.012 [DOI] [PubMed] [Google Scholar]
- 54.Velleca A, Shullo MA, Dhital K, et al. The International Society for Heart and Lung Transplantation (ISHLT) guidelines for the care of heart transplant recipients. J Heart Lung Transplant. 2023. May;42(5):e1-e141. doi: 10.1016/j.healun.2022.10.015 [DOI] [PubMed] [Google Scholar]
- 55.Chirakarnjanakorn S, Starling RC, Popovic ZB, Griffin BP, Desai MY. Dobutamine stress echocardiography during follow-up surveillance in heart transplant patients: Diagnostic accuracy and predictors of outcomes. J Heart Lung Transplant. 2015. May;34(5):710-7. doi: 10.1016/j.healun.2014.11.019 [DOI] [PubMed] [Google Scholar]
- 56.Clerkin KJ, Farr MA, Restaino SW, Ali ZA, Mancini DM. Dobutamine stress echocardiography is inadequate to detect early cardiac allograft vasculopathy. J Heart Lung Transplant. 2016. Aug;35(8):1040-1. doi: 10.1016/j.healun.2016.05.012 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 57.Wever-Pinzon O, Romero J, Kelesidis I, et al. Coronary computed tomography angiography for the detection of cardiac allograft vasculopathy: a meta-analysis of prospective trials. J Am Coll Cardiol. 2014. May 20;63(19):1992-2004. doi: 10.1016/j.jacc.2014.01.071 [DOI] [PubMed] [Google Scholar]
- 58.Asleh R, Briasoulis A, Smith B, et al. Association of Aspirin Treatment With Cardiac Allograft Vasculopathy Progression and Adverse Outcomes After Heart Transplantation. J Card Fail. 2021. May;27(5):542-51. doi: 10.1016/j.cardfail.2021.01.019 [DOI] [PubMed] [Google Scholar]
- 59.Kim M, Bergmark BA, Zelniker TA, et al. Early aspirin use and the development of cardiac allograft vasculopathy. J Heart Lung Transplant. 2017. Dec;36(12):1344-9. doi: 10.1016/j.healun.2017.06.015 [DOI] [PubMed] [Google Scholar]
- 60.Peled Y, Lavee J, Raichlin E, et al. Early aspirin initiation following heart transplantation is associated with reduced risk of allograft vasculopathy during long-term follow-up. Clin Transplant. 2017. Dec;31(12). doi: 10.1111/ctr.13133 [DOI] [PubMed] [Google Scholar]
- 61.Fang JC, Kinlay S, Beltrame J, et al. Effect of vitamins C and E on progression of transplant-associated arteriosclerosis: a randomized trial. Lancet. 2002. Mar 30;359(9312):1108-13. doi: 10.1016/S0140-6736(02)08154-0 [DOI] [PubMed] [Google Scholar]
- 62.Kobashigawa JA, Katznelson S, Laks H, et al. Effect of pravastatin on outcomes after cardiac transplantation. N Engl J Med. 1995. Sep 7;333(10):621-7. doi: 10.1056/NEJM199509073331003 [DOI] [PubMed] [Google Scholar]
- 63.Kobashigawa JA, Moriguchi JD, Laks H, et al. Ten-year follow-up of a randomized trial of pravastatin in heart transplant patients. J Heart Lung Transplant. 2005. Nov;24(11):1736-40. doi: 10.1016/j.healun.2005.02.009 [DOI] [PubMed] [Google Scholar]
- 64.Wenke K, Meiser B, Thiery J, et al. Simvastatin reduces graft vessel disease and mortality after heart transplantation: a four-year randomized trial. Circulation. 1997. Sep 2;96(5):1398-402. doi: 10.1161/01.cir.96.5.1398 [DOI] [PubMed] [Google Scholar]
- 65.Wenke K, Meiser B, Thiery J, et al. Simvastatin initiated early after heart transplantation: 8-year prospective experience. Circulation. 2003. Jan 7;107(1):93-7. doi: 10.1161/01.cir.0000043241.32523.ee [DOI] [PubMed] [Google Scholar]
- 66.Golbus JR, Adie S, Yosef M, Murthy VL, Aaronson KD, Konerman MC. Statin 6 intensity and risk for cardiovascular events after heart transplantation. ESC Heart Fail. 2020. Oct;7(5):2074-81. doi: 10.1002/ehf2.12784 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 67.Ellimuttil TM, Harrison K, Rollins AT, et al. Effect of Statin Intensity on the Progression of Cardiac Allograft Vasculopathy. Card Fail Rev. 2021. Nov 12;7:e15. doi: 10.15420/cfr.2021.07 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 68.Harris J, Teuteberg J, Shullo M. Optimal low-density lipoprotein concentration for cardiac allograft vasculopathy prevention. Clin Transplant. 2018. May;32(5):e13248. doi: 10.1111/ctr.13248 [DOI] [PubMed] [Google Scholar]
- 69.Broch K, Lemstrom KB, Gustafsson F, et al. Randomized Trial of Cholesterol Lowering With Evolocumab for Cardiac Allograft Vasculopathy in Heart Transplant Recipients. JACC Heart Fail. 2024. Oct;12(10):1677-88. doi: 10.1016/j.jchf.2024.04.026 [DOI] [PubMed] [Google Scholar]
- 70.Eisen HJ, Tuzcu EM, Dorent R, et al. Everolimus for the prevention of allograft rejection and vasculopathy in cardiac-transplant recipients. N Engl J Med. 2003. Aug 28;349(9):847-58. doi: 10.1056/NEJMoa022171 [DOI] [PubMed] [Google Scholar]
- 71.Eisen HJ, Kobashigawa J, Starling RC, et al. Everolimus versus mycophenolate mofetil in heart transplantation: a randomized, multicenter trial. Am J Transplant. 2013. May;13(5):1203-16. doi: 10.1111/ajt.12181 [DOI] [PubMed] [Google Scholar]
- 72.Keogh A, Richardson M, Ruygrok P, et al. Sirolimus in de novo heart transplant recipients reduces acute rejection and prevents coronary artery disease at 2 years: a randomized clinical trial. Circulation. 2004. Oct 26;110(17):2694-700. doi: 10.1161/01.CIR.0000136812.90177.94 [DOI] [PubMed] [Google Scholar]
- 73.Mancini D, Pinney S, Burkhoff D, et al. Use of rapamycin slows progression of cardiac transplantation vasculopathy. Circulation. 2003. Jul 8;108(1):48-53. doi: 10.1161/01.CIR.0000070421.38604.2B [DOI] [PubMed] [Google Scholar]
- 74.Raichlin E, Bae JH, Khalpey Z, et al. Conversion to sirolimus as primary immunosuppression attenuates the progression of allograft vasculopathy after cardiac transplantation. Circulation. 2007. Dec 4;116(23):2726-33. doi: 10.1161/CIRCULATIONAHA.107.692996 [DOI] [PubMed] [Google Scholar]
- 75.Asleh R, Briasoulis A, Kremers WK, et al. Long-Term Sirolimus for Primary Immunosuppression in Heart Transplant Recipients. J Am Coll Cardiol. 2018. Feb 13;71(6):636-50. doi: 10.1016/j.jacc.2017.12.005 [DOI] [PubMed] [Google Scholar]
- 76.Halle AA 3rd, DiSciascio G, Massin EK, et al. Coronary angioplasty, atherectomy and bypass surgery in cardiac transplant recipients. J Am Coll Cardiol. 1995. Jul;26(1):120-8. doi: 10.1016/0735-1097(95)00124-i [DOI] [PubMed] [Google Scholar]
- 77.Heublein B, Pethig K, Maass C, Wahlers T, Haverich A. Coronary artery stenting in cardiac allograft vascular disease. Am Heart J. 1997. Nov;134(5 Pt 1):930-8. doi: 10.1016/s0002-8703(97)80017-8 [DOI] [PubMed] [Google Scholar]
- 78.Wong PM, Piamsomboon C, Mathur A, et al. Efficacy of coronary stenting in the management of cardiac allograft vasculopathy. Am J Cardiol. 1998. Jul 15;82(2):239-41. doi: 10.1016/s0002-9149(98)00295-1 [DOI] [PubMed] [Google Scholar]
- 79.Jain SP, Ramee SR, White CJ, et al. Coronary stenting in cardiac allograft vasculopathy. J Am Coll Cardiol. 1998. Nov 15;32(6):1636-40. doi: 10.1016/s0735-1097(98)00432-x [DOI] [PubMed] [Google Scholar]
- 80.Lee MS, Kobashigawa J, Tobis J. Comparison of percutaneous coronary intervention with bare-metal and drug-eluting stents for cardiac allograft vasculopathy. JACC Cardiovasc Interv. 2008. Dec;1(6):710-5. doi: 10.1016/j.jcin.2008.10.001 [DOI] [PubMed] [Google Scholar]
- 81.Lee MS, Lluri G, Finch W, Park KW. Role of Percutaneous Coronary Intervention in the Treatment of Cardiac Allograft Vasculopathy. Am J Cardiol. 2018. May 1;121(9):1051-5. doi: 10.1016/j.amjcard.2018.01.025 [DOI] [PubMed] [Google Scholar]
- 82.Rizvi SSA, Luc JGY, Choi JH, et al. Outcomes and survival following heart retransplantation for cardiac allograft failure: a systematic review and meta-analysis. Ann Cardiothorac Surg. 2018. Jan;7(1):12-8. doi: 10.21037/acs.2018.01.09 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 83.Lund LH, Edwards LB, Kucheryavaya AY, et al. The registry of the International Society for Heart and Lung Transplantation: thirty first official adult heart transplant report--2014; focus theme: retransplantation. J Heart Lung Transplant. 2014. Oct;33(10):996-1008. doi: 10.1016/j.healun.2014.08.003 [DOI] [PubMed] [Google Scholar]
- 84.Goldraich LA, Stehlik J, Kucheryavaya AY, Edwards LB, Ross HJ. Retransplant and Medical Therapy for Cardiac Allograft Vasculopathy: International Society for Heart and Lung Transplantation Registry Analysis. Am J Transplant. 2016. Jan;16(1):301-9. doi: 10.1111/ajt.13418 [DOI] [PubMed] [Google Scholar]
- 85.Alba AC, Fan CS, Manlhiot C, Dipchand AI, Stehlik J, Ross HJ. The evolving risk of sudden cardiac death after heart transplant. An analysis of the ISHLT Thoracic Transplant Registry. Clin Transplant. 2019. Mar;33(3):e13490. doi: 10.1111/ctr.13490 [DOI] [PubMed] [Google Scholar]
- 86.Tsai VW, Cooper J, Garan H, et al. The efficacy of implantable cardioverter-defibrillators in heart transplant recipients: results from a multicenter registry. Circ Heart Fail. 2009. May;2(3):197-201. doi: 10.1161/CIRCHEARTFAILURE.108.814525 [DOI] [PubMed] [Google Scholar]
- 87.Mehra MR, Crespo-Leiro MG, Dipchand A, et al. International Society for Heart and Lung Transplantation working formulation of a standardized nomenclature for cardiac allograft vasculopathy 2010. J Heart Lung Transplant. 2010. Jul;29(7):717-27. doi: 10.1016/j.healun.2010.05.017 [DOI] [PubMed] [Google Scholar]