



Abstract
Purpose
To investigate the diurnal variations of episcleral venous pressure (EVP) and its relationships with IOP, blood pressure, and heart rate in healthy and systemic hypertension subjects.
Methods
Twenty healthy adults and eight patients taking systemic antihypertensive medications were enrolled. IOP and EVP of both eyes, systolic and diastolic blood pressure (SBP and DBP), and heart rate (HR), were measured at five time points, every two hours from 8 AM to 4 PM. IOP was measured by pneumatonometry, and EVP was assessed using a computer-controlled episcleral venomanometer with video recording and image processing. Changes in measurements at each time point were compared with baseline (8 AM) by using generalized estimating equation models. Correlations between EVP and other variables were determined using linear regression analysis.
Results
EVP and IOP were highest in the early morning (8 AM) and lowest in the late afternoon (4 PM), with statistically significant changes (P < 0.05) across all time points compared to baseline in normotensive subjects. Changes in EVP and IOP were correlated at all time points. In treated systemic hypertensive subjects, similar trends were observed, with significant IOP and EVP correlations at multiple time points. No clear pattern of correlation was noted between EVP, SBP, DBP, and HR in all subjects.
Conclusions
IOP and EVP follow a diurnal rhythm with the highest values in the early morning, which gradually decrease throughout the day. The relationship between IOP and EVP suggests that reduction of EVP can be an important target for clinical regulation and stability of IOP.
Keywords: diurnal variation, circadian rhythm, episcleral venous pressure (EVP), IOP, blood pressure, hypertension
The most prevalent risk factor for glaucoma, a progressive neurodegenerative disease of the optic nerve,1 is elevated IOP, and reduction of IOP is currently the only effective treatment for glaucoma. IOP is the result of fluid dynamics of aqueous humor production and removal through various tissues of the outflow system. It has a circadian variation, as well as rapid changes because of multiple factors, a few of which include Valsalva maneuvers, exercise, changes in body position, fluid intake, eye movement, and blinking.2–8 The episcleral veins form the distal portion of the conventional aqueous outflow pathway that begins at the trabecular meshwork, continues in the collector channels and aqueous veins, and drains into the venous system.9–12 The specialized morphology of the episcleral vasculature, with numerous arteriovenous anastomoses and smooth muscle–rich arteries and veins innervated for vasodilation and vasoconstriction, allows regulation of blood flow and volume in the episcleral vessels.13,14 Episcleral venous pressure (EVP) is the pressure that has to be overcome for aqueous humor to leave the eye via the conventional outflow pathway and therefore is a key determinant of IOP15 as it sets a floor value below which IOP cannot drop in a normal or glaucomatous eye. Mean EVP values have been reported between 6.4 and 11 mm Hg in normal subjects, with most recent human studies using objective measurement techniques reporting EVP between 6–8 mm Hg.16–23 The relationship between IOP and EVP remains incompletely understood, with Goldmann's classic model of aqueous humor dynamics describing a 1:1 relationship, but other studies reporting that for every 1 mm Hg increase in EVP, IOP rises by approximately 0.8 mm Hg.24,25 Nevertheless, given the key role of EVP in IOP regulation, there is a need for elucidating the mechanisms of EVP variations, which may consequently help identify novel therapeutic targets for IOP reduction and stabilization.
EVP is influenced by a variety of factors. These include posture,18,19,21,24,26 autonomic nervous system activity,9 and pathologies caused by venous congestion (such as cavernous sinus thrombosis or orbital tumors) or arteriovenous anomalies (such as carotid-cavernous sinus fistula and Sturge Weber syndrome).27–30 Postural changes, such as shifting from a seated to a supine position, can lead to rapid alterations in EVP, with EVP being higher when lying down compared to the sitting position.18,19,31 Additionally, autonomic nervous system activity may modulate EVP by regulating vascular tone and blood flow in the episcleral venous plexus.9
Previous research has suggested that EVP exhibits diurnal variations, with pressure typically being lower in the late afternoon and evening.16–19,32 However, these studies used subjective methodologies and did not describe the relationship between diurnal IOP and EVP variations. To address this, we used a computerized EVP venomanometer,20,22,23,33 which measured EVP by using an objective end point (beginning of collapse of episcleral veins) and investigated the diurnal relationship between EVP, IOP, systemic blood pressure, and heart rate in human subjects.
Methods
Subject Enrollment and Study Criteria
All subjects were brought to the Department of Ophthalmology, Mayo Clinic Rochester, where the study was explained and informed consent was obtained. All measurements were performed in a standard ophthalmic examination room and were administered by trained study personnel. This study was approved by the Institutional Review Board at Mayo Clinic (IRB no. 19-009876) and adhered to the tenets of the Declaration of Helsinki.
Subjects
Subjects were recruited in two groups: (1) healthy group and (2) hypertension group with treated systemic hypertension to assess the effect of systemic antihypertensive medications. Sample size was determined in order to detect a change in EVP as the primary outcome variable. Assuming a mean EVP of 7 mm Hg and standard deviation of 1.5 mm Hg, based on our previous studies in normal subjects,23,34 a sample size of 20 was determined to have a minimum detectable difference of 1.0 mm Hg with a power of 80% (α=0.05, β=0.20, paired t-test).
Eligibility Criteria
Subjects, both male and female, aged 35 years and older, with no history of glaucoma or any other clinically significant eye disease were recruited from local area residents, existing patients, and employees of Mayo Clinic, Rochester, MN. All subjects underwent a screening examination, which included a complete dilated eye examination and a review of existing medical history. Inclusion criteria stipulated that IOP must be less than 24 mm Hg during both the screening examination and baseline visit.
Subjects were included in the healthy group if they did not have a diagnosis of systemic hypertension, were not on any antihypertensive medication, and their systolic blood pressure (SBP) was less than 145 mm Hg, and diastolic blood pressure (DBP) was less than 95 mm Hg. Individuals taking systemic corticosteroids or medications known to affect EVP, IOP, or BP were excluded from the healthy group. Subjects were included in the hypertension group if they had an existing diagnosis of systemic hypertension, and their disease was stable and under medical treatment with antihypertensive medication(s) and SBP <145 mm Hg and DBP <95 mm Hg. Because our primary goal was to evaluate the effect of systemic antihypertensive medications on the diurnal rhythm of EVP, we did not exclude individuals from the hypertension group if they were inadequately controlled based on current hypertension guidelines, nor did we exclude individuals from the healthy group if they had undiagnosed/untreated hypertension, as long as their blood pressure was less than 145/95 mm Hg and not receiving antihypertensive medications.
Other specific exclusion criteria for both groups included any history of intraocular surgery or laser procedure, history of corneal refractive surgery, narrow angles, uveitis, clinically significant retinal disease, myopia greater than −6.00D, or hyperopia greater than 2.00D, and central corneal thickness <480 µm or >620 µm. Women of childbearing potential who were pregnant, nursing, or planning a pregnancy during the study period were excluded from the study.
Measurements
Diurnal patterns of EVP, IOP, BP, and HR were assessed with measurements performed every two hours in a relaxed sitting position between 8 AM and 4 PM, for a total of five time points (8 AM, 10 AM, 12 PM, 2 PM, and 4 PM).
EVP
EVP was measured noninvasively using a custom-designed slit-lamp mounted venomanometer, developed and constructed by the Mayo Clinic Division of Engineering (Fig. 1A). This technique has been used to identify changes in EVP for both investigational and approved drugs.22,23,35 In brief, subjects' eyes were anesthetized with one to two drops of proparacaine. A clear flexible bulb was placed against an episcleral vein (same vessel utilized for all measurements), visualized through a slit-lamp biomicroscope as vessels with a straighter profile and located deeper than conjunctival vessels (Fig. 1B). Pressure in the bulb was increased via a computer-controlled motor drive and recorded with a transducer. Simultaneously, vein collapse was imaged with a high-definition video camera. Pressure measurements were synchronized with the video stream and image analysis software was used to determine the pressure required to begin venous collapse, which corresponds to EVP. The initiation of venous collapse was determined by graphing the peak vessel brightness as a function of applied pressure. Intersection of the fitted line with the horizontal line for the no-collapse phase (mean pressure) represents the beginning of vessel collapse (Fig. 1C). The mean of three measurements was taken for each subject at every time point.
Figure 1.
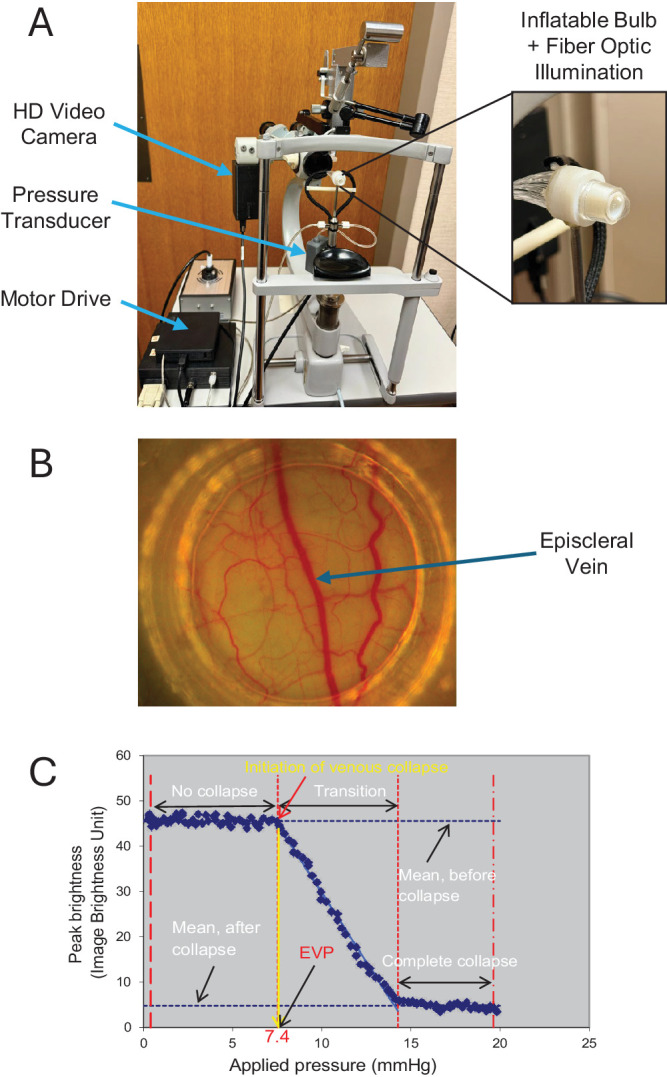
Measuring episcleral venous pressure. (A) Computer controlled slit-lamp mounted episcleral venomanometer with fiber optic illumination. (B) An episcleral vein visualized through the slit-lamp with magnification ×25. (C) Changes in vessel brightness profile across an episcleral vein during episcleral venomanometry.
IOP
IOP was measured noninvasively using a pneumatonometer (Model 30; Reichert Inc., Depew, NY, USA). Three measurements were taken and averaged to increase accuracy and minimize variability in measurements. Prior to each IOP measurement, one to two drops of proparacaine 0.5% as a topical anesthetic was applied to the subjects' eyes.
Blood Pressure, Heart Rate, and Ocular Perfusion Pressure
Blood pressure and heart rate were measured in a relaxed sitting position at each time point, every two hours from 8 AM to 4 PM using an automated digital blood pressure monitor (Omron 10 Series, Omron, Lake Forest, IL, USA). This device provides an average of three readings that was used as the blood pressure and heart rate measurements for a given time point. For each time point, mean arterial blood pressure (MABP) was calculated as the diastolic blood pressure plus one third of the difference between the systolic and the diastolic blood pressures.36 Ocular perfusion pressure (OPP) was calculated using the formulas from Liu et al.,37 which were based on an analysis by Bill.38
This formula accounts for the difference in hydrostatic pressure between the brachial artery measured at the level of the heart and the ophthalmic artery pressure in an upright subject to provide a more appropriate estimate of ocular perfusion pressure.
Statistical Analysis
Measurements at individual time points were compared with 8 AM values using generalized estimating equation (GEE) models. The GEE model was chosen for its robustness in handling correlated data by accounting for potential correlation between eyes of the same subject and suitability for analyzing datasets with repeated measures.39 Correlations between changes in EVP and changes in other variables were determined using linear regression analysis, with statistical significance calculated using GEE models.
All values were expressed in graphs as mean ± standard errors. Standard deviation values are included in the expanded data tables. Correlations and differences between means were considered significant at P < 0.05.
Results
Forty eyes from 20 healthy subjects (five male, 15 females; age 35–64 years; average 45 ± 10 years) and 16 eyes from eight subjects with treated systemic hypertension (one male, seven females; age 38–72 years; average 56 ± 11 years) were enrolled in the study. IOP measurements for each subject at all time points are shown in Fig. 2 and EVP measurements for each subject at all time points are shown in Figure 3. There is significant variability between subjects, and no qualitative difference in pattern between the two groups.
Figure 2.

Individual diurnal IOP measurements for healthy and hypertension subjects. Each line represents measurements for one eye of one subject.
Figure 3.

Individual diurnal EVP measurements for healthy and hypertension subjects. Each line represents measurements for one eye of one subject.
Comparison of IOP, EVP, Blood Pressure, Heart Rate, and OPP at Different Time Points Throughout the Day in Healthy Subjects
In healthy subjects, measurement of EVP and IOP at the 5 time points indicated a clear trend towards highest IOP (18.0 ± 2.0 mm Hg) and EVP (7.8 ± 2.7 mm Hg) in the early morning (8 AM) and lowest (IOP, 16.3 ± 2.3 mm Hg; EVP, 6.7 ± 2.5 mm Hg) in the late afternoon (4 PM) (Table 1). EVP and IOP at 10 AM, 12 PM, 2 PM, and 4PM were all significantly lower compared to measurements taken at the 8 AM time point (Table 1; Fig. 4; P < 0.05). EVP and IOP changes were also significantly correlated to each other for all time points (Table 1; Fig. 5; P < 0.001). However, no significant differences were found across any of the time points for systolic blood pressure (SBP), heart rate (HR), and ocular perfusion pressure (OPP) whereas significant changes in diastolic blood pressure (DBP) were noted at 12 PM and 2 PM compared to the 8 AM measurement (Table 1, P < 0.05). The change in EVP was inversely correlated with change in DBP at 12 PM, HR at 4 PM, and OPP at 12 PM and 2 PM (Table 1).
Table 1.
IOP, EVP, and Blood Pressure Measurements in Healthy Subjects
| EVP (mm Hg) | IOP (mm Hg) | SBP (mm Hg) | DBP (mm Hg) | HR (beats/min) | OPP (mm Hg) | |
|---|---|---|---|---|---|---|
| 8 AM | ||||||
| Mean ± SD | 7.8 ± 2.7 | 18.0 ± 2.0 | 119.8 ± 9.8 | 83.0 ± 7.2 | 73.1 ± 8.0 | 46.6 ± 5.0 |
| 10 AM | ||||||
| Mean ± SD | 7.4 ± 2.7 | 17.2± 2.1 | 120.3 ± 12.0 | 82.4 ± 7.4 | 70.8± 9.2 | 47.3 ± 6.2 |
| Change from 8 AM | −0.5 ± 0.7 | −0.8 ± 1.4 | 0.6 ± 6.0 | −0.6 ± 4.6 | −2.3 ± 7.9 | 0.7 ± 3.6 |
| P | 0.004 | 0.012 | 0.69 | 0.57 | 0.21 | 0.31 |
| Correlation with EVP change (r) | 0.75 | −0.08 | −0.21 | −0.24 | −0.43 | |
| P | <0.001 | 0.88 | 0.44 | 0.30 | 0.17 | |
| 12 PM | ||||||
| Mean ± SD | 7.3 ± 2.7 | 17.2 ± 2.6 | 118.3 ± 13.7 | 80.3 ± 8.8 | 73.1 ± 10.9 | 46.0 ± 7.1 |
| Change from 8 AM | −0.5 ± 0.8 | −0.8 ± 1.7 | −1.5 ± 8.6 | −2.7 ± 5.5 | −0.1 ± 10.3 | −0.6 ± 4.8 |
| P | 0.005 | 0.036 | 0.46 | 0.04 | 0.98 | 0.53 |
| Correlation with EVP change (r) | 0.75 | −0.27 | −0.35 | −0.01 | −0.57 | |
| P | <0.001 | 0.39 | 0.009 | 0.97 | 0.002 | |
| 2 PM | ||||||
| Mean ± SD | 6.8 ± 2.6 | 16.5 ± 2.4 | 118.9 ± 12.5 | 79.5 ± 7.2 | 74.4 ± 8.4 | 46.3 ± 5.7 |
| Change from 8 AM | −1.0 ± 0.7 | −1.5 ± 1.4 | −0.9 ± 8.0 | −3.5 ± 5.5 | 1.3 ± 6.7 | −0.3 ± 4.1 |
| P | <0.001 | <0.001 | 0.64 | 0.01 | 0.40 | 0.68 |
| Correlation with EVP change (r) | 0.64 | 0.04 | −0.25 | −0.21 | −0.35 | |
| P | <0.001 | 0.90 | 0.14 | 0.24 | 0.02 | |
| 4 PM | ||||||
| Mean ± SD | 6.7 ± 2.5 | 16.3 ± 2.3 | 120.8 ± 11.6 | 82.2 ± 7.1 | 71.0 ± 7.8 | 48.2 ± 5.3 |
| Change from 8 AM | −1.2 ± 0.6 | −1.7 ± 1.2 | 1.0 ± 8.0 | −0.8 ± 6.2 | −2.2 ± 7.5 | 1.6 ± 4.2 |
| P | <0.001 | <0.001 | 0.58 | 0.57 | 0.21 | 0.12 |
| Correlation with EVP change (r) | 0.53 | −0.02 | −0.23 | −0.37 | −0.30 | |
| P | <0.001 | 0.93 | 0.09 | 0.005 | 0.053 |
Bolded P values are significant.
Figure 4.

Diurnal changes of IOP (A) and EVP (B) showing significant correlation and similar downward trend across all time points throughout the day in healthy subjects. Error bars show standard error.
Figure 5.

(A) Diurnal IOP and EVP changes (from 8 AM) in healthy subjects. (B) Correlation between IOP and EVP changes in healthy subjects. Each point represents the mean of three measurements taken at every time point for each subject.
In healthy subjects, mean of SBP at all timepoints (n = 100) was 119.6 ± 11.8 mm Hg with 95% confidence interval (CI) of 115.0–124.8 mm Hg. Mean DBP was 81.5 ± 7.5 mm Hg with 95% CI of 78.3–84.5 mm Hg.
Comparison of IOP, EVP, Blood Pressure, Heart Rate, and OPP of Patients with Systemic Hypertension at Different Time Points Throughout the Day
Similar to healthy subjects, EVP in patients with systemic hypertension was also found to be highest (8.0 ± 2.3 mm Hg) at 8 AM, with all other time points significantly lower, and the lowest EVP (6.9 ± 2.5 mm Hg) noted at 2 PM (Table 2; Fig. 6; P < 0.05). IOP also showed an overall downward trend, with highest values observed at 8 AM (18.7 ± 3.1 mm Hg), and values for all time points except 12 PM were significantly lower (Table 2; Fig. 6). All IOP changes correlated significantly with EVP changes at all time points including the 12 PM timepoint. (Table 2; Fig. 7; P < 0.001). Unlike EVP and IOP, SBP and DBP did not show any specific trend and changes in these parameters did not correlate with changes in EVP, except at the 2 PM time point. No diurnal changes or correlation with EVP were noted with OPP or HR across the time points.
Table 2.
EVP, IOP, and Blood Pressure Measurements in Systemic Hypertension Patients
| EVP (mm Hg) | IOP (mm Hg) | SBP (mm Hg) | DBP (mm Hg) | HR (beats/min) | OPP (mm Hg) | |
|---|---|---|---|---|---|---|
| 8 AM | ||||||
| Mean ± SD | 8.0 ± 2.3 | 18.7 ± 3.1 | 128.8 ± 9.5 | 85.8 ± 7.0 | 72.3 ± 7.9 | 49.2 ± 5.5 |
| 10 AM | ||||||
| Mean ± SD | 7.0 ± 2.2 | 17.4± 3.1 | 129.4 ± 9.4 | 84.6 ± 6.3 | 69.4± 4.7 | 50.1 ± 4.9 |
| Change from 8 AM | −1.0 ± 0.5 | −1.3 ± 0.8 | 0.6 ± 8.9 | −1.1 ± 6.1 | −2.9 ± 6.5 | 0.9 ± 4.2 |
| P | <0.001 | <0.001 | 0.85 | 0.62 | 0.25 | 0.52 |
| Correlation with EVP change (r) | 0.71 | 0.33 | 0.33 | −0.20 | 0.23 | |
| P | <0.001 | 0.20 | 0.09 | 0.47 | 0.40 | |
| 12 PM | ||||||
| Mean ± SD | 7.5 ± 2.3 | 18.4 ± 2.7 | 126.5 ± 12.5 | 84.4 ± 9.9 | 74.6 ± 11.7 | 48.4 ± 7.1 |
| Change from 8 AM | −0.4 ± 0.7 | −0.3 ± 1.2 | −2.3 ± 13.9 | −1.4 ± 5.9 | 2.4 ± 9.6 | −0.8 ± 5.3 |
| P | 0.046 | 0.36 | 0.66 | 0.53 | 0.51 | 0.67 |
| Correlation with EVP change (r) | 0.81 | 0.08 | 0.13 | 0.03 | −0.08 | |
| P | <0.001 | 0.84 | 0.75 | 0.79 | 0.60 | |
| 2 PM | ||||||
| Mean ± SD | 6.9 ± 2.5 | 17.3 ± 2.6 | 129.5 ± 14.6 | 84.1 ± 9.6 | 73.1 ± 8.1 | 50.1 ± 6.5 |
| Change from 8 AM | −1.1 ± 0.9 | −1.4 ± 1.7 | 0.8 ± 16.0 | −1.6 ± 7.3 | 0.9 ± 9.0 | 0.9 ± 6.1 |
| P | <0.001 | 0.01 | 0.90 | 0.55 | 0.79 | 0.68 |
| Correlation with EVP change (r) | 0.86 | 0.52 | 0.58 | −0.31 | 0.36 | |
| P | <0.001 | 0.002 | 0.006 | 0.18 | 0.12 | |
| 4 PM | ||||||
| Mean ± SD | 7.3 ± 2.6 | 17.6 ± 2.6 | 136.4 ± 18.8 | 88.3 ± 11.4 | 69.5 ± 7.8 | 53.2 ± 8.6 |
| Change from 8 AM | −0.7 ± 1.0 | −1.1 ± 1.6 | 7.6 ± 18.1 | 2.5 ± 67.1 | −2.8 ± 6.4 | 3.9 ± 6.6 |
| P | 0.04 | 0.03 | 0.27 | 0.35 | 0.26 | 0.08 |
| Correlation with EVP change (r) | 0.82 | 0.40 | 0.34 | 0.12 | 0.20 | |
| P | <0.001 | 0.06 | 0.20 | 0.70 | 0.99 |
Bolded P values are significant.
Figure 6.

Diurnal changes of IOP (A) and EVP (B) showing significant correlation and similar downward trend across most time points throughout the day in patients with systemic hypertension. Error bars show standard error.
Figure 7.

(A) Diurnal IOP and EVP changes (from 8 AM) in systemic hypertension subjects. (B) Correlation between IOP and EVP changes in systemic hypertension subjects. Each point represents the mean of three measurements taken at every time point for each subject.
In hypertensive subjects, mean of SBP at all timepoints (n = 40) was 130.1 ± 13.2 mm Hg with 95% CI of 123.3 – 136.9 mm Hg. Mean DBP was 85.4 ± 8.7 mm Hg with 95% CI of 80.2 – 90.7 mm Hg.
Comparison of IOP and EVP Change From Baseline Between Healthy Subjects and Systemic Hypertension Patients
When comparing the change in IOP and change in EVP between healthy subjects and hypertensive patients, there were no significant differences at any time point between the two groups (Table 3). Changes in IOP and EVP at most time points in both groups were not correlated to the baseline BP (SBP and DBP), except at 10 AM with DBP in the hypertension group for the IOP and EVP changes and 12 PM with SBP in the healthy group for the EVP change (Table 4).
Table 3.
Comparison of IOP and EVP Change From Baseline Between Healthy Subjects and Systemic Hypertension Patients
| EVP Change From 8 AM (mm Hg) | IOP Change From 8 AM (mm Hg) | |||||||
|---|---|---|---|---|---|---|---|---|
| Healthy | HTN | Difference (95% CI) | P | Healthy | HTN | Difference (95% CI) | P | |
| 10 AM | −0.5 ± 0.7 | −1.0 ± 0.5 | −0.53 (−0.90 to 0.48) | 0.81 | −0.8 ± 1.4 | −1.3 ± 0.8 | −0.45 (−1.17 to 0.26) | 0.51 |
| 12 PM | −0.5 ± 0.8 | −0.4 ± 0.7 | 0.09 (−0.37 to 0.54) | 0.87 | −0.8 ± 1.7 | −0.3 ± 1.2 | 0.43 (−0.45 to 1.33) | 0.34 |
| 2 PM | −1.0 ± 0.7 | −1.1 ± 0.9 | −0.02 (−0.46 to 0.43) | 0.60 | −1.5 ± 1.4 | −1.4 ± 1.7 | −0.06 (−0.78 to 0.89) | 0.92 |
| 4 PM | −1.2 ± 0.6 | −0.7 ± 1.0 | 0.51 (−0.17 to 0.90) | 0.18 | −1.7 ± 1.2 | −1.1 ± 1.6 | 0.65 (−0.09 to 1.39) | 0.72 |
HTN, hypertension.
Table 4.
Significance of Correlation Between Baseline BP and EVP Change and IOP Change in Healthy Subjects and Systemic Hypertension Patients
| Significance of Correlation (P) With EVP Change | Significance of Correlation (P) With IOP Change | |||||||
|---|---|---|---|---|---|---|---|---|
| Healthy | HTN | Healthy | HTN | |||||
| SBP | DBP | SBP | DBP | SBP | DBP | SBP | DBP | |
| 10 AM | 0.10 | 0.39 | 0.16 | 0.04 | 0.25 | 0.60 | 0.37 | <0.001 |
| 12 PM | 0.02 | 0.17 | 0.64 | 0.54 | 0.44 | 0.33 | 0.89 | 0.90 |
| 2 PM | 0.25 | 0.76 | 0.36 | 0.94 | 0.21 | 0.98 | 0.58 | 0.79 |
| 4 PM | 0.15 | 0.59 | 0.43 | 0.38 | 0.89 | 0.99 | 0.98 | 0.97 |
HTN, hypertension.
Discussion
The relationship between IOP and EVP is important in understanding IOP homeostasis and pathophysiology of ocular hypertensive diseases. Elevated IOP can result from increased resistance to aqueous humor outflow through the trabecular meshwork, Schlemm's canal, collector channels and the more distal episcleral vasculature. EVP directly influences IOP by setting the back pressure against which aqueous humor must drain and re-enter the ocular venous circulation. The modified Goldmann equation models IOP as varying in a 1:1 manner under steady state conditions, and studies in animal models have shown a significant correlation between IOP and EVP.40–42 Furthermore, it is well accepted that venous congestion and arteriovenous anomalies that occur in conditions such as cavernous sinus thrombosis, orbital tumors, Sturge Weber syndrome, and carotid-cavernous sinus fistula will lead to elevated EVP and glaucoma with elevated IOP.27–30 However, evidence of synchronous variations in EVP and IOP in human subjects has been lacking until now.
The current study investigated the diurnal variations of IOP, EVP, OPP, blood pressure and heart rates across multiple time points in both healthy individuals and those with treated systemic hypertension. Our results show a consistent trend of higher IOP and EVP in the mornings, followed by a decline throughout the day in both groups. These findings are consistent with previous studies which have reported higher IOP in the morning and lower values in the later afternoon or evening,43–52 and no difference in OPP during the diurnal period.37 However, those studies did not measure EVP concurrently with IOP. Similar relationships between changes in EVP and IOP in healthy eyes has previously been observed by Blondeau et al.18 They found that changes in IOP were correlated with the changes in EVP throughout the day and the values of IOP and EVP were lower in mid afternoon and evening. However, that study used subjective endpoints for the measurement of EVP making it difficult to fully interpret the correlation with IOP.
Our study was limited to the assessment of diurnal changes as nocturnal EVP measurements are logistically challenging and were outside of the scope of this study. In a previous study from our group, we compared aqueous humor dynamics in the mid-diurnal period (2–4 PM) with the mid-nocturnal period (2–4 AM) and found no difference in EVP.53 However, there are two important caveats concerning nocturnal EVP measurement. First, all EVP measurements using our technique are performed using a slit-lamp mounted device and do not allow for measurements in the supine position, even though EVP is known to change with body position.21 Second, measurements of EVP are technically challenging and require significantly more time than IOP measurements. It would therefore be difficult to perform these measurements in a manner that does not disturb sleep and the circadian rhythm, which may alter EVP. Further advancements in the technique and technology for EVP measurement are required to fully investigate its circadian rhythm.
Several studies found that other parameters like corneal thickness, corneal curvature, and axial length showed significant diurnal changes.52,54–61 CCT was found to increase overnight during sleep hours, peaking right after awakening and returns to baseline two to three hours after awakening.52,61 We performed the first set of our measurement starting at 8 AM which was around two to three hours after awakening. Therefore, at the time of the first measurements of the study day, corneal thickness should have returned to baseline levels. Between 8 AM to 4 PM, the change in CCT reported by Read et al. is less than 3 µm, which equates to approximately 0.5% in healthy eyes.52 In a meta-analysis, Doughty and Zaman62 reported that a 1.1 mm Hg difference in IOP measurement could be expected for a 10% change in CCT, and a 0.5% change in CCT would therefore produce a negligible change in IOP.
IOP variations, including diurnal and circadian modulations, have been identified as a risk factor for glaucoma progression in several clinical studies.63–66 The finding of a strong correlation between EVP and IOP indicates a dependency between these two parameters. Therefore, it is logical to hypothesize that clinical management plans for glaucomatous pathologies may benefit from compounds targeting EVP along with IOP. At present, there are limited therapeutic options available for modulating EVP. Among commonly available ocular hypotensive medications, netarsudil has been shown to decrease EVP by approximately 10% in normal human subjects, as well as ocular hypertension and open-angle glaucoma patients.23,35 Apraclonidine was reported to reduce EVP by approximately 1 mm Hg in normal subjects and ocular hypertension patients, although that study did not use objective measurements of EVP.67 Topical phenylephrine 2.5% also reduces EVP by approximately 1 mm Hg in normal subjects but does not have a significant effect on IOP.22 Given the small effect or limited duration of action, current medications do not appear to be suitable options for therapeutic modulation of EVP as a primary mechanism of action. However, novel compounds currently in development may provide options. In particular, ATP sensitive potassium (KATP) channel openers, such as cromakalim prodrug 1 (CKLP1), QLS-101, and QLS-111, have been shown to produce robust ocular hypotensive effects through direct reduction of EVP as the primary mechanism of action in normotensive and ocular hypertensive animal model systems.68,69 Our results elucidate a direct and significant physiological link between EVP and IOP and provide further evidence that targeting EVP may be a necessary therapeutic paradigm for better management of glaucoma. These results help to understand the relationship between EVP changes and IOP fluctuations in response to diurnal variations, further aiding in development of precise therapeutic approaches that capitalize on favorable EVP conditions to optimize aqueous humor drainage and reduce IOP burden.
Although there were no consistent diurnal trends for SBP, DBP, HR, and OPP, significant correlations with changes in EVP did occur at some time points for DBP, HR, and OPP in healthy subjects and SBP and DBP in hypertensive subjects. The significance of this is unclear, and the findings may have been due to random variation as the correlations were moderate to weak for these parameters. Furthermore, for DBP there were negative correlations in healthy subjects but a positive correlation in hypertensive subjects. The weak or absent correlation between systemic BP and EVP indicates a lack of functional linkage between EVP and systemic blood pressure parameters, suggesting that diurnal EVP regulation may occur independent of systemic BP.
The precise mechanisms by which EVP is regulated are unclear. One theory suggested by Zamora and Kiel hypothesizes that EVP may be controlled through regulation between the arterial and venous circulation of the episcleral blood supply.70 In a rat model, EVP appears to be controlled neuronally by the superior salivatory nucleus, with separate control of the limbal and episcleral vessels.15,71 However, whether or not similar control mechanisms exist in humans is unclear. Our results are also limited in our study of patients with systemic hypertension, as all of them were using oral medications to control their blood pressure. This may affect the relationship between blood pressure and EVP although understanding the extent of variability introduced by these medications is beyond the scope of this study. Nevertheless, further research is required to fully elucidate the relationship between EVP and BP in humans.
In summary, IOP and EVP both follow a similar diurnal rhythm with highest values in the early morning that gradually decrease throughout the day. Variations in systemic blood pressure and heart rate appear to have minimal effect on IOP or EVP. These results suggest that modulation of EVP may be an important and novel therapeutic target for reduction of IOP and minimization of diurnal IOP variations in glaucoma patients and those at risk for glaucoma.
Acknowledgments
Supported by Qlaris Bio Inc., Mayo Foundation for Medical Education and Research, Presented in part at the annual meeting of the Association for Research in Vision and Ophthalmology (ARVO) 2023, New Orleans, LA.
Disclosure: A. Kazemi, None; U. Roy Chowdhury, Qlaris Bio, Inc. (E); M.P. Fautsch, Qlaris Bio, Inc. (O, C); T.M. Htoo, Qlaris Bio, Inc. (E); B.M. Wirostko, Qlaris Bio, Inc. (E); D.O. Hodge, None; A.J. Sit, Globe Biomedical, Inc. (C, I); Injectsense, Inc. (C, I); Nicox Ophthalmics, Inc. (F); PolyActiva, Pty (C); Qlaris Bio, Inc. (C, F); Santen Pharmaceuticals Asia, Pty (C)
References
- 1. Weinreb RN, Khaw PT. Primary open-angle glaucoma. Lancet. 2004; 363: 1711–1720. [DOI] [PubMed] [Google Scholar]
- 2. Galin MA, Mc IJ, Magruder GB. Influence of position on intraocular pressure. Am J Ophthalmol. 1963; 55: 720–723. [PubMed] [Google Scholar]
- 3. Lam AK, Douthwaite WA. Does the change of anterior chamber depth or/and episcleral venous pressure cause intraocular pressure change in postural variation? Optom Vis Sci. 1997; 74: 664–667. [DOI] [PubMed] [Google Scholar]
- 4. Morris HJ, Tang J, Cruz Perez B, et al.. Correlation between biomechanical responses of posterior sclera and IOP elevations during micro intraocular volume change. Invest Ophthalmol Vis Sci. 2013; 54: 7215–7222. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 5. Anderson DR, Grant WM. The influence of position on intraocular pressure. Invest Ophthalmol. 1973; 12: 204–212. [PubMed] [Google Scholar]
- 6. Weinreb RN, Cook J, Friberg TR. Effect of inverted body position on intraocular pressure. Am J Ophthalmol. 1984; 98: 784–787. [DOI] [PubMed] [Google Scholar]
- 7. Susanna R Jr., Vessani RM, Sakata L, Zacarias LC, Hatanaka M. The relation between intraocular pressure peak in the water drinking test and visual field progression in glaucoma. Br J Ophthalmol. 2005; 89: 1298–1301. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 8. Sakata R, Aihara M, Murata H, et al.. Intraocular pressure change over a habitual 24-hour period after changing posture or drinking water and related factors in normal tension glaucoma. Invest Ophthalmol Vis Sci. 2013; 54: 5313–5320. [DOI] [PubMed] [Google Scholar]
- 9. McDougal DH, Gamlin PD. Autonomic control of the eye. Compr Physiol. 2015; 5: 439–473. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 10. Ashton N. Anatomical study of Schlemm's canal and aqueous veins by means of neoprene casts. Part I. Aqueous veins. Br J Ophthalmol. 1951; 35: 291–303. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 11. Ashton N. Anatomical study of Schlemm's canal and aqueous veins by means of neoprene casts. II. Aqueous veins. Br J Ophthalmol. 1952; 36: 265–267. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 12. Ashton N, Smith R. Anatomical study of Schlemm's canal and aqueous veins by means of neoprene casts. III. Arterial relations of Schlemm's canal. Br J Ophthalmol. 1953; 37: 577–586. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 13. Selbach JM, Schonfelder U, Funk RH. Arteriovenous anastomoses of the episcleral vasculature in the rabbit and rat eye. J Glaucoma. 1998; 7: 50–57. [PubMed] [Google Scholar]
- 14. Selbach JM, Rohen JW, Steuhl KP, Lutjen-Drecoll E. Angioarchitecture and innervation of the primate anterior episclera. Curr Eye Res. 2005; 30: 337–344. [DOI] [PubMed] [Google Scholar]
- 15. Strohmaier CA, Reitsamer HA, Kiel JW. Episcleral venous pressure and IOP responses to central electrical stimulation in the rat. Invest Ophthalmol Vis Sci. 2013; 54: 6860–6866. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16. Zeimer RC, Gieser DK, Wilensky JT, Noth JM, Mori MM, Odunukwe EE. A practical venomanometer. Measurement of episcleral venous pressure and assessment of the normal range. Arch Ophthalmol. 1983; 101: 1447–1449. [DOI] [PubMed] [Google Scholar]
- 17. Phelps CD, Armaly MF. Measurement of episcleral venous pressure. Am J Ophthalmol. 1978; 85: 35–42. [DOI] [PubMed] [Google Scholar]
- 18. Blondeau P, Tetrault JP, Papamarkakis C. Diurnal variation of episcleral venous pressure in healthy patients: a pilot study. J Glaucoma. 2001; 10: 18–24. [DOI] [PubMed] [Google Scholar]
- 19. Sultan M, Blondeau P. Episcleral venous pressure in younger and older subjects in the sitting and supine positions. J Glaucoma. 2003; 12: 370–373. [DOI] [PubMed] [Google Scholar]
- 20. Sit AJ, McLaren JW. Measurement of episcleral venous pressure. Exp Eye Res. 2011; 93: 291–298. [DOI] [PubMed] [Google Scholar]
- 21. Arora N, McLaren JW, Hodge DO, Sit AJ. Effect of body position on epsicleral venous pressure in healthy subjects. Invest Ophth Vis Sci. 2017; 58: 5151–5156. [DOI] [PubMed] [Google Scholar]
- 22. Kazemi A, McLaren JW, Sit AJ. Effect of topical phenylephrine 2.5% on episcleral venous pressure in normal human eyes. Invest Ophthalmol Vis Sci. 2021; 62: 4. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 23. Kazemi A, McLaren JW, Kopczynski CC, Heah TG, Novack GD, Sit AJ. The effects of netarsudil ophthalmic solution on aqueous humor dynamics in a randomized study in humans. J Ocul Pharmacol Ther. 2018; 34: 380–386. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 24. Friberg TR, Sanborn G, Weinreb RN. Intraocular and episcleral venous pressure increase during inverted posture. Am J Ophthalmol. 1987; 103: 523–526. [DOI] [PubMed] [Google Scholar]
- 25. Selbach JM, Posielek K, Steuhl KP, Kremmer S. Episcleral venous pressure in untreated primary open-angle and normal-tension glaucoma. Ophthalmologica. 2005; 219: 357–361. [DOI] [PubMed] [Google Scholar]
- 26. Leith AB. Episcleral venous pressure in tonography. Br J Ophthalmol. 1963; 47: 271–278. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27. Bigger JF. Glaucoma with elevated episcleral venous pressure. South Med J. 1975; 68: 1444–1448. [DOI] [PubMed] [Google Scholar]
- 28. Weinreb RN. Glaucoma secondary to elevated episcleral venous pressure. In: Ritch R, Shields MB, Krupin T. , eds. The Glaucomas . St. Louis: Mosby; 1989: 1127–1140. [Google Scholar]
- 29. Greenfield DS. Glaucoma associated with elevated episcleral venous pressure. J Glaucoma. 2000; 9: 190–194. [DOI] [PubMed] [Google Scholar]
- 30. Celebi S, Alagoz G, Aykan U. Ocular findings in Sturge-Weber syndrome. Eur J Ophthalmol. 2000; 10: 239–243. [DOI] [PubMed] [Google Scholar]
- 31. Kaskel D, Muller-Breitenkamp R, Wilmans I, Rudolf H, Jessen K. [The influence of changes in body position on intraocular pressure, episcleral venous pressure, and blood pressure (author's transl)]. Albrecht Von Graefes Arch Klin Exp Ophthalmol. 1978; 208: 217–228. [DOI] [PubMed] [Google Scholar]
- 32. Friberg TR. Portable transducer for measurement of episcleral venous pressure. Am J Ophthalmol. 1986; 102: 396–397. [DOI] [PubMed] [Google Scholar]
- 33. Sit AJ, Ekdawi NS, Malihi M, McLaren JW. A novel method for computerized measurement of episcleral venous pressure in humans. Exp Eye Res. 2011; 92: 537–544. [DOI] [PubMed] [Google Scholar]
- 34. Reitinger JC, Reed DM, Peres C, et al. Understanding individual intraocular pressure response to treatment with latanoprost and timolol. J Ocul Pharmacol Ther 2025; 41: 251–258. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 35. Sit AJ, Gupta D, Kazemi A, et al.. Netarsudil Improves Trabecular outflow facility in patients with primary open angle glaucoma or ocular hypertension: a Phase 2 study. Am J Ophthalmol. 2021; 226: 262–269. [DOI] [PubMed] [Google Scholar]
- 36. Papaioannou TG, Protogerou AD, Vrachatis D, et al.. Mean arterial pressure values calculated using seven different methods and their associations with target organ deterioration in a single-center study of 1878 individuals. Hypertens Res. 2016; 39: 640–647. [DOI] [PubMed] [Google Scholar]
- 37. Liu JH, Gokhale PA, Loving RT, Kripke DF, Weinreb RN. Laboratory assessment of diurnal and nocturnal ocular perfusion pressures in humans. J Ocul Pharmacol Ther. 2003; 19: 291–297. [DOI] [PubMed] [Google Scholar]
- 38. Bill A. Physiological aspects of the circulation in the optic nerve. In: Heilmann K (ed), Glaucoma: Conceptions of a Disease . Philadelphia: W.B. Saunders; 1978: 97–103. [Google Scholar]
- 39. Zeger SL, Liang KY, Albert PS. Models for longitudinal data: a generalized estimating equation approach. Biometrics. 1988; 44: 1049–1060. [PubMed] [Google Scholar]
- 40. Lavery WJ, Kiel JW. Effects of head down tilt on episcleral venous pressure in a rabbit model. Exp Eye Res. 2013; 111: 88–94. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 41. Funk RH, Gehr J, Rohen JW. Short-term hemodynamic changes in episcleral arteriovenous anastomoses correlate with venous pressure and IOP changes in the albino rabbit. Curr Eye Res. 1996; 15: 87–93. [DOI] [PubMed] [Google Scholar]
- 42. Wong VHY, Zhao D, Bui BV, Millar CJ, Nguyen CTO. Increased episcleral venous pressure in a mouse model of circumlimbal suture induced ocular hypertension. Exp Eye Res. 2021; 202: 108348. [DOI] [PubMed] [Google Scholar]
- 43. De Venecia G, Davis MD. Diurnal variation of intraocular pressure in the normal eye. Arch Ophthalmol. 1963; 69: 752–757. [DOI] [PubMed] [Google Scholar]
- 44. Drance SM. The significance of the diurnal tension variations in normal and glaucomatous eyes. Arch Ophthalmol. 1960; 64: 494–501. [DOI] [PubMed] [Google Scholar]
- 45. Liu JH, Kripke DF, Hoffman RE, et al.. Nocturnal elevation of intraocular pressure in young adults. Invest Ophthalmol Vis Sci. 1998; 39: 2707–2712. [PubMed] [Google Scholar]
- 46. Liu JH, Kripke DF, Twa MD, et al.. Twenty-four-hour pattern of intraocular pressure in the aging population. Invest Ophthalmol Vis Sci. 1999; 40: 2912–2917. [PubMed] [Google Scholar]
- 47. Liu JH, Zhang X, Kripke DF, Weinreb RN. Twenty-four-hour intraocular pressure pattern associated with early glaucomatous changes. Invest Ophthalmol Vis Sci. 2003; 44: 1586–1590. [DOI] [PubMed] [Google Scholar]
- 48. Newell FW, Krill AE. Diurnal tonography in normal and glaucomatous eyes. Am J Ophthalmol. 1965; 59: 840–853. [DOI] [PubMed] [Google Scholar]
- 49. Sacca SC, Rolando M, Marletta A, Macri A, Cerqueti P, Ciurlo G. Fluctuations of intraocular pressure during the day in open-angle glaucoma, normal-tension glaucoma and normal subjects. Ophthalmologica. 1998; 212: 115–119. [DOI] [PubMed] [Google Scholar]
- 50. Wilensky JT, Gieser DK, Dietsche ML, Mori MT, Zeimer R. Individual variability in the diurnal intraocular pressure curve. Ophthalmology. 1993; 100: 940–944. [DOI] [PubMed] [Google Scholar]
- 51. Chakraborty R, Read SA, Collins MJ. Diurnal variations in axial length, choroidal thickness, intraocular pressure, and ocular biometrics. Invest Ophthalmol Vis Sci. 2011; 52: 5121–5129. [DOI] [PubMed] [Google Scholar]
- 52. Read SA, Collins MJ, Iskander DR. Diurnal variation of axial length, intraocular pressure, and anterior eye biometrics. Invest Ophthalmol Vis Sci. 2008; 49: 2911–2918. [DOI] [PubMed] [Google Scholar]
- 53. Nau CB, Malihi M, McLaren JW, Hodge DO, Sit AJ. Circadian variation of aqueous humor dynamics in older healthy adults. Invest Ophthalmol Vis Sci. 2013; 54: 7623–7629. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 54. Read SA, Collins MJ. Diurnal variation of corneal shape and thickness. Optom Vis Sci. 2009; 86: 170–180. [DOI] [PubMed] [Google Scholar]
- 55. Kiely PM, Carney LG, Smith G. Diurnal variations of corneal topography and thickness. Am J Optom Physiol Opt. 1982; 59: 976–982. [DOI] [PubMed] [Google Scholar]
- 56. Harper CL, Boulton ME, Bennett D, et al.. Diurnal variations in human corneal thickness. Br J Ophthalmol. 1996; 80: 1068–1072. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 57. Feng Y, Varikooty J, Simpson TL. Diurnal variation of corneal and corneal epithelial thickness measured using optical coherence tomography. Cornea. 2001; 20: 480–483. [DOI] [PubMed] [Google Scholar]
- 58. du Toit R, Vega JA, Fonn D, Simpson T. Diurnal variation of corneal sensitivity and thickness. Cornea. 2003; 22: 205–209. [DOI] [PubMed] [Google Scholar]
- 59. Handa T, Mukuno K, Niida T, Uozato H, Tanaka S, Shimizu K. Diurnal variation of human corneal curvature in young adults. J Refract Surg. 2002; 18: 58–62. [DOI] [PubMed] [Google Scholar]
- 60. Read SA, Collins MJ, Carney LG. The diurnal variation of corneal topography and aberrations. Cornea. 2005; 24: 678–687. [DOI] [PubMed] [Google Scholar]
- 61. Hamilton KE, Pye DC, Aggarwala S, Evian S, Khosla J, Perera R. Diurnal variation of central corneal thickness and Goldmann applanation tonometry estimates of intraocular pressure. J Glaucoma. 2007; 16: 29–35. [DOI] [PubMed] [Google Scholar]
- 62. Doughty MJ, Zaman ML. Human corneal thickness and its impact on intraocular pressure measures: a review and meta-analysis approach. Surv Ophthalmol. 2000; 44: 367–408. [DOI] [PubMed] [Google Scholar]
- 63. De Moraes CG, Mansouri K, Liebmann JM, Ritch R, Triggerfish C. Association between 24-hour intraocular pressure monitored with contact lens sensor and visual field progression in older adults with glaucoma. JAMA Ophthalmol. 2018; 136: 779–785. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 64. Asrani S, Zeimer R, Wilensky J, Gieser D, Vitale S, Lindenmuth K. Large diurnal fluctuations in intraocular pressure are an independent risk factor in patients with glaucoma. J Glaucoma. 2000; 9: 134–142. [DOI] [PubMed] [Google Scholar]
- 65. Caprioli J, Coleman AL. Intraocular pressure fluctuation a risk factor for visual field progression at low intraocular pressures in the advanced glaucoma intervention study. Ophthalmology. 2008; 115: 1123–1129.e1123. [DOI] [PubMed] [Google Scholar]
- 66. Sit AJ. Intraocular pressure variations: causes and clinical significance. Can J Ophthalmol. 2014; 49: 484–488. [DOI] [PubMed] [Google Scholar]
- 67. Toris CB, Tafoya ME, Camras CB, Yablonski ME. Effects of apraclonidine on aqueous humor dynamics in human eyes. Ophthalmology. 1995; 102: 456–461. [DOI] [PubMed] [Google Scholar]
- 68. Roy Chowdhury U, Millar JC, Holman BH, et al.. Effect of ATP-sensitive Potassium Channel Openers on Intraocular Pressure in Ocular Hypertensive Animal Models. Invest Ophthalmol Vis Sci. 2022; 63: 15. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 69. Roy Chowdhury U, Rinkoski TA, Bahler CK, et al.. Effect of cromakalim prodrug 1 (CKLP1) on aqueous humor dynamics and feasibility of combination therapy with existing ocular hypotensive agents. Invest Ophthalmol Vis Sci. 2017; 58: 5731–5742. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 70. Zamora DO, Kiel JW. Episcleral venous pressure responses to topical nitroprusside and N-Nitro-L-arginine methyl ester. Invest Ophthalmol Vis Sci. 2010; 51: 1614–1620. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 71. Strohmaier CA, Kiel JW, Reitsamer HA. Episcleral venous pressure response to brain stem stimulation: effect of topical lidocaine. Exp Eye Res. 2021; 212: 108766. [DOI] [PubMed] [Google Scholar]