



Abstract
Abstract
Rheumatoid arthritis (RA) is a persistent autoimmune disorder where serological biomarkers play a crucial role in diagnosis and monitoring disease activity. Antibodies targeting cyclic citrullinated peptides (anti-CCP), mutated citrullinated vimentin (anti-MCV), and rheumatoid factor are commonly used serological markers for RA. However, their respective diagnostic efficacies and potential for mutual complementation remain incompletely understood. This study investigates the diagnostic performance of these three antibodies and their association with disease progression in RA. A total of 257 RA patients who visited Jinhua Hospital Affiliated with Zhejiang University between March and December 2019 were enrolled. Serum specimens were analyzed for anti-CCP, anti-MCV antibodies, and RF levels using chemiluminescence immunoassay (CLIA) and rate nephelometry. The results indicated that the specificity of anti-CCP (94.2%) was higher than that of anti-MCV (84.4%) and RF (84.8%). Furthermore, anti-MCV antibody levels were significantly link to disease duration and morning stiffness. Additionally, anti-MCV and anti-CCP demonstrated differing associations with extra-articular manifestations of RA. The study suggests that anti-MCV antibodies hold significant potential as adjunctive biomarkers in RA, complementing anti-CCP antibodies to improve diagnostic accuracy and provide new insights for early diagnosis and disease monitoring in RA.
Graphical abstract
Complementary Roles and Clinical Significance of Anti-CCP Antibody, Anti-MCV Antibody, and RF in RA Diagnosis.
Keywords: Rheumatoid arthritis, Anti-CCP, Anti-MCV, Serological markers, Disease progression, Diagnostic performance
Introduction
Rheumatoid arthritis (RA) is a systemic autoimmune disorder marked by persistent, symmetric polyarthritis. Its pathological mechanism involves the dysregulated immune responses, which promote synovial hyperplasia, progressive erosion of cartilage and bone, and ultimately lead to joint deformities and functional impairment [1]. RA primarily affects small joints, particularly those of the hands and feet, and is also frequently associated with various extra-articular manifestations, including involvement of the lungs, kidneys, and cardiovascular system, as well as overlapping symptoms with other autoimmune diseases [2, 3]. The global prevalence of RA is approximately 0.5–1%, with incidence influenced by geographic, demographic, and genetic factors. Among these, sex and age are the most consistent epidemiological features, with women disproportionately affected and incidence rising with advancing age. Globally, RA remains a major contributor to disability and reduced work capacity [4, 5]. Early diagnosis and intervention are critical for delaying disease progression and improving patient outcomes. Currently, the diagnosis of RA relies on clinical manifestations, imaging studies, and serological biomarkers [6–8].
Among the serological biomarkers, rheumatoid factor (RF) and anti-cyclic citrullinated peptide (anti-CCP) antibodies are the most commonly utilized [9]. However, RF exhibits low sensitivity during the early stages of RA and may yield false-positive results in individuals with infectious diseases and the elderly [10, 11]. Although anti-CCP antibody has high specificity, its sensitivity remains suboptimal in early RA [12]. Therefore, identifying more sensitive and specific biomarkers has become a key focus in RA research. In recent years, antibodies targeting mutated citrullinated vimentin (anti-MCV) antibodies have been identified as a novel biomarker, garnering increasing attention in the academic community [13, 14]. Studies suggest that anti-MCV antibodies may exhibit high sensitivity and specificity in the diagnosis of RA [15, 16], particularly in patients with early-stage RA. For example, a study involving 500 RA patients reported that it achieved a sensitivity of 75% and specificity of 95%, significantly outperforming RF and anti-CCP antibodies [17]. However, the extent to which anti-MCV, anti-CCP, and RF serve complementary diagnostic functions remains controversial. Some studies suggest that anti-MCV and anti-CCP antibodies exhibit high diagnostic consistency, while others report independent positive results in certain patients, indicating potential differences in their pathophysiological significance [18, 19]. Additionally, the associations between anti-MCV antibody levels and clinical indices such as disease activity, joint damage, and extra-articular manifestations require further validation.
Although anti-CCP antibodies and RF have played significant roles in diagnosing RA, their limitations have driven researchers to explore new biomarkers [12, 20]. Anti-MCV antibody, a novel biomarker, has shown potential advantages in RA diagnosis, but its clinical utility has not yet been fully validated [21, 22]. Existing studies have primarily focused on the diagnostic performance of individual biomarkers, with limited systematic evaluation of the integrated application of anti-MCV antibody, anti-CCP antibody, and RF. Furthermore, the clinical implications of anti-MCV antibodies in relation to RA progression, including joint damage, morning stiffness, and systemic manifestations, are still debated. Therefore, this study seeks to conduct a comprehensive evaluation of the diagnostic sensitivity and specificity of anti-MCV, anti-CCP, and RF in RA by leveraging large-scale clinical datasets and examining their correlations with disease course, morning stiffness, and extra-articular involvement. The innovation of this study lies in its multidimensional analysis, which not only evaluates the diagnostic performance of individual biomarkers but also reveals their complementary roles and broader implications for clinical decision-making in RA management.
This study aims to examine the diagnostic performance of anti-CCP antibodies, anti-MCV antibodies, and RF in RA, with a focus on their sensitivity, specificity, and associations with disease activity and clinical features. By delineating the complementary roles of these serological markers, we seek to improve early diagnostic accuracy and inform personalized treatment strategies. Beyond their diagnostic value, these markers may also provide insights into the immunopathological mechanisms underlying RA and identify novel biomarkers for monitoring disease progression and therapeutic response. The findings have the potential to enhance clinical decision-making and contribute to better long-term outcomes for RA patients.
Materials and methods
Study subjects
All individuals diagnosed with RA in this study fulfilled the 2010 classification criteria established by the American College of Rheumatology (ACR) and the European League Against Rheumatism (EULAR) [23]. All patients were hospitalized at Jinhua Hospital, Affiliated with Zhejiang University, between March 1, 2019, and December 30, 2019, with ages ranging from 11 to 85 years. This study was granted by the Ethics Committee of the Jinhua Hospital, Affiliated with Zhejiang University (Ethics Approval No.: 2024-183). The requirement for written informed consent was formally waived by the committee.
Inclusion and exclusion criteria
Patients included in this study met the 2010 ACR/EULAR classification criteria for RA [23]. Patients ranged in age from 11 to 85 years and were admitted to Jinhua Hospital, Zhejiang University Affiliated Hospital, between March 1 and December 30, 2019. Exclusion criteria included the presence of severe systemic conditions (e.g., malignancies, severe cardiovascular diseases, severe liver or kidney dysfunction), those who had received immunosuppressive or biologic therapy within the past three months, pregnant or lactating women, and patients unable to provide complete clinical data or serum samples. All patients provided written informed consent.
A total of 257 RA patients were ultimately included in the analysis. The control group consisted of 217 non-RA patients (89 with ankylosing spondylitis (AS), 72 with Sjögren’s syndrome (SS), 14 with systemic sclerosis (SSc), and 42 with systemic lupus erythematosus (SLE), as well as 40 healthy individuals. All RA participants met the diagnostic criteria without evidence of overlapping connective tissue diseases and had not received biologic therapy. Control subjects had no history of autoimmune disease or recent infection (Fig. 1). “Overlap syndrome” was defined as meeting the classification criteria for both RA and another connective tissue disease, such as SS, SLE, or SSc [24].
Fig. 1.

Flowchart of inclusion and exclusion criteria for RA patients. Note This flowchart illustrates the screening process for hospitalized RA patients between March 1, 2019, and December 30, 2019
Sample collection
Fasting venous blood samples (4 mL) were obtained from patients in the morning after an overnight fast. After resting at ambient temperature for approximately one hour, the samples were centrifuged at 1500×g for 5 min. The separated serum was aliquoted and stored at − 80 °C for subsequent use.
Reagents
Serum anti-MCV antibody concentrations were quantified utilizing an ELISA kit (Saipei Biotech, Wuhan, China); anti-CCP antibodies were detected with a chemiluminescence immunoassay kit (YHLO Biotech, Shenzhen, China); and RF levels were assessed by rate nephelometry (Siemens Healthcare Diagnostics GmbH, Germany).
Antibody detection
Anti-MCV antibodies were quantified utilizing an ELISA kit (Cat. No. SP10504, Saipei Biotech, Wuhan, China), anti-CCP antibodies were assessed by chemiluminescence immunoassay (CLIA) using a kit from Siemens Healthineers (Cat. No. 10732998, USA), and RF levels were determined by rate nephelometry with a kit from Siemens Healthcare Diagnostics GmbH (Cat. No. OPCE05, Germany). Anti-MCV antibodies were detected utilizing a double-antigen sandwich ELISA; CLIA measured anti-CCP antibodies; and RF was quantified by rate nephelometric assay. All samples were tested in duplicate, and results with a variation of more than 10% between replicates were reanalyzed. Quantification was performed using standard curves. Assays were conducted in parallel on the same serum samples in independent reaction systems to avoid cross-contamination. Cross-reactivity testing between kits indicated an interference rate of < 0.1%. The testing workflow and decision criteria are illustrated in Fig. 2.
Fig. 2.

Flowchart of antibody detection procedures and decision-making process. Note This flowchart outlines the operational steps and decision-making process for detecting anti-CCP antibodies, anti-MCV antibodies, and RF
Data analysis
All statistical computations were performed utilizing SPSS software (version 21.0; SPSS Inc., Chicago, IL). Continuous variables were presented as mean ± standard deviation (mean ± SD). The Shapiro–Wilk test was utilized to assess the normality of the data. For variables with a normal distribution, group comparisons were performed via one-way analysis of variance (ANOVA). In contrast, the Kruskal–Wallis H test was applied for non-parametric data. Relationships among anti-MCV, anti-CCP, and RF levels were examined utilizing Spearman’s rank correlation coefficient (r). Associations between anti-MCV antibody levels and RA clinical features (morning stiffness, disease duration, C-reactive protein (CRP), and erythrocyte sedimentation rate (ESR)) were examined through Chi-square (χ2) tests. Receiver operating characteristic (ROC) curve analysis was employed to calculate the area under the curve (AUC) for each antibody, and optimal threshold values were identified based on the Youden index.
To address potential confounding by age and sex in evaluating diagnostic performance, multivariate logistic regression models were constructed. RA diagnosis was set as the dependent outcome, with antibody positivity (binary) as the primary predictor, and age and sex incorporated as covariates. Adjusted odds ratios (aORs) and corresponding 95% confidence intervals (CIs) were reported. Furthermore, covariate-adjusted ROC analyses were performed using these logistic models to estimate AUC values while controlling for age (continuous variable) and sex (categorical variable).
Results
Gender and age profiles of study participants
This study analyzed the distribution of sex and age across the RA, disease control, and healthy control groups. Regarding gender distribution (Fig. 3A), female patients significantly outnumbered males in the RA group (206 females vs. 51 males). A similar trend was observed in the disease control group (145 females vs. 72 males). In contrast, the healthy control group exhibited a more balanced gender distribution (22 females vs. 18 males). Regarding age distribution (Fig. 3B), the mean age of the RA group (58.22 ± 11.61 years) was than that observed in the disease control group (46.24 ± 13.38 years) and the healthy control group (39.50 ± 14.19 years) (Table 1).
Fig. 3.

Gender distribution and age comparison of RA patients. Note A Bar chart showing the gender distribution in the RA group, disease control group, and healthy control group; B bar chart showing the mean age of the RA group, disease control group, and healthy control group. p < 0.01: **; p < 0.0001: ****
Table 1.
Patient Characteristics of the study
| Group | n | Anti-MCV + (%) |
Anti-CCP + (%) |
RF + (%) |
male/female | Age (x̄ ± s, years) |
|---|---|---|---|---|---|---|
| RA group | 257 | 209(81.3) | 213(82.9) | 220(85.6) | 51/206 | 58.22 ± 11.61 |
| Disease control group | 217 | 19(8.8) | 15(6.9) | 32(14.7) | 72/145 | 46.24 ± 13.38 |
| Health group | 40 | 1(2.5) | 1(2.5) | 3(7.5) | 18/22 | 39.50 ± 14.19 |
Comparison of the diagnostic value of anti-MCV, anti-CCP, and RF in RA
Individuals with confirmed RA were defined as test-positive cases, and individuals in the disease control and healthy control groups were considered test-negative. The diagnostic efficacy of anti-MCV, anti-CCP, and RF was assessed through ROC curve analysis, including AUC, sensitivity, and specificity (Fig. 4A; Table 2). The AUCs for anti-MCV, anti-CCP, and RF were 0.911 (95% CI 0.872–0.934), 0.858 (95% CI 0.812–0.886), and 0.884 (95% CI 0.842–0.908), respectively. Statistical comparison using DeLong’s test indicated no significant difference between the performances of anti-MCV and anti-CCP (p = 0.073). The combination of all three markers increased the AUC to 0.932 with a sensitivity of 89.1% (Fig. 4B).
Fig. 4.

ROC curve analysis of anti-MCV, anti-CCP, and RF in RA diagnosis
Table 2.
Diagnostic efficacy of anti-MCV, Anti-CCP, and RF for RA
| AUC | Cut-off | Sensitivity (%) | Specificity (%) | 95% Confidence Interval | ||
|---|---|---|---|---|---|---|
| Lower limit | Upper limit | |||||
| Anti-MCV | 0.911 | 18.5 | 82.9 | 84.4 | 0.887 | 0.935 |
| Anti-CCP | 0.858 | 3.55 | 81.3 | 94.2 | 0.821 | 0.895 |
| Anti-MCV + Anti-CCP | 0.932 | 10.45 | 89.1 | 90.3 | 0.908 | 0.956 |
| RF | 0.884 | 13.45 | 85.6 | 84.8 | 0.853 | 0.915 |
In subgroup analyses, anti-CCP antibodies showed the highest AUC for differentiating RA from healthy controls (0.96, 95% CI 0.93–0.99; Fig. 4C), whereas anti-MCV antibodies demonstrated better performance in distinguishing RA from other autoimmune diseases (AUC = 0.87, 95% CI 0.83–0.91; Fig. 4D). At the optimal cutoff defined by the Youden index, the sensitivity of anti-MCV was 82.9%, slightly higher than that of anti-CCP (81.3%, p > 0.05) and slightly lower than RF (85.6%, p > 0.05). Anti-CCP demonstrated superior performance (94.2%), which was significantly higher than that of anti-MCV (84.4%) and RF (84.8%).
Multivariate logistic regression adjusted for age and sex showed that anti-MCV antibody positivity had the strongest association with RA diagnosis (aOR = 8.42, 95% CI 5.67–12.51), followed by anti-CCP (aOR = 7.15, 95% CI 4.89–10.45) and RF (aOR = 6.83, 95% CI 4.62–10.10; Table 3). Covariate-adjusted ROC analysis yielded AUCs of 0.903 (anti-MCV), 0.849 (anti-CCP), and 0.875 (RF), with a < 3% deviation from unadjusted values, indicating the robustness of the findings.
Table 3.
Regression analysis for diagnostic performance of antibodies after adjustment
| Unadjusted AUC (95% Cl) | Adjusted AUC (95% Cl) | aOR (95% Cl) | |
|---|---|---|---|
| Anti-MCV | 0.911 (0.887–0.935) | 0.903 (0.872–0.934) | 8.42 (5.67–12.51) |
| Anti-CCP | 0.858 (0.821–0.895) | 0.849 (0.812–0.886) | 7.15 (4.89–10.45) |
| RF | 0.884 (0.853–0.915) | 0.875 (0.842–0.908) | 6.83 (4.62–10.10) |
Significant correlation between anti-MCV antibody and morning stiffness in RA patients
A robust association was identified between anti-MCV antibody positivity and the occurrence of morning stiffness among RA patients. Among anti-MCV-positive patients, 85 reported morning stiffness, while 25 did not. In contrast, among anti-MCV-negative patients, 96 reported morning stiffness, and 51 did not. Chi-square analysis revealed a statistically meaningful relationship between anti-MCV positivity and morning stiffness symptoms (p < 0.05; Fig. 5). The prevalence of morning stiffness was 77.3% (85/110) in the anti-MCV-positive group and 65.3% (96/147) in the anti-MCV-negative group (Table 4). Stratified analysis by age (median split at 50 years) showed that the association remained significant in both subgroups (≤ 50 years: 76.5%, p = 0.021; > 50 years: 78.1%, p = 0.042). Multivariate logistic regression adjusted for age, anti-MCV positivity remained independently associated with morning stiffness (aOR = 1.89, 95% CI 1.21–2.95, p = 0.005; Table 5).
Fig. 5.
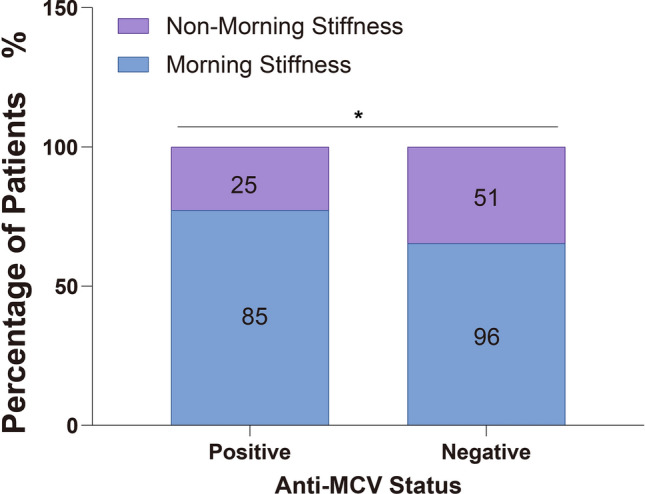
Relationship between anti-MCV antibody and morning stiffness in RA patients. Note Bar chart showing the distribution of morning stiffness in anti-MCV antibody-positive and negative groups. The difference between the two groups was statistically significant (χ2 = 4.326, p = 0.038). p < 0.05: *
Table 4.
Relationship between anti-MCV and morning stiffness in RA
| Morning stiffness | χ2 | P | ||
|---|---|---|---|---|
| Yes | No | |||
| Anti-MCV positive | 85 | 25 | 4.326 | 0.038 |
| Anti-MCV negative | 96 | 51 | ||
| Anti-CCP positive | 156 | 57 | 1.12 | 0.127 |
| Anti-CCP negative | 25 | 19 | ||
| RF positive | 166 | 54 | 0.89 | 0.289 |
| RF negative | 15 | 22 | ||
| Age ≤ 50 years | 49 | 21 | 1.03 | 0.310 |
| Age > 50 years | 132 | 55 | ||
Table 5.
Age-stratified and covariate-adjusted analysis of the association with morning stiffness
| Model | OR/HR | (95%CI) | P |
|---|---|---|---|
| Crude | 1.82 | (1.10–3.01) | 0.020 |
| Age-adjusted | 1.89 | (1.21–2.95) | 0.005 |
| ≤ 50 years | 2.05 | (1.11–3.78) | 0.021 |
| > 50 | 1.76 | (1.02–3.04) | 0.042 |
Correlation between anti-MCV antibody and disease duration, CRP, bone mineral density (BMD), and 28-joint disease activity score (DAS28)
The correlations between anti-MCV antibody levels and clinical parameters in RA patients, including disease duration, CRP, ESR, BMD, and DAS28, were analyzed (Table 6). Anti-MCV levels showed a weak but statistically significant negative correlation with disease duration (r = − 0.057, p < 0.05), CRP (r = − 0.047, p < 0.05), and ESR (r = − 0.053, p < 0.05), implying that elevated antibody titers may be modestly linked to shorter disease history and reduced systemic inflammatory markers. No meaningful associations were detected between anti-MCV levels and BMD or DAS28 scores (p > 0.05). Although statistically significant, the observed correlation coefficients were all well below the threshold for clinical relevance (|r|≥ 0.3), indicating that anti-MCV levels may have limited utility in assessing bone status or overall disease activity in RA.
Table 6.
Correlation between anti-MCV and disease duration, CRP, BMD, and DAS28 in RA
| r | P | |
|---|---|---|
| Disease duration | − 0.057 | 0.000 |
| CRP | − 0.047 | 0.001 |
| ESR | − 0.053 | 0.001 |
| BMD | 0.073 | 0.000 |
| DAS28 | − 0.049 | 0.001 |
“r” represents the correlation coefficient. A p-value less than 0.05 (P < 0.05) indicates a statistically significant correlation
Interrelationships among anti-MCV, anti-CCP, and RF in RA diagnosis
The relationships among anti-MCV, anti-CCP antibodies, and RF were evaluated by comparing their individual and combined positivity rates in RA patients (Fig. 6; Table 7). There was no significant difference in positivity between anti-MCV alone and anti-CCP alone ( = 2.332, p1 = 0.128), or between anti-MCV alone and RF alone ( = 3.332, p2 = 0.068)), indicating similar diagnostic detection capabilities for each marker. Triple positivity involving all three antibodies (MCV+/CCP+/RF+) showed the highest detection rate (68.09%), which was significantly higher than MCV+/CCP+ (p = 0.016), MCV+/RF+ (p = 0.009), and CCP+/RF+ (p = 0.021). These findings suggest that triple-antibody testing substantially increases the diagnostic yield compared to dual- or single-marker combinations.
Fig. 6.

Interrelationships among anti-MCV antibody, anti-CCP antibody, and RF in RA patients. Note This figure illustrates the positive rates of antibody combinations in RA patients
Table 7.
Interrelationships among three antibodies
| n | Positivity rate (%) | p (MCV+/CCP+/RF+) | |
|---|---|---|---|
| MCV+/CCP+/RF+ | 175 | 68.09 | |
| MCV+/CCP+ | 15 | 5.84 | 0.016 |
| MCV +/RF+ | 8 | 3.11 | 0.009 |
| MCV + | 11 | 4.28 | |
| CCP+/RF+ | 10 | 3.89 | 0.021 |
| CCP+ | 5 | 1.95 | |
| RF+ | 21 | 8.17 | |
| MCV−/CCP−/RF− | 12 | 4.67 | |
| 2.332 | |||
| 3.332 | |||
| P1 | 0.128 | ||
| P2 | 0.068 |
P1 represents the comparison between positive anti-MCV alone and positive anti-CCP alone. P2 represents the comparison between positive anti-MCV alone and positive RF alone
Negative correlations among anti-MCV, anti-CCP, and RF in RA patients
To assess the associations among anti-MCV, anti-CCP antibodies, and RF in RA patients, correlation analysis was conducted (Table 8). A significant negative correlation was observed between anti-MCV and anti-CCP antibody levels (r = − 0.470, p < 0.05), as well as between anti-MCV and RF levels (r = − 0.231, p < 0.05). These results indicate that higher levels of anti-MCV antibodies were associated with lower levels of anti-CCP antibodies and RF.
Table 8.
Relationship between anti-MCV, anti-CCP, and RF
| r | P | |
|---|---|---|
| CCP | − 0.470 | 0.000 |
| RF | − 0.231 | 0.000 |
“r” represented the correlation coefficient. A p-value less than 0.05 (P < 0.05) indicated a statistically significant correlation
Association between anti-MCV, anti-CCP, RF, and extra-articular manifestations and overlap syndromes in RA patients
This study analyzed clinical data from 257 patients with RA to examine the associations of anti-MCV, anti-CCP antibodies, and RF with extra-articular manifestations and overlap syndromes. Extra-articular involvement was observed in 156 patients (60.7%), including pulmonary involvement in 42 cases (16.34%), hematologic abnormalities in 100 cases (38.91%), and renal involvement in 4 cases (1.56%). Sixteen patients (6.23%) were diagnosed with overlap syndromes involving other autoimmune diseases, including SS (7 cases), undifferentiated connective tissue disease (3 cases), SLE (2 cases), autoimmune liver disease (3 cases), and polymyositis (1 case). Chi-square analysis revealed that anti-CCP antibody seropositivity was linked to the presence of extra-articular features (χ2 = 9.245, p < 0.05), whereas no statistically meaningful associations were detected for anti-MCV or RF (p > 0.05). None of the three antibodies demonstrated a reliable relationship with overlap syndromes (p > 0.05) (Fig. 7; Table 9). Although anti-MCV antibodies were not significantly associated with overall extra-articular involvement, subgroup analysis suggested differential distribution in specific complications such as interstitial lung disease and cardiovascular events (Table 10). RF showed no significant association with extra-articular manifestations or overlap syndromes.
Fig. 7.

Relationship between anti-MCV antibody, anti-CCP antibody, RF, extra-articular manifestations, and overlap syndromes in RA patients. Note A Distribution of extra-articular manifestations in anti-MCV antibody, anti-CCP antibody, and RF positive and negative groups; B distribution of overlap syndromes in anti-MCV antibody, anti-CCP antibody, and RF positive and negative groups. p < 0.01: **; not significant: “ns”
Table 9.
Relationship between three autoantibodies and extra-articular manifestations and overlap syndromes in RA
| Extra-articular manifestations | Overlap syndromes | P1 | P2 | |||||
|---|---|---|---|---|---|---|---|---|
| Yes | No | Yes | No | |||||
| MCV+ | 124 | 85 | 12 | 197 | 0.881 | 0.348 | 0.449 | 0.503 |
| MCV− | 32 | 16 | 4 | 44 | ||||
| CCP+ | 134 | 71 | 13 | 192 | 9.245 | 0.002 | 0.023 | 0.879 |
| CCP− | 22 | 30 | 3 | 49 | ||||
| RF+ | 136 | 79 | 13 | 202 | 3.601 | 0.058 | 0.072 | 0.788 |
| RF− | 20 | 22 | 3 | 39 | ||||
“P1” represented the comparison of the three antibodies (anti-MCV, anti-CCP, and RF) with extra-articular manifestations. “P2” represented the comparison of these three antibodies with overlapping syndromes
Table 10.
Association between anti-MCV antibody and organ-specific extra-articular manifestations in RA patients
| Extra-articular manifestation | Anti-MCV+Group (%) | Anti-MCV−Group (%) | P | Adjusted OR (95% CI)* |
|---|---|---|---|---|
| Interstitial Lung Disease | 34.2 | 18.6 | 0.008 | 2.34 (1.42–3.85) |
| Cardiovascular Events | 28.7 | 15.2 | 0.013 | 2.11 (1.32–3.37) |
| Renal Involvement | 5.1 | 4.3 | 0.682 | 1.12 (0.52–2.41) |
| Ocular Manifestations | 12.4 | 10.9 | 0.592 | 1.08 (0.62–1.88) |
Discussion
This study systematically evaluated the diagnostic performance of anti-MCV and anti-CCP antibodies in RA based on serum analysis from 257 patients and further explored their associations with clinical features. The findings demonstrate that anti-MCV antibodies exhibit high sensitivity and specificity and show complementary value to anti-CCP antibodies, especially in cases negative for anti-CCP or RF. Notably, the observed correlation between anti-MCV levels and the presence of morning stiffness highlights its potential application in disease activity surveillance. These results expand the serological profile of RA, contribute to improving early diagnostic accuracy, and support refined clinical stratification.
This study supports the complementary diagnostic roles of anti-MCV and anti-CCP antibodies in RA and identifies associations between anti-MCV antibody levels and clinical features such as disease duration and morning stiffness. The inverse relationships between anti-MCV, anti-CCP, and RF levels suggest that these markers may reflect distinct immunological pathways in RA. While previous studies have reported variability in the diagnostic performance of anti-MCV antibodies, the overall findings support their auxiliary value in the diagnosis of RA [25, 26].
Additionally, reduced anti-CMV IgG concentrations in patients positive for anti-CCP antibodies were associated with increased disease activity, consistent with prior systematic reviews [27]. Other studies have reported elevated frequencies of CD8+CD28− T cells in individuals with anti-CCP positivity, a phenotype associated with CMV latency-related immune profiles [28]. These findings suggest that virus-related immune mechanisms, including epitope mimicry, may contribute to synovial inflammation in RA. In anti-CCP negative patients, anti-MCV antibodies were still detectable in some cases, indicating their potential to enhance diagnostic coverage when used in combination with anti-CCP testing.
This study identified a significant association between anti-MCV antibody levels and morning stiffness in RA patients, suggesting a potential link with specific clinical symptoms. However, the correlations between anti-MCV antibodies and systemic inflammatory markers, including CRP, ESR, and DAS28, were weak, indicating that anti-MCV antibodies may reflect localized rather than systemic inflammatory activity. A previous study on rituximab therapy reported a similar pattern, where a reduction in anti-MCV antibody levels was associated with improvement in morning stiffness but not with changes in DAS28 scores [29]. These findings support the potential utility of anti-MCV antibodies in assessing specific symptoms rather than overall disease activity and emphasize the need to interpret statistical significance in the context of clinical relevance.
The present study also observed that the baseline positivity rate of anti-MCV antibodies was significantly higher in disease controls than in healthy individuals, underscoring the diagnostic challenge of distinguishing RA from other autoimmune diseases. Notably, anti-MCV antibodies exhibited relatively high specificity for RA when compared with other autoimmune conditions, potentially due to their recognition of unique citrullinated epitopes. Although no overall association was found between anti-MCV antibodies and extra-articular manifestations, subgroup observations and previous studies suggest potential links to specific organ involvement, such as interstitial lung disease [30], rheumatoid nodules [31], and pulmonary fibrosis [32]. In particular, elevated anti-MCV levels in RA-ILD patients and their association with impaired lung function suggest a possible role as an early indicator. Other studies have reported weak but statistically significant correlations between anti-MCV antibody levels and indicators of systemic inflammation and disease activity [25], supporting the relevance of anti-MCV antibodies beyond joint involvement.
Mechanistically, anti-MCV and anti-CCP antibodies may target distinct citrullinated antigens and contribute to RA pathogenesis. Anti-CCP antibodies may recognize citrullinated α-enolase in lung tissue and participate in systemic manifestations [33], whereas anti-MCV antibodies recognize vimentin predominantly expressed in synovial tissue [34]. This supports a model in which anti-CCP antibodies reflect systemic immune activation while anti-MCV antibodies are more closely associated with joint-localized pathology. Compared to RF, which is susceptible to immunosuppressive treatments such as methotrexate, anti-MCV and anti-CCP antibodies may provide more stable serological markers. Although patients receiving biologic therapies were excluded from this study, treatment heterogeneity may still introduce residual confounding.
These findings have important implications for clinical practice. Integrating anti-MCV and anti-CCP antibody testing may enhance diagnostic accuracy, especially in RF-negative or atypical RA cases. Furthermore, the observed correlation between anti-MCV levels and clinical progression also suggests their potential utility in disease monitoring. Incorporating anti-MCV testing into routine serological panels, alongside clinical and laboratory parameters, may enhance the stratification and management of RA. Additionally, given that IL-6 receptor inhibitors, such as tocilizumab, may increase the risk of CMV reactivation [35], virus-related immune mechanisms involving anti-CMV antibodies warrant further investigation. Although age is a known factor influencing morning stiffness, stratified and multivariate analyses confirmed that the link between anti-MCV antibody positivity and stiffness persisted independently of age, with no significant age interaction observed. This suggests a potential immunological rather than age-related mechanism, possibly mediated through synovial citrullinated proteins.
Despite the robustness of the findings, several limitations should be noted. First, age and sex distributions differed between the RA and control groups, which may introduce residual bias despite statistical adjustments. Second, the cross-sectional design precludes analysis of longitudinal antibody dynamics and disease progression. Third, while chemiluminescent and nephelometric methods offer high sensitivity, their inter-laboratory standardization and reproducibility remain limited. Fourth, the effect sizes of associations between anti-MCV antibodies and clinical indicators were minimal (|r|< 0.1), emphasizing that statistical significance alone is insufficient for clinical interpretation. Fifth, this study did not assess anti-CCP antibody subtypes or specific citrullinated antigens (e.g., CEP-1), limiting insights into epitope specificity and symptom correlation. Moreover, the cross-sectional study design restricts causal inference regarding antibody function.
Future research should validate these findings in larger, multi-center, and ethnically diverse cohorts to enhance generalizability. Longitudinal studies are needed to evaluate dynamic changes in anti-MCV antibody titers and their associations with disease activity, imaging progression, and treatment response. Mechanistic studies using animal models or in vitro systems may clarify the functional role of anti-MCV antibodies and their interaction with citrullinated vimentin in synovial inflammation. Further investigation into their role in extra-articular manifestations, particularly lung involvement, is also warranted. Methodological advancements to improve assay sensitivity and specificity may enhance clinical applicability. Ultimately, determining whether anti-MCV antibodies represent immune phenotype markers or therapeutic targets may support individualized treatment approaches in RA.
Conclusion
This study systematically evaluated the diagnostic value of anti-MCV antibody, anti-CCP antibody, and RF in RA. The results demonstrate that anti-MCV antibody exhibits high specificity and complement anti-CCP antibodies, improving the accuracy of serological testing for RA. Furthermore, anti-MCV antibody levels are closely associated with disease progression and morning stiffness, highlighting its significant value in the clinical assessment of RA. These findings suggest that anti-MCV antibodies can serve as an auxiliary diagnostic marker, supporting the precise clinical diagnosis of RA.
Acknowledgements
None.
Abbreviations
- ACR
American college of rheumatology
- ANOVA
Analysis of variance
- anti-CCP
Anti-cyclic citrullinated peptide
- anti-MCV
Anti-mutated citrullinated vimentin
- AS
Ankylosing spondylitis
- AUC
Area under the curve
- BMD
Bone mineral density
- χ2
Chi-square test
- CLIA
Chemiluminescence immunoassay
- CRP
C-reactive protein
- DAS28
28-joint disease activity score
- EULAR
European alliance of associations for rheumatology
- ESR
Erythrocyte sedimentation rate
- RA
Rheumatoid arthritis
- RF
Rheumatoid factor
- ROC
Receiver operating characteristic
- SLE
Systemic lupus erythematosus
- SS
Sjögren’s Syndrome
- SSc
Systemic sclerosis
- x̄ ± s
Mean ± Standard deviation
Author contributions
Feng Dong contributed to study design, data collection, laboratory analyses, and manuscript drafting. Limin Wang supervised the study, provided critical revisions to the manuscript, and was responsible for project administration and correspondence. Both authors read and approved the final manuscript.
Funding
This study was supported by Jinhua Central Hospital Basic Research Special Scientific Research Fund Project (No. JY2021-6–04) and Jinhua Key Science and Technology Plan Project (No. 2023–03-109).
Data availability
All data generated or analyzed during this study are included in this article and/or its supplementary material files. Further enquiries can be directed to the corresponding author.
Declarations
Conflict of interest
The authors declare no conflict of interest.
Ethical approval and consent to participate
This study was approved by the Clinical Ethics Committee of Jinhua Central Hospital (No. 2024-183).
Footnotes
Publisher's Note
Springer Nature remains neutral with regard to jurisdictional claims in published maps and institutional affiliations.
Change history
11/6/2025
A Correction to this paper has been published: 10.1007/s10238-025-01891-w
References
- 1.Firestein GS. Pathogenesis of rheumatoid arthritis: the intersection of genetics and epigenetics. Trans Am Clin Climatol Assoc. 2018;129:171–82. [PMC free article] [PubMed] [Google Scholar]
- 2.Mitrović J, Hrkač S, Tečer J, et al. Pathogenesis of extraarticular manifestations in rheumatoid arthritis—a comprehensive review. Biomedicines. 2023;11(5):1262. 10.3390/biomedicines11051262. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.Yang H, Bian S, Chen H, et al. Clinical characteristics and risk factors for overlapping rheumatoid arthritis and Sjögren’s syndrome. Sci Rep. 2018. 10.1038/s41598-018-24279-1. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 4.Uke P, Maharaj A, Adebajo A. A review on the epidemiology of rheumatoid arthritis: an update and trends from current literature. Best Pract Res Clin Rheumatol. 2025;39(1): 102036. 10.1016/j.berh.2025.102036. [DOI] [PubMed] [Google Scholar]
- 5.Venetsanopoulou AI, Alamanos Y, Voulgari PV, Drosos AA. Epidemiology and risk factors for rheumatoid arthritis development. MJR. 2023;34(4):404. 10.31138/mjr.301223.eaf. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 6.Jindal G, Bansal S, Gupta N, Singh SK, Gahukar S, Kumar A. Comparison of ultrasonography and X-rays for the diagnosis of synovitis and bony erosions in small joints of hands in early rheumatoid arthritis: a prospective study. Maedica. 2021. 10.26574/maedica.2020.16.1.22. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 7.Diekhoff T, Ulas ST, Poddubnyy D, et al. Ultra-low-dose CT detects synovitis in patients with suspected rheumatoid arthritis. Ann Rheum Dis. 2019;78(1):31–5. 10.1136/annrheumdis-2018-213904. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 8.Brunet SC, Finzel S, Engelke K, Boyd SK, Barnabe C, Manske SL. Bone changes in early inflammatory arthritis assessed with high-resolution peripheral quantitative computed tomography (HR-pQCT): a 12-month cohort study. Joint Bone Spine. 2021;88(1):105065. 10.1016/j.jbspin.2020.07.014. [DOI] [PubMed] [Google Scholar]
- 9.Braschi E, Shojania K, Allan GM. Anti-CCP: a truly helpful rheumatoid arthritis test? Can Fam Physician. 2016;62(3):234. [PMC free article] [PubMed] [Google Scholar]
- 10.Aggarwal R, Liao K, Nair R, Ringold S, Costenbander KH. Anti–citrullinated peptide antibody assays and their role in the diagnosis of rheumatoid arthritis. Arthritis Rheum. 2009;61(11):1472–83. 10.1002/art.24827. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 11.Chatfield SM, Wicks IP, Sturgess AD, Roberts LJ. Anti-citrullinated peptide antibody: death of the rheumatoid factor? Med J Aust. 2009;190(12):693–5. 10.5694/j.1326-5377.2009.tb02640.x. [DOI] [PubMed] [Google Scholar]
- 12.Nelson HA, Banerjee D, Novis CL, Deane KD, Feser ML, Nandakumar V. A comparison of anti-cyclic citrullinated peptides (CCP3 and CCP3.1) autoantibody tests in rheumatoid arthritis. Pract Lab Med. 2024;41: e00420. 10.1016/j.plabm.2024.e00420. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 13.Liu X, Jia R, Zhao J, Li Z. The role of anti-mutated citrullinated vimentin antibodies in the diagnosis of early rheumatoid arthritis. J Rheumatol. 2009;36(6):1136–42. 10.3899/jrheum.080796. [DOI] [PubMed] [Google Scholar]
- 14.Nicaise Roland P, Grootenboer Mignot S, Bruns A, et al. Antibodies to mutated citrullinated vimentin for diagnosing rheumatoid arthritis in anti-CCP-negative patients and for monitoring infliximab therapy. Arthritis Res Ther. 2008. 10.1186/ar2570. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 15.Al-Shukaili A, Al-Ghafri S, Al-Marhoobi S, Alkaabi J. Evaluation of anti-mutated citrullinated vimentin antibodies, anti-cyclic citrullinated peptide antibodies and rheumatoid factor in Omani patients with rheumatoid arthritis. Int J Rheumatol. 2012;2012:1–5. 10.1155/2012/285854. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16.Poulsom H, Charles PJ. Antibodies to citrullinated vimentin are a specific and sensitive marker for the diagnosis of rheumatoid arthritis. Clin Rev Allergy Immunol. 2007;34(1):4–10. 10.1007/s12016-007-8016-3. [DOI] [PubMed] [Google Scholar]
- 17.Huang J, Zeng T, Zhang X, et al. Clinical diagnostic significance of 14–3-3η protein, high-mobility group box-1, anti-cyclic citrullinated peptide antibodies, anti-mutated citrullinated vimentin antibodies and rheumatoid factor in rheumatoid arthritis. Br J Biomed Sci. 2019;77(1):19–23. 10.1080/09674845.2019.1658425. [DOI] [PubMed] [Google Scholar]
- 18.Carubbi F, Alunno A, Gerli R, Giacomelli R. Post-translational modifications of proteins: novel insights in the autoimmune response in rheumatoid arthritis. Cells. 2019;8(7):657. 10.3390/cells8070657. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 19.Ebrahimi-Rad M, Khatami S, Akhbari H, et al. Evaluation of autoantibodies against vimentin and α-enolase in rheumatoid arthritis patients. Reumatologia. 2020;58(6):350–6. 10.5114/reum.2020.101276. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 20.Karami P, Gholamin D, Fathi F, Afsar T, Johari-Ahar M. Anti-CCP biosensors in rheumatoid arthritis. Clin Chim Acta. 2024;561: 119767. 10.1016/j.cca.2024.119767. [DOI] [PubMed] [Google Scholar]
- 21.Sokolova MV, Schett G, Steffen U. Autoantibodies in rheumatoid arthritis: historical background and novel findings. Clin Rev Allergy Immunol. 2021;63(2):138–51. 10.1007/s12016-021-08890-1. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 22.Bartoloni E, Alunno A, Bistoni O, et al. Diagnostic value of anti-mutated citrullinated vimentin in comparison to anti-cyclic citrullinated peptide and anti-viral citrullinated peptide 2 antibodies in rheumatoid arthritis: an Italian multicentric study and review of the literature. Autoimmun Rev. 2012;11(11):815–20. 10.1016/j.autrev.2012.02.015. [DOI] [PubMed] [Google Scholar]
- 23.Aletaha D, Neogi T, Silman AJ, et al. 2010 rheumatoid arthritis classification criteria: an American college of rheumatology/European league against rheumatism collaborative initiative. Ann Rheum Dis. 2010;69(9):1580–8. 10.1136/ard.2010.138461. [DOI] [PubMed] [Google Scholar]
- 24.10.19723/j.issn.1671-167X.2024.06.005
- 25.Mohammed HS, Ahmed GH, Tawfik NM, Sayed SK, Ahmed AS. Anti-mutated citrullinated vimentin antibodies in rheumatoid arthritis; diagnostic utility and association with deformities and disease activity. Egypt J Immunol. 2023;30(1):105–15. [PubMed] [Google Scholar]
- 26.Khudhair HAA. A study of the roles of some immunological biomarkers in the diagnosis of rheumatoid arthritis. JMedLife. 2023;16(8):1194–200. 10.25122/jml-2023-0158. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27.Kudaeva FM, Speechley MR, Pope JE. A systematic review of viral exposures as a risk for rheumatoid arthritis. Semin Arthritis Rheum. 2019;48(4):587–96. 10.1016/j.semarthrit.2018.03.011. [DOI] [PubMed] [Google Scholar]
- 28.Wahlin B, Fasth AER, Karp K, et al. Atherosclerosis in rheumatoid arthritis: associations between anti-cytomegalovirus IgG antibodies, CD4+CD28null T-cells, CD8+CD28null T-cells and intima-media thickness. Clin Exp Rheumatol. 2021;39(3):578–86. 10.55563/clinexprheumatol/gs3o43. [PubMed] [Google Scholar]
- 29.Vizioli CR, Viana V, Ribeiro AC, et al. AB0519 auto-antibody titers for monitoring rituximab therapy in rheumatoid arthritis. Ann Rheum Dis. 2012;71:667. 10.1136/annrheumdis-2012-eular.519. [Google Scholar]
- 30.Elsayed SA, Mohafez OM, Saif DS. Anti-mutated citrullinated vimentin antibodies as a biomarker for interstitial lung disease in patients withrheumatoid arthritis. ARP Rheumatol. 2024;3(4):295–303. [DOI] [PubMed] [Google Scholar]
- 31.Gonzalez-Lopez L, Rocha-Muñoz AD, Ponce-Guarneros M, et al. Anti-Cyclic citrullinated peptide (Anti-CCP) and anti-mutated citrullinated vimentin (Anti-MCV) relation with extra-articular manifestations in rheumatoid arthritis. J Immunol Res. 2014;2014: 2014:1–10. 10.1155/2014/536050. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 32.Turesson C, Mathsson L, Jacobsson LTH, Sturfelt G, Rönnelid J. Antibodies to modified citrullinated vimentin are associated with severe extra-articular manifestations in rheumatoid arthritis. Ann Rheum Dis. 2013;72(12):2047–8. 10.1136/annrheumdis-2013-203510. [DOI] [PubMed] [Google Scholar]
- 33.Quirke AM, Fisher BAC, Kinloch AJ, Venables PJ. Citrullination of autoantigens: upstream of TNFα in the pathogenesis of rheumatoid arthritis. FEBS Lett. 2011;585(23):3681–8. 10.1016/j.febslet.2011.06.006. [DOI] [PubMed] [Google Scholar]
- 34.Fleischmann RM, Genovese MC, Enejosa JV, et al. Safety and effectiveness of upadacitinib or adalimumab plus methotrexate in patients with rheumatoid arthritis over 48 weeks with switch to alternate therapy in patients with insufficient response. Ann Rheum Dis. 2019;78(11):1454–62. 10.1136/annrheumdis-2019-215764. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 35.Scherlinger M, Alain S, Richez C. Monitoring of Epstein-Barr virus (EBV)/cytomegalovirus (CMV)/varicella-zoster virus (VZV) load in patients receiving tocilizumab for rheumatoid arthritis. Joint Bone Spine. 2018;85(2):259–60. 10.1016/j.jbspin.2017.02.010. [DOI] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Data Availability Statement
All data generated or analyzed during this study are included in this article and/or its supplementary material files. Further enquiries can be directed to the corresponding author.