



ABSTRACT
This study investigates the experiences of autistic adult women, a group understudied in autism research due to a predominant focus on early identification/intervention, restrictive research participation criteria, and differing rates of diagnosis by sex. This study characterizes a cohort of autistic adult women (n = 1424) across various dimensions including demographics, relationships, education, employment, income, well‐being, and co‐occurring psychiatric conditions. It also explores differences among those diagnosed with autism as children versus those diagnosed as adults. The sample was limited to women able to read and provide independent consent to participate. Results indicated that the average age of diagnosis for those diagnosed before age 18 was 9.6 years old, whereas for those diagnosed in adulthood it was 31.8. Over 80% of the sample had completed some college or post‐secondary education, with more than a third of those diagnosed as adults having attained a 4‐year college degree or higher. More than half were employed, with those diagnosed as adults more likely to be employed full time (31.74%). Additionally, more than half were married or identified a romantic partner. Significant rates of psychiatric comorbidity were reported, with those diagnosed with autism as adults more likely to have co‐occurring anxiety (69.87%), depression (61.79%), eating disorders (17.28%), and substance use diagnoses (8.85%) than those diagnosed as children. High rates of suicidal ideation (34%) and self‐harm (21%) were endorsed in the full sample. Regression analyses indicated that being diagnosed with autism at a later age was associated with higher internalizing, externalizing, and substance use as well as a lower report of personal strengths, even when accounting for demographic factors. Despite these challenges, our findings highlight that many autistic women have positive outcomes and meet common adult developmental milestones. The authors advocate for the development of more tailored treatment options that address the specific needs of autistic women.
Keywords: adults, autism, co‐occurring conditions, LGBT, lifespan, SPARK, women
Summary.
This study investigates the lived experiences of adult autistic women, some of whom were diagnosed with autism in childhood, and others who were diagnosed later in adulthood.
More than half of the women were in the work force, a third were married, and many struggled with thoughts of hurting or killing themselves.
More than half of the sample reported feeling anxious or depressed.
1. Introduction
Autism is a neurodevelopmental disorder defined by its impact on social communication skills and behavioral flexibility. Prevalence rates (1:36; Maenner et al. 2023) have been rising for 25 years (Nevison and Zahorodny 2019). Various factors contribute to this phenomenon, including an increase in diagnostic rates of females (McDonnell et al. 2020). New research on differentiated profiles of autistic women and girls and the impact of cohort effects around diagnosis and prevalence has emerged (Keyes et al. 2012; Lehnhardt et al. 2016). However, there remains relatively limited information about the lives of autistic adult women due to systemic exclusion of autistic females in research and lack of information about autism in adults.
2. Autism and Sex
Historically, females have been excluded from autism research on autism in efforts to restrict heterogeneity, or because numbers are too few to analyze (a self‐reifying problem wherein fewer diagnoses and less research participation mutually escalate; Rynkiewicz et al. 2019). Furthermore, many research studies on autism exclude those with ID, thus excluding more females than males (Diemer et al. 2022). Prevalence rates are consistently higher among males (3.8:1) and even higher when excluding those with co‐occurring intellectual disability ([ID]; prevalence ratio approximately = 5.2:1; Maenner et al. 2023; Shenouda et al. 2023). Researchers debate the degree to which differences in diagnostic rates are access‐driven, biological (i.e., genetic or hormonal), a product of socialization and social motivation (i.e., Rylaarsdam and Guemez‐Gamboa 2019; Sedgewick et al. 2016), or psychometrically driven through limitations in assessment (Dillon et al. 2023; D’Mello et al. 2022). Importantly, research in autism has not always been diligent to identify or disentangle influences of sex differences as compared to gender differences, socialization, or influences of gender diversity on these questions.
For a thorough review of sex differences in autism, please see Ferri et al. (2018) and Napolitano et al. (2022). Briefly, some sex differences include: compared to autistic males, autistic females may be more likely to have sensory concerns (Lai et al. 2011), more repetitive play with toys (Hiller et al. 2016), less likely to have restricted interests (Moseley et al. 2018), and have more complex interpersonal relationships (Gosling et al. 2023). The theory that autistic people may compensate for social deficits with extra effort and social mimicry, or “masking,” is important in the literature (Dean et al. 2017; Lai et al. 2017), and women might experience higher social motivation (Bargiela et al. 2016), which drives the behavior. This comes at a psychological cost, and autistic women report that masking can lead to identity confusion, negative mental health outcomes including suicidal ideation, and fatigue (Beck et al. 2020).
Autistic women also report complex relationships with gender identity (Kanfiszer et al. 2017) and some report internal feelings of disassociation from assigned sex at birth. Furthermore, challenges with performing or interpreting gendered socialization, and features of autism presentation that misalign with gender expectations (i.e., special interest in trains), influence the experience and expression of gender identity (Strang et al. 2020). Extremely limited measurement options in relation to non‐binary identities also contribute to a lack of research (Strang et al. 2020).
Recently, researchers have found that autistic females are enrolling in research at a higher rate than males, and a majority of those females were diagnosed in adulthood and also reported high levels of co‐occurring psychiatric conditions (Jadav and Bal 2022). Thus, this specific project presents a novel opportunity to examine co‐occurring conditions in a national sample.
3. Age of Autism Diagnosis
Age of autism diagnosis is often a proxy measure in research for healthcare access, services received, provider biases, symptom presentation, and more (Daniels and Mandell 2014; Russell et al. 2025). Autism can be diagnosed very early in development and it is not considered to “onset,” later in life (Daniels and Mandell 2014). Delayed diagnoses impact access to early interventions, school‐based supports, and prescriptions (Klin et al. 2015), as well as less tangible factors like family supports, identity, and community (Kanfiszer et al. 2017). Importantly, the relationship between age of diagnosis and severity of symptom presentation may be non‐linear. Ambiguous autism presentation may apply to those with low‐support needs, for whom strong language skills or other cognitive abilities “mask” symptoms. Ambiguity and delayed diagnosis may also impact those with high support needs, where symptoms of severe ID and autism are difficult to disentangle (Hus and Segal 2021; Thurm et al. 2019). Whether a person is diagnosed with autism in adulthood (18 years or older) compared to childhood, is meaningful in terms of who referred the person for evaluation (e.g., pediatrician or therapist), motivations for evaluation (e.g., early childhood delays or adulthood identity concerns), consent to evaluation (e.g., parents/self), services available (e.g., speech therapy or community seeking), and influences on medical care (e.g., being seen in a developmental‐behavioral pediatrics department or managing increased medical comorbidities; Huang et al. 2020).
4. Autism and the Lifespan
Autism research and clinical services have focused overwhelmingly on children, with limited discussion of transition to adulthood, middle age, or older adulthood (Lorenc et al. 2018). Supports in childhood are well‐developed and include intervention services (e.g., applied behavior analysis; Bailey et al. 2004), school services, and specialized medical care. Transition to adulthood has become a growing area of interest (Baldwin and Costley 2016), but information about characteristics and clinical services in adulthood remains comparatively limited.
While Begeer et al. (2013) identified that females tend to be diagnosed later than males across the spectrum and lifespan, to the authors' knowledge, no studies have compared the experiences of autistic women diagnosed in childhood to those diagnosed in adulthood (Lockwood Estrin et al. 2021). Women diagnosed later in life may have unique experiences across the lifespan (Bargiela et al. 2016; Green et al. 2019) and adapted strategies (and faced challenges) in adulthood that can be better supported and understood (Baldwin and Costley 2016). Mental health may also be a primary area of interest in this group for both researchers and autistic women themselves, as autistic people are reported to experience higher rates of psychiatric and medical conditions than their neurotypical peers (Malow et al. 2023).
5. Current Study
This study used data from the SPARK study cohort. We aimed, first, to characterize autistic adult women enrolled in the SPARK cohort by detailing demographics, describing family and relationships, education, employment, and income; measuring mental well‐being, and co‐occurring psychiatric conditions. The second aim was to explore whether there are systematic differences in these areas among those diagnosed with autism as children versus those diagnosed as adults. This information is vital to the development of lifespan supports, understanding of adult concerns and priorities, and to counter potentially stigmatizing narratives about autistic women.
6. Methods
This project was reviewed by Medical University South Carolina Institutional Review Board and determined exempt from review. The parent study (SPARK) is approved by WCG IRB (#20151664).
6.1. Participants
Fourteen‐hundred‐twenty‐four women (cisgender = 1411; trans women = 13; non‐binary assigned female at birth [AFAB] = 134) were included in this analysis (excludes individuals who self‐identified as trans‐men). Transwomen, cisgender women, and AFAB identifying as non‐binary or “other” will be hereafter be referred to as “women and NBP” (women and non‐binary people). All women and NBP were enrolled in the SPARK research study at age of 18 or older (M = 32.38, SD = 9.72), and had received a professional diagnosis of autism either in childhood (n = 490) or adulthood (n = 933). SPARK is a national study that has recruited over 100,000 autistic individuals and their family members across 31 recruitment sites (Feliciano et al. 2018). Adults living in the United States with a professional autism diagnosis can enroll in SPARK online, or through a recruitment event, where they answer questions and can be matched with appropriate research studies.
The current study included women and NBP who provided independent consent and had completed the SPARK Background History for Adults, Basic Medical Screening, and Adult Self Report (ASR; Achenbach and Rescorla 2003). SPARK requires a professional diagnosis of autism for enrollment; and provides a composite validity flag variable to identify participants whose diagnosis may not be medically verified (e.g., participant unable to identify which type of provider diagnosed them, history of questioned or refuted autism diagnosis). We excluded 206 cases which were flagged for diagnostic validity concerns.
6.2. Study Measures
6.2.1. Background History and Basic Medical Screening
The Background History form for adults asks about demographics, educational achievements, supports, sexual orientation, family history, and more. The Basic Medical Screening form includes questions about medical and psychiatric diagnoses and concerns. Both forms were self‐completed by all participants included in analyses.
6.2.2. Adult Self Report
The ASR is part of the Achenbach System of Empirically Based Assessment battery measuring mental health and adaptive functioning across the lifespan (Achenbach and Rescorla 2003). This comprehensive measure includes questions about family, work, internalizing, externalizing, and suicidality and takes approximately 20 min to complete. Participants rate items on a 3‐point scale (not true, sometimes or somewhat true, very true or often true). The measure is widely used as a broad measure of adult functioning (Achenbach et al. 2005; Ivanova et al. 2015; Rescorla et al. 2016). Several meta‐analyses and comparative studies have found strong internal consistency (Cronbach's alpha = 0.95; De Vries et al. 2020).
The ASR has adaptive (e.g., friends, family support), DSM‐oriented (e.g., depressive, anxiety), broadband, and syndrome subscales. This study utilized 13 out of 32 possible scales. Authors elected to include all broadband, strengths, adaptive, and substance use scales, as well as certain syndrome scales which supplemented aims, while managing the risk of multiple comparisons. Specifically, for Aim 1 (characterizing the sample), scales were categorized by functioning domain. Family and relationships were measured using the Friends, Spouse, and Family ASR scales wherein participants report on the number of friends, frequency of contact, how well they get along with their partner, relationship satisfaction, and how well they get along with family members. Happiness in education and employment was examined using the Job and Education subscales. These scales focus on getting along with others at work or school, finding work and education satisfying/fulfilling. The Personal Strengths scale focuses on self‐efficacy. Co‐occurring psychiatric conditions were assessed using the Total Problems, Internalizing, Externalizing, and Substance Use Composites. The Total Problems Composite score measures a composite of all 120 problem items across internalizing, externalizing, and other (e.g., thought problems, attention problems) scales. The Internalizing Composite score includes Anxious/Depressed, Withdrawn, and Somatic Complaints scales; the Externalizing Composite includes Rule Breaking Behavior, Aggressive Behavior, and Intrusive Behavior. Lastly, the Substance Use Composite score includes information from the Tobacco, Alcohol, and Drug Use scales, which were incorporated to examine patterns of substance use in this population. T‐Scores for ASR subscales were utilized for all analyses. Higher T scores indicate more positive functioning in adaptive measures.
6.3. Data Analysis
The current study utilized SPSS V29.0.1.0 to conduct all analyses. Only participants who completed all measures were included in the analyses, thus there were no missingness analyses completed. For the first aim, authors used descriptive analyses to characterize: demographics; family, education, work; personal strengths and co‐occurring conditions. For the second aim, t‐tests and chi‐square tests examined differences between individuals diagnosed with autism as children (under 18 years old) or as adults (18+). Differences in education, employment status, income, and marital status were also examined within a linear regression framework (logistic used for marital status) controlling for age at enrollment, since individuals diagnosed as children were on average younger than those diagnosed as adults at the time of participation (M child = 28.29 years and M adult = 35.70 years, p < 0.001). For these supplemental analyses, education, employment status, and income brackets were treated as continuous outcome variables. Marital status (married vs. not) and having children were treated as a dichotomous outcome variables and examined using logistic regressions in supplemental analyses. When examining the ASR, authors used descriptives and correlational testing to analyze which demographic variables (education, marital status, employment, and having children) were associated with ASR composite scores, and the personal strengths subscale. Linear regressions were conducted with covariates and the variable of interest (diagnostic age) entered as predictors and ASR composites as the dependent variables. Individual betas as well as model R 2 statistics were examined and included in Table 4. The Benjamini–Hochberg False Discovery Rate (Benjamini and Hochberg 1995) correction was used to protect against inflation of type 1 errors due to multiple comparisons.
TABLE 4.
Age at autism diagnosis predicting internalizing, externalizing, substance use, total problems, and personal strengths.
| Predictors | 95% CI | p | |||||
|---|---|---|---|---|---|---|---|
| Beta | SE | LL | UL | ß | R 2 | ||
| Internalizing | 0.039 | ||||||
| Age of autism diagnosis | 0.01 | 0.00 | 0.01 | 0.01 | 0.12 | < 0.001 | |
| Have children | 0.90 | 0.65 | −0.38 | 2.17 | 0.04 | 0.169 | |
| Education | −1.60 | 0.34 | −2.27 | −0.93 | −0.14 | < 0.001 | |
| Employment | −1.11 | 0.37 | −1.84 | −0.39 | −0.08 | 0.003 | |
| Externalizing | 0.049 | ||||||
| Age of autism diagnosis | 0.01 | 0.00 | 0.01 | 0.01 | 0.13 | < 0.001 | |
| Have children | 1.51 | 0.59 | 0.36 | 2.66 | 0.07 | 0.01 | |
| Education | −1.87 | 0.31 | −2.47 | −1.26 | −0.18 | < 0.001 | |
| Employment | −0.49 | 0.33 | −1.15 | 0.16 | −0.04 | 0.138 | |
| Substance use composite | 0.043 | ||||||
| Age of autism diagnosis | 0.01 | 0.00 | 0.01 | 0.01 | 0.14 | < 0.001 | |
| Have children | 1.23 | 0.47 | 0.31 | 2.16 | 0.07 | 0.009 | |
| Education | −1.20 | 0.25 | −1.69 | −0.72 | −0.14 | < 0.001 | |
| Employment | 0.90 | 0.27 | 0.38 | 1.42 | 0.1 | < 0.001 | |
| Total problems | 0.063 | ||||||
| Age of autism diagnosis | 0.01 | 0.00 | 0.01 | 0.02 | 0.18 | < 0.001 | |
| Have children | 1.36 | 0.61 | 0.17 | 2.56 | 0.06 | 0.025 | |
| Education | −1.87 | 0.32 | −2.5 | −1.25 | −0.17 | < 0.001 | |
| Employment | −0.97 | 0.35 | −1.64 | −0.29 | −0.08 | 0.005 | |
| Personal strengths | 0.034 | ||||||
| Age of autism diagnosis | −0.01 | 0.00 | −0.01 | −0.01 | −0.168 | < 0.001 | |
| Have children | −0.15 | 0.53 | −1.19 | 0.88 | −0.008 | 0.772 | |
| Employment | 1.07 | 0.29 | 0.51 | 1.63 | 0.099 | < 0.001 | |
Note: These are Adult Self Report (ASR) findings. Have children coded as = 1, no children coded as = 0.
7. Results
7.1. Demographics
Age of autism diagnosis was normally distributed (skewness = 0.21, kurtosis = −0.74), with a range of 18 months to 58 years. Average age of diagnosis in this sample was 24.19 years (SD = 13.31; see Table 1); with a median = 23.58 and a mode = 3.00 years old; see Figure 1 for distribution. Around one third of this sample was diagnosed as children (34.4% diagnosed before age 18; 15.7% diagnosed at age 8 or younger). Of those diagnosed under 18, the average age of diagnosis was 9.67 (SD = 4.91). Of those diagnosed as adults, average age of diagnosis was 31.83 (SD = 9.39). Average age at enrollment in SPARK was 32.74 (SD = 9.71), (diagnosed as children, =28.29 (SD = 8.30); and diagnosed as adults, = 35.70 (SD = 9.40)). The sample was limited in its racial diversity, with 92.0% identifying as White non‐Hispanic. More individuals diagnosed as children identified as Black, compared to individuals diagnosed as adults (Pearson chi square; X 2 (1) = 5.76; p = 0.016).
TABLE 1.
Demographics.
| Full sample | Diagnosed 0–18 | Diagnosed 18+ | p | |
|---|---|---|---|---|
| M(SD)/(%) | M(SD)/(%) | M(SD)/(%) | ||
| Age at diagnosis (years) | 24.20 (13.30) | 9.67(4.91) | 31.83(9.38) | |
| Age at study participation (years) | 32.74 (9.71) | 28.29(8.3) | 35.70(9.40) | < 0.001 |
| Race | ||||
| Asian | 3.37% | 2.65% | 3.75% | 0.276 |
| Black | 4.84% | 6.73% | 3.85% | 0.016 |
| Native American | 5.76% | 5.01% | 6.12% | 0.438 |
| Hawaiian | 0.28% | 0.20% | 0.32% | 0.691 |
| White | 91.99% | 91.22% | 92.39% | 0.442 |
| Other | 4.85% | 5.10% | 4.72% | 0.747 |
| More than 1 | 8.79% | 8.37% | 9.00% | 0.687 |
| Hispanic | 8.00% | 8.16% | 7.93% | 0.878 |
| Highest education level | < 0.001 | |||
| Did not attend/Some HS | 3.16% | 5.71% | 1.82% | |
| HS/GED | 15.31% | 24.89% | 10.29% | |
| AA/Trade School/some college/current college | 44.87% | 47.34% | 43.52% | |
| Bachelor's | 22.54% | 15.71% | 26.93% | |
| Graduate/professional | 13.90% | 6.12% | 18.01% | |
| Employment | < 0.001 | |||
| Full time | 31.74% | 21.63% | 36.97% | |
| Part time | 20.58% | 23.88% | 18.86% | |
| Not working (retired, unable, unemployed, unpaid student) | 46.84% | 53% | 43.52% | |
| Household income | < 0.001 | |||
| 35 k or less | 53.72% | 62.04% | 49.41% | |
| 35 k–80 k | 25.63% | 20.00% | 28.51% | |
| 80 k+ | 19.66% | 16.32% | 21.43% | |
| Marital status | < 0.001 | |||
| Single | 38.90% | 51.02% | 32.58% | |
| Married | 30.54% | 20.20% | 36.01% | |
| Partner | 22.12% | 24.29% | 21.01% | |
| Divorced | 7.87% | 3.87% | 9.86% | |
| Family | ||||
| Have children | 38.06% | 27.35% | 43.62% | < 0.001* |
Significance did not hold up in follow‐up analysis accounting for impact of age at participation using linear regression framework.
FIGURE 1.

Age of autism diagnosis distribution.
7.1.1. Family and Relationships
Regarding sexual orientation, 41.50% of women and NBP endorsed identifying as heterosexual, 6.18% endorsed gay, 16.78% endorsed bisexual, 9.69% endorsed asexual, and 25.9% chose not to respond. In terms of relationships, 30.55% were married, 7.86% were divorced, 22.12% were in a relationship, and 38.90% were single. Thirty‐eight percent reported having children of their own. Those diagnosed as adults were more likely to be married than those diagnosed as children (Pearson chi square; X 2 (1) = 37.83; p < 0.001). This finding remained significant after accounting for age at enrollment (Table S1, OR = 1.001, p < 0.001).
7.1.2. Education, Employment, and Income
Regarding education, 12.08% were high school graduates and 5.06% had trade school education, 22.54% had a Bachelor's degree, 9.20% had an Associate degree, and 10.88% were currently in college. Furthermore, 13.90% had a graduate/professional level degree. Individuals diagnosed in adulthood were more likely to have higher education attainment than those diagnosed as children (Pearson chi square; X 2 (4) = 109.32; p < 0.001). This remained significant when accounting for age of enrollment (Table S2; Standardized B = 0.19).
In terms of employment, 31.74% work full time, 20.56% work part time, and 28.58% reported they were unable to work, with an additional 15.45% labeling themselves unemployed. More participants diagnosed in adulthood held full‐time employment than those diagnosed as children (Pearson chi square; X 2 (6) = 49.92; p < 0.001). This finding remained significant after accounting for age of enrollment (Table S3; Standardized B = 0.05). The most common occupations were skilled craftsmen or technicians (18.47%), upper management or professional (14.89%), and service industry (12.56%). Household income varied, with 52.72% making $35,000 per year or less, 25.62% making between $35,000 and $80,000, and 19.65% making $80,000 or more in household income. More participants diagnosed as adults were in the higher income brackets compared to those diagnosed as children (Pearson Chi Square; X 2 (2) = 22.93; p < 0.001). This finding also held significant when accounting for age of enrollment (Table S4; Standardized B = 0.04).
7.1.3. Co‐Occurring Psychiatric Conditions
Overall, rates of lifetime reported co‐occurring diagnoses were high (Table 3), and 76.4% of the sample had more than one co‐occurring diagnosis. ADHD diagnoses were reported by 46.07%. Differences in rates of co‐occurring conditions were found between participants diagnosed with autism as adults compared to those diagnosed as children. Participants diagnosed with autism as children were more likely to have ODD (Pearson chi square; X 2 (1) = 23.63; p < 0.001) and conduct disorder (Pearson chi square; X 2 (1) = 6.97; p = 0.008) diagnoses compared to those diagnosed with autism as adults.
TABLE 3.
Co‐occurring diagnoses (lifetime).
| Co‐occurring diagnoses | Full sample | Diagnosed 0–18 | Diagnosed 18+ | p |
|---|---|---|---|---|
| Neurodevelopmental/Childhood | ||||
| ADHD | 46.07% | 46.73% | 45.65% | 0.699 |
| ODD | 4.85% | 8.57% | 2.79% | < 0.001 |
| Conduct | 1.05% | 2.04% | 0.54% | 0.008 |
| Mood | ||||
| Anxiety | 69.87% | 68.16% | 70.74% | 0.314 |
| OCD | 25.49% | 26.12% | 25.19% | 0.701 |
| Bipolar | 18.26% | 19.59% | 17.47% | 0.324 |
| Depression | 61.79% | 56.94% | 64.42% | 0.006 |
| Other | ||||
| Schizophrenia | 3.79% | 3.67% | 3.85% | 0.862 |
| Personality disorder | 12.35% | 11.63% | 12.65% | 0.580 |
| Sleep diagnosis | 31.81% | 33.47% | 30.87% | 0.317 |
| Substance abuse | 8.85% | 6.94% | 9.86% | 0.065 |
| Eating disorder | 17.28% | 13.27% | 19.39% | 0.004 |
A depressive diagnosis was reported by 61.79% of participants, and 69.87% reported having a diagnosed anxiety disorder. Depression was more common in those diagnosed with autism as adults (Pearson chi square; X 2 (6) = 7.61; p = 0.006) than diagnosed as children.
A diagnosed sleep disorder was reported by 31.80% of the participants, and 17.28% an eating disorder. Eating disorders were more common in adult‐diagnosed sample (Pearson chi square; X 2 (1) = 8.46; p = 0.004). Considering diagnoses with relatively low base rates, 3.79% had a schizophrenia diagnosis, and 12.35% reported having a diagnosed personality disorder.
ASR findings regarding job, education, and family satisfaction subscales are listed in Table 2. Regarding substance use symptom reports, women and NBP diagnosed as adults indicated more alcohol (t(1410) = −3.21, p < 0.001) and drug use (t(1407) = −4.09, p < 0.001). Linear regressions included covariates from analyses in Table S5 (i.e., having had children, education level, and employment). All regression analyses are available in Table 4. In summary, after controlling covariates, all models were significant (ps < 0.001), and age of autism diagnosis was a significant predictor in all models, including for internalizing scores (ß = 0.10), externalizing scores (ß = 0.13), substance use (ß = 0.14), total problems (ß = 0.18), and personal strengths (ß = −0.17, p < 0.001). These overall models accounted for a range of variance in our reported outcome variables, ranging from 0.034–0.063.
TABLE 2.
Adult self‐report.
| Full sample, M (SD) | Diagnosed 0–18,M (SD) | Diagnosed 18+, M (SD) | p | |
|---|---|---|---|---|
| Family and relationships | ||||
| Friends | 37.53(10.73) | 38.05(10.754) | 37.25(10.719) | 0.188 |
| Spouse | 42.09(8.807) | 42.65(8.633) | 41.88(8.88) | 0.313 |
| Family | 38.85(10.031) | 39.88(9.971) | 38.3(10.028) | 0.005 |
| Education, employment, income | ||||
| Job | +38.51(8.658) | 40.1(8.167) | 37.78(8.782) + | 0.001 |
| Education | 40.43(11.509) | 41.48(11.481) | 39.78(11.504) + | 0.164 |
| Co‐occurring psychiatric conditions | ||||
| Tobacco use | 53.04(9.121) | 52.84(8.863) | 53.14(9.261) | 0.343 |
| Alcohol use | 53.11(6.456) | 52.35(5.397) | 53.51(6.92) | < 0.001 |
| Drug use | 55.18(12.081) | 53.36(9.821) | 56.12(13.019) | < 0.001 |
Note: Scales are t scores. Significant differences were based on T‐test for friends (t(1409) = 1.318, p = 0.188, spouse (t(673) = 1.009, p = 0.313, family (t(1383) = 2.802, p < 0.005, job (t(899) = 3.762, p < 0.001 and education (t(376) = 1.394, p = 0.164). Family and relationships, education, employment, income, and personal strengths subscales, as well as tobacco, alcohol, and drug use subscales, were determined via t‐testing.
As an exploratory post hoc analysis, the authors investigated mental health scales in the ASR, including internalizing, externalizing, total problems, and substance use, in the subgroup of participants with no diagnosed internalizing disorders (i.e., without OCD, Anxiety, Depression, Bipolar; n = 213; approximately 15%). The internalizing and total problems t scores were elevated in these populations, M = 65.11 and M = 63.89, respectively. This falls in a “borderline,” referral range, between the 91st and 94th percentile.
Critical items (Figure 2) revealed a high level of suicidal ideation and self‐harm, with 34.13% of the sample saying that they think about killing themselves, and 20.72% saying they deliberately try to self‐harm or kill themselves. As these numbers were much higher than anticipated, the authors added an exploratory post hoc analysis based on research suggesting that rates of suicidal ideation may be higher among individuals who identify as gender diverse or sexually minoritized (Sidaros 2017). Results showed that reports of deliberately trying to self‐harm or kill themselves were higher in the part of the sample that identified as sexual‐orientation diverse or gender diverse (i.e., excluding heterosexual and cisgendered women; n = 710). Regarding deliberate self‐harm or attempts to kill themselves, the exploratory chi square was significant; (Pearson chi square; X 2 (1) = 28.502; p < 0.001). Heterosexual/cisgendered people reported a 14.4% rate of self‐harm or suicide attempt histories, while 26.6% of gender/sexual orientation minoritized people endorsed this history. With regard to suicidal ideation, an association was also found (Pearson chi square; X 2 (1) = 34.45; p < 0.001), with 25.8% of heterosexual/cisgendered people and 41.4% of gender/sexual orientation minoritized people endorsing suicidal ideation.
FIGURE 2.
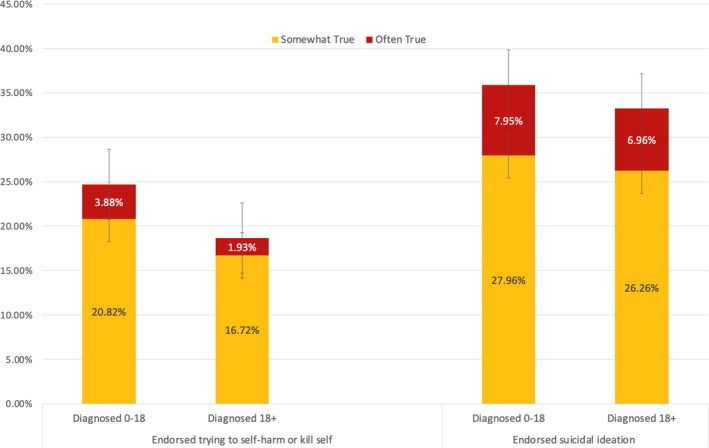
Suicidality according to ASR critical items.
8. Discussion
This study provides a deeper understanding of the family, relationships, education, work life, and psychiatric health of more than 1400 autistic women and NBP, and explored potential differences in those diagnosed as children compared to adults. Participants reported positive outcomes such as employment, relationships, and education. High rates of health problems and alarmingly high rates of self‐harm and suicidal ideation were also endorsed (see Figure 3 for a summary of major findings).
FIGURE 3.

Summary of selected findings.
8.1. Demographics
The distribution of age of diagnosis is unique compared to other large scale autism studies. The modal age was consistent with national averages (Maenner et al. 2023), however, less than 1 in 7 were diagnosed by age 8, often considered the age by which “most” children are diagnosed (Maenner et al. 2023). This likely reflects potential bias in the sample, and challenging diagnostic journeys that autistic women and NBP encounter. Importantly, our sample excluded those under guardianship and those unable to complete self‐report forms independently. This contributed to the overall older age of diagnosis, and resulted in a sample which excluded those with the highest support needs.
8.2. Family and Relationships
Consistent with past research, participants were less likely to be married than neurotypical peers, and more likely to identify as LGBTQ. Recent data from the PEW Research Center (2016) indicates that in the 25–54 age range, over 50% of adults are married, compared with 31% in this sample (37.2% of our 25–54 aged participants). Weir et al. (2021) found that autistic adults were more likely to identify as LGBTQ than peers. In our sample, less than half identified as cisgender and heterosexual, showing the importance of considering holistic identities in clinical care and understanding the forces that affect their lives (e.g., ableism and homophobia).
8.3. Education, Employment, and Income
This sample was employed at similar rates as females in the general population, but with lower average household incomes. Census data indicates 56.8% participation of females in the labor force (which includes unemployed job‐seekers; Bureau of Labor Statistics 2023). Combined part and full time, 52.3% in this sample work, however, the majority of those in this study (almost 80%) had household incomes less than the median (approximately $74,580 in 2022; U.S. Census Bureau). This income data available is difficult to interpret, as we do not know who constitutes the reported households (i.e., partners, parents, singles), but generally, the findings support prior research suggesting that autistic adults are at risk of under‐employment (Baldwin et al. 2014).
Lower incomes do not appear in the context of low educational attainment. This sample was more likely to progress to post‐secondary education than the general population (Census Bureau 2023). Census data are an imperfect match given age/ability discrepancies; however, the rates of college (23% vs. 22.54%) and postgraduate (14% vs. 13.9%) completion were very similar (26.9% college completion and 17.1% graduate education in the aged matched 25–54 subsample). One interpretation is selective bias towards highly educated individuals (many research samples skew educated; Henrich et al. 2010). Alternatively, it is plausible that higher academic achievement is a characteristic of the population. Cridland et al. (2014) postulated that autistic girls may have skills suited to academic success, including rule following, preference for structure, and involvement in groups with shared interests.
Another interpretation is that autistic women and NBP are drawn to careers, like hospitality/service industry or driven by altruism, which are traditionally lower‐paying. It is also possible that lower wages may be a function of difficulties particular to the workplace, like discrimination and insufficient support. Some employment opportunities are inhospitable to those with neurodiverse differences, and demand independent time management, multitasking, and personnel management which may pose challenges (Hayward et al. 2018, 2019). Organizational psychologists, clinical psychologists, and autistic women may be able to work collaboratively to identify and evaluate accommodations to make the workplace more hospitable.
8.4. Co‐Occurring Psychiatric Conditions
Overall, rates of co‐occurring conditions trended higher than neurotypical populations. Nearly half endorsed co‐occurring ADHD. A large review of co‐occurring conditions in autistic populations estimated 27% co‐occurrence of ADHD in adults (Rosen et al. 2018). It is possible that our numbers are higher because elevated symptoms indicate screening for autism, or motivate people to seek evaluations, closing the gap in referrals. Regarding ODD and conduct disorder, Rosen and colleagues reported 25% co‐occurrence in a mixed sample of males and females, while this study indicated lower rates. Jadav and Bal (2022) found that autistic females endorsed more psychiatric symptoms and conditions than male counterparts, and that adult‐diagnosed people endorsed more psychiatric symptoms than their child‐diagnosed counterparts.
It is important to note that these data are likely under‐estimates of true co‐occurring prevalences, as they include official diagnoses by a medical provider, and women and NBP may be coping with undiagnosed difficulties due to barriers in access to care (Doherty et al. 2022). Among the subsample of participants who did not report an internalizing disorder diagnosis, average total problems and internalizing were still high, underscoring the possibility of under‐diagnosis and widespread elevation in internalizing symptoms in this population.
More than a third of autistic women reported experiencing suicidal thoughts and/or engaging in self‐harm behaviors. This pattern of high suicidal ideation aligns with previous findings (Blanchard et al. 2021) and has been linked to masking and mental health concerns in autistic women (Miller et al. 2021). Even more striking, those who identified as gender or sexual orientation‐diverse endorsed higher rates of suicidal ideation and self‐harm than cisgender/heterosexual counterparts, further emphasizing the importance of considering intersectional identities when measuring risk.
Elevated substance use rates were reported in this sample, which may increase the risk of death in neurotypical populations (Esang and Ahmed 2018). Nyrenius et al. (2023) found that drug and alcohol use was a high‐risk factor for recent episodes of suicidality and self‐harm among autistic adults diagnosed in adulthood (Larkin et al. 2017). Research on substance use and autism has been mixed, sometimes indicating reduced risk, and other times suggesting situationally increased risk (i.e., with co‐occurring ADHD: Rosen et al. 2018). In this sample, almost 9% reported substance use diagnoses, suggesting a need for developing interventions tailored to the specific needs of those on the spectrum. Increasingly, substance use has been considered through a gendered lens, with females having unique risk factors (e.g., pregnancy, domestic violence), addiction courses (e.g., more rapid progression of disease course), and outcomes (e.g., breast cancer risk, harmful psychological concerns), compared to men (Dawson et al. 2010; Hussong et al. 2011; Pinkerton et al. 2015; McCaul et al. 2019; McHugh et al. 2018; Towers et al. 2023). The importance of assessment and avoiding assumptions is clear.
Almost a third of the sample reported diagnosed sleep disorders. Research has indicated signature sleeping patterns as possible endophenotypes, and evidence of widespread sleep problems in autistic populations (Veatch et al. 2015). In line with research indicating symptomology overlap between autism and eating disorders (i.e., ritualized eating behaviors, food refusals; Rosen et al. 2018), there was a high rate of eating disorders. Autistic women identified need for control, difficulty dealing with emotions, and preference for predictability as driving factors for co‐occurring anorexia (Brede et al. 2020; Huke et al. 2013).
8.5. Diagnosis in Childhood Versus Adulthood
A secondary aim of this study was to determine ways in which autistic women and NBP diagnosed as children differ from those diagnosed as adults. Those diagnosed as adults had attained higher levels of education, were more likely full‐time employed, with higher household income, and more likely to be married than those diagnosed as children. Those diagnosed as adults were more likely to have depression and eating disorders diagnoses. Regression analyses indicate that age of diagnosis is significantly related to adult report of mental health symptoms, even when accounting for other demographic factors like employment and education status. Older age of diagnosis was related to more internalizing, more externalizing, more substance use, and less personal strengths reporting. While the effect of age of autism diagnosis was consistent and impactful, it still contributed only a small amount to explaining the overall variance of these symptom reports, suggesting that other factors we have not accounted for are also relevant. These might include IQ, adaptive skills, internalized ableism, and more. That said, the two groups also looked similar in many ways, with high numbers of co‐occurring conditions and symptoms.
While objectively meeting many typical adult milestones, individuals diagnosed as adults self‐reported greater overall psychological distress and fewer personal strengths than individuals diagnosed as children. Potential explanations for this finding are multifactorial and may include lasting impacts of missing out on early intervention opportunities (Ben Itzchak and Zachor 2011) and lack of a diagnostic label to support identity development in childhood. Individuals diagnosed in adulthood may be masking at higher levels (contributing to delayed diagnosis) taking a toll on their mental health. It is also possible that women and NBP who sought out a diagnosis in adulthood did so due to psychiatric distress. Capitalizing on personal strengths would be a strong start for treatment planning, and future research should emphasize successful coping mechanisms, self‐image, stress management, productivity, and engagement.
8.6. Limitations
This sample is not representative of the larger population of autistic women, nor of autistic adults. It is specifically a majority white, highly educated sample, and the findings should be understood within that context. The reasons for this are intersectional (for more, see Fannin et al. 2024). While the rates of autism diagnosis in BIPOC are rising (Maenner et al. 2023), these changing dynamics appear to be primarily in children, who may not have aged into an adult sample. This study does not include any measure of autism‐specific symptom intensity or impairment, nor measures of cognitive ability. These study findings should not be used to make generalizations about individuals. Participants reported autism diagnosis from a qualified professional, but diagnoses were not validated. In one study, 98.8% of autism diagnoses in SPARK were validated by medical record review (inclusive of adults; Fombonne et al. 2022). We excluded participants who had a flag for questionable diagnostic validity to control for this limitation. Our sample excludes those with high support needs (who could not fill out self‐report forms or were under guardianship).
8.7. Conclusion
This study paints a complex picture of community, education, and medical life for autistic women and NBP. Results provide compelling support for further research into tailored mental health supports; particularly suicidal thoughts and behaviors, substance use, eating disorders, and internalizing conditions. Improved assessment measures and supports for autistic adults will improve long‐term outcomes for this population.
This work was supported by a grant from the Simons Foundation or the Simons Foundation International (515840, LAC). We are grateful to all of the families in SPARK, the SPARK clinical sites and SPARK staff. We appreciate obtaining access to phenotypic data on SFARI Base. Approved researchers can obtain the SPARK population dataset described in this study https://base.sfari.org/public/user/6ab558d6‐f5af‐44f6‐a554‐689bf2a0879a by applying at https://base.sfari.org.
Ethics Statement
This project was reviewed and determined to be exempt by the Medical University of South Carolina Institutional Review Board approval.
Conflicts of Interest
The authors declare no conflicts of interest.
Supporting information
Table S1. Logistic regression: Diagnostic age predicting odds of being married, controlling for current age.
Table S2. Linear regression analysis: Diagnostic age predicting highest education level attained, controlling for current age.
Table S3. Linear regression analysis: Diagnostic age predicting employment status, controlling for current age.
Table S4. Linear regression analysis: Diagnostic age predicting income, controlling for current age.
Table S5. Control variables analyzed for relation to ASR composite variables for main analyses regressions.
Diemer, M. C. , Ros‐Demarize R., Bradley C. C., et al. 2025. “Comparative Analysis of Autistic Women Across the Lifespan: Childhood vs. Adulthood Diagnosis.” Autism Research 18, no. 8: 1651–1663. 10.1002/aur.70073.
Funding: This work was supported by a grant from the Simons Foundation or the Simons Foundation International (515840, L.A.C.). We are grateful to all of the families in SPARK, the SPARK clinical sites and SPARK staff.
Contributor Information
Maire Claire Diemer, Email: diemerm@musc.edu.
Laura A. Carpenter, Email: carpentl@musc.edu.
Data Availability Statement
The data that support the findings of this study are available from Simons Foundation. Restrictions apply to the availability of these data, which were used under license for this study. Data are available from https://sparkforautism.org/portal/page/autism‐research/ with the permission of Simons Foundation.
References
- Achenbach, T. M. , Krukowski R. A., Dumenci L., and Ivanova M. Y.. 2005. “Assessment of Adult Psychopathology: Meta‐Analyses and Implications of Cross‐Informant Correlations.” Psychological Bulletin 131, no. 3: 361–382. 10.1037/0033-2909.131.3.361. [DOI] [PubMed] [Google Scholar]
- Achenbach, T. M. , and Rescorla L. A.. 2003. Manual for the ASEBA Adult Forms & Profiles: For Ages 18–59; Adult Self‐Report; Adult Behavior Checklist; an Integrated System of Multi‐Informant Assessment. ASEBA. [Google Scholar]
- Bailey, D. B. , Hebbeler K., Scarborough A., Spiker D., and Mallik S.. 2004. “First Experiences With Early Intervention: A National Perspective.” Pediatrics 113, no. 4: 887–896. 10.1542/peds.113.4.887. [DOI] [PubMed] [Google Scholar]
- Baldwin, S. , and Costley D.. 2016. “The Experiences and Needs of Female Adults With High‐Functioning Autism Spectrum Disorder.” Autism 20, no. 4: 483–495. 10.1177/1362361315590805. [DOI] [PubMed] [Google Scholar]
- Baldwin, S. , Costley D., and Warren A.. 2014. “Employment Activities and Experiences of Adults With High‐Functioning Autism and Asperger's Disorder.” Journal of Autism and Developmental Disorders 44, no. 10: 2440–2449. 10.1007/s10803-014-2112-z. [DOI] [PubMed] [Google Scholar]
- Bargiela, S. , Steward R., and Mandy W.. 2016. “The Experiences of Late‐Diagnosed Women With Autism Spectrum Conditions: An Investigation of the Female Autism Phenotype.” Journal of Autism and Developmental Disorders 46, no. 10: 3281–3294. 10.1007/s10803-016-2872-8. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Beck, J. S. , Lundwall R. A., Gabrielsen T., Cox J. C., and South M.. 2020. “Looking Good but Feeling Bad: ‘Camouflaging’ Behaviors and Mental Health in Women With Autistic Traits.” Autism 24, no. 4: 809–821. 10.1177/1362361320912147. [DOI] [PubMed] [Google Scholar]
- Benjamini, Y. , and Hochberg Y.. 1995. “Controlling the False Discovery Rate: A Practical and Powerful Approach to Multiple Testing.” Journal of the Royal Statistical Society: Series B (Methodological) 57, no. 1: 289–300. 10.1111/j.2517-6161.1995.tb02031.x. [DOI] [Google Scholar]
- Begeer, S. , Mandell D., Wijnker‐Holmes B., et al. 2013. “Sex Differences in the Timing of Identification Among Children and Adults With Autism Spectrum Disorders.” Journal of Autism and Developmental Disorders 43, no. 5: 1151–1156. 10.1007/s10803-012-1656-z. [DOI] [PubMed] [Google Scholar]
- Ben Itzchak, E. , and Zachor D. A.. 2011. “Who Benefits From Early Intervention in Autism Spectrum Disorders?” Research in Autism Spectrum Disorders 5, no. 1: 345–350. 10.1016/j.rasd.2010.04.018. [DOI] [Google Scholar]
- Blanchard, A. , Chihuri S., DiGuiseppi C. G., and Li G.. 2021. “Risk of Self‐Harm in Children and Adults With Autism Spectrum Disorder: A Systematic Review and Meta‐Analysis.” JAMA Network Open 4, no. 10: e2130272. 10.1001/jamanetworkopen.2021.30272. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Brede, J. , Babb C., Jones C., et al. 2020. “‘For Me, the Anorexia Is Just a Symptom, and the Cause Is the Autism’: Investigating Restrictive Eating Disorders in Autistic Women.” Journal of Autism and Developmental Disorders 50, no. 12: 4280–4296. 10.1007/s10803-020-04479-3. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Bureau of Labor Statistics, U.S. Department of Labor, The Economics Daily . 2023. “Labor Force Participation Rate for Women Highest in the District of Columbia in 2022.”
- Census Bureau Releases . 2023. New Educational Attainment Data (Press Release Number CB23‐TPS.21). https://www.census.gov/newsroom/press‐releases/2023/educational‐attainment‐data.html.
- Cridland, E. K. , Jones S. C., Caputi P., and Magee C. A.. 2014. “Being a Girl in a Boys' World: Investigating the Experiences of Girls With Autism Spectrum Disorders During Adolescence.” Journal of Autism and Developmental Disorders 44, no. 6: 1261–1274. 10.1007/s10803-013-1985-6. [DOI] [PubMed] [Google Scholar]
- Daniels, A. M. , and Mandell D. S.. 2014. “Explaining Differences in Age at Autism Spectrum Disorder Diagnosis: A Critical Review.” Autism 18, no. 5: 583–597. 10.1177/1362361313480277. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Dawson, D. A. , Goldstein R. B., Moss H. B., Li T.‐K., and Grant B. F.. 2010. “Gender Differences in the Relationship of Internalizing and Externalizing Psychopathology to Alcohol Dependence: Likelihood, Expression and Course.” Drug and Alcohol Dependence 112, no. 1–2: 9–17. 10.1016/j.drugalcdep.2010.04.019. [DOI] [PMC free article] [PubMed] [Google Scholar]
- De Vries, L. P. , Van De Weijer M. P., Ligthart L., et al. 2020. “A Comparison of the ASEBA Adult Self Report (ASR) and the Brief Problem Monitor (BPM/18‐59).” Behavior Genetics 50, no. 5: 363–373. 10.1007/s10519-020-10001-3. [DOI] [PMC free article] [PubMed] [Google Scholar]
- D’Mello, A. M. , Frosch I. R., Li C. E., Cardinaux A. L., and Gabrieli J. D. E.. 2022. “Exclusion of Females in Autism Research: Empirical Evidence for a “Leaky” Recruitment‐to‐Research Pipeline.” Autism Research 15, no. 10: 1929–1940. 10.1002/aur.2795. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Dean, M. , Harwood R., and Kasari C.. 2017. “The Art of Camouflage: Gender Differences in the Social Behaviors of Girls and Boys With Autism Spectrum Disorder.” Autism 21, no. 6: 678–689. 10.1177/1362361316671845. [DOI] [PubMed] [Google Scholar]
- Diemer, M. C. , Gerstein E. D., and Regester A.. 2022. “Autism Presentation in Female and Black Populations: Examining the Roles of Identity, Theory, and Systemic Inequalities.” Autism 136236132211135: 1931–1946. 10.1177/13623613221113501. [DOI] [PubMed] [Google Scholar]
- Dillon, E. F. , Kanne S., Landa R. J., et al. 2023. “Sex Differences in Autism: Examining Intrinsic and Extrinsic Factors in Children and Adolescents Enrolled in a National ASD Cohort.” Journal of Autism and Developmental Disorders 53, no. 4: 1305–1318. 10.1007/s10803-021-05385-y. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Doherty, M. , Neilson S., O'Sullivan J., et al. 2022. “Barriers to Healthcare and Self‐Reported Adverse Outcomes for Autistic Adults: A Cross‐Sectional Study.” BMJ Open 12, no. 2: e056904. 10.1136/bmjopen-2021-056904. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Esang, M. , and Ahmed S.. 2018. “A Closer Look at Substance Use and Suicide.” American Journal of Psychiatry Residents' Journal 13, no. 6: 6–8. 10.1176/appi.ajp-rj.2018.130603. [DOI] [Google Scholar]
- Fannin, D. K. , Williams E. G., Fuller M., et al. 2024. “Unpacking the Prevalence: A Warning Against Overstating the Recently Narrowed Gap for Black Autistic Youth.” Autism Research 17, no. 6: 1072–1082. 10.1002/aur.3168. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Feliciano, P. , Daniels A. M., Green Snyder L., et al. 2018. “SPARK: A US Cohort of 50,000 Families to Accelerate Autism Research.” Neuron 97, no. 3: 488–493. 10.1016/j.neuron.2018.01.015. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Ferri, S. L. , Abel T., and Brodkin E. S.. 2018. “Sex Differences in Autism Spectrum Disorder: A Review.” Current Psychiatry Reports 20, no. 2: 9. 10.1007/s11920-018-0874-2. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Fombonne, E. , Coppola L., Mastel S., and O’Roak B. J.. 2022. “Validation of Autism Diagnosis and Clinical Data in the SPARK Cohort.” Journal of Autism and Developmental Disorders 52, no. 8: 3383–3398. 10.1007/s10803-021-05218-y. [DOI] [PubMed] [Google Scholar]
- Gosling, J. , Purrington J., and Hartley G.. 2023. “Exploring the Lived Experiences of Autistic Women: A Thematic Synthesis.” Review Journal of Autism and Developmental Disorders. 10.1007/s40489-023-00367-5. [DOI] [Google Scholar]
- Green, R. M. , Travers A. M., Howe Y., and McDougle C. J.. 2019. “Women and Autism Spectrum Disorder: Diagnosis and Implications for Treatment of Adolescents and Adults.” Current Psychiatry Reports 21, no. 4: 22. 10.1007/s11920-019-1006-3. [DOI] [PubMed] [Google Scholar]
- Hayward, S. M. , McVilly K. R., and Stokes M. A.. 2018. “Challenges for Females With High Functioning Autism in the Workplace: A Systematic Review.” Disability and Rehabilitation 40, no. 3: 249–258. 10.1080/09638288.2016.1254284. [DOI] [PubMed] [Google Scholar]
- Hayward, S. M. , McVilly K. R., and Stokes M. A.. 2019. ““I Would Love to Just be Myself”: What Autistic Women Want at Work.” Autism in Adulthood: Challenges and Management 1, no. 4: 297–305. 10.1089/aut.2019.0020. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Henrich, J. , Heine S. J., and Norenzayan A.. 2010. “The Weirdest People in the World?” Behavioral and Brain Sciences 33, no. 2–3: 61–83. 10.1017/S0140525X0999152X. [DOI] [PubMed] [Google Scholar]
- Hiller, R. M. , Young R. L., and Weber N.. 2016. “Sex Differences in Pre‐Diagnosis Concerns for Children Later Diagnosed With Autism Spectrum Disorder.” Autism 20, no. 1: 75–84. 10.1177/1362361314568899. [DOI] [PubMed] [Google Scholar]
- Huang, Y. , Arnold S. R., Foley K.‐R., and Trollor J. N.. 2020. “Diagnosis of Autism in Adulthood: A Scoping Review.” Autism 24, no. 6: 1311–1327. 10.1177/1362361320903128. [DOI] [PubMed] [Google Scholar]
- Huke, V. , Turk J., Saeidi S., Kent A., and Morgan J. F.. 2013. “Autism Spectrum Disorders in Eating Disorder Populations: A Systematic Review: Autism Spectrum Disorders in Eating Disorders.” European Eating Disorders Review 21, no. 5: 345–351. 10.1002/erv.2244. [DOI] [PubMed] [Google Scholar]
- Hus, Y. , and Segal O.. 2021. “Challenges Surrounding the Diagnosis of Autism in Children.” Neuropsychiatric Disease and Treatment 17: 3509–3529. 10.2147/NDT.S282569. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Hussong, A. M. , Jones D. J., Stein G. L., Baucom D. H., and Boeding S.. 2011. “An Internalizing Pathway to Alcohol Use and Disorder.” Psychology of Addictive Behaviors 25, no. 3: 390–404. 10.1037/a0024519. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Ivanova, M. Y. , Achenbach T. M., Rescorla L. A., et al. 2015. “Syndromes of Self‐Reported Psychopathology for Ages 18–59 in 29 Societies.” Journal of Psychopathology and Behavioral Assessment 37, no. 2: 171–183. 10.1007/s10862-014-9448-8. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Jadav, N. , and Bal V. H.. 2022. “Associations Between Co‐Occurring Conditions and Age of Autism Diagnosis: Implications for Mental Health Training and Adult Autism Research.” Autism Research 15, no. 11: 2112–2125. 10.1002/aur.2808. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Kanfiszer, L. , Davies F., and Collins S.. 2017. “‘I Was Just So Different’: The Experiences of Women Diagnosed With an Autism Spectrum Disorder in Adulthood in Relation to Gender and Social Relationships.” Autism 21, no. 6: 661–669. 10.1177/1362361316687987. [DOI] [PubMed] [Google Scholar]
- Keyes, K. M. , Susser E., Cheslack‐Postava K., Fountain C., Liu K., and Bearman P. S.. 2012. “Cohort Effects Explain the Increase in Autism Diagnosis Among Children Born From 1992 to 2003 in California.” International Journal of Epidemiology 41, no. 2: 495–503. 10.1093/ije/dyr193. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Klin, A. , Klaiman C., and Jones W.. 2015. “Reducing Age of Autism Diagnosis: Developmental Social Neuroscience Meets Public Health Challenge.” Revista de Neurologia 60, no. Suppl 1: S3–S11. [PMC free article] [PubMed] [Google Scholar]
- Lai, M.‐C. , Lombardo M. V., Pasco G., et al. 2011. “A Behavioral Comparison of Male and Female Adults With High Functioning Autism Spectrum Conditions.” PLoS One 6, no. 6: e20835. 10.1371/journal.pone.0020835. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Lai, M.‐C. , Lombardo M. V., Ruigrok A. N., et al. 2017. “Quantifying and Exploring Camouflaging in Men and Women With Autism.” Autism 21, no. 6: 690–702. 10.1177/1362361316671012. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Larkin, C. , Griffin E., Corcoran P., McAuliffe C., Perry I. J., and Arensman E.. 2017. “Alcohol Involvement in Suicide and Self‐Harm: Findings From Two Innovative Surveillance Systems.” Crisis 38, no. 6: 413–422. 10.1027/0227-5910/a000488. [DOI] [PubMed] [Google Scholar]
- Lehnhardt, F.‐G. , Falter C. M., Gawronski A., et al. 2016. “Sex‐Related Cognitive Profile in Autism Spectrum Disorders Diagnosed Late in Life: Implications for the Female Autistic Phenotype.” Journal of Autism and Developmental Disorders 46, no. 1: 139–154. 10.1007/s10803-015-2558-7. [DOI] [PubMed] [Google Scholar]
- Lockwood Estrin, G. , Milner V., Spain D., Happé F., and Colvert E.. 2021. “Barriers to Autism Spectrum Disorder Diagnosis for Young Women and Girls: A Systematic Review.” Review Journal of Autism and Developmental Disorders 8, no. 4: 454–470. 10.1007/s40489-020-00225-8. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Lorenc, T. , Rodgers M., Marshall D., et al. 2018. “Support for Adults With Autism Spectrum Disorder Without Intellectual Impairment: Systematic Review.” Autism 22, no. 6: 654–668. 10.1177/1362361317698939. [DOI] [PubMed] [Google Scholar]
- Maenner, M. J. , Warren Z., Williams A. R., et al. 2023. “Prevalence and Characteristics of Autism Spectrum Disorder Among Children Aged 8 Years—Autism and Developmental Disabilities Monitoring Network, 11 Sites, United States, 2020.” MMWR Surveillance Summaries 72, no. 2: 1–14. 10.15585/mmwr.ss7202a1. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Malow, B. A. , Qian Y., Ames J. L., Alexeeff S., and Croen L. A.. 2023. “Health Conditions in Autism: Defining the Trajectory From Adolescence to Early Adulthood.” Autism Research 16, no. 7: 1437–1449. 10.1002/aur.2960. [DOI] [PMC free article] [PubMed] [Google Scholar]
- McCaul, M. E. , Roach D., Hasin D. S., Weisner C., Chang G., and Sinha R.. 2019. “Alcohol and Women: A Brief Overview.” Alcoholism, Clinical and Experimental Research 43, no. 5: 774–779. 10.1111/acer.13985. [DOI] [PMC free article] [PubMed] [Google Scholar]
- McDonnell, C. G. , DeLucia E. A., Hayden E. P., et al. 2020. “Sex Differences in Age of Diagnosis and First Concern Among Children With Autism Spectrum Disorder.” Journal of Clinical Child & Adolescent Psychology 50: 1–11. 10.1080/15374416.2020.1823850. [DOI] [PubMed] [Google Scholar]
- McHugh, R. K. , Votaw V. R., Sugarman D. E., and Greenfield S. F.. 2018. “Sex and Gender Differences in Substance Use Disorders.” Clinical Psychology Review 66: 12–23. 10.1016/j.cpr.2017.10.012. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Miller, D. , Rees J., and Pearson A.. 2021. ““Masking Is Life”: Experiences of Masking in Autistic and Nonautistic Adults.” Autism in Adulthood 3, no. 4: 330–338. 10.1089/aut.2020.0083. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Moseley, R. L. , Hitchiner R., and Kirkby J. A.. 2018. “Self‐Reported Sex Differences in High‐Functioning Adults With Autism: A Meta‐Analysis.” Molecular Autism 9, no. 1: 33. 10.1186/s13229-018-0216-6. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Napolitano, A. , Schiavi S., La Rosa P., et al. 2022. “Sex Differences in Autism Spectrum Disorder: Diagnostic, Neurobiological, and Behavioral Features.” Frontiers in Psychiatry 13: 889636. 10.3389/fpsyt.2022.889636. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Nevison, C. , and Zahorodny W.. 2019. “Race/Ethnicity‐Resolved Time Trends in United States ASD Prevalence Estimates from IDEA and ADDM.” Journal of Autism and Developmental Disorders 49, no. 12: 4721–4730. 10.1007/s10803-019-04188-6. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Nyrenius, J. , Waern M., Eberhard J., Ghaziuddin M., Gillberg C., and Billstedt E.. 2023. “Autism in Adult Psychiatric Out‐Patients: Self‐Reported Suicidal Ideation, Suicide Attempts and Non‐Suicidal Self‐Injury.” BJPsych Open 9, no. 5: e167. 10.1192/bjo.2023.553. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Pinkerton, K. E. , Harbaugh M., Han M. K., et al. 2015. “Women and Lung Disease. Sex Differences and Global Health Disparities.” American Journal of Respiratory and Critical Care Medicine 192, no. 1: 11–16. 10.1164/rccm.201409-1740PP. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Pew Research Center . 2016. “Social and Demographic Trends.”
- Rescorla, L. A. , Achenbach T. M., Ivanova M. Y., et al. 2016. “Problems and Adaptive Functioning Reported by Adults in 17 Societies.” International Perspectives in Psychology 5, no. 2: 91–109. 10.1037/ipp0000046. [DOI] [Google Scholar]
- Rosen, T. E. , Mazefsky C. A., Vasa R. A., and Lerner M. D.. 2018. “Co‐Occurring Psychiatric Conditions in Autism Spectrum Disorder.” International Review of Psychiatry 30, no. 1: 40–61. 10.1080/09540261.2018.1450229. [DOI] [PubMed] [Google Scholar]
- Russell, A. S. , McFayden T. C., McAllister M., et al. 2025. “Who, When, Where, and Why: A Systematic Review of ‘Late Diagnosis’ in Autism.” Autism Research 18, no. 1: 22–36. 10.1002/aur.3278. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Rylaarsdam, L. , and Guemez‐Gamboa A.. 2019. “Genetic Causes and Modifiers of Autism Spectrum Disorder.” Frontiers in Cellular Neuroscience 13: 385. 10.3389/fncel.2019.00385. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Rynkiewicz, A. , Janas‐Kozik M., and Słopień A.. 2019. “Girls and Women With Autism.” Psychiatria Polska 53, no. 4: 737–752. 10.12740/PP/OnlineFirst/95098. [DOI] [PubMed] [Google Scholar]
- Sedgewick, F. , Hill V., Yates R., Pickering L., and Pellicano E.. 2016. “Gender Differences in the Social Motivation and Friendship Experiences of Autistic and Non‐autistic Adolescents.” Journal of Autism and Developmental Disorders 46, no. 4: 1297–1306. 10.1007/s10803-015-2669-1. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Shenouda, J. , Barrett E., Davidow A. L., et al. 2023. “Prevalence and Disparities in the Detection of Autism Without Intellectual Disability.” Pediatrics 151, no. 2: e2022056594. 10.1542/peds.2022-056594. [DOI] [PubMed] [Google Scholar]
- Sidaros, R. 2017. “Current Challenges in the Management of LGBT Suicide.” American Journal of Psychiatry Residents' Journal 12, no. 1: 8–10. 10.1176/appi.ajp-rj.2017.120103. [DOI] [Google Scholar]
- Strang, J. F. , Van Der Miesen A. I., Caplan R., Hughes C., daVanport S., and Lai M.‐C.. 2020. “Both Sex‐ and Gender‐Related Factors Should Be Considered in Autism Research and Clinical Practice.” Autism 24, no. 3: 539–543. 10.1177/1362361320913192. [DOI] [PubMed] [Google Scholar]
- Thurm, A. , Farmer C., Salzman E., Lord C., and Bishop S.. 2019. “State of the Field: Differentiating Intellectual Disability From Autism Spectrum Disorder.” Frontiers in Psychiatry 10: 526. 10.3389/fpsyt.2019.00526. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Towers, E. B. , Williams I. L., Qillawala E. I., Rissman E. F., and Lynch W. J.. 2023. “Sex/Gender Differences in the Time‐Course for the Development of Substance Use Disorder: A Focus on the Telescoping Effect.” Pharmacological Reviews 75, no. 2: 217–249. 10.1124/pharmrev.121.000361. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Veatch, O. J. , Maxwell‐Horn A. C., and Malow B. A.. 2015. “Sleep in Autism Spectrum Disorders.” Current Sleep Medicine Reports 1, no. 2: 131–140. 10.1007/s40675-015-0012-1. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Weir, E. , Allison C., and Baron‐Cohen S.. 2021. “The Sexual Health, Orientation, and Activity of Autistic Adolescents and Adults.” Autism Research 14, no. 11: 2342–2354. 10.1002/aur.2604. [DOI] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Supplementary Materials
Table S1. Logistic regression: Diagnostic age predicting odds of being married, controlling for current age.
Table S2. Linear regression analysis: Diagnostic age predicting highest education level attained, controlling for current age.
Table S3. Linear regression analysis: Diagnostic age predicting employment status, controlling for current age.
Table S4. Linear regression analysis: Diagnostic age predicting income, controlling for current age.
Table S5. Control variables analyzed for relation to ASR composite variables for main analyses regressions.
Data Availability Statement
The data that support the findings of this study are available from Simons Foundation. Restrictions apply to the availability of these data, which were used under license for this study. Data are available from https://sparkforautism.org/portal/page/autism‐research/ with the permission of Simons Foundation.