



Abstract
Objective
Describe anti-Müllerian hormone (AMH) variation across normal menstrual cycles.
Design
Cohort study
Setting
Academic environment
Patients
Twenty regularly-menstruating women
Interventions
Serum AMH and inhibin B assayed daily during one normal menstrual cycle
Main Outcome Measures
Intracycle variability of AMH and inhibin B
Results
Data was classified into quartiles of AMH area-under-the-curve (AUCs). Mean AMH AUC was 15.7 ng/ml for Quartile 1 vs. 43.5, 80.9 and 144.9 ng/ml for Quartiles 2, 3 and 4. Mean AMH levels (ng/ml) were 0.67, 1.71, 3.02, and 5.33, respectively. There was no variation in Quartile 1 AMH rate of change from stochastic modeling, but in Quartiles 2–4, there were increased rates of change in days 2–7. Women in Quartile 1 had the lowest mean inhibin B (24.2 pg/ml vs. 44.3, 43.2, and 42.2 pg/ml) and had shorter menstrual cycles (24.6 days) than women in Quartiles 3 and 4 (28.2 and 28.4 days).
Conclusions
There were two menstrual cycle patterns of AMH. The “aging ovary” pattern included low AMH levels with little variation, lower inhibin B and shorter cycle lengths. The “younger ovary” pattern included higher AMH levels with significant variation days 2–7, suggesting that for women with AMH >1 ng/ml, the interpretation of AMH levels is contingent upon the day of the menstrual cycle on which specimen is obtained.
Key Terms: AMH, menstrual cycle variability, ovarian aging, reproductive aging, ovarian reserve
INTRODUCTION (n=2228)
Biomarkers of ovarian reserve are used to clinically assess fertility potential, guide infertility treatment and, more recently, estimate time to the final menstrual period (1–4). The ideal biomarker of ovarian reserve would directly measure the process of folliculogenesis and accurately reflect the functional capacity of the ovary. Two such candidate biomarkers are anti-Müllerian hormone (AMH) and inhibin B, paracrine modulators of follicular development and dominant follicle selection produced by ovarian granulosa cells (5).
There is particular interest in using measures of AMH as a biomarker because it is thought to have minimal within-menstrual cycle variation as compared to inhibin B or the more classically assessed follicle-stimulating hormone (FSH) (6). Serum AMH levels decline with age and menstrual cycle variability (7, 8) and reach undetectable levels approximately 5 years before final menstrual period (7). AMH is a product of granulosa cells of primordial follicles that have undergone initial recruitment and is thought to reflect the size and quality of the ovarian reserve (9). Inhibin B, also a product of granulosa and theca cells, amplifies FSH withdrawal from non-dominant follicles during the preovulatory period, facilitating the development of a single dominant ovulatory follicle (10). As a biomarker, inhibin B is thought to represent the gonadotropin-responsive antral follicle pool. With diminishing ovarian reserve, the decline in inhibin B is associated with a concomitant rise in FSH from the progressive withdrawal of negative feedback from the ovary to the pituitary (11).
The degree of daily AMH variability across the normal menstrual cycle as well as correlation of these AMH levels with inhibin B levels during the menstrual cycle have yet to be fully described. However, this information is central to understanding and interpreting AMH assay information. Two studies (12, 13) have reported a statistically significant late follicular phase peak in AMH levels during a normal menstrual cycle. Conversely, other studies (14–17) have failed to identify the presence of significant variation across the menstrual cycle. These reported inconsistencies may be attributable to limitations in the published studies including inadequate sample sizes, infrequent sampling of days across the menstrual cycle, or sampling of women with different chronological ages which, to some degree, is a proxy for ovarian aging and declining ovarian reserve.
We hypothesized that AMH levels were relatively invariant across the menstrual cycle in women aged 30–40 years whose chronological age placed them at risk for diminished ovarian reserve. An effective means of assessing this hypothesis was to obtain daily serum AMH values, analyzing them with a time series approach. This study differs from previous reports in that, for the first time, AMH and inhibin B values were assayed daily across an entire menstrual cycle, providing the most complete characterization of the intracycle variability of AMH and inhibin B. This additional information will improve the interpretation of AMH levels used to characterize ovarian reserve.
MATERIALS AND METHODS
Population
Specimens for assay of serum AMH and inhibin B were collected daily from 20 healthy women aged 30–40 years who reported regular menstruation. This resulted in 537 specimens available for analyses. Samples were collected beginning at the onset of menstrual bleeding and ending at the subsequent initiation of menstrual bleeding. Cycle lengths ranged from 23 to 35 days. The body mass index (BMI) of study participants ranged from 24.5 to 26.5 kg/m2. Women volunteers were recruited from the University of Michigan and the Michigan Health System using flyers and postings to bulletin boards designated for recruitment of research participants. Women using oral or injected contraceptive preparations or who smoked were not recruited. Also not recruited were women who reported diagnoses of or treatment for diseases including a diagnosis of polycystic ovary syndrome. The protocol and recruitment practices were approved by the University of Michigan Institutional Review Board.
Specimens and Assays
Specimens were collected daily from fasting participants, prior to 10 am. At the time of collection, specimens were aliquoted and stored at −80 degrees Centigrade without thaw until assay.
A commercially available enzyme-linked immunosorbence assay (ELISA) from Diagnostic Systems Laboratories (Beckman Coulter, DSL, Webster, TX) were used for the in vitro quantitative measurement of Müllerian Inhibiting Substance/Anti-Müllerian Hormone (MIS/AMH) in human serum. This ELISA is a direct competitive immunoassay without sample extraction or hydrolysis. Sample wells were coated with a primary antibody. The detection system consisted of a biotinylated secondary antibody and strepavidin-labeled horseradish peroxidase. Specimens were assayed in duplicate. There is no detectable cross-reactivity with closely related compounds. The assay measured AMH concentrations from 0.017 ng/mL to 10 ng/mL with an assay range (standard curve) of 0.05 ng/mL to10 ng/mL. Manufacturer-specified inter-assay coefficients of variation (CV) were 8.0% at 0.15 ng/mL, 4.8% at 0.85 ng/mL and 6.7% at 4.28 ng/mL (mean = 6.5%); intra-assay CVs were 4.6% at 0.14 ng/mL, 2.4% at 0.84 ng/mL and 3.3% at 4.41 ng/mL (mean= 4.0%).
Serum inhibin B concentrations were measured in duplicate with α-βB dimeric ELISA and referenced to a standard of human inhibin B preparation isolated from human follicular fluid provided by Nigel Groome (Oxford Brookes University, Oxford, UK). Specimens were assayed in duplicate. The assay sensitivity is 4 pg/L. The within- and between-assay variations were 11.7% and 15.6%, respectively. Assays for both AMH and inhibin B were measured in a single time period and kits came from single lots.
Other Measures
Height and weight data for each study participant were collected at the time of enrollment and were used to calculate BMI as weight (kilograms) divided by height squared (meters).
Statistical Analysis
Daily AMH and inhibin B values for each of the 20 women were individually plotted to characterize their levels over the course of a normal menstrual cycle. These plots confirmed that, for each woman, inhibin B levels were very low or below the assay detection level (<10 ng/ml) in the late luteal phase of the menstrual cycle. For each woman, daily AMH and inhibin B levels were also summed over the menstrual cycle to create total AMH and inhibin B areas-under-the-curve (AUC). The AMH AUC was categorized into quartiles because of its skewed distribution.
Means and standard errors were calculated for age, menstrual cycle lengths, and hormone values, overall and by quartile of the AMH distribution. Non-parametric stochastic mixed modeling with a smoothing spline was used to describe the daily AMH and inhibin B profiles over the menstrual cycle. Both measures were log-transformed for model fitting and back-transformed into the original scale for data presentation.
RESULTS
The mean AMH AUC of Quartile 1 was 15.7 ng/ml compared to the progressively higher mean AMH AUC values of 43.5, 80.9 and 144.9 ng/ml in Quartiles 2–4, respectively. The mean AMH level within each quartile was 0.67, 1.71, 3.02, and 5.33 ng/ml, respectively (Table 1). Quartile 1 values for AMH AUC (p=0.007), mean AMH (p=0.009), inhibin B AUC (p=0.006), and mean inhibin B (p=0.002) were statistically significantly different than values of Quartiles 2–4. The average menstrual cycle duration for the AMH quartiles were 24.6, 26.2, 28.2, and 28.4 days, respectively.
Table 1.
AMH area under the curve, mean AMH, inhibin B area under the curve, mean inhibin B, mean menstrual cycle length and chronological age, based on AMH AUC quartiles in 20 women
| AMH AUC quartile | AMH AUC (ng/ml) Mean (se) |
Mean AMH (ng/ml) Mean (se) |
Inhibin B (pg/ml) AUC Mean (se) |
Mean Inhibin B (pg/ml) Mean (se) |
Menstrual Cycle Length (day) Mean (se) |
Age Mean (se) |
|---|---|---|---|---|---|---|
| 1 | 15.7 (2.5) | 0.67 (0.11) | 563.9 (35.0) | 24.2 (1.8) | 24.6 (0.5) | 35.8 (1.3) |
| 2 | 43.5 (6.3) | 1.71 (0.21) | 1065.7 (193.5) | 44.3 (9.5) | 26.2 (0.7) | 37.0 (1.5) |
| 3 | 80.9 (5.11) | 3.02 (0.16) | 1112.1 (183.4) | 43.2 (8.3) | 28.2 (1.8) | 37.8 (0.8) |
| 4 | 144.9 (25.3) | 5.33 (1.05) | 1136.1 (170.4) | 42.2 (5.0) | 28.4 (1.2) | 34.8 (1.7) |
| AMH AUC quartile 1 comparison to other quartiles* | 1 vs 2,3,4: p=0.007 | 1 vs. 2,3,4 p=0.009 |
1 vs 2,3,4: p=0.006 | 1 vs 2,3,4: p=0.02 | 1,2 vs 3,4: p=0.02 | |
| Pair-wise comparisons of AMH AUC Quartile 1 to AMH AUC quartiles 2, 3, and 4* | 1 vs 2: p=0.16 | 1 vs. 2: p=0.19 | 1 vs 2:p=0.04 | 1 vs 2:p=0.05 | 1 vs 2; p =0.34 | NS |
| 1 vs 3:p=0.003 | 1 vs.3:p=0.008 | 1 vs 3:p=0.03 | 1 vs 3:p=0.07 | 1 vs 3: p=0.04 | ||
| 1 vs 4:p<0.0001 | 1 vs 4:p<.0001 | 1 vs 4:p=0.02 | 1 vs 4:p=0.08 | 1 vs 4: p=0.03 | ||
Statistical tests based on analysis of covariance with orthogonal contracts.
Figure 1A, upper panel, shows the mean AMH profile for Quartile 1 as well as the individual data points across the menstrual cycle. This low profile is in contrast to the mean higher AMH profiles in Quartiles 2–4 (see Figure 1B–D). Not only were the mean AMH profiles observed in Quartiles 2–4 considerably higher across the cycle, the AMH profiles showed greater variation, particularly in days 2–7 following onset of menses.
Figure 1.
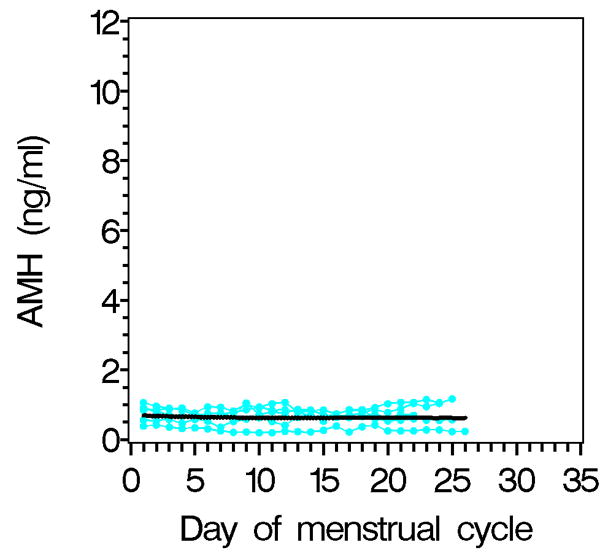
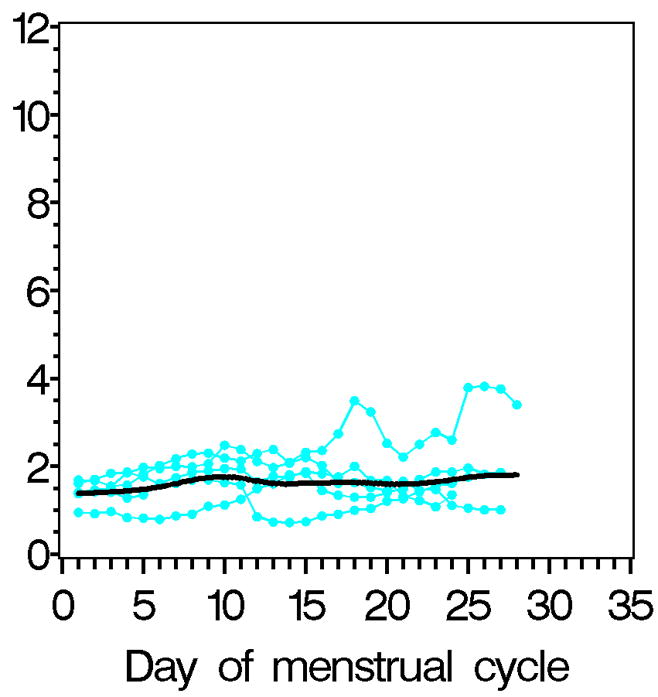
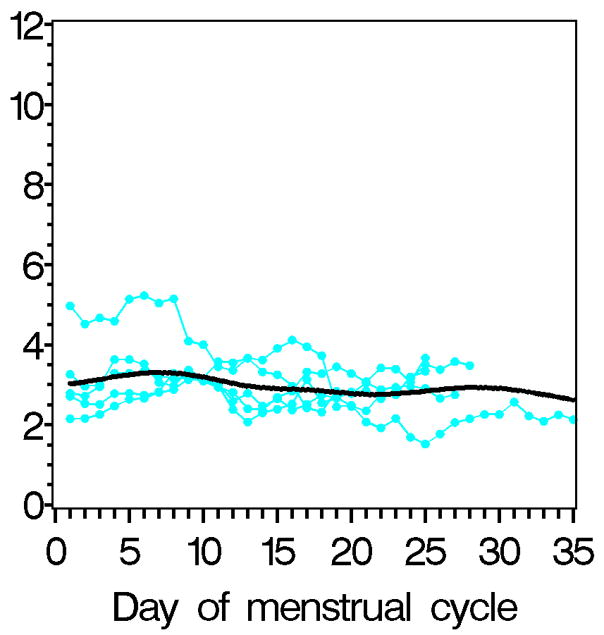
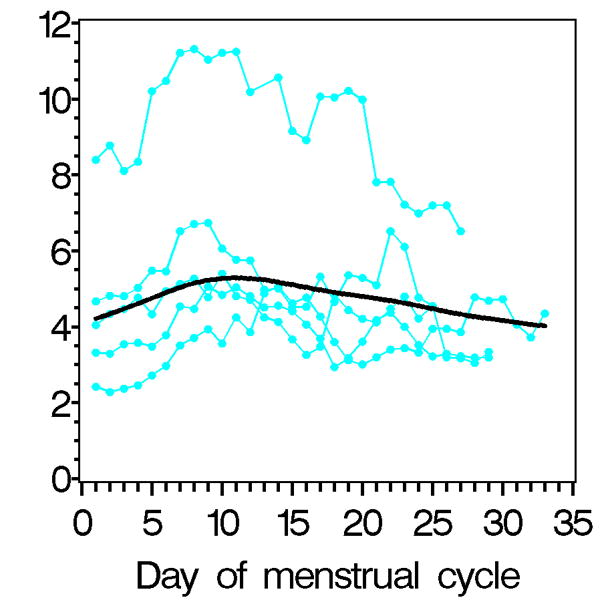
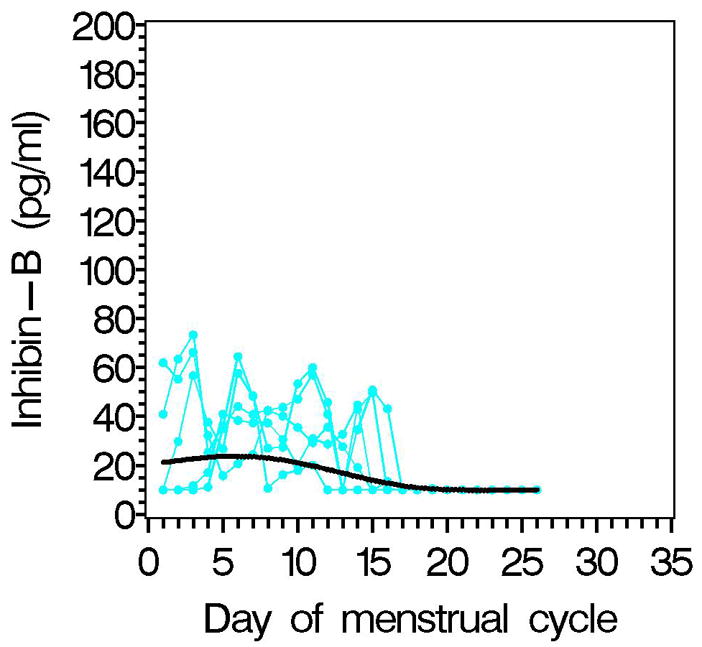
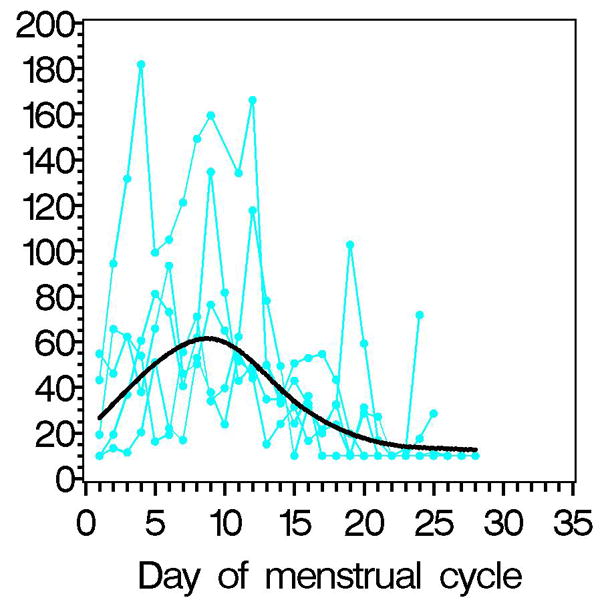
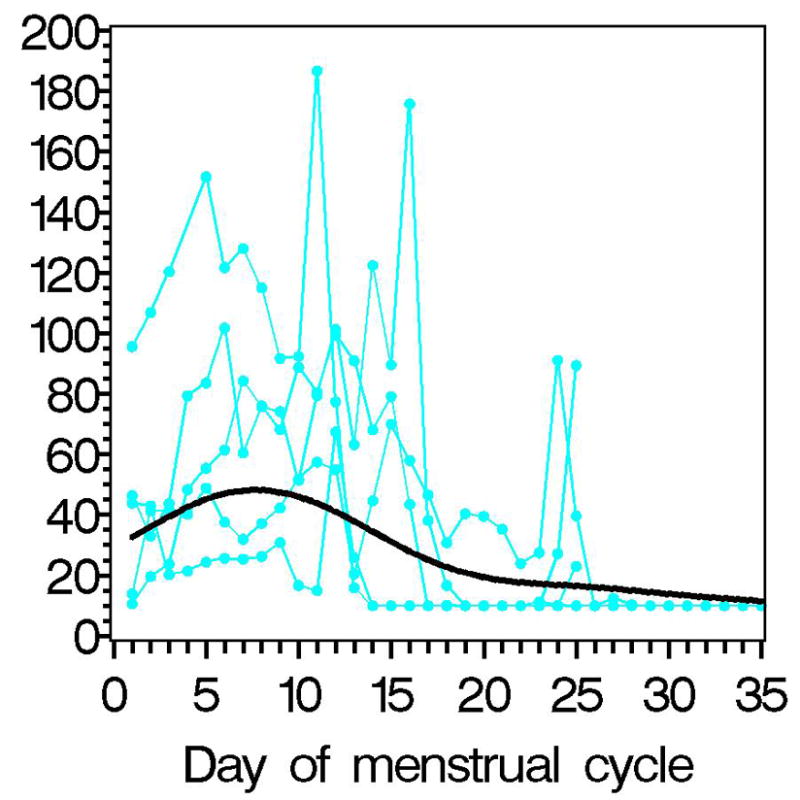
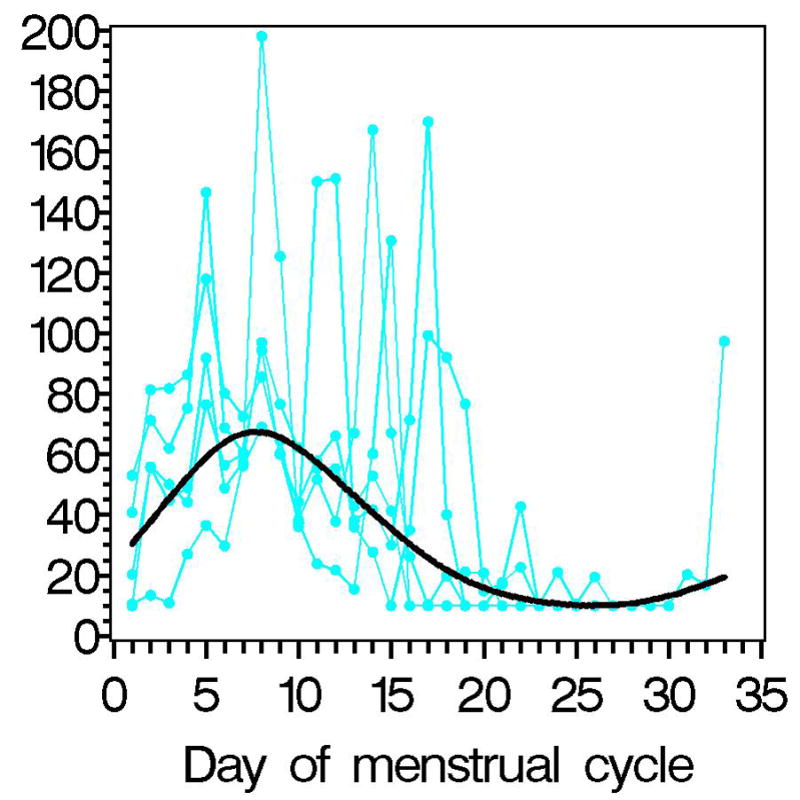
Mean AMH (top panel, 1A–1D) and inhibin B (bottom panel, 1E–1H) across the menstrual cycle in 20 women, according to quartiles of their AMH area-under-the-curve. Black solid line is the spline smoothed mean values and the cyan dashed lines are individual profiles
The mean inhibin B values for each AMH AUC quartile were 24.2, 44.3, 43.2, and 42.2 pg/ml, respectively (Table 1). Women in AMH AUC Quartile 1 had the lowest mean inhibin B level, the lowest inhibin B AUC, and shorter mean menstrual cycle length. In contrast, women in Quartiles 2–4 had similar inhibin B AUC and mean inhibin B levels (see Figure 1E–H). The low AMH levels with minimal variation through the cycle in the Quartile 1 were correlated with strikingly lower inhibin B values in that quartile.
DISCUSSION
For the first time, we identified two distinct patterns in AMH profiles. The AMH profile in the lowest AMH AUC quartile (Quartile 1) had minimal variation throughout the menstrual cycle. This profile was also associated with strikingly low inhibin B values in that quartile. This pattern was consistent with the commonly held belief that there is minimal variation of AMH across the menstrual cycle and this suggests an “aging ovary” pattern or diminished ovarian reserve in women in the lowest quartile. These women had the lowest mean AMH level (< 1 ng/ml), AMH AUC, mean inhibin B, inhibin B AUC, and shorter menstrual cycle lengths. These findings parallel a recent report that twenty five percent of women with incipient ovarian failure have low AMH levels, even in the setting of continued regular menstrual cycles (18). It is interesting to note the similar results between our study and Knauff et al despite the fact that they used a preselected population of patients recruited from infertility clinics while we used a non-selected population of patients.
There was a contrasting “younger ovary” pattern embodied in the remaining three quartiles where women had higher AMH profiles. These profiles demonstrated significant follicular phase AMH variation. In these women, inhibin B levels were also significantly higher. Notably, the chronological ages of women with the “aging ovary” pattern were not significantly different that the mean chronological ages of those women characterized as being in the “younger ovarian” groups, albeit all women studied were between 30 to 40 years.
The extant literature includes reports of both noticeable fluctuations and flat profiles in AMH levels across the menstrual cycle. Our report identifies two distinct patterns of AMH expression through out a single menstrual cycle, and offers the first explanation for the apparent discrepant results seen in prior studies. Those reports that included women with greater ovarian reserve may observe AMH profile variability across the menstrual cycle whereas investigations including chronologically older women and limited days of sampling may report flat profiles. Visually, the composite plot of raw data across the cycle provided by Hehenkamp et al. (17) reveals the presence of two AMH patterns. Yet, while these investigators discussed the presence of AMH variation across the menstrual cycle among women with higher AMH, they reported a single fitted profile. These investigators evaluated a sample of women ranging in age from 25.6 to 46.2 years which increases the likelihood that their data was from a mix of women with “younger ovarian” profiles and “aging ovarian” profiles.
The follicular phase rise of AMH profiles, consistent with our “younger ovary” pattern, was reported by Wunder et al. (13) where specimens from 36 women aged 20 to 32 years were taken on alternating days except for the time around ovulation during which sampling occurred daily. The investigators reported a statistically significant rise in AMH during the follicular phase using paired nonparametric statistical testing. The relatively young age range of participants in this group would support the concept of a “younger ovary” pattern.
Our finding that the AMH profiles reflecting the “aging ovary” pattern were accompanied by low inhibin B concentrations replicates findings from other research. Tsepelidis et al. (14) previously reported that low AMH levels were accompanied by low inhibin B values. It is noteworthy that our inhibin B values remained above the detection level of the assay and then, like the pattern seen in the women with the “younger ovary” pattern, fell to values below the level of assay detection in the second half of the menstrual cycle.
We found that the inhibin B AUC gradient did not replicate the AMH AUC gradient in which there were progressively higher mean AMH levels for each quartile. In contrast, the inhibin B AUC values were similar in the upper three quartiles of the AMH AUC. If the gradient of AMH AUC is generated by granulosa cells from a steadily declining number of recruitable primordial cells but the number of recruited preantral follicles, whose granulosa cells produce the inhibin B, is more constant until later in the ovarian aging process, this would account for the difference in the gradients between the two biomarkers. The biological interpretation of this requires further evaluation in that it infers that there is an underlying regulation of apoptotic processes to sustain a more stable number of preantral follicles. Further, if the inhibin B AUC is relatively fixed, then the value of inhibin B as a marker of early ovarian aging would be less valuable than a measure of AMH levels because of the absence of this gradient. However, the combination of both AMH and inhibin B in relation to each other might be a useful index of the integrity of the recruitment process in anticipation of the likelihood of ovulation. Unfortunately, our sample size is too small to address this in detail.
In conclusion, we observed that AMH varies across the menstrual cycle differently based on the relative ovarian age rather than chronological age. The “younger ovary” pattern had a higher mean AMH, higher AMH AUC, higher inhibin B AUC, and a rise in AMH during the follicular phase of the menstrual cycle. This is in contrast with an “aging ovary” pattern with low mean AMH, low AMH AUC, strikingly low inhibin B levels, shorter menstrual cycle lengths and minimal variation in AMH levels during the cycle, suggesting diminished ovarian reserve. Both patterns were discernible in these women who ranged in age from 30 to 40 years. Understanding the potential for and attributes of these two patterns has immediate clinical relevance in interpreting assays of ovarian reserve. These data suggest that, with this assay, if the AMH level is below 1 ng/ml, then this is likely indicative of a constituently low level and decreased ovarian reserve, and this interpretation could be made independent of the day of collection across the menstrual cycle. In contrast, interpretation of higher AMH levels will be dependent upon the day in which the specimen is collected within the menstrual cycle.
Acknowledgments
Grants supporting the writing of this manuscript: General Clinical Research Center for phlebotomy work has been supported in part by NIH grant UL1RR024986. Recruitment and data analyses were supported by the Center for Integrated Approaches to Complex Diseases (MF Sowers, Director).
Enzyme- linked immunosorbence assays (ELISA) from Diagnostic Systems Laboratories (Beckman Coulter, DSL, Webster, Texas) were used for the in vitro quantitative measurement of Müllerian Inhibiting Substance/Anti-Müllerian Hormone (MIS/AMH) in human serum.
Footnotes
The research was conducted at the University of Michigan, Ann Arbor, Michigan
Conflict of Interest: MFS, DM, KG, HZ, BN, JM & JR have no conflicts of interest.
Publisher's Disclaimer: This is a PDF file of an unedited manuscript that has been accepted for publication. As a service to our customers we are providing this early version of the manuscript. The manuscript will undergo copyediting, typesetting, and review of the resulting proof before it is published in its final citable form. Please note that during the production process errors may be discovered which could affect the content, and all legal disclaimers that apply to the journal pertain.
References
- 1.Steiner AZ. Clinical implications of ovarian reserve testing. Obstet Gynecol Surv. 2009;64:120–8. doi: 10.1097/OGX.0b013e3181932e3f. [DOI] [PubMed] [Google Scholar]
- 2.Kligman I, Rosenwaks Z. Differentiating clinical profiles: Predicting good responders, poor responders, and hyperresponders. Fertil Steril. 2001;76:1185–90. doi: 10.1016/s0015-0282(01)02893-x. [DOI] [PubMed] [Google Scholar]
- 3.Robertson DM, Hale GE, Fraser IS, Hughes CL, Burger HG. A proposed classification system for menstrual cycles in the menopausal transition based on changes in serum profiles. Menopause. 2008;15:1139–44. doi: 10.1097/gme.0b013e3181735687. [DOI] [PubMed] [Google Scholar]
- 4.Hale GE, Zhao X, Hughes CL, Burger HG, Robertson DM, Fraser IS. Endocrine features of menstrual cycles in middle and late reproductive age and the menopausal transition classified according to the staging of reproductive aging workshop (STRAW) staging system. J Clin Endocrinol Metab. 2007;92:3060–7. doi: 10.1210/jc.2007-0066. [DOI] [PubMed] [Google Scholar]
- 5.Knight PG, Glister C. TGF-beta superfamily members and ovarian follicle development. Reproduction. 2006;132:191–206. doi: 10.1530/rep.1.01074. [DOI] [PubMed] [Google Scholar]
- 6.Fanchin R, Taieb J, Lozano DH, Ducot B, Frydman R, Bouyer J. High reproducibility of serum anti-mullerian hormone measurements suggests a multi-staged follicular secretion and strengthens its role in the assessment of ovarian follicular status. Hum Reprod. 2005;20:923–7. doi: 10.1093/humrep/deh688. [DOI] [PubMed] [Google Scholar]
- 7.Sowers MR, Eyvazzadeh AD, McConnell D, Yosef M, Jannausch ML, Zhang D, et al. Anti-mullerian hormone and inhibin B in the definition of ovarian aging and the menopause transition. J Clin Endocrinol Metab. 2008;93:3478–83. doi: 10.1210/jc.2008-0567. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 8.Van Rooij IA, Tonkelaar I, Broekmans FJ, Looman CW, Scheffer GJ, de Jong FH, Themmen AP, te Velde ER. Anti-Mullerian hormone is a promising predictor for the occurrence of the menopausal transition. Menopause. 2004;11(6 pt 1):601–6. doi: 10.1097/01.gme.0000123642.76105.6e. [DOI] [PubMed] [Google Scholar]
- 9.McGee EA, Hsueh AJ. Initial and cyclic recruitment of ovarian follicles. Endocr Rev. 2000;21:200–14. doi: 10.1210/edrv.21.2.0394. [DOI] [PubMed] [Google Scholar]
- 10.Welt CK. Regulation and function of inhibins in the normal menstrual cycle. Semin Reprod Med. 2004;22:187–93. doi: 10.1055/s-2004-831894. [DOI] [PubMed] [Google Scholar]
- 11.Klein NA, Illingworth PJ, Groome NP, McNeilly AS, Battaglia DE, Soules MR. Decreased inhibin B secretion is associated with the monotropic FSH rise in older, ovulatory women: A study of serum and follicular fluid levels of dimeric inhibin A and B in spontaneous menstrual cycles. J Clin Endocrinol Metab. 1996;81:2742–5. doi: 10.1210/jcem.81.7.8675606. [DOI] [PubMed] [Google Scholar]
- 12.Cook CL, Siow Y, Taylor S, Fallat ME. Serum mullerian-inhibiting substance levels during normal menstrual cycles. Fertil Steril. 2000;73:859–61. doi: 10.1016/s0015-0282(99)00639-1. [DOI] [PubMed] [Google Scholar]
- 13.Wunder DM, Bersinger NA, Yared M, Kretschmer R, Birkhauser MH. Statistically significant changes of antimullerian hormone and inhibin levels during the physiologic menstrual cycle in reproductive age women. Fertil Steril. 2008;89:927–33. doi: 10.1016/j.fertnstert.2007.04.054. [DOI] [PubMed] [Google Scholar]
- 14.Tsepelidis S, Devreker F, Demeestere I, Flahaut A, Gervy C, Englert Y. Stable serum levels of anti-mullerian hormone during the menstrual cycle: A prospective study in normo-ovulatory women. Hum Reprod. 2007;22:1837–40. doi: 10.1093/humrep/dem101. [DOI] [PubMed] [Google Scholar]
- 15.La Marca A, Malmusi S, Giulini S, Tamaro LF, Orvieto R, Levratti P, et al. Anti-mullerian hormone plasma levels in spontaneous menstrual cycle and during treatment with FSH to induce ovulation. Hum Reprod. 2004;19:2738–41. doi: 10.1093/humrep/deh508. [DOI] [PubMed] [Google Scholar]
- 16.La Marca A, Stabile G, Artenisio AC, Volpe A. Serum anti-mullerian hormone throughout the human menstrual cycle. Hum Reprod. 2006;21:3103–7. doi: 10.1093/humrep/del291. [DOI] [PubMed] [Google Scholar]
- 17.Hehenkamp WJ, Looman CW, Themmen AP, de Jong FH, Te Velde ER, Broekmans FJ. Anti-mullerian hormone levels in the spontaneous menstrual cycle do not show substantial fluctuation. J Clin Endocrinol Metab. 2006;91:4057–63. doi: 10.1210/jc.2006-0331. [DOI] [PubMed] [Google Scholar]
- 18.Knauff EA, Eijkemans MJ, Lambalk CB, ten Kate-Booij MJ, Hoek A, Beerendonk CC, Laven JS, Goverde AJ, Broekmans FJ, Themmen AP, de Jong FH, Fauser BC Dutch Premature Ovarian Failure Consortium. Anti-Mullerian hormone, inhibin B, and antral follicle count in young women with ovarian failure. J Clin Endocrinol Metab. 2009;94:786–792. doi: 10.1210/jc.2008-1818. [DOI] [PubMed] [Google Scholar]