



Abstract
Cigarette smoking is the single most important risk factor for the development of cardiovascular and pulmonary diseases (CVPD), however, the role of nicotine in the pathogenesis of CVPD is incompletely understood. The purpose of this study was to examine the effects of chronic nicotine inhalation on the development of CVPD with a focus on blood pressure (BP) and cardiac remodeling. Male C57BL6/J mice were exposed to air (control) or nicotine vapor (daily, 12 h on/12 h off) for 8 weeks. Systemic BP was recorded weekly by radio-telemetry and cardiac remodeling was monitored by echocardiography. At the end of the 8 weeks, mice were subjected to right heart catheterization to measure right ventricular systolic pressure (RVSP). Nicotine-exposed mice exhibited elevated systemic BP from weeks 1–3, which then returned to baseline from weeks 4–8, indicating development of tolerance to nicotine. At 8 weeks, significantly increased RVSP was detected in nicotine-exposed mice compared to the air controls. Echocardiography showed that 8-week nicotine inhalation resulted in RV hypertrophy with increased RV free wall thickness and a trend of increase in RV internal diameter. In contrast, there were no significant structural or functional changes in the left ventricle (LV) following nicotine exposure. Mechanistically we observed increased expression of angiotensin-converting enzyme and enhanced activation of mitogen-activated protein kinase pathways in the RV but not in the LV. We conclude that chronic nicotine inhalation alters both systemic and pulmonary BP with the latter accompanied by RV remodeling, possibly leading to progressive and persistent pulmonary hypertension.
Keywords: hypertension, pulmonary hypertension, nicotine, right ventricular remodeling, angiotensin-converting enzyme
Graphical Abstract

INTRODUCTION
Cigarette smoking is the single most important risk factor for the development of cardiovascular and pulmonary diseases (CVPD), with smokers being 2–4 times more likely to develop CVPD than non-smokers.1 Although cigarette smoking has been in constant decline since the 1950’s, the introduction of electronic cigarettes (e-cig) or electronic nicotine delivery system has attracted former smokers as well as a new generation of consumers. Of great concern, use of nicotine inhalation devices is becoming an epidemic among young adults and youths,2 emphasizing the need for further study of the potential cardiopulmonary risks of nicotine and associated products.
Nicotine is the addictive component of all tobacco products; however, the effects of nicotine are not limited to the central nervous system. With regards to the cardiovascular system, it has been reported that nicotine inhalation leads to acute increases in both systolic and diastolic blood pressure (BP) as well as heart rate (HR).3–5 The effect of cigarette smoking or nicotine inhalation on long-term BP control, however, is controversial. Although surveys of outpatient BP measurement report that smokers have either similar or slightly lower BP compared to matched nonsmokers,6, 7 studies of ambulatory BP monitoring show that long-term cigarette smoking increases average HR and BP throughout the day.8, 9 In addition, in animal studies, administration of nicotine has been shown to exacerbate existing cardiovascular diseases including chronic hypertension, atherosclerosis and myocardial infarction.10–13
Like systemic hypertension, cigarette smoking or nicotine inhalation has not been causally linked to the development of pulmonary hypertension (PH) due to the complex nature of the disease. Cigarette smoke exposure in animal studies has been shown to induce PH,14–17 however, the contribution of nicotine to the development of PH is not clear. In chronic cigarette smoke exposure-induced PH in rodents, the renin-angiotensin system (RAS) has been shown to be activated and treatment with angiotensin (Ang)-II type I receptor antagonist losartan attenuates cigarette smoke-induced pulmonary vascular remodeling and PH.14, 18 In addition, both cigarette smoke and nicotine have been shown to induce proliferation of cultured pulmonary artery smooth muscle cells via connective tissue growth factor-cyclin D1 pathway.19
The current study aims to examine the effects of chronic nicotine inhalation on the cardiopulmonary system with an emphasis on both systemic and pulmonary BP and cardiac remodeling, using a murine chronic nicotine inhalation model.
METHODS
The authors declare that all supporting data are available within the article [and its online supplementary files].
Animals
Experiments were performed in adult C57BL6/J mice (males, 8–12 weeks old) purchased from the Jackson Laboratory (Bar Harbor, ME). Mice were housed in a temperature- and humidity-controlled facility under a 12-h dark/light cycle, fed standard mouse chow (iOS Teklab Extruded Rodent Diet 2019S; Envigo, Huntingdon, UK) and water ad libitum. Care included a pre-operative injection of Buprenorphine-SR (1 mg/kg s.c.; ZooPharm, Windsor, CO) for pain relief and Penicillin G Procaine (60–100 UI/g i.m.; Blue Springs, MO, USA) as antibiotic. All procedures conformed to the National Institutes of Health Guide for the Care and Use of Laboratory Animals and were approved by the Louisiana State University Health Sciences Center Institutional Animal Care and Use Committee (protocol #3390).
Chronic Nicotine Inhalation Model
Mice in the nicotine group were housed in a nicotine inhalation chamber (La Jolla Alcohol Research, La Jolla, CA). Nicotine vapor was produced by bubbling air at a flow rate of 3 L/min through a gas-washing bottle containing a solution of pure nicotine (free base; Sigma Aldrich, St. Louis, MO). The highly concentrated nicotine vapor was then passed through a drop-catch bottle and diluted by the addition of 60 L/min of clean air in a 2 L Erlenmeyer vacuum flask at room temperature. The final nicotine-air mixture was homogeneously distributed to each chamber at a flow rate of 7–8 L/min/chamber. Nicotine vapor concentration was adjusted by varying the flow rate at which nicotine was bubbled to achieve plasma cotinine levels that resembled levels observed in human smokers. Mice were exposed to nicotine on a 12 h on/12 h off schedule with the nicotine exposure (9:00 PM-9:00 AM) overlapping with the dark cycle (6:00 PM-6:00 AM). Blood cotinine level (a more stable metabolite of nicotine) was monitored weekly. For this purpose, blood was obtained by submandibular vein puncture within 1 h following the end of nicotine exposure and serum cotinine levels were determined by enzyme-linked immunosorbent assay (ELISA; Calbiotech, El Cajon, CA). Mice in the air-exposed group were housed in the same room outside the chamber.
Radio-Telemetry Implantation and BP Measurement
Before surgery, mice were anesthetized with isoflurane (2%) in an oxygen flow (1 L/min) and placed on a heating pad to maintain body temperature around 37.5°C. Mice were implanted with telemetry probes (PA-C10 or HD-X10; DSI, St Paul, MN) for conscious BP monitoring, as previously.20, 21 Following recovery, at least one week, BP was recorded weekly for 24 h in all groups. Data were analyzed by calculating the areas above and below the systolic and diastolic BP traces (Prism 8, GraphPad software, CA) for each animal to determine hypertensive and normotensive zones. The thresholds were set at 130 mmHg for systolic BP and 90 mmHg for diastolic BP.
Ang-II infusion
A subset of air-exposed mice was subjected to Ang-II (Sigma-Aldrich) or vehicle (0.9% saline) infusion via subcutaneous osmotic mini-pumps (Alzet Model 1004; Durect Corporation, Minneapolis, MN) at the dose of 450 ng/kg/min for the duration of 4 weeks.
Echocardiography
Echocardiography was performed at baseline and at 4- and 8-week time points using VisualSonics Vevo 3100 Imaging System with a 30-MHz probe (VisualSonics, Toronto, Canada). Mice were anesthetized with 1–1.5% isoflurane on a heated pad to maintain body temperature, and measurements were taken at HR between 450–550 beats per min. B-mode images were used to obtain short-axis (mid-left ventricular) and long-axis views, and then M-mode recordings were collected using a two-dimensional reference sector for right ventricular (RV) and left ventricular (LV) dimensions. Ultrasound M-mode image processing was performed using the leading-edge method with VisualSonics software. All measurements were performed on a minimum of three cardiac cycles, and group averages were calculated for each time point. For LV measurement, data from two cohorts were combined (n=22–23 per group); however, RV measurements were performed only on the second cohort (n=8–9 per group).
RV Pressure Measurement and Pulmonary Vascular Resistance (PVR)
Right heart catheterization was performed at the end of the 8-week exposure. Mice were placed on a heated pad and anesthetized with 2% isoflurane. After dissection, a pressure transducer (SPR-1000; Millar, Houston, TX) was inserted into the RV through the right jugular vein. RV pressure was recorded and analyzed by the PowerLab 8/35 acquisition system (ADInstuments, Colorado Springs, CO). PVR was calculated based on the following formula: PVR = ΔP/Flow = (RVSP-LVEDP)/CO, where RVSP was RV systolic pressure, LVEDP was left ventricular end diastolic pressure (which assumed equal to left atrial pressure), and CO was cardiac output. LVEDP was determined by direct pressure measurement using a pressure transducer (SPR-1000) inserted into the left ventricle from the right common carotid artery, whereas CO was estimated by echocardiography (stroke volume × HR).
Tissue Harvest, Fixation and Processing
At the end of the 8-week exposure, mice were euthanized by decapitation followed by blood collection. Heart and lung tissues were collected from a subset of mice (8–9/group) and snap frozen in liquid nitrogen for further analysis. For the heart, RV was separated from LV and intraventricular septum and individually weighed. To examine histological changes in the heart, another subset of mice (n=3/group) was subjected to transcardial perfusion fixation with 4% paraformaldehyde. For lung histology, another subset of mice (n=7/group) was perfused with Z-Fix (Anatech, Battle Creek, MI) through a tracheal cannula at a pressure of 25 cm of H2O for 10 min followed by immersion fixation in Z-Fix for at least 24 h before processing for paraffin embedding and sectioning.
ELISA
ELISA was performed to determine serum levels of cotinine (Calbiotech), plasma and RV levels of brain or B-type natriuretic peptide (BNP; Raybiotech, Peachtree Corners, GA) per manufacturers’ instructions.
Western Blotting
Total proteins were extracted using RIPA buffer containing protease and phosphatase inhibitors (Cell Signaling, Danvers, MA) and quantified using the bicinchoninic acid method (Pierce Biotechnology, Waltham, MA). Equal amounts of proteins were analyzed by Western blotting as described.22 Antibodies against angiotensin-converting enzyme (ACE; AF1513, R&D systems, Minneapolis, MN), total and phosphorylated extracellular signal-regulated kinase (ERK; #4370 and #4695, Cell signaling), p38 (#8690 and #4511, Cell Signaling), c-Jun N-terminal kinase (JNK; #9252 and #4668, Cell Signaling), collagen I (#34710, Abcam, Cambridge, MA) and GAPDH (#5174, Cell signaling) were used. The primary antibodies were used at 1:1,000 dilutions and HRP-conjugated secondary antibodies (Cell Signaling) were used at 1:20,000 dilutions. Densitometry measurements were performed using NIH ImageJ.
Immunohistochemistry
Paraffin-embedded lung tissue sections were deparaffinized and rehydrated. Heat-induced antigen retrieval was achieved by using a pressure cooker at 98–100°C for 15 min in 300 mM NaCl, 30 mM sodium citrate, pH 6.0, followed by cooling at room temperature for 30 min. Histostain-Plus Kit with diaminobenzidine as the substrate (Invitrogen, Carlsbad, CA) was used for detection of α-smooth muscle actin (SMA) using a mouse monoclonal antibody (Sigma Aldrich). Non-immune mouse IgG (0.5 μg/mL; Invitrogen) was used as the control. Sections were counterstained with hematoxylin.
Statistics
Data were expressed as mean±SEM and analyzed by Student’s t-test, one-way ANOVA followed by Tukey’s post-hoc test for multiple comparisons between means, Kruskal-Wallis test, two-way ANOVA followed by Bonferroni’s post-hoc test for multiple comparisons between means, when appropriate, using GraphPad Prism 8 (GraphPad Software, San Diego, CA). P<0.05 was considered statistically significant.
RESULTS
Chronic Nicotine Inhalation Model
To examine the effects of chronic nicotine inhalation on the development of CVPD, we exposed C57BL6/J mice (male, 8–12 weeks of age) to air (control) or nicotine vapor (daily, 12 h on/12 h off) for 8 weeks. Nicotine exposure was assessed by weekly measurement of serum cotinine levels, which showed a weekly average of 613.5±38.5 ng/mL in nicotine-exposed mice (Figure 1). The weekly serum cotinine levels did not vary significantly during the course of the study, indicating that nicotine metabolism in these mice did not change during the 8-week exposure period. As a reference, an average cigarette contains 0.8–1.9 mg nicotine and delivers roughly 10–30 μg/kg of body weight, typically resulting in 10–50 ng/mL peak plasma nicotine levels in humans.23 Due to the much shorter half-life of nicotine in mice compared to humans (6–7 min in mice compared to 2 h in humans),23 serum cotinine level (a more stable metabolite of nicotine) is generally used to measure nicotine exposure in mice. With chronic nicotine exposure, it has been shown that plasma cotinine levels can be many times (15 times or more) higher than plasma nicotine.23 Thus, the serum cotinine levels in our nicotine-exposed mice were within the range seen in human smokers.
Figure 1.
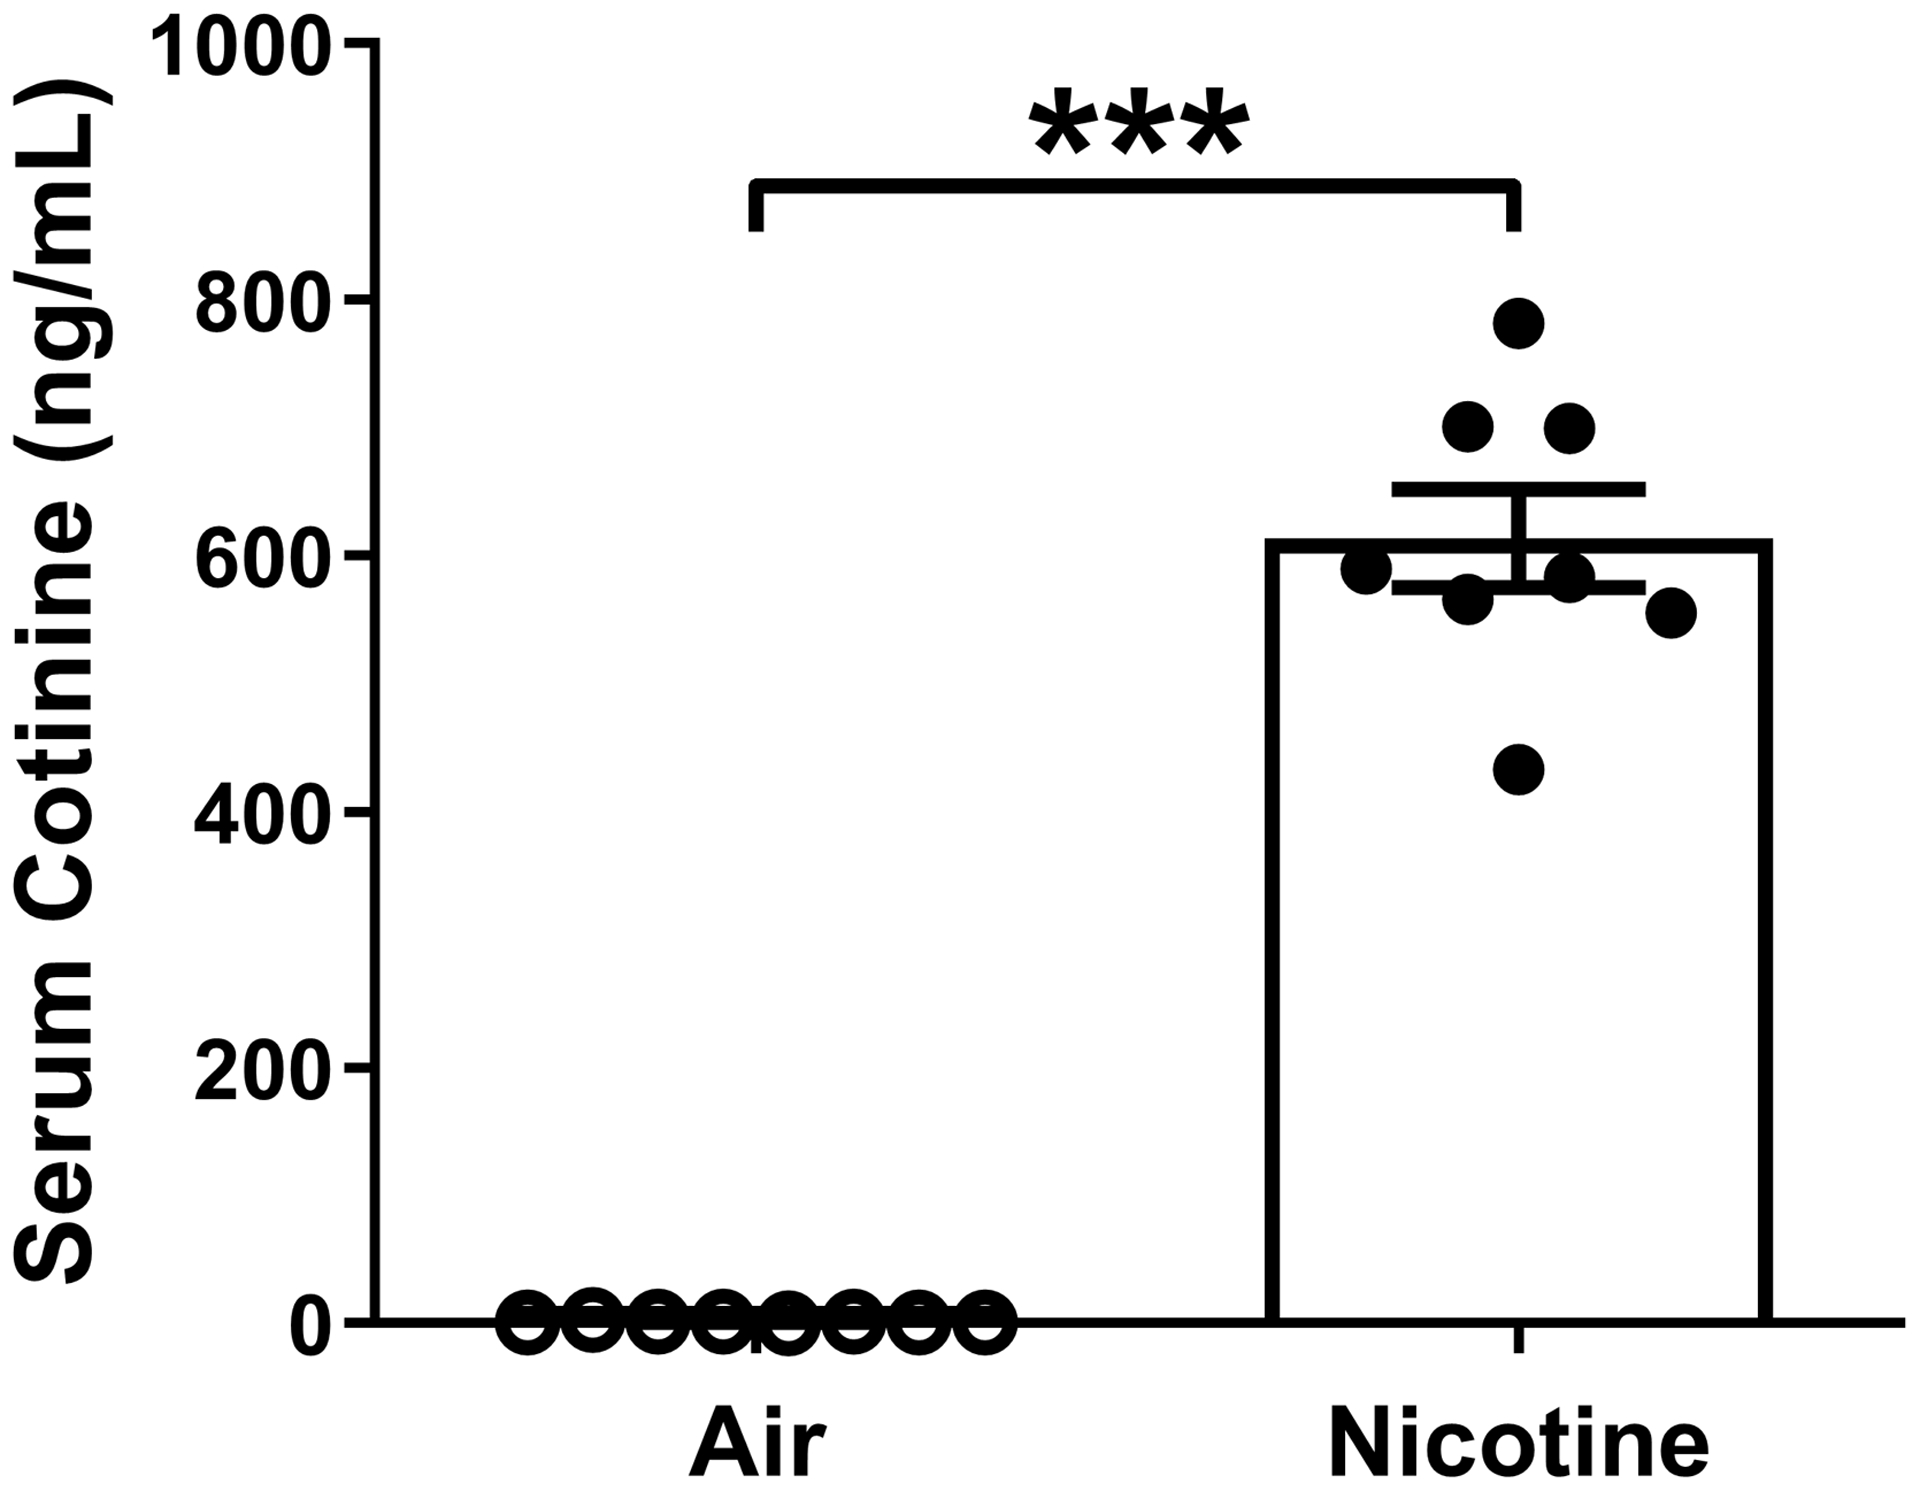
Serum cotinine levels in air- and nicotine-exposed mice. Weekly averages from air- or nicotine-exposed mice (5–6/group) during the 8-week exposure period (n=8) were shown. ***P < 0.001, nicotine vs. air control group (unpaired student t-test).
Chronic Nicotine Inhalation Leads to Systemic Hypertension
To assess the impact of chronic nicotine inhalation, BP was recorded weekly for 24 h. Systolic (Figure 2) and diastolic (Figure S1) BP were significantly elevated (2 way ANOVA, P<0.05) as early as 1 week after nicotine exposure in both dark (6:00 PM to 6:00 AM) and light (6:00 AM to 6:00 PM) phases, with a maximal effect after 2 weeks and a normalization by 4 weeks. In order to better identify specific periods during which BP was elevated, we introduced a new methodology based on the calculation of areas below and above a specific threshold. To validate this approach, Ang-II infusion was used as a positive control for hypertension. For systolic BP, calculation of the areas between the BP trace and the 130 mmHg threshold led to the identification of a normotensive zone (below threshold) and a hypertensive zone (above threshold). Nicotine inhalation resulted in a significant reduction of the normotensive zone and a significant increase in the hypertensive zone (Figure 2) from weeks 1 to 3. Ang-II infusion showed a similar pattern, albeit more pronounced, thus validating our approach. Diastolic BP (Figure S1) presented the same profile. The increase in BP in nicotine-exposed mice in the first week of exposure was associated with a significant reduction of systolic BP dipping (ΔBP) between the active and inactive phases (air-exposed: 16.5 mmHg vs. nicotine-exposed: 8.5 mmHg, P<0.05), a well-known risk factor for cardiovascular, cerebrovascular and kidney diseases, as well as end-organ damage.24, 25 BP was not significantly different between the air- and nicotine-exposed groups from weeks 5 to 8 (Figure S2). HR (Figure S3) was not significantly different between the groups in weeks 1–3, but a pronounced bradycardia (P<0.001) was observed in the nicotine-exposed mice after the BP had returned to a normotensive level in week 4. Changes in these hemodynamic parameters appeared independent of behavioral activity (Figure S4), which was not altered by nicotine or Ang-II infusion.
Figure 2.
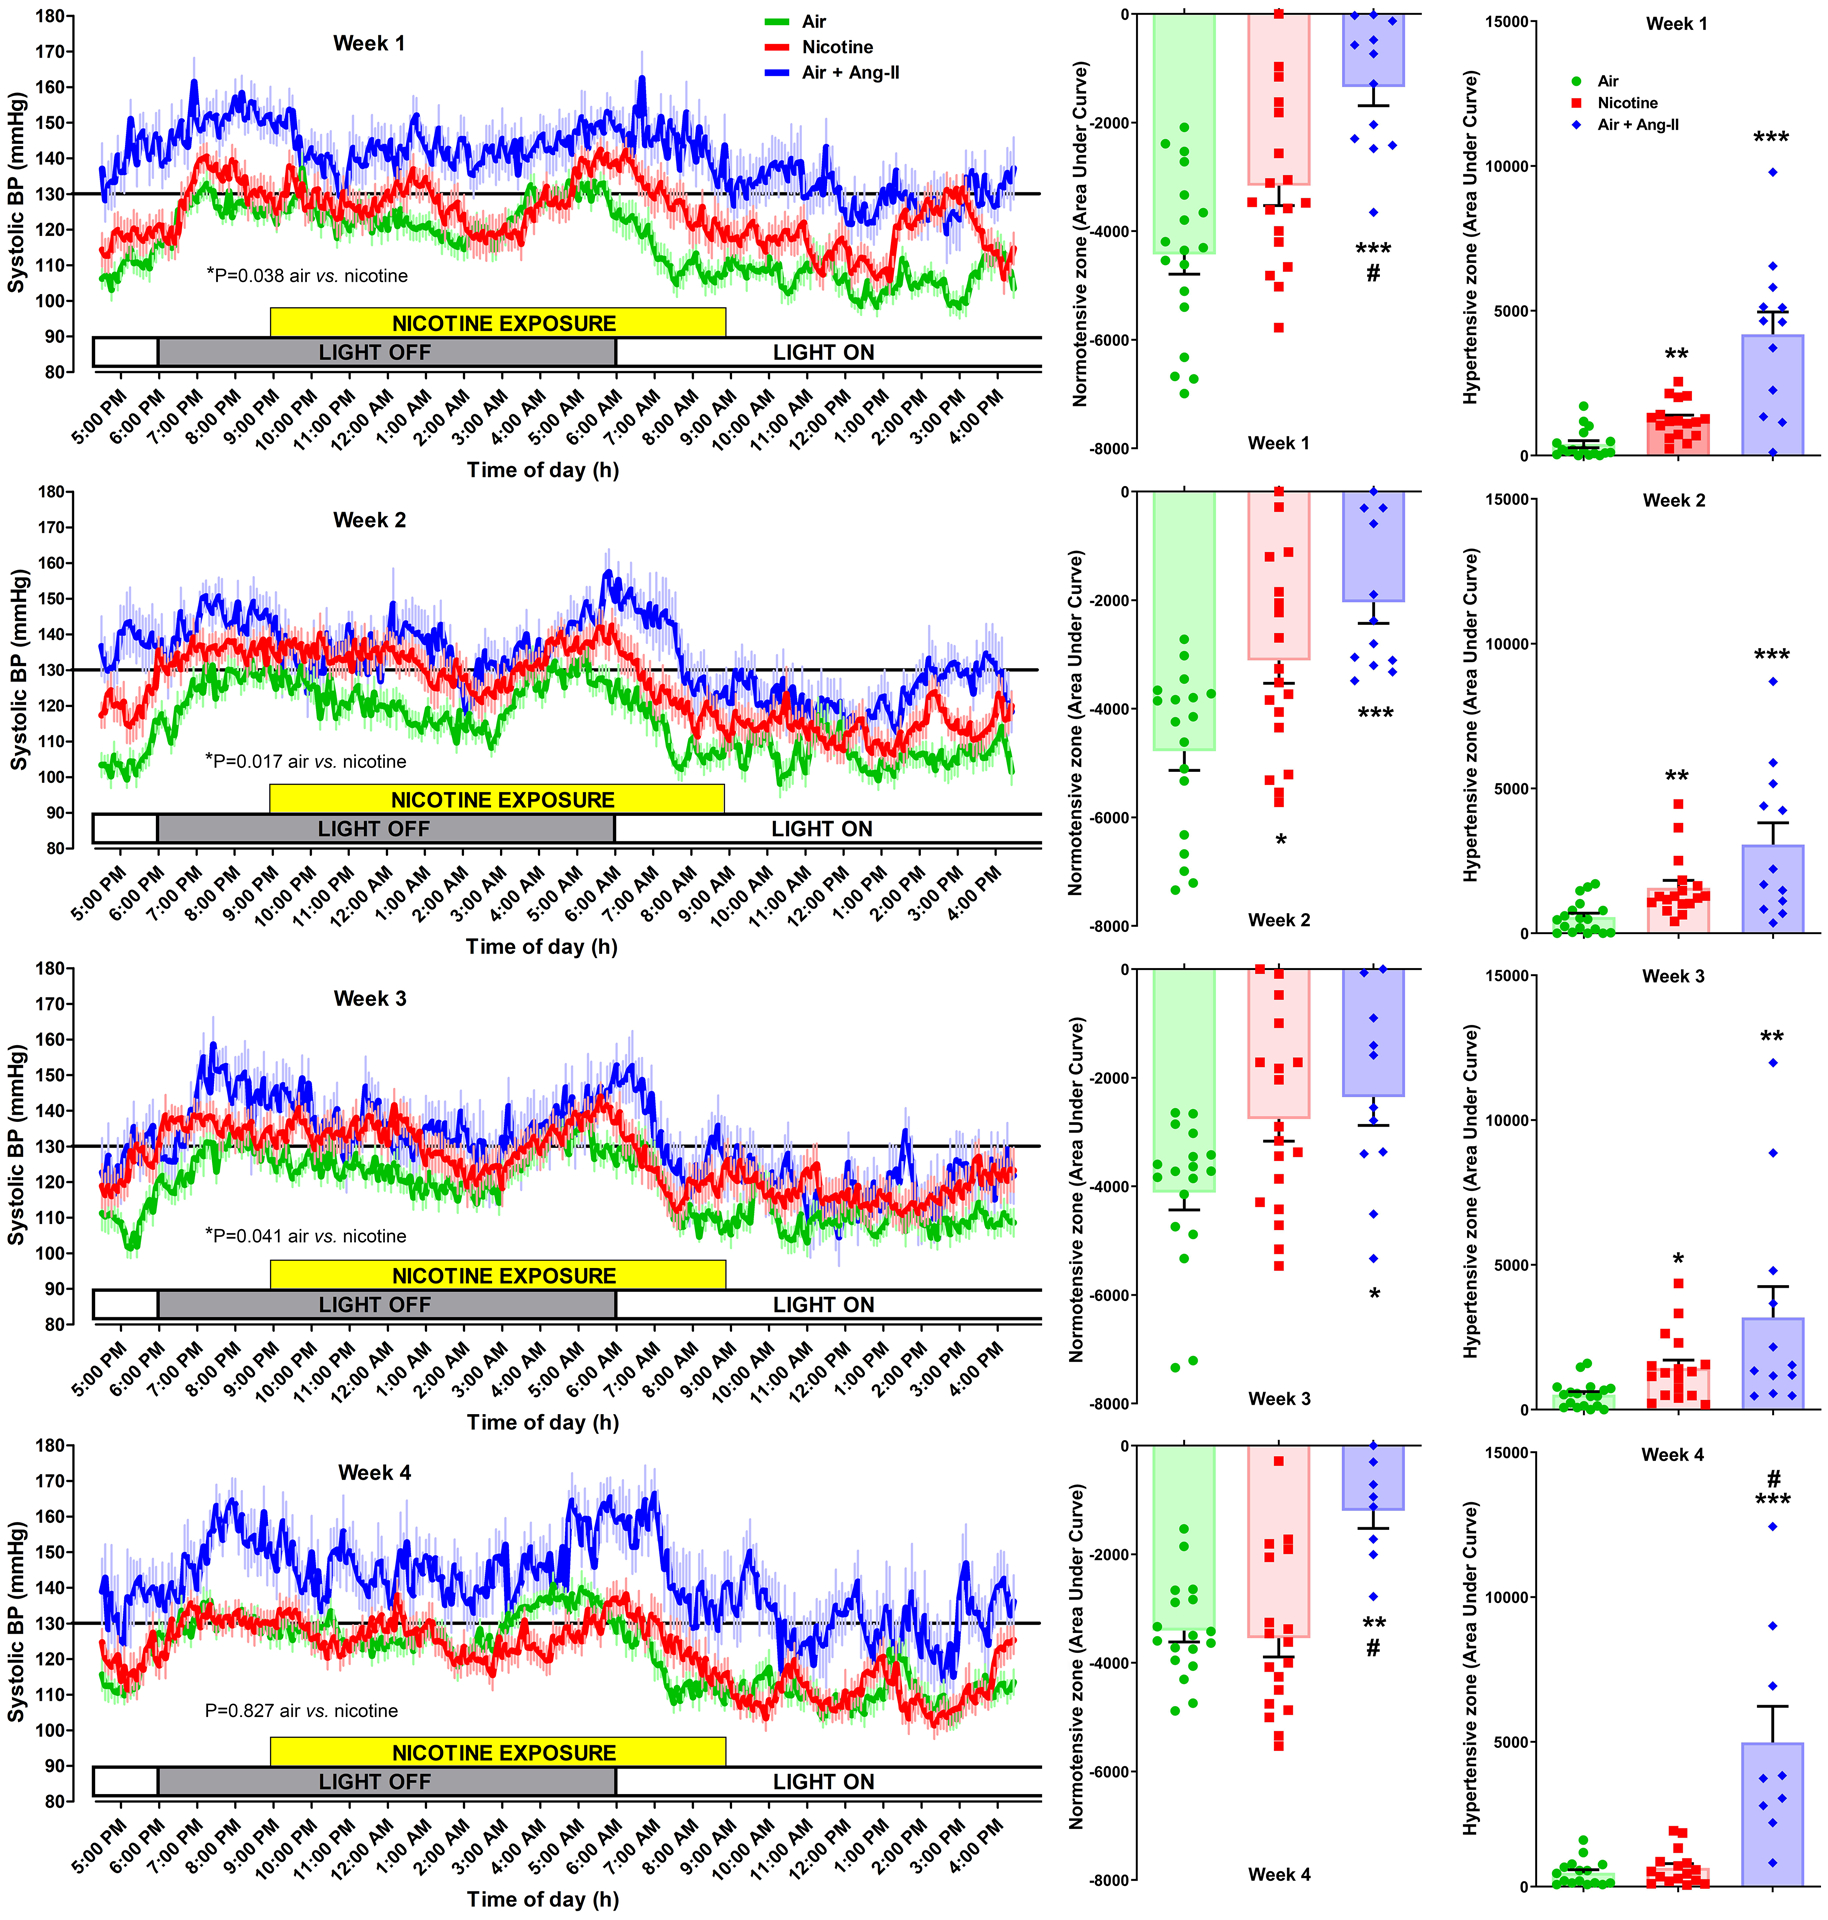
Chronic nicotine inhalation leads to early increase in systolic blood pressure (BP). Weekly average 24 h recording of systolic BP in mice exposed to air (green, n=18) or nicotine (red, n=18). Some mice were infused with angiotensin-II (450 ng/kg/min) as a hypertensive positive control (blue, n=9–12). Results of the two-way ANOVA between air-and nicotine-exposed mice are indicated below the traces. Area under the curve was calculated for the BP traces below and above the 130 mmHg threshold to identify normotensive and hypertensive zones, respectively, as defined in the Methods section. Statistical significance: *P<0.05, **P<0.01, ***P<0.001 vs. air control group and #P<0.05 vs. nicotine-exposed mice (Kruskal-Wallis test followed by Dunn’s multiple comparison test).
Chronic Nicotine Inhalation Leads to PH
At the end of the 8 weeks, mice were subjected to right heart catheterization to measure RVSP as an index of pulmonary artery systolic pressure. As shown in Figure 3 A–B, nicotine-exposed mice exhibited significantly increased RVSP (39.3±2.9 mmHg, n=10) compared to air-exposed controls (23.3±1.3 mmHg, n=11, P<0.001), and the effect of nicotine was as potent as Ang-II infusion (38.0±2.2 mmHg, n=7, P<0.001 vs. air-exposed controls). In some nicotine-exposed mice, RV diastolic pressure (RVDP) was also increased compared to air-exposed controls (Figure 3A, lower graph), however, this was not a consistent finding. It is important to note that the RV pressures were collected under isoflurane anesthesia, so the values in conscious mice were likely even higher. The increased RVSP by nicotine was accompanied by enhanced expression of BNP in RV protein extracts (44.1±1.9 pg/mg, n=7) compared to the air-exposed controls (37.5±1.6 pg/mg, n=8, P<0.05, Figure 3C). BNP is released primarily from the heart (particularly the ventricles) due to myocardial strain and is among the first biomarkers identified in patients with PH.26 The increased RV BNP expression is consistent with increased RVSP induced by chronic nicotine inhalation. Plasma BNP levels in nicotine-exposed mice, however, were not significantly different from the levels in air-exposed controls (not shown), which was not entirely surprising as nicotine-exposed mice did not suffer overt heart failure (as shown by echocardiography below). In addition, nicotine-exposed mice exhibited significantly increased Fulton index and PVR (Figure 3D–E).
Figure 3.
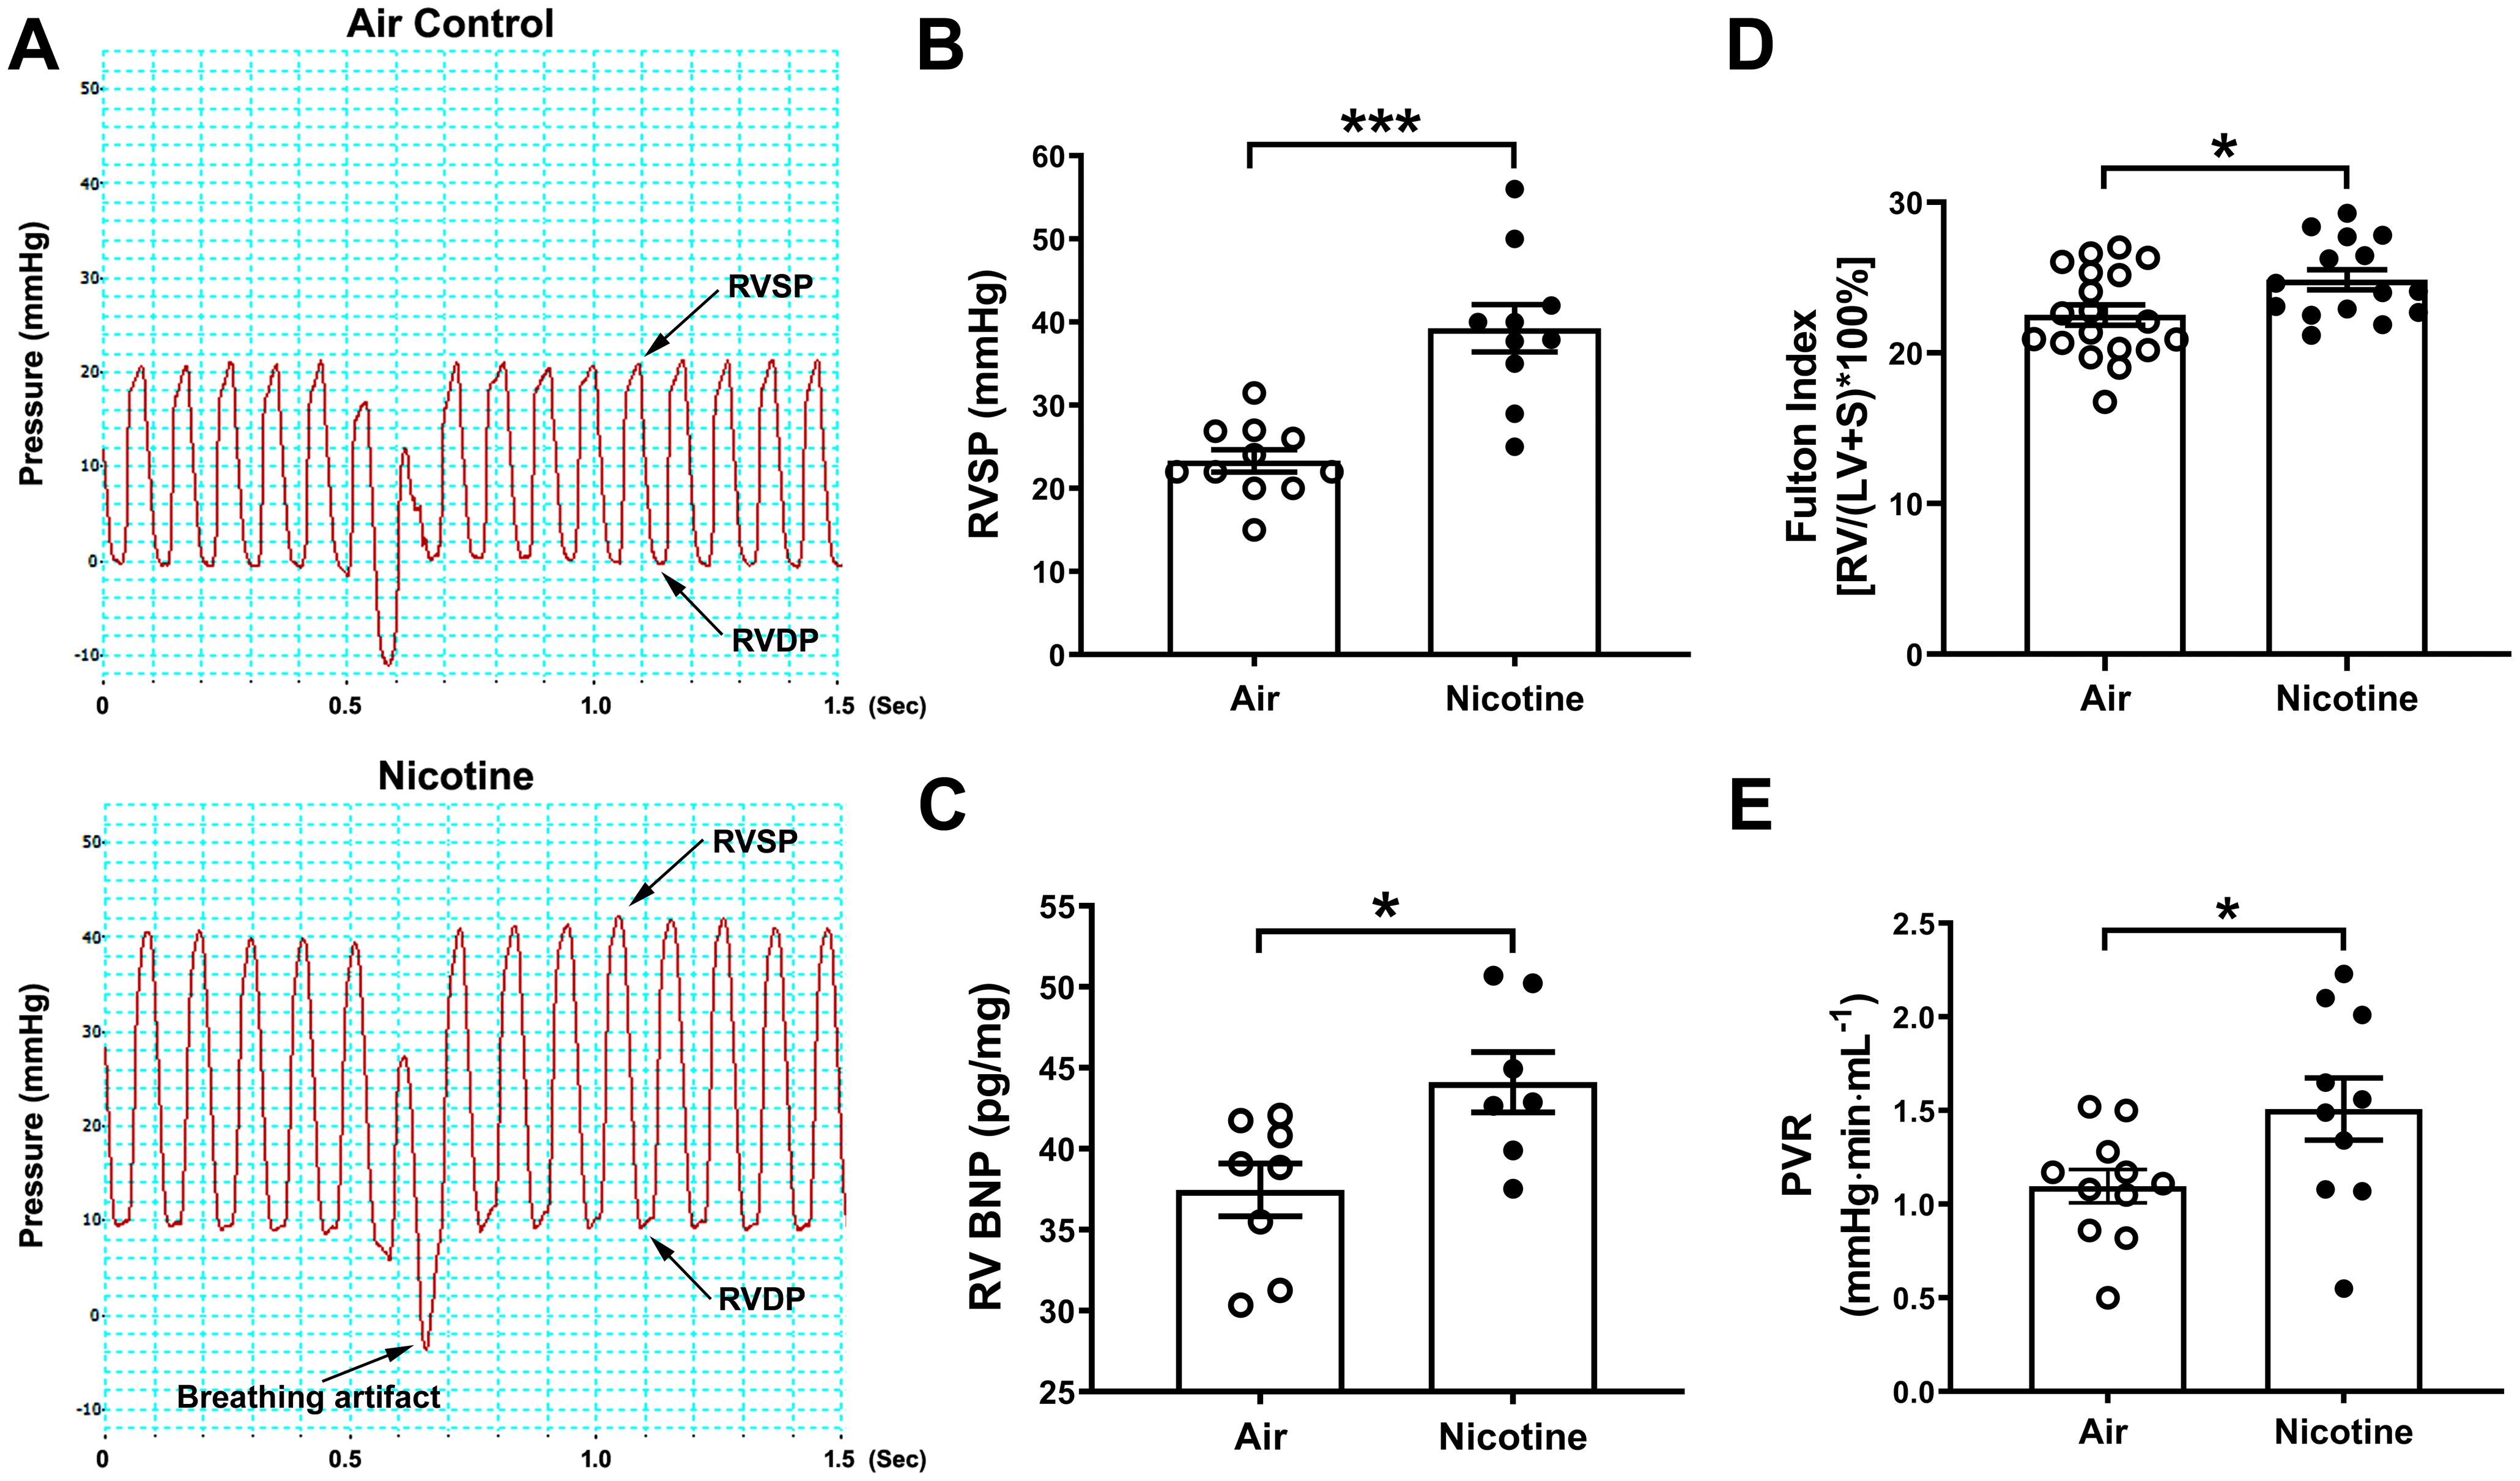
Chronic nicotine inhalation leads to the development of pulmonary hypertension. (A) Representative right ventricular (RV) pressure tracing from air- (upper) and nicotine- (lower) exposed mice. RVSP, RV systolic pressure; RVDP, RV diastolic pressure. (B) Quantification of RVSP. (C) Expression of brain or B-type natriuretic peptide (BNP) in RV protein extracts measured by ELISA. (D) Fulton Index. S, interventricular septum. (E) Pulmonary vascular resistance (PVR). *P<0.05, ***P<0.001, nicotine vs. air control group (unpaired student t-test).
Chronic Nicotine Inhalation Leads to RV, but not LV, Remodeling
RV failure is the cause of mortality in PH and is often associated with maladaptive RV remodeling.27 Echocardiography was employed to study structural and functional changes in the heart following chronic nicotine inhalation. As shown in Figure 4A, 8-week exposure to nicotine led to RV hypertrophy with increased RV free wall thickness (FWT) at diastole (RV FWT;d, 0.50±0.02 mm in nicotine-exposed compared to 0.42±0.03 mm in air-exposed mice, P<0.05) consistent with increased Fulton index (Figure 3D), and a trend of increase in RV internal diameter at diastole (RVID;d, 1.92±0.21 mm in nicotine-exposed compared to 1.45±0.08 mm in air-exposed mice, P=0.069). Representative echocardiographic images are shown in Figure S5. In contrast, there were no significant structural or functional changes in the LV following nicotine exposure (Figure 4B), including LV posterior wall (LVPW) thickness at either diastole (d) or systole (s), LV chamber dimension, fractional shortening or ejection fraction. Echocardiography did not detect significant changes either in the RV or the LV at the 4-week nicotine exposure time point (not shown), indicating that prolonged nicotine exposure is required for the observed RV remodeling.
Figure 4.
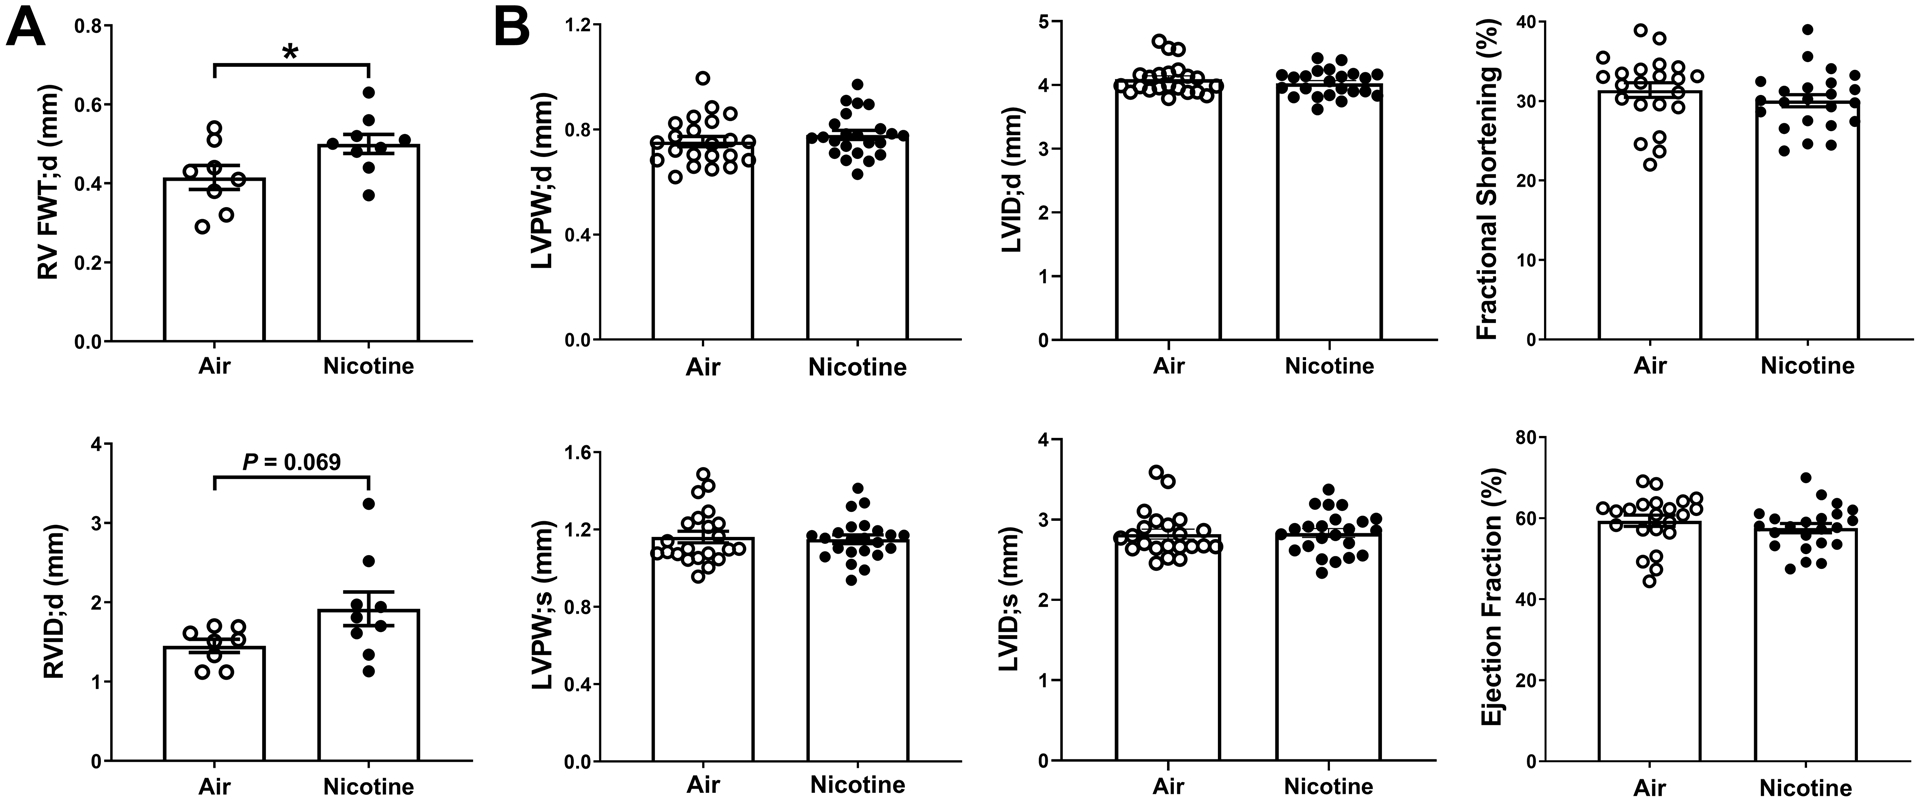
Chronic nicotine inhalation leads to RV, but not LV, remodeling as revealed by echocardiography. (A) RV measurements, including RV free wall thickness (FWT) and RV internal diameter (RVID) at diastole (d). Air, n=8; Nicotine, n=9. *P<0.05, nicotine vs. air control group (unpaired student t-test). (B) LV measurements, including LV posterior wall (LVPW) and LVID at both diastole (d) and systole (s), fractional shortening and ejection fraction. Air, n=22; Nicotine, n=23.
Chronic Nicotine Inhalation Leads to Pulmonary Vascular Remodeling
PH is often associated with pulmonary vascular remodeling.28 Accordingly, we performed immunohistochemistry using α-SMA specific antibody to label the smooth muscle layer in pulmonary arterioles. As shown in Figure 5, although we did not observe increased arterial wall thickness (arterioles associated with the bronchioles with internal diameters between 30 to 100 μm, Figure 5A), the number of muscularized (α-SMA positive, brown) pulmonary arterioles in the alveolar region (not associated with bronchioles) was increased in nicotine-exposed mice compared to air-exposed mice (Figure 5B–C). The above results suggest that chronic nicotine inhalation led to muscularization of previously non-muscular pulmonary arterioles, consistent with increased RVSP and PVR (Figure 3).
Figure 5.
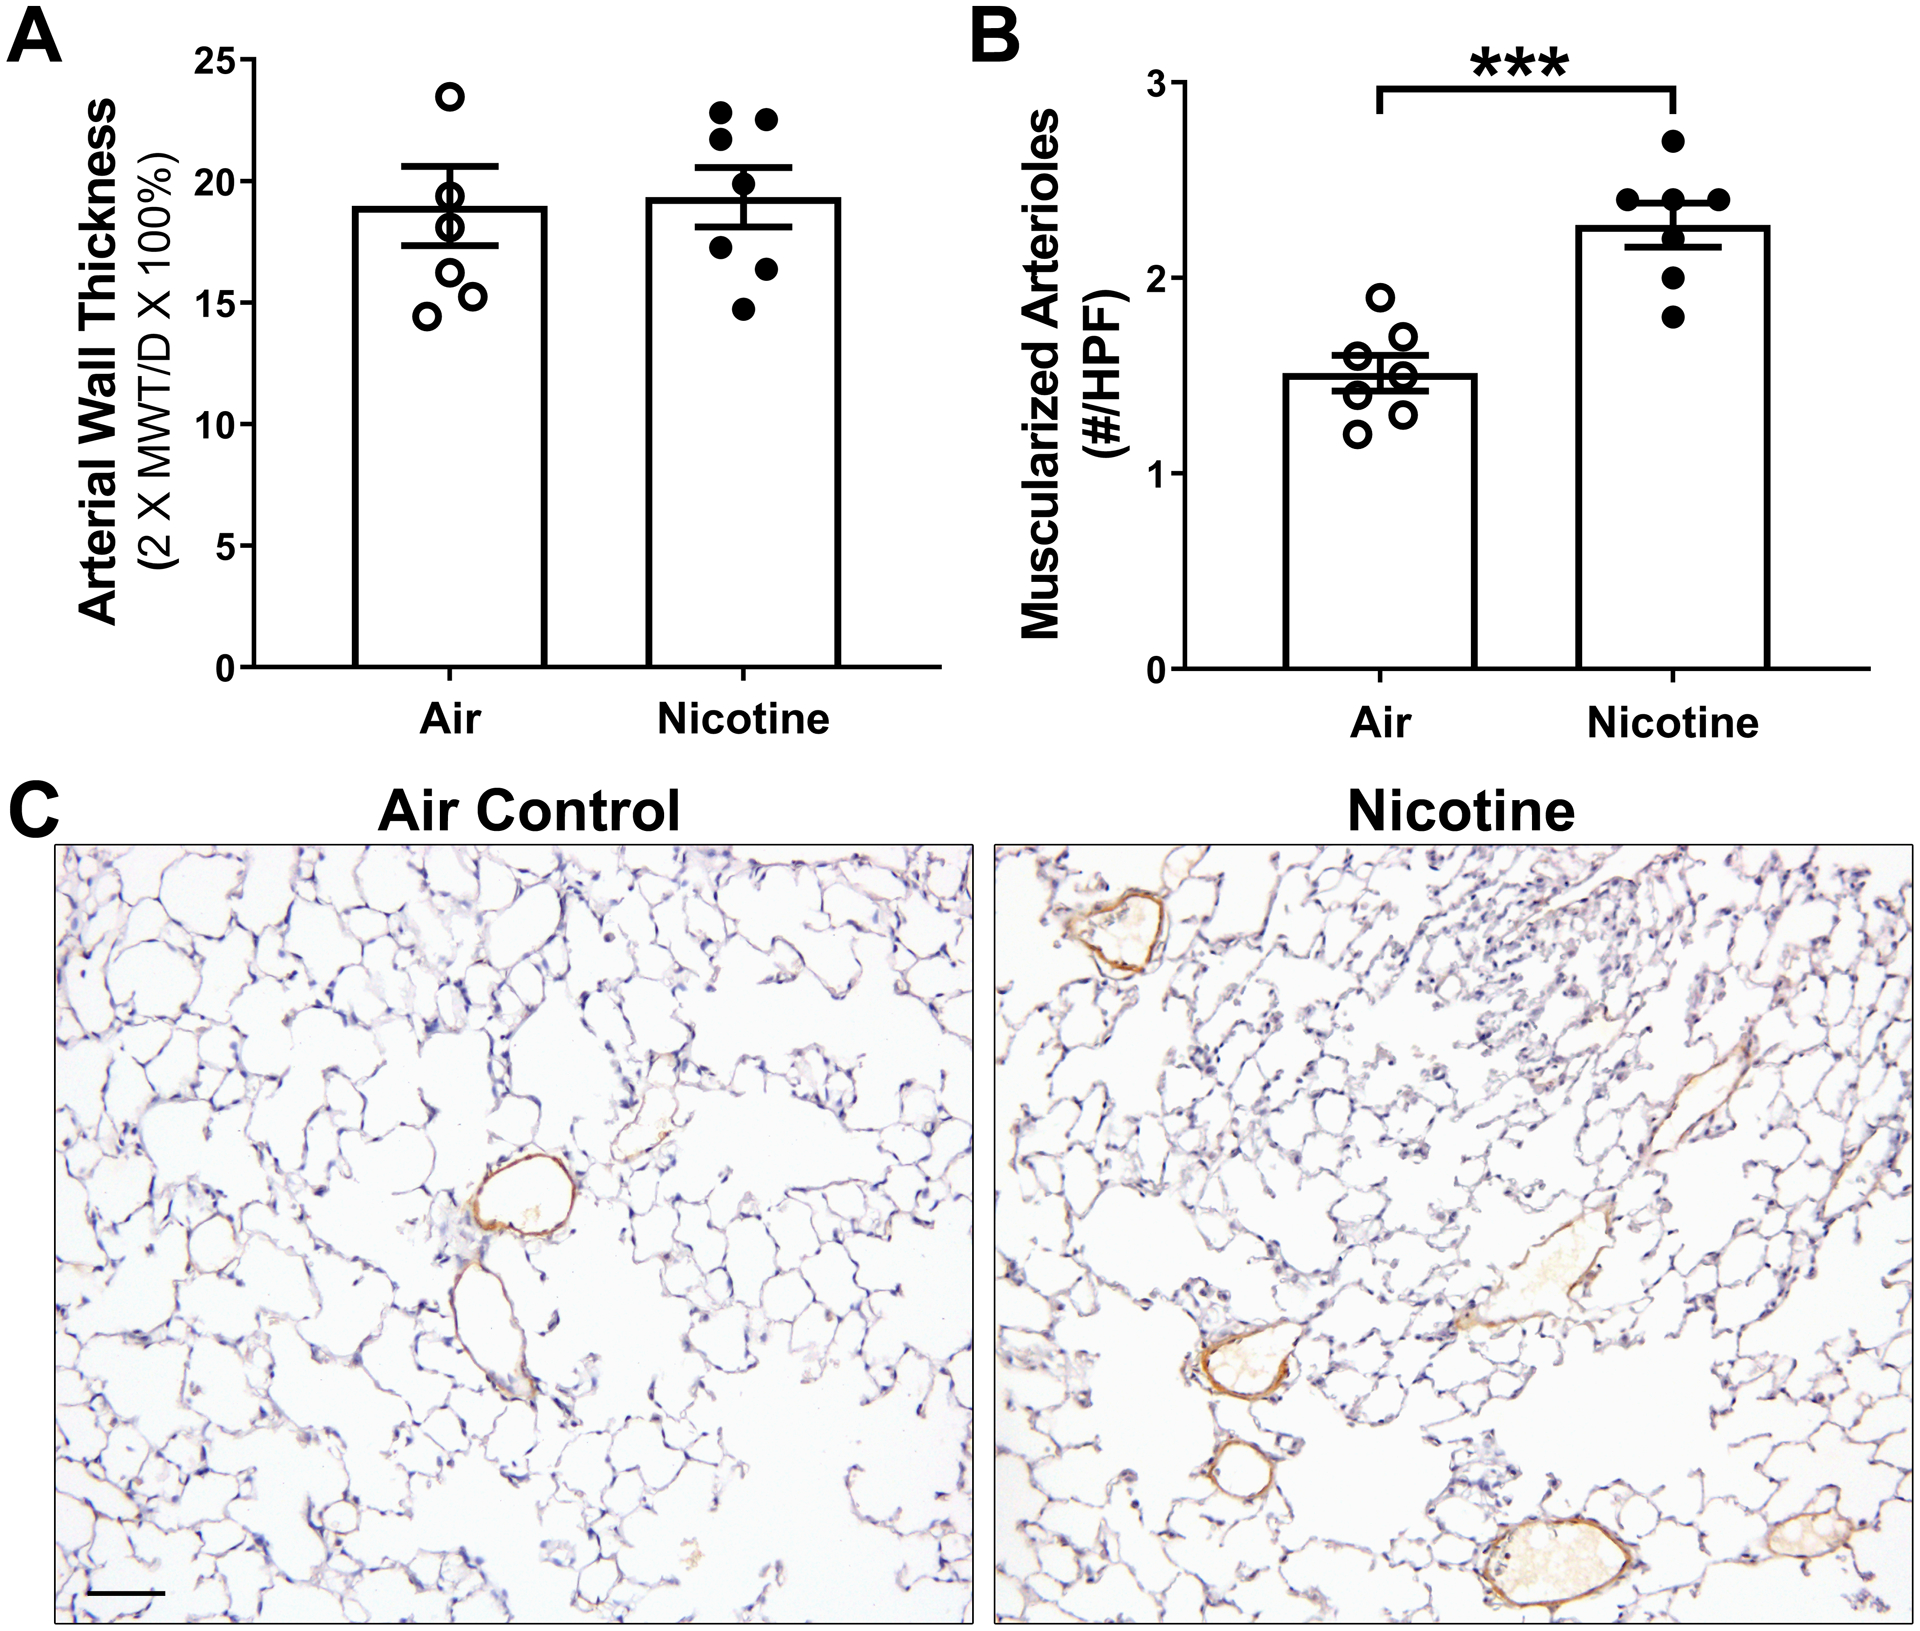
Chronic nicotine inhalation promotes pulmonary vascular remodeling. (A) Arterial wall thickness was measured as 2 × medial wall thickness (MWT)/external diameter (D) × 100%. Measurements were performed on lung tissue sections immunostained with α-SMA and all arterioles associated with the bronchioles with internal diameters between 30 to 100 μm were included. Air, n=7; nicotine, n=7. (B) Number of α-SMA positive, muscularized arterioles in the alveolar region in air- and nicotine-exposed mice per high power field (HPF). The average of 10 HPFs from each mouse was used. Air, n=7; nicotine, n=7. ***P<0.001, nicotine vs. air control group (unpaired student t-test). (C) Representative α-SMA immunostaining (brown) of lung sections from air- and nicotine-exposed mice. Scale bar, 50 μm.
Cigarette smoking is associated with the development of chronic obstructive pulmonary diseases (COPD) including emphysema and chronic bronchitis.29 However, we did not observe significant alteration in alveolar structure or inflammatory cell infiltration in the lung following the 8-week nicotine exposure (Figure S6 A–B). In addition, nicotine-exposed mice did not exhibit altered airway reactivity either at baseline or following challenge with methacholine (Figure S6 C).
Chronic Nicotine Inhalation Leads to ACE Overexpression and MAPK Activation in the RV
The differential response of RV vs. LV to nicotine is intriguing. We thus performed Western blotting to examine the potential signaling pathways activated by nicotine. As shown in Figure 6, nicotine exposure resulted in significant upregulation of ACE expression in the RV, which was accompanied by activation of the mitogen-activated protein kinases (MAPK) including ERK, p38 and JNK pathways. In contrast, we did not observe significant changes in ACE expression or MAPK activation in total protein extracts from the LV (except a non-significant increase in activated ERK, Figure 6B) or the lungs (not shown). It is interesting to note that mice with the highest ACE expression in the RV also had the greatest RV remodeling (hypertrophy and dilatation as revealed by echocardiography, Figure 6C). In addition, RV samples with the highest ACE expression exhibited increased protein levels of collagen I (precursor form at 170 kDa), however, as a group, collagen I expression in nicotine-exposed mice was not significantly different from that in air-exposed mice (Figure 6 A–B). Similarly, we did not find significant differences in collagen deposition by Masson’s trichrome staining on lung or heart tissue sections (Figure S7).
Figure 6.
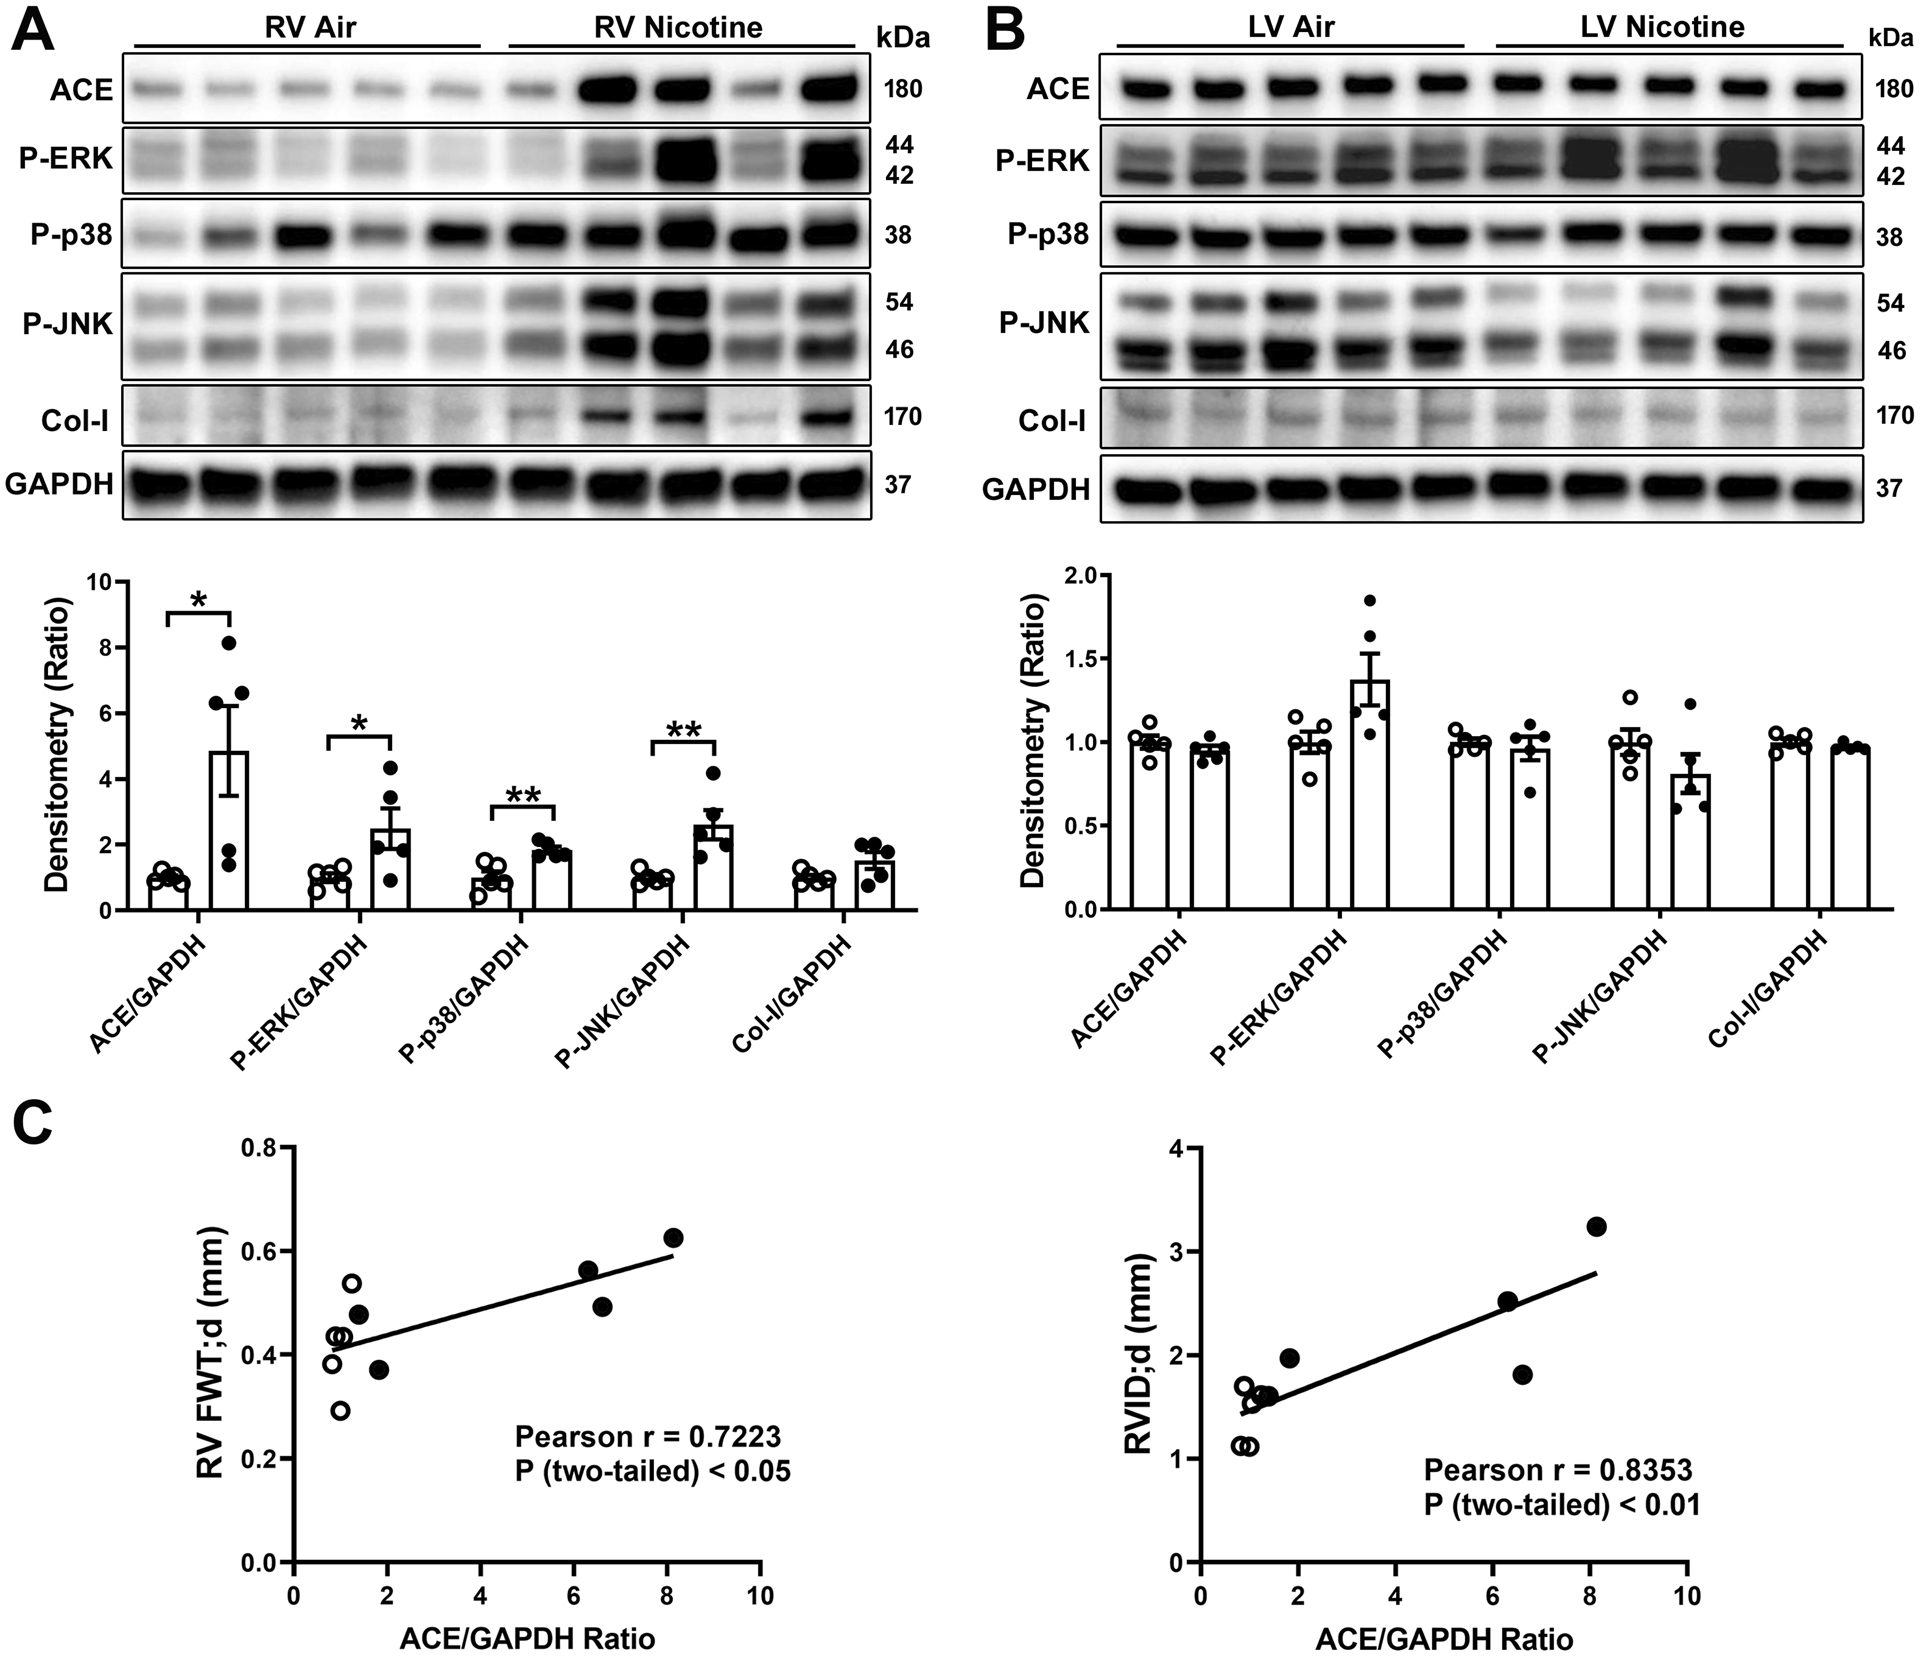
Chronic nicotine inhalation leads to ACE overexpression and MAPK activation in the RV, but not in the LV. (A) Representative Western blots of RV protein extracts and Western densitometry quantification. (B) Representative Western blots of LV protein extracts and Western densitometry quantification. Col-I, collagen I. Open circles, air; closed black circles, nicotine. *P<0.05, **P<0.01, nicotine vs. air control group (unpaired student t-test). Protein expression levels were normalized to the expression of GAPDH. For phosphorylated MAPKs, normalization to respective total MAPKs gave similar results (not shown). (C) Correlation between RV ACE expression and RV free wall thickness (FWT) and RV internal diameter (RVID) at diastole (d).
DISCUSSION
The current study examined the effects of chronic nicotine inhalation on the cardiopulmonary system with a focus on systemic and pulmonary BP and cardiac function. Our study, for the first time, shows that chronic inhalation exposure to nicotine alone in mice leads to PH with pulmonary vascular and RV remodeling. Although our study only detected a transient increase in systemic BP with nicotine inhalation, this increase was sufficiently long to pose potential health risks in individuals with pre-existing cardiopulmonary conditions.
As previously reviewed by us,30 human studies investigating the impact of inhaled nicotine on BP are limited with most studies examining BP changes immediately following cigarette smoke or nicotine inhalation session, while animal studies are often confounded by various doses and routes of administration. The murine nicotine inhalation model employed in this study closely mimics human smokers/e-cig users, in terms of route of nicotine exposure, dosage, and chronicity (over 8-week period in mice). Our finding that nicotine inhalation leads to elevated systolic and diastolic BP as early as the first week of exposure is consistent with the acute effects of nicotine on BP reported previously. These effects are physiological responses to nicotine-induced activation of nicotinic acetylcholine receptors (nAChR), leading to sympathetic neural activation and catecholamine release from the adrenal glands.31, 32 It is generally believed that these responses are short-term because of the rapid development of tolerance and the effect of nicotine on long-term BP control is controversial. The return of BP to normal level after 3 weeks in our study supports the development of tolerance to nicotine and/or activation of compensatory mechanisms of BP regulation. Whether these counter regulatory mechanisms will be able to maintain BP within the normal range with continued nicotine inhalation (beyond the period examined in the current study) is unknown. In addition, the BP increase within the first week of nicotine inhalation was associated with a lack of systolic BP dipping, which is considered a risk factor for cardiovascular diseases and end organ damage.24, 25 Considering that these changes were observed in healthy animals, it is likely that more dramatic effects could be observed in individuals with pre-existing cardiovascular conditions.
It is well-established that cigarette smoking promotes the occurrence of lung diseases (e.g. COPD) that lead to the development of PH.33 Similarly, cigarette smoking is a major risk factor for ischemic left-sided ventricular heart disease, leading to pulmonary venous hypertension.34 Whether cigarette smoking or nicotine itself promotes PH in the absence of these cardiopulmonary conditions was not clear. Our study suggests that nicotine exposure alone promotes the development of PH in the absence or prior to the occurrence of emphysematous or other structural changes commonly observed in COPD. The development of PH is often associated with pulmonary vascular remodeling with thickening of the smooth muscle layer of pulmonary arterioles and/or extension of new smooth muscle layer around the previously non-muscular precapillary arterioles.28 Although we did not observe increased arterial wall thickness, the number of muscularized pulmonary arterioles in the alveolar region was increased in nicotine-exposed mice compared to air controls, consistent with increased PVR and RVSP. Whether the above changes are due to increased smooth muscle cell proliferation or migration induced by nicotine requires further investigation. Our pilot experiments showed that aortas isolated from nicotine-exposed mice exhibited reduced endothelium-dependent vasodilatory response to acetylcholine compared to aortas isolated from the air control mice (unpublished data), suggesting that chronic nicotine exposure leads to systemic endothelial dysfunction. The contribution of pulmonary endothelial dysfunction and the consequent pulmonary vasoconstriction to the development of nicotine-induced PH requires further investigation.
The RAS has been shown to be involved in the development of both systemic hypertension and PH as well as cardiac remodeling.30, 35 In nicotine-exposed mice, we observed increased expression of ACE in the RV accompanied by the activation of MAPK signaling pathways including ERK, p38 and JNK, well-known signaling pathways downstream of ACE/Ang-II.36, 37 The heart has a complete local RAS and cardiac Ang-II formation appears to be regulated independently from the circulating RAS.38 ERK activation has been shown to mediate Ang-II-induced hypertrophic response in cardiomyocytes and is generally regarded as pro-survival and cardioprotective.36, 37, 39 In contrast, p38 and JNK, the so-called stress-activated MAPKs, are often associated with pathological cardiac remodeling and heart failure.39, 40 In contrast to a previous report that cigarette smoke exposure enhances ACE expression in the lung,14 we did not observe significant changes in lung ACE levels between air- and nicotine-exposed mice by Western blotting. It is possible that longer nicotine exposure (>8 weeks) is needed to alter ACE expression in the lung.
Our finding that chronic nicotine inhalation leads to RV, but not LV, remodeling is consistent with increased pulmonary BP but not systemic BP (even though a transient increase was observed at the early time points). The changes observed in the RV (structural, functional and signaling) following nicotine exposure are likely compensatory changes in response to increased PVR. However, there are intrinsic differences between RV and LV,41 and it is possible that nicotine induces specific responses in the RV independently of changes in pulmonary BP. The α7-nAChR is expressed in the heart and activation of this receptor has been shown to alter myocardial infarct size, hemodynamic and cardiac function in the setting of ischemia/reperfusion (I/R) injury.42 In addition, stimulation of α7-nAChR exerts anti-apoptotic, anti-oxidative stress, and anti-inflammatory effects following I/R.42
One limitation of this study is whether our model accurately reflects nicotine exposure in human smokers or e-cig users. Although the serum cotinine levels in our nicotine-exposed mice were within the range seen in human smokers (Results), our mice were exposed to nicotine continuously for 12 h per day instead of the intermittent exposure most likely experienced by human smokers or e-cig users. Another unanswered question is whether smokers who undergo nicotine replacement therapy in the attempt to quit smoking (with the target plasma nicotine levels usually below the levels of ad libitum smoking43) would face increased cardiopulmonary risks identified in the study. Future studies should examine the dose-dependent effects of nicotine.
The current study focuses on the cardiopulmonary effects of chronic nicotine inhalation, and our findings add to the expanding list of adverse health consequences of nicotine including nicotine-induced immunosuppression and carcinogenesis.44, 45 Genetic predisposition has been shown to play an important role in cigarette smoke-induced CVPD.46, 47 In tobacco-related cancers, there is growing evidence that the unique genetic makeup of an individual, such as polymorphisms in genes encoding nAChR subunits, influences the susceptibility of that individual to nicotine-induced carcinogenesis.45, 48 Although we used an inbred mouse strain (C57BL6/J) in our study, we observed significant individual differences in their responses to nicotine, e.g., individual differences in ACE expression and MAPK activation in the RV induced by nicotine (Figure 6). Identification of the factors that contribute to the increased susceptibility to nicotine-induced cardiopulmonary dysfunction should be another focus of future investigation.
PERSPECTIVES
With the increasing popularity of e-cig, newer generations of e-cig formulation and the general lack of knowledge of the harmful effects of nicotine, youth and young adults are exposed to potentially much higher concentrations of nicotine compared to conventional cigarette smokers and thus are at increased risk of nicotine-induced cardiopulmonary dysfunction.49, 50 The current study clearly demonstrates the adverse effects of nicotine on both systemic and pulmonary BP and cardiac remodeling. This study should help raise the awareness of the adverse effects of nicotine inhalation on the cardiopulmonary system, stimulate continued nicotine research, and help formulate public health policies on e-cig.
Supplementary Material
Novelty and significance:
What is new?
Our study demonstrates for the first time that chronic inhalation of nicotine alone leads to both systemic and pulmonary hypertension with pulmonary vascular and right ventricular remodeling. Interestingly, the adverse effects of inhaled nicotine are largely isolated to the right heart, as we found no significant changes in left heart remodeling or protein expression. In addition, our study shows activation of the cardiac renin-angiotensin system with chronic nicotine inhalation.
What is relevant?
There is a frightening trend of increasing usage of e-cig and vape products in youths and young adults. Recent high-profile cases of hospitalization and death following e-cig usage necessitate a greater understanding regarding the health impact of inhaled nicotine delivery systems. Our findings reveal significant adverse cardiopulmonary effects of chronically inhaled nicotine and shed light on potential mechanisms of nicotine-induced injury.
Summary
Our study shows that chronic nicotine inhalation in mice leads to both systemic and pulmonary hypertension with the latter accompanied by pulmonary vascular and right ventricular remodeling, and the activation of the renin-angiotensin system may contribute to nicotine-induced cardiopulmonary dysfunction.
Acknowledgements
The authors would like to thank Dr. Thomas Flanagan for his assistance with whole-body plethysmography and the Cardiovascular Function Core Facility in the Cardiovascular Center of Excellence at LSUHSC for its assistance with echocardiography.
Sources of Funding
This study was supported in part by research grants from the National Institute of Health (HL135635 to J.D. Gardner, E. Lazartigues and X. Yue and COBRE P30GM106392) and from Department of Veterans Affairs (BX004294 to E. Lazartigues).
Footnotes
Disclosures
None.
References
- 1.Jamal A, Phillips E, Gentzke AS, Homa DM, Babb SD, King BA, Neff LJ. Current cigarette smoking among adults - united states, 2016. MMWR Morb Mortal Wkly Rep. 2018;67:53–59 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 2.Wagoner KG, Cornacchione J, Wiseman KD, Teal R, Moracco KE, Sutfin EL. E-cigarettes, hookah pens and vapes: Adolescent and young adult perceptions of electronic nicotine delivery systems. Nicotine Tob Res. 2016;18:2006–2012 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.García Calzado MC, García Rojas JF, Mangas Rojas A, Millán J. Tobacco and arterial pressure (ii.). The acute effects on the angiotensin-converting enzyme. An Med Interna. 1990;7:392–395 [PubMed] [Google Scholar]
- 4.Groppelli A, Giorgi DM, Omboni S, Parati G, Mancia G. Persistent blood pressure increase induced by heavy smoking. Journal of hypertension. 1992;10:495–499 [DOI] [PubMed] [Google Scholar]
- 5.Cellina GU, Honour AJ, Littler WA. Direct arterial pressure, heart rate, and electrocardiogram during cigarette smoking in unrestricted patients. Am Heart J. 1975;89:18–25 [DOI] [PubMed] [Google Scholar]
- 6.Green MS, Jucha E, Luz Y. Blood pressure in smokers and nonsmokers: Epidemiologic findings. Am Heart J. 1986;111:932–940 [DOI] [PubMed] [Google Scholar]
- 7.Friedman GD, Klatsky AL, Siegelaub AB. Alcohol, tobacco, and hypertension. Hypertension. 1982;4:III143–150 [DOI] [PubMed] [Google Scholar]
- 8.Pickering TG, Schwartz JE, James GD. Ambulatory blood pressure monitoring for evaluating the relationships between lifestyle, hypertension and cardiovascular risk. Clin Exp Pharmacol Physiol. 1995;22:226–231 [DOI] [PubMed] [Google Scholar]
- 9.Palatini P, Pessina AC, Graniero GR, Canali C, Mormino P, Dorigatti F, Accurso V, Michieletto M, Ferrarese E, Vriz O, et al. The relationship between overweight, life style and casual and 24-hour pressures in a population of male subjects with mild hypertension. The results of the harvest study. G Ital Cardiol. 1995;25:977–989 [PubMed] [Google Scholar]
- 10.Bui LM, Keen CL, Dubick MA. Comparative effects of 6-week nicotine treatment on blood pressure and components of the antioxidant system in male spontaneously hypertensive (shr) and normotensive wistar kyoto (wky) rats. Toxicology. 1995;98:57–63 [DOI] [PubMed] [Google Scholar]
- 11.Lau PP, Li L, Merched AJ, Zhang AL, Ko KW, Chan L. Nicotine induces proinflammatory responses in macrophages and the aorta leading to acceleration of atherosclerosis in low-density lipoprotein receptor(−/−) mice. Arterioscler Thromb Vasc Biol. 2006;26:143–149 [DOI] [PubMed] [Google Scholar]
- 12.Sridharan MR, Flowers NC, Hand RC, Hand JW, Horan LG. Effect of various regimens of chronic and acute nicotine exposure on myocardial infarct size in the dog. Am J Cardiol. 1985;55:1407–1411 [DOI] [PubMed] [Google Scholar]
- 13.Zhou MS, Chadipiralla K, Mendez AJ, Jaimes EA, Silverstein RL, Webster K, Raij L. Nicotine potentiates proatherogenic effects of oxldl by stimulating and upregulating macrophage cd36 signaling. Am J Physiol Heart Circ Physiol. 2013;305:H563–574 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 14.Han SX, He GM, Wang T, Chen L, Ning YY, Luo F, An J, Yang T, Dong JJ, Liao ZL, Xu D, Wen FQ. Losartan attenuates chronic cigarette smoke exposure-induced pulmonary arterial hypertension in rats: Possible involvement of angiotensin-converting enzyme-2. Toxicol Appl Pharmacol. 2010;245:100–107 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 15.Weissmann N, Lobo B, Pichl A, Parajuli N, Seimetz M, Puig-Pey R, Ferrer E, Peinado VI, Dominguez-Fandos D, Fysikopoulos A, Stasch JP, Ghofrani HA, Coll-Bonfill N, Frey R, Schermuly RT, Garcia-Lucio J, Blanco I, Bednorz M, Tura-Ceide O, Tadele E, Brandes RP, Grimminger J, Klepetko W, Jaksch P, Rodriguez-Roisin R, Seeger W, Grimminger F, Barbera JA. Stimulation of soluble guanylate cyclase prevents cigarette smoke-induced pulmonary hypertension and emphysema. Am J Respir Crit Care Med. 2014;189:1359–1373 [DOI] [PubMed] [Google Scholar]
- 16.Wright JL, Tai H, Churg A. Vasoactive mediators and pulmonary hypertension after cigarette smoke exposure in the guinea pig. J Appl Physiol (1985). 2006;100:672–678 [DOI] [PubMed] [Google Scholar]
- 17.Wright JL, Churg A. Effect of long-term cigarette smoke exposure on pulmonary vascular structure and function in the guinea pig. Exp Lung Res. 1991;17:997–1009 [DOI] [PubMed] [Google Scholar]
- 18.Yuan YM, Luo L, Guo Z, Yang M, Ye RS, Luo C. Activation of renin-angiotensin-aldosterone system (raas) in the lung of smoking-induced pulmonary arterial hypertension (pah) rats. J Renin Angiotensin Aldosterone Syst. 2015;16:249–253 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 19.Wang R, Xu YJ, Liu XS, Zeng DX, Xiang M. Ccn2 promotes cigarette smoke-induced proliferation of rat pulmonary artery smooth muscle cells through upregulating cyclin d1 expression. J Cell Biochem. 2012;113:349–359 [DOI] [PubMed] [Google Scholar]
- 20.Xia H, Sriramula S, Chhabra K, Lazartigues E. Brain ace2 shedding contributes to the development of neurogenic hypertension. Circ Res. 2013;113:1087–1096 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 21.Xu J, Sriramula S, Xia H, Moreno-Walton L, Culicchia F, Domenig O, Poglitsch M, Lazartigues E. Clinical relevance and role of neuronal at1 receptors in adam17-mediated ace2 shedding in neurogenic hypertension. Circ Res. 2017;121:43–55 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 22.Lu J, Auduong L, White ES, Yue X. Up-regulation of heparan sulfate 6-o-sulfation in idiopathic pulmonary fibrosis. Am J Respir Cell Mol Biol. 2014;50:106–114 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 23.Matta SG, Balfour DJ, Benowitz NL, Boyd RT, Buccafusco JJ, Caggiula AR, Craig CR, Collins AC, Damaj MI, Donny EC, Gardiner PS, Grady SR, Heberlein U, Leonard SS, Levin ED, Lukas RJ, Markou A, Marks MJ, McCallum SE, Parameswaran N, Perkins KA, Picciotto MR, Quik M, Rose JE, Rothenfluh A, Schafer WR, Stolerman IP, Tyndale RF, Wehner JM, Zirger JM. Guidelines on nicotine dose selection for in vivo research. Psychopharmacology (Berl). 2007;190:269–319 [DOI] [PubMed] [Google Scholar]
- 24.Sarikaya S, Sahin S, Ozturk S, Akyol L, Altunkas F, Karaman K, Alcelik A, Keser Yilmaz Y. Detection of atrial electrical and mechanical dysfunction in non-dipper pre-hypertensive subjects. Clin Exp Hypertens. 2014;36:465–470 [DOI] [PubMed] [Google Scholar]
- 25.Gorostidi M, Sobrino J, Segura J, Sierra C, de la Sierra A, Hernandez del Rey R, Vinyoles E, Galceran JM, Lopez-Eady MD, Marin R, Banegas JR, Sarria A, Coca A, Ruilope LM, Spanish Society of Hypertension ARi. Ambulatory blood pressure monitoring in hypertensive patients with high cardiovascular risk: A cross-sectional analysis of a 20,000-patient database in spain. J Hypertens. 2007;25:977–984 [DOI] [PubMed] [Google Scholar]
- 26.Swaminathan AC, Dusek AC, McMahon TJ. Treatment-related biomarkers in pulmonary hypertension. Am J Respir Cell Mol Biol. 2015;52:663–673 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27.Lan NSH, Massam BD, Kulkarni SS, Lang CC. Pulmonary arterial hypertension: Pathophysiology and treatment. Diseases 2018;6. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 28.Tuder RM. Pulmonary vascular remodeling in pulmonary hypertension. Cell Tissue Res. 2017;367:643–649 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 29.Sethi JM, Rochester CL. Smoking and chronic obstructive pulmonary disease. Clin Chest Med. 2000;21:67–86, viii [DOI] [PubMed] [Google Scholar]
- 30.Oakes JM, Fuchs RM, Gardner JD, Lazartigues E, Yue X. Nicotine and the renin-angiotensin system. Am J Physiol Regul Integr Comp Physiol. 2018;315:R895–R906 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 31.Benowitz NL, Gourlay SG. Cardiovascular toxicity of nicotine: Implications for nicotine replacement therapy. J Am Coll Cardiol. 1997;29:1422–1431 [DOI] [PubMed] [Google Scholar]
- 32.Klevans LR, Gebber GL. Comparison of differential secretion of adrenal catecholamines by splanchnic nerve stimulation and cholinergic agents. J Pharmacol Exp Ther. 1970;172:69–76 [PubMed] [Google Scholar]
- 33.Zakynthinos E, Daniil Z, Papanikolaou J, Makris D. Pulmonary hypertension in copd: Pathophysiology and therapeutic targets. Curr Drug Targets. 2011;12:501–513 [DOI] [PubMed] [Google Scholar]
- 34.Lakier JB. Smoking and cardiovascular disease. Am J Med. 1992;93:8S–12S [DOI] [PubMed] [Google Scholar]
- 35.Maron BA, Leopold JA. The role of the renin-angiotensin-aldosterone system in the pathobiology of pulmonary arterial hypertension (2013 grover conference series). Pulm Circ. 2014;4:200–210 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 36.Forrester SJ, Booz GW, Sigmund CD, Coffman TM, Kawai T, Rizzo V, Scalia R, Eguchi S. Angiotensin ii signal transduction: An update on mechanisms of physiology and pathophysiology. Physiol Rev. 2018;98:1627–1738 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 37.Balakumar P, Jagadeesh G. A century old renin-angiotensin system still grows with endless possibilities: At1 receptor signaling cascades in cardiovascular physiopathology. Cell Signal. 2014;26:2147–2160 [DOI] [PubMed] [Google Scholar]
- 38.Wollert KC, Drexler H. The renin-angiotensin system and experimental heart failure. Cardiovasc Res. 1999;43:838–849 [DOI] [PubMed] [Google Scholar]
- 39.Rose BA, Force T, Wang Y. Mitogen-activated protein kinase signaling in the heart: Angels versus demons in a heart-breaking tale. Physiol Rev. 2010;90:1507–1546 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 40.Arabacilar P, Marber M. The case for inhibiting p38 mitogen-activated protein kinase in heart failure. Front Pharmacol. 2015;6:102. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 41.Friedberg MK, Redington AN. Right versus left ventricular failure: Differences, similarities, and interactions. Circulation. 2014;129:1033–1044 [DOI] [PubMed] [Google Scholar]
- 42.Intachai K CC S, Chattipakorn N, Shinlapawittayatorn K. Revisiting the cardioprotective effects of acetylcholine receptor activation against myocardial ischemia/reperfusion injury. Int J Mol Sci. 2018;19. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 43.Stead LF, Perera R, Bullen C, Mant D, Hartmann-Boyce J, Cahill K, Lancaster T. Nicotine replacement therapy for smoking cessation. Cochrane Database Syst Rev. 2012;11:CD000146 [DOI] [PubMed] [Google Scholar]
- 44.Hajiasgharzadeh K, Sadigh-Eteghad S, Mansoori B, Mokhtarzadeh A, Shanehbandi D, Doustvandi MA, Asadzadeh Z, Baradaran B. Alpha7 nicotinic acetylcholine receptors in lung inflammation and carcinogenesis: Friends or foes? J Cell Physiol. 2019. [Epub ahead of print] [DOI] [PubMed] [Google Scholar]
- 45.Grando SA. Connections of nicotine to cancer. Nat Rev Cancer. 2014;14:419–429 [DOI] [PubMed] [Google Scholar]
- 46.Armani C, Landini L, Leone A. Interactive effect of cigarette smoking and gene variants for predisposing to cardiovascular disease. Curr Pharm Des. 2010;16:2531–2538 [DOI] [PubMed] [Google Scholar]
- 47.Li Y, Cho MH, Zhou X. What do polymorphisms tell us about the mechanisms of copd? Clin Sci (Lond) 2017;131:2847–2863 [DOI] [PubMed] [Google Scholar]
- 48.Russo P, Cardinale A, Margaritora S, Cesario A. Nicotinic receptor and tobacco-related cancer. Life Sci. 2012;91:1087–1092 [DOI] [PubMed] [Google Scholar]
- 49.Fadus MC, Smith TT, Squeglia LM. The rise of e-cigarettes, pod mod devices, and juul among youth: Factors influencing use, health implications, and downstream effects. Drug Alcohol Depend. 2019;201:85–93 [DOI] [PMC free article] [PubMed] [Google Scholar]
- 50.Walley SC, Wilson KM, Winickoff JP, Groner J. A public health crisis: Electronic cigarettes, vape, and juul. Pediatrics. 2019;143. [DOI] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.