



Abstract
Bullosis diabeticorum (BD) is considered a rare and relatively harmless skin manifestation with tense blisters appearing rapidly and mostly on the feet. Most papers report only a few cases and the cause of the blisters is not known. We have experienced that the lesions are not so rare and may turn into chronic foot ulcers with complications. Retrospective study of 25 consecutive patients with 35 outbreaks and 93 bullae in a population of 5000 people with diabetes treated during a 3‐year period. The bullae were deroofed in order to examine the bulla base and treated as foot ulcers including debridement, antibiotics, bandage and protective footwear. The incidence of BD per year in the present diabetic population is 0·16%. In 29 outbreaks, there were hypoglycaemic episodes or highly varying blood glucose. Antibiotics were given in 17 of 35 episodes. Time to healing was as much as median 2·5 months (range 0·5–23 months). Two patients had minor amputations. BD should be well known to all members of diabetic foot care teams. Blood glucose control with special attention to hypoglycaemia at the time of eruption, deroofing of the bullae and foot ulcer care are recommended.
Keywords: Bullosis diabeticorum, Diabetic foot, Diabetes mellitus, Foot wounds, Skin manifestations
Background
Cutaneous manifestations occur in approximately 30% of diabetic patients during the course of their illness (1). Among the skin diseases associated with diabetes mellitus, bullosis diabeticorum (BD) is poorly understood and considered to be rare. The majority of the literature is case stories 2, 3, 4, 5, 6, 7, 8, 9, 10, 11 with a few small series 12, 13. The diagnosis is based on characteristic findings, clinical course and the absence of any other tenable diagnosis. There are no specific diagnostic tests. The patient presents with painless bullae, evolved rapidly, often overnight and sometimes during less than 1 hour 1, 2, 3, 4, 7, 11(1, 2). The lesions are localised to the acral areas, in most cases the feet and with one to several bullae per episode. The fluid may be more or less syrupy in consistency, sometimes haemorrhagic (Figure 2). Recurrent episodes are not uncommon 2, 3, 5, 6, 9, 11, 14. In a recent larger study of 12 diabetic patients, the diagnosis was based among other findings on bullae, which healed with no scarring and without specific treatment in a few weeks (12). With such criteria, BD is per definition a relatively harmless disease in which the diagnosis can only be settled retrospectively. In our experience, the bullous lesions on the feet might turn into severe chronic ulceration with skin necrosis and infection (3, 4), and adequate diabetic wound care should therefore be initiated without delay. Moreover, frequent severe hypoglycaemia at the outbreak as found in the present series calls for immediate attention to blood glucose regulation. Based on data of 25 diabetic patients with lesions considered as BD, this skin manifestation is associated with significant morbidity as characteristic for diabetic foot ulcers.
Figure 1.
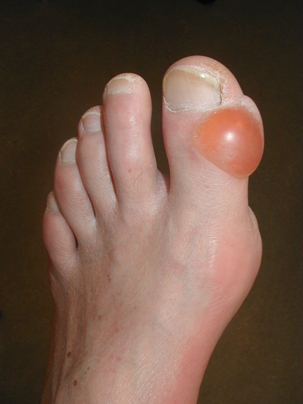
Typical lesion. Bulla developed spontaneously overnight.
Figure 2.
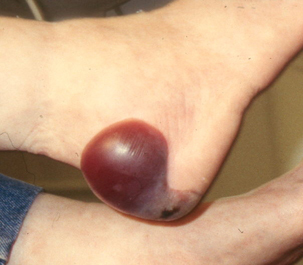
Typical lesion. Haemorrhagic bulla on the heel.
Figure 3.
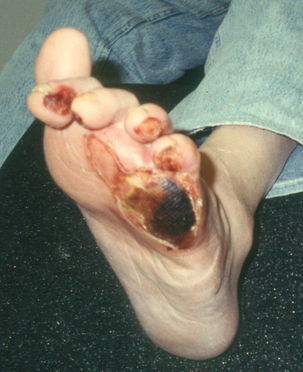
Deep skin necrosis following bullous eruption.
Figure 4.
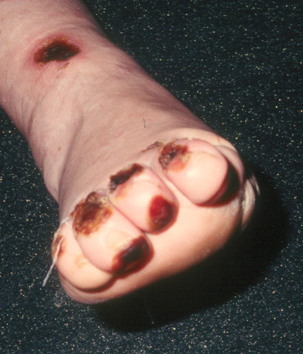
Several areas with skin necrosis following bullous eruptions. Because of the sparse soft tissue on the toes, the lesions are in close proximity with bone, tendons and joints.
Methods
During a 3‐year period, 25 diabetic patients with BD were treated in Steno Diabetes Center, a tertiary hospital specialised in the treatment of diabetes with a population of 5000 patients. One patient had 5 episodes, 1 had 4, 3 had 2 and 20 had 1, that is 35 episodes with 93 bullae. The series was consecutive and the files were studied retrospectively. The demographic data and comorbidity are given in Table 1.
Table 1.
Clinical data of 25 patients with bullosis diabeticorum*
| Men/women | 19/6 |
| Type 1 diabetes/type 2 diabetes | 21/4 |
| Age, years | 65 (42–81) |
| Diabetes duration, years | 14 (1–47) |
| Peripheral neuropathy (%) | 80 |
| Urinary albumin excretion (%) | |
| Normal <30 mg/24 hours) | 40 |
| Incipient nephropathy (30–300 mg/24 hours) | 20 |
| Diabetic nephropathy (>300 mg/24 hours) | 40 |
| Retinopathy (%) | |
| Normal | 8 |
| Simplex retinopathy | 60 |
| Proliferative retinopathy | 32 |
| Insulin dose, units/kg (n = 23) | 0·42 (0·10–1·20) |
| Other medication (%) | |
| Diuretics | 48 |
| Antihypertensives | 40 |
| Actual HbA1c (%) | 9·4 (5·5–13·4) |
| Change in HbA1c (%) | −0·1 (−4·1 to 4·6) |
| Thyroid function (%) | |
| Normal | 84 |
| Hypothyroidism | 12 |
| Hyperthyroidism | 4 |
| Haemoglobin (mmol/l) | 8·2 (6·5–9·6) |
| Cholesterol (mmol/l) | 5·0 (2·7–7·5) |
HbA1c, haemoglobin A1c.
Values are given as median (range) unless otherwise stated.
The localisation of the bullae is shown in Figure 5. All but one patient presented with bullae on the feet. Patients were not included if there was a history or clinical sign of infection, critical ischaemia, repetitive stress from shoe wear or overuse, other trauma including burns and frostbite or a clinical course with regular outbreak of new bullae indicating other skin disease. Twenty patients had peripheral neuropathy as evaluated by biothesiometry. Thirteen patients had palpable foot pulses, and 12 patients had toe blood pressures ranging from 46 to 95 mmHg, that is the perfusion was normal or near normal. Seven patients had Charcot deformity, six patients had previously undergone a toe or forefoot amputation, two a transtibial amputation.
Figure 5.
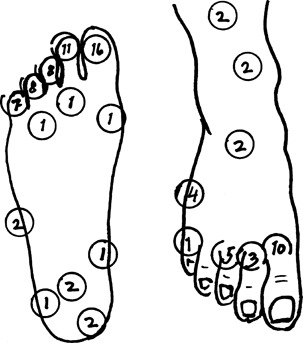
Localisation of 90 bullae on the lower limbs.
In ten patients, sufficient fluid from the bullae could be saved for measurement of the total protein content using a Dc Protein Kit (Bio‐Rad, Hercules, CA). In five analysis, interleukin 1‐beta could be measured using a cytokine‐specific enzyme‐linked immunosorbent assay (CytoSet; BioSource, Nivelle, Belgium). The comorbidity, the metabolic glycaemic state, insulin types and drugs were analysed for possible relation with the pathogenesis.
Treatment
The bullae were treated with deroofing in order to examine the floor, as this may present with wound bed infection or skin necrosis (3, 4, 6, 7) and the wound was covered by a moisty gauze, Bactigras® (Smith & Nephew, Hull, UK) and was changed three to six times per week. The feet were protected with therapeutic sandals (Rathgeber) with rigid rockerbar bottom and individual off loading insoles made of shock absorbing materials. Antibiotics were administered when there was sign of wound bed infection, invasive infection or necrosis. The patients were admitted, when blood glucose could not be properly controlled on an ambulant basis and when the foot lesions required extraordinary control for necrosis and debridement.
Figure 6.
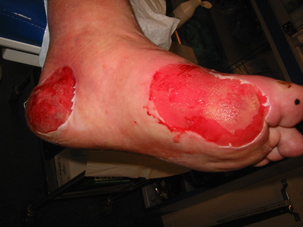
Deroofing allows proper inspection of the bulla base.
Figure 7.
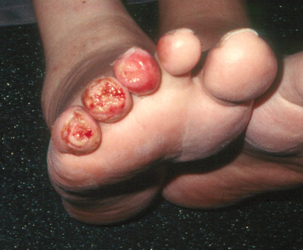
Wound bed infection in the bulla bases.
Results
The finding of 25 patients with eruption during a 3‐year period in our diabetes population of 5000 patients indicates an incidence of BD of 0·16% per year.
Seven patients were hospitalised from 1 to 2 weeks, one patient for 8 weeks because of skin lesions with necrosis and infection. Oral antibiotics were given in 17 of 35 episodes. Time to healing was as long as median 2·5 months (range 0·5–23 months) for 31 episodes. Two patients died with unhealed lesion. One patient had a partial toe amputation and one patient had a transmetatarsal ray amputation because of necrosis and infection. Ten patients had bespoke shoe wear before the bulla episodes, and after healing another two were supplied.
The levels of total fluid protein were: median 92·6 mg/ml (range 13·6–287 mg/ml). The values of interleukin 1‐beta varied greatly: median 7·4 pg/ml (range 4·9–572·5), or as expressed per mg protein: 0·105 pg/mg protein (range 0·051–2·863 pg/mg protein).
Although no obvious relation of the eruptions with late diabetic complications were found, more of the patients had peripheral neuropathy, albuminuria and retinopathy compared with the background diabetic population at Steno Diabetic Center. In accordance, many patients received antihypertensives and diuretics, but no specific type of drug was overrepresented among the patients. Likewise, no single type of insulin was used. The haemoglobin A1c (HbA1c) did not differ from the latest previous test. However, in 20 of 35 cases of BD, the patients reported hypoglycaemic episodes, often at the time of bulla eruption. Moreover, in nine cases, the blood glucose varied considerably from about 5 to 25 mmol/l or with values lying far from the level indicated by HbA1c. In five cases, the patients had severe longstanding hyperglycaemia.
Discussion
The more important findings of the present study are the severity of the lesions and the relatively high incidence of 0·16%, that is of the same order of magnitude as for example Charcot’s osteoarthropathy (15). Recently used diagnostic criteria were the occurrence of non traumatic bullae, which could not be otherwise explained and which healed within a few weeks without scarring (12). However, chronic lesions have been described in other papers 3, 5, 7, 9, and also toe amputation, large necrotic areas, osteomyelitis and scarring have been reported 3, 7, 8, 12, 16, demonstrating that there is no consensus on the definition of BD. The recommended treatment consisting of aspiration of the blisters to prevent spontaneous rupture and using the blister skin as wound covering (12), may perhaps be adequate for blisters on the hands and uncomplicated cases in the feet. However, treatment should aim at preventing or limiting complications. Because the bulla base may show or may develop necrosis and/or infection, we recommend initial deroofing for inspection and drainage, treatment with a non adherent medicated bandage and regular wound care, protection of the foot and offloading, possibly antibiotics, full assessment of the condition of the diabetic foot, the metabolic condition and comorbidity, that is a standard programme for treatment of diabetic foot ulcers.
The somewhat varying definition of BD is related to the lack of an exact diagnostic tests. The appearance of the bullae in our series were typical. They ranged in size from 0·5 to 10 cm and at the time of eruption, there was no surrounding erythema or induration. The eruption was often dramatically fast and we have seen development over 15 minutes during a visit in the foot clinic. Bullae were most commonly found on the toes, often dorsally and on the plantar surfaces of the feet. One had lesions on the hands. If localised to the plantar surface, the bullae usually occurred in skin sites with no calluses demonstrating that there is more to the aetiology than just repetitive stress. Bullae caused by severe infection or ischaemia can be safely excluded by clinical examination, by objective measurements of the arterial perfusion and by the course of the disease. Burns or frostbite will be evident from the history. Other skin diseases such as pemphigoid, porphyria cutanea tarda, erythema multiforme and epidermolysis bullosa aquisita can be excluded based on the clinical course and specific tests.
Histopathological examinations have shown inconsistent levels of skin separation. The split may be intraepidermal (subcorneal to suprabasilar) 1, 3, 4, 14, 17 as well as subepidermal 1, 2, 4, 6, 8, 10, 11, 14. Electron microscopy has shown separation of the cell membrane and basal lamina preceded by loss of anchoring filaments and hemidesmosomes (1), but other investigators have found these structures intact (2). One paper reported a patient with immunoglobulin M , complement and fibrinogen in the wall of the dermal blood vessels (6), but others have found no evidence of deposition of complements or immunoglobulins. Direct fluorescence microscopy of the perilesional skin has been found to be normal 2, 6, 18. Thus, no specific pathology has been found. Biopsy is not without risk in a diabetic neuropathic or neuroischaemic foot and should be used only in case of continuous eruptions suggesting chronic skin disease.
Most patients reported in the literature have diabetes of long duration, but the range is from newly diagnosed diabetes to about 30‐year duration. BD is described in type 1 as well as type 2 diabetes treated with or without insulin. The age of the patients varies from 17 to 80 years, most patients being 50–70 years. Males are more commonly affected than women 11, 12. Our patients were elderly, the far majority were men and with longstanding type 1 diabetes. In concordance with previous papers, most of our patients presented with late complications to diabetes including peripheral neuropathy but with peripheral arterial perfusion adequate for healing.
The bullous fluid is typically proteinacous 2, 10, and the present protein measurements demonstrate highly varying protein content similar to that in fluid from acute and chronic wounds 19, 20. Secretion of interleukin 1‐beta and other proinflammatory factors starts almost immediately after an acute skin lesion and is useful in determining vitality and wound age in forensic medicine (21). Interleukin 1‐beta was present in the wound fluid in very varying small amounts, but the clinical significance of this is not clear at present.
Many theories have been forwarded for the aetiology of BD. A decreased threshold for suction‐induced blisters was found in 15 patients with type 1 diabetes compared with 20 control subjects (22). Such an increased susceptibility to develop blisters from minor frictional or physical trauma has, however, been questioned by others (23). Other suggestions for the aetiology are microangiopathy 2, 8, 24, neuropathy 13, 24, 25, nephropathy 1, 26 and disturbed metabolism of calcium (1). None of these factors, however, is universal.
Previously, that is in the l970s and 1980s, BD was rarely seen in our setting, and the incidence is probably increasing. For this reason, we analysed whether BD could be because of modern treatment including new types of insulin, cholesterol lowering and antihypertensive drugs including furosemide and angiotensin‐converting enzyme inhibitors. But we were not able to identify any specific causative agents or common denominators.
Little attention has been directed to the glycaemic regulation. We compared the HbA1c, 3 months before and at the time of outbreak, but there was no significant change. However, in the majority of the episodes, the patients had hypoglycaemic episodes or presented with highly varying blood glucose. Neither hypoglycaemic episodes nor greatly varying glycaemia would necessarily be revealed by the HbA1c because of the averaging nature of this test. In our opinion, it is likely that poor metabolic control, possibly hypoglycaemia in particular, or highly varying glycaemia is important in the pathophysiology.
Toxicological studies during Second World War have shown that blisters caused by toxic compounds such as Lewisite and arsenicals were because of severe poisoning of the oxidation of carbohydrates at the pyrovate enzyme level (27). This might support the suggested importance of the metabolic control.
Although BD has been described in relation to ketoacidosis and hyperglycaemia 28, 29, most reported cases with type 1 diabetes were described as properly controlled and the possibility of hypoglycaemia seems not to be explored. BD is also reported in type 2 diabetic patients not receiving insulin, which makes hypoglycaemia less likely as the only precipitating cause. Our patients were nearly all poorly controlled in spite of frequent admission for regulation and our series differ on that point from most previous reports. This might perhaps also explain that many of our cases developed chronic ulceration. Perhaps the real aetiology of BD lies somewhere in between the aforementioned theories and observations, that is some pathology is not properly identified, but with an increased propensity for eruptions when the metabolic control is poor.
Conclusion
BD must be considered a not so rare and potential serious complication to diabetes mellitus in type 1 as well as in type 2 diabetes. BD should be well known to all members of foot care teams. It is recommended to treat eruptions as foot ulcers and to examine for hypoglycaemia or greatly varying blood glucose at the outbreak. A bullous lesion in a diabetic foot requires standard assessment of the foot and patient and a standard diabetic wound care programme.
Acknowledgements
Analysis for protein and interleukin 1‐beta was carried out by biochemist Rikke Zilmer, PhD and by laboratory technician. Rikke Roel.
References
- 1. Bernstein JE, Medenica M, Soltani K, Griem SF. Bullous eruption of diabetes mellitus. Arch Dermatol 1979;115:324–5. [PubMed] [Google Scholar]
- 2. Basarab T, Munn SE, McGrath J, Russell JR. Bullosis diabeticorum. A case report and literature review. Clin Exp Dermatol 1995;20:218–20. [DOI] [PubMed] [Google Scholar]
- 3. Borner C, Herzog E, Hild R, Hopker WW. [Bullosis diabeticorum: 2 follow‐up studies]. Med Klin (Munich) 1987;82:165–8. [PubMed] [Google Scholar]
- 4. Cantwell AR Jr, Martz W. Idiopathic bullae in diabetics. Bullosis diabeticorum. Arch Dermatol 1967;96:42–4. [PubMed] [Google Scholar]
- 5. Cope RL. Spontaneous bulla formation in the skin in diabetes mellitus. Ann Intern Med 1950;32:964–7. [DOI] [PubMed] [Google Scholar]
- 6. James WD, Odom RB, Goette DK. Bullous eruption of diabetes mellitus. A case with positive immunofluorescence microscopy findings. Arch Dermatol 1980;116:1191–2. [PubMed] [Google Scholar]
- 7. Kramer D. Early or warning signs of impending gangrene in diabetes. Med J Rec 1930;132:338–42. [Google Scholar]
- 8. Kurwa A, Roberts P, Whitehead R. Concurrence of bullous and atrophic skin lesions in diabetes mellitus. Arch Dermatol 1971;103:670–5. [PubMed] [Google Scholar]
- 9. Lejman K, Chorzelski TP, Starzycki Z. [Bullous skin changes with ensuing transformation into necrotic ulcers in diabetes mellitus]. Dermatol Monatsschr 1977;163:790–3. [PubMed] [Google Scholar]
- 10. Pirotta SS, Johnson JD, Young G, Bezzant J. Bullosis diabeticorum. J Am Podiatr Med Assoc 1995;85:169–71. [DOI] [PubMed] [Google Scholar]
- 11. Toonstra J. Bullosis diabeticorum. Report of a case with a review of the literature. J Am Acad Dermatol 1985;13(5 pt 1):799–805. [PubMed] [Google Scholar]
- 12. Lipsky BA, Baker PD, Ahroni JH. Diabetic bullae: 12 cases of a purportedly rare cutaneous disorder. Int J Dermatol 2000;39:196–200. [DOI] [PubMed] [Google Scholar]
- 13. Rocca FF, Pereyra E. Phlyctenar lesions in the feet of diabetic patients. Diabetes 1963;12:220–2. [DOI] [PubMed] [Google Scholar]
- 14. Feldmann R, Prins C. [Skin symptoms in diabetic metabolism]. Ther Umsch 1995;52:264–8. [PubMed] [Google Scholar]
- 15. Fabrin J, Larsen K, Holstein PE. Long‐term follow‐up in diabetic Charcot feet with spontaneous onset. Diabetes Care 2000;23:796–800. [DOI] [PubMed] [Google Scholar]
- 16. Tunuguntla A, Patel KN, Peiris AN, Zakaria WN. Bullosis diabeticorum associated with osteomyelitis. Tenn Med 2004;97:503–4. [PubMed] [Google Scholar]
- 17. Gouterman IH, Sibrack LA. Cutaneous manifestations of diabetes. Cutis 1980;25:45–54. [PubMed] [Google Scholar]
- 18. Paltzik RL. Bullous eruption of diabetes mellitus. Bullosis diabeticorum. Arch Dermatol 1980;116:474–6. [DOI] [PubMed] [Google Scholar]
- 19. Baker EA, Leaper DJ. Proteinases, their inhibitors, and cytokine profiles in acute wound fluid. Wound Repair Regen 2000;8:392–8. [DOI] [PubMed] [Google Scholar]
- 20. Zillmer R. Characterisation of the microenvironment in chronic wounds. PhD thesis, Copenhagen Wound Mealing Center, University of Copenhagen, 2001. [Google Scholar]
- 21. Grellner W. Time‐dependent immunohistochemical detection of proinflammatory cytokines (IL‐1beta, IL‐6, TNF‐alpha) in human skin wounds. Forensic Sci Int 2002;130:90–6. [DOI] [PubMed] [Google Scholar]
- 22. Bernstein JE, Levine LE, Medenica MM, Yung CW, Soltani K. Reduced threshold to suction‐induced blister formation in insulin‐dependent diabetics. J Am Acad Dermatol 1983;8:790–1. [DOI] [PubMed] [Google Scholar]
- 23. Huntley AC. Threshold to suction‐induced blister formation in insulin‐dependent diabetics. J Am Acad Dermatol 1984;10:305–6. [DOI] [PubMed] [Google Scholar]
- 24. Goodfield MJ, Millard LG, Harvey L, Jeffcoate WJ. Bullosis diabeticorum [letter]. J Am Acad Dermatol 1986;15:1293–4. [DOI] [PubMed] [Google Scholar]
- 25. Hofbauer MH, Puleo D. Idiopathic diabetic bullosum. A case report. J Am Podiatr Med Assoc 1991;81:613–7. [DOI] [PubMed] [Google Scholar]
- 26. Downham TF, Chapel TA. Bullous pemphigoid therapy in patients with and without diabetes mellitus. Arch Dermatol 1978;114:1639–42. [DOI] [PubMed] [Google Scholar]
- 27. Peters RA, Stocken LA, Thompson RHS. British anti‐Lewisite (BAL). Nature 1945;156:616–9. [DOI] [PubMed] [Google Scholar]
- 28. Allen GE, Hadden DR. Bullous lesions of the skin in diabetes (bullosis diabeticorum). Br J Dermatol 1970;82:216–20. [DOI] [PubMed] [Google Scholar]
- 29. Plaseski A, Sadikario S, Dimitrovski C, Bogoev M. Bullosis diabeticorum in a juvenile diabetic with ketoacidosis. God Zb Med Fak Skopje 1977;23:943–8. [PubMed] [Google Scholar]