



Abstract
BACKGROUND
Chromosomal mosaicism can be detected in different stages of early life: in cleavage stage embryos, in blastocysts and biopsied cells from blastocysts during preimplantation genetic testing for aneuploidies (PGT-A) and later during prenatal testing, as well as after birth in cord blood. Mosaicism at all different stages can be associated with adverse pregnancy outcomes. There is an onward discussion about whether blastocysts diagnosed as chromosomally mosaic by PGT-A should be considered safe for transfer. An accurate diagnosis of mosaicism remains technically challenging and the fate of abnormal cells within an embryo remains largely unknown. However, if aneuploid cells persist in the extraembryonic tissues, they can give rise to confined placental mosaicism (CPM). Non-invasive prenatal testing (NIPT) uses cell-free (cf) DNA released from the placenta in maternal blood, facilitating the detection of CPM. In literature, conflicting evidence is found about whether CPM is associated with fetal growth restriction (FGR) and/or other pregnancy outcomes. This makes counselling for patients by clinicians challenging and more knowledge is needed for clinical decision and policy making.
OBJECTIVE AND RATIONALE
The objective of this review is to evaluate the association between CPM and prenatal growth and adverse pregnancy outcomes. All relevant literature has been reviewed in order to achieve an overview on merged results exploring the relation between CPM and FGR and other adverse pregnancy outcomes.
SEARCH METHODS
The following Medical Subject Headings (MESH) terms and all their synonyms were used: placental, trophoblast, cytotrophoblast, mosaicism, trisomy, fetal growth, birth weight, small for gestational age and fetal development. A search in Embase, PubMed, Medline Ovid, Web of Science, Cochrane Central Register of Controlled Trials (CENTRAL) and Google Scholar databases was conducted. Relevant articles published until 16 July 2020 were critically analyzed and discussed.
OUTCOMES
There were 823 articles found and screened based on their title/abstract. From these, 213 articles were selected and full text versions were obtained for a second selection, after which 70 publications were included and 328 cases (fetuses) were analyzed. For CPM in eight different chromosomes (of the total 14 analyzed), there was sufficient evidence that birth weight was often below the 5th percentile of fetal growth standards. FGR was reported in 71.7% of CPM cases and preterm birth (<37 weeks of delivery) was reported in 31.0% of cases. A high rate of structural fetal anomalies, 24.2%, in cases with CPM was also identified. High levels of mosaicism in CVS and presence of uniparental disomy (UPD) were significantly associated with adverse pregnancy outcomes.
WIDER IMPLICATIONS
Based on the literature, the advice to clinicians is to monitor fetal growth intensively from first trimester onwards in case of CPM, especially when chromosome 2, 3, 7, 13, 15, 16 and 22 are involved. In addition to this, it is advised to examine the fetuses thoroughly for structural fetal anomalies and raise awareness of a higher chance of (possibly extreme) premature birth. Despite prematurity in nearly a fifth of cases, the long-term follow-up of CPM life borns seems to be positive. More understanding of the biological mechanisms behind CPM will help in prioritizing embryos for transfer after the detection of mosaicism in embryos through PGT-A.
Keywords: pregnancy, chorionic villi sampling, trisomy, aneuploidy, mosaicism, birth weight, fetal growth retardation, pregnancy outcome, embryonic development, fertilization in vitro
Introduction
The human embryo
Following fertilization, the human zygote goes through eight or nine rounds of cell division before implantation. After the cleavage divisions, the embryo undergoes compaction and then the first lineage specification results in formation of the blastocyst, comprising of an outer layer of polarized epithelial cells, the trophectoderm (TE), a compact inner cell mass (ICM) and a fluid filled cavity, the blastocoel. The extraembryonic TE develops into the trophoblast and cytotrophoblast compartments of the placenta, while during the second lineage specification the ICM will form the epiblast and the hypoblast that later give rise to the fetus and yolk sac, respectively. The hypoblast also contributes to the mesenchymal core present in the chorionic villi (Fig. 1).
Figure 1.

Schematic illustration of pre- and post-implantation development. (A) A blastocyst at day 5 of embryonic development. Two cell types can be defined at this early stage: the trophectoderm (TE) and the inner cell mass (ICM). The extra embryonic TE develops into two tissues of the fetal part of the placenta, the syncytioblast and cytotrophoblast. Short-term culture villi (STC- villi) studies examine the cytotrophoblast. The ICM will develop into the epiblast (eventually the fetus) and the hypoblast (eventually the mesenchymal core). Long- term culture villi (LTC-villi) studies examine the mesenchymal core. Because of their same origin (i.e. the ICM), the LTC-villi is a better reflection of the fetus than the STC-villi. (B) The different cell types after implantation on the 13th day of the embryonic development. (C) Confined placental mosaicism (CPM) can be categorised into the three subtypes, depending on the cell lineage(s) affected.
Aneuploidy and mosaicism during preimplantation embryo development
Interestingly, this process of early human embryo development suffers from high rates of aneuploidy, which constitutes a major cause of early pregnancy loss (Macklon et al., 2002; Nagaoka et al., 2012). Insights derived from in-vitro fertilization (IVF) embryos demonstrate that chromosome abnormalities can be observed in 50–90% of human IVF embryos at the 8-cell stage (van Echten-Arends et al., 2011; McCoy, 2017; Popovic et al., 2020). In embryos from young women, some of these embryos (10–20%) are uniformly aneuploid, as the result of an error during meiosis in the oocyte (Baart et al., 2006; McCoy et al., 2015). The proportion of embryos affected by an error originating during meiosis in the oocyte increases dramatically with maternal age (Gruhn et al., 2019). The majority of embryos at the cleavage stages, however, consist of a mixture of cells with normal and abnormal chromosomal constitutions, or cells with different abnormalities (Baart et al., 2006; Vanneste et al., 2009; van Echten-Arends et al., 2011; Mertzanidou et al., 2013; Akera and Lampson 2019; Shi, Qiu et al., 2020; Starostik et al., 2020; Tsuiko et al., 2020). The presence of two (or more) distinct cytogenetic populations of cells in an embryo or individual derived from a single fertilized oocyte is defined as mosaicism (Spinner and Conlin, 2014). These mosaic embryos are the result of post-zygotic errors, i.e. chromosome segregation errors occurring during the first mitotic divisions.
The timing of the segregation error defines the degree of mosaicism and the affected cell lineages, resulting in diverse mosaic patterns (McCoy, 2017). The etiology of mosaicism in human preimplantation embryos is multifactorial and has been reviewed extensively elsewhere (McCoy, 2017; Popovic et al., 2020; Tsuiko et al., 2020). It is hypothesized that the molecular pathways that normally monitor accurate chromosome segregation are less stringent in early embryos to allow for the rapid cell divisions needed for development to occur in a concerted fashion (Akera and Lampson, 2019; Vazquez-Diez et al., 2019). After the cleavage stages, the incidence of aneuploidy and chromosomal mosaicism appears to decrease as embryos reach the blastocyst stage, as there seems to be a selection within the embryo against cells carrying complex abnormalities and monosomies (McCoy et al., 2015; Fragouli et al., 2019). Although establishing the exact prevalence of mosaicism at the blastocyst stage remains a challenge (as reviewed in (Popovic et al., 2018; Fragouli et al., 2019; Starostik et al., 2020), it appears that chromosomal mosaicism can still be detected in at least one-third of blastocysts (Santos et al., 2010; Popovic et al., 2018; Fragouli et al., 2019; Starostik et al., 2020).
Preimplantation genetic testing for aneuploidies and mosaicism
Preimplantation genetic testing for aneuploidies (PGT-A) is considered a promising strategy to select chromosomally normal embryos for transfer with the aim of improving IVF treatment outcomes. This is currently preferably performed by a trophectoderm biopsy of 5–10 cells at the blastocyst stage, followed by analysis of the biopsied cells by comprehensive molecular cytogenetic methods. The TE cells are used to predict the chromosomal configuration of the remaining embryo, as shown in Fig. 2. The recent development of more sensitive forms of next-generation sequencing (NGS) enabled improved detection of mosaicism within a biopsy (Fragouli et al., 2017). If mosaicism is detected, the decision as to whether the embryo qualifies for transfer is ambiguous. There is an ongoing debate about whether the mosaicism detected correctly reflects the true incidence of mosaicism or whether it results from a technical artifact (Capalbo and Rienzi, 2017; Marin et al., 2020; Popovic et al., 2020). As a result, clinical management remains unclear. To date, scientific data on the transfer of mosaic embryos is limited. The transfer of mosaic embryos can result in healthy life births (Munne et al., 2020), but is also associated with decreased implantation, as well as increased risk of genetic abnormalities and adverse pregnancy outcomes (Victor et al., 2019; Munne et al., 2020; Tiegs et al., 2020). From a counseling perspective, this makes it difficult to predict the risk, phenotype and long-term effect on the offspring.
Figure 2.

From blastocyst cells to prenatal scenario. (A) Three different scenarios arise if only diploid cells are retrieved through biopsy in blastocyst stage. (B) When both diploid and trisomic cells are biopsied, three different scenarios can also arise. If the mosaicism is only found in the trophectoderm and not within the inner cell mass (ICM), confined placental mosaicim (CPM) type 1 develops. (C) If all biopsied cells appear to be trisomic, even in the ICM, as a result of trisomic rescue, the epiblast will eliminate the trisomic cells and will only consist of diploid cells, thus CPM type 2 or 3 can develop.
Aneuploidy and mosaicism during post-implantation development
The incidence of aneuploidy in recognized pregnancies is strongly related to maternal age and is also dependent on the stage of development. Only 0.6% of newborns are aneuploid, but the incidence of aneuploidy is 45% when miscarriages are investigated (Hook, 1981; van den Berg et al., 2012). The most common abnormalities among newborns and stillbirths are trisomy 13, 18, 21 or sex chromosomal aneuploidies (i.e. 45X, 47XXX, 47XXY and 47XYY). The only significant monosomy observed during post-implantation development is 45, X (Nagaoka et al., 2012). In contrast, trisomies of all chromosomes have been described in miscarriages, with the most common being trisomy 15, 16, 21 or 22. With the exception of 21, these aberrations are lethal early in pregnancy, and only allow fetal survival beyond the first trimester if present in mosaic form.
Prenatal testing procedures
Different genetic tests can be performed during pregnancy and are derived from different origins of early embryonic development. Chorionic villus sampling (CVS) is a prenatal procedure in which a sample of chorionic villi is removed from the placenta for genetic testing. The procedure can be performed transabdominally or transcervically, according the placental localization and the experience and/or preference of the operator. CVS should be performed after 10 weeks of gestation (Ghi et al., 2016). With the samples of the chorionic villi, two different analysis approaches are performed, short-term culture (STC-villi) and long-term culture (LTC-villi) of the villi. STC-villi allows the analysis of the cytotrophoblast which originates from the trophoblast (Fig. 1) (Gibas, Grujic et al., 1987). LTC-villi allows selection of cells from the mesenchymal core that originates from the hypoblast compartment of the ICM (Fig. 1) (Smidt-Jensen et al., 1989).
Amniocentesis refers to transabdominal aspiration of amniotic fluid from the uterine cavity. This should be performed at or beyond 15 weeks of gestation (Ghi et al., 2016). Amniotic cells come from the epiblast, which will form the embryo (Fig. 1).
At the time of writing, non-invasive prenatal testing (NIPT) is the most recently developed prenatal test. This test is based on the analysis of cell-free DNA (cfDNA) fragments, the fetal part originating from the placenta, circulating in the maternal plasma. These cfDNA fragments end up in the maternal plasma as a result of apoptotic cytotrophoblast of chorionic villi. Therefore, NIPT analyzes the same cells as the STC-villi during CVS. In general, NIPT is used as a screening method (mostly limited to detection of trisomy 21, 13 and 18). In case of a positive finding, diagnostic follow-up investigation such as CVS or amniocentesis is needed.
Currently, different molecular karyotyping techniques exist to analyze the different prenatal samples, each with their own advantages and limitations for detecting aneuploidy and mosaicisms. This is beyond the scope of this review and has been the focus of another recent review (Jelin et al., 2019).
Confined placental mosaicism and its different subtypes
Confined placental mosaicism (CPM) is defined as a chromosomally abnormal cell line restricted to the placenta, while the chromosomes of the fetus itself are normal (Fig. 2) (Kalousek and Dill, 1983). CPM usually does not give rise to ultrasound abnormalities or pregnancy complications, so it is in general found by accident.
CPM can arise as a result of a post-zygotic error, through non-disjunction in a diploid conception. It can also arise by a trisomic rescue mechanism, wherein a viable trisomic conceptus loses one chromosome through anaphase lagging and produces a diploid cell line (Fig. 2) (Schuring-Blom et al., 1993; Kalousek, 2000).
CPM can be categorized into three subtypes (type 1, 2 and 3) depending on where the chromosomal abnormality is found in the placenta, as shown in Fig. 1 (Toutain et al., 2018). When the chromosomal abnormality is only found in the cytotrophoblast (and can be found after examination of the short-term culture villi (STC)), it is CPM type 1. If the chromosomal abnormality is only found after long-term culture villi (LTC), it is restricted to the mesenchymal core of the chorionic villi, and is categorized as type 2. Type 3 is defined as the presence of the abnormality in both the mesenchymal core and cytotrophoblast and can be found after both LTC and STC analysis. As noted above, NIPT (and STC-villi) analyzes the cytotrophoblast and thereby NIPT is able to determine CPM type I and type III.
As a result of trisomy rescue mechanism, uniparental disomy (UPD) can occur. UPD refers to the situation in which two copies of a chromosome come from the same parent, instead of one maternal and one of paternal origin. UPD can have multiple different disease implications; the most familiar is Prader Willi Syndrome caused by UPD 15 (Yamazawa et al., 2010).
Over the last seven years, NIPT has been widely introduced in obstetric medicine as a screening test for trisomy 21, 13 and 18, enabling large scale prenatal testing without an indication. In addition, NIPT has been suggested to be more sensitive to detect CPM as compared to CVS, as the entire placental trophoblast sheds cfDNA into the maternal circulation (Brison et al., 2018; Van Opstal et al., 2020). The presence of chromosomally abnormal cells restricted to the placental areas that are not sampled by CVS, may be detected with NIPT. Therefore, NIPT can give an abnormal result indicating the presence of CPM in an otherwise uneventful pregnancy, thereby increasing the chances of identifying cases with CPM.
CPM during pregnancy
As noted, pregnancies with CPM are usually uneventful during the first trimester, or at least until the time of prenatal testing. However, CPM can be associated with fetal growth restriction (FGR) (Kalousek and Dill, 1983; Toutain et al., 2018). Therefore, in obstetric practice, caregivers advise regular checks of fetal growth during pregnancy in case of diagnosed CPM. Conversely it is not common policy to search actively for CPM in case of FGR. Still, to provide adequate counselling in cases of CPM, it is very important to have detailed knowledge of the possible impacts CPM has on the outcome of pregnancy. Here, reported findings are conflicting. There are case reports in which no signs of FGR or other adverse pregnancy outcomes are observed in cases of CPM (Goldberg and Wohlferd, 1997; Amor et al., 2006). And in some cases after a normal amniocentesis and no structural fetal anomalies found at the advanced ultrasound, there is still a possibility of fetal mosaicism and congenital anomalies.
Therefore, different strategies have been used to improve prediction of the clinical outcome. It has been suggested to use the presence of uniparental disomy (UPD) (Bennett et al., 1992) or the percentage of chromosomally abnormal cells within the biopsied cells as additional predictors (Wolstenholme et al., 1994). Other authors suggest a relation between elevated maternal serum screening and impaired fetal growth in case of CPM (Zimmermann et al., 1995; Groli et al., 1996; Morssink et al., 1996). There are also case reports of CPM with no signs of FGR or other adverse pregnancy outcomes (Goldberg and Wohlferd, 1997; Amor et al., 2006). In obstetric literature, it seems clear that adverse pregnancy outcomes in CPM also depend on the chromosome involved in the trisomic cell line present, as there appears to be a correlation with fetal growth (Toutain et al., 2018). Data for a chromosome-based risk assessment are currently lacking.
This literature review aims to provide an overview about fetal growth and pregnancy outcome in case of CPM. It also aims to provide a comprehensive overview of all the literature available on the specific chromosome involved in the abnormality observed in CPM and assesses whether there is a difference in outcome between chromosomes. To this end, an analysis per chromosome is performed in order to make a detailed description and provide tools for counselling. These insights are valuable for obstetric care givers facing a patient with a normal trimester pregnancy and a diagnosis of CPM, but also for risk assessment in the decision to transfer a mosaic embryo after PGT-A.
Methods
Search strategy
The literature search was developed in consultation with a research librarian. The latest update of the library was on 16 July 2020. The following Medical Subject Headings (MESH) terms and all their synonyms were used: placental, trophoblast, cytotrophoblast, mosaicism, trisomy, fetal growth, birth weight, small for gestational age and fetal development. EMBASE, Medline (including Epub (Ovid)), Cochrane Central Register of Controlled Trials (CENTRAL) and Google Scholar databases were systematically searched for all relevant articles on CPM and fetal growth or birth weight and other adverse pregnancy outcomes. The search was restricted to publications in English and Dutch language, human populations.
Study selection
A flowchart of the search strategy and study selection process of the articles is shown in Fig. 3. Three independent reviewers (A.T.J.I.G., G.M.E. and R.J.H.G.) screened titles and abstracts of all retrieved articles for relevance. Published manuscripts that potentially contained results of CPM and fetal growth were selected for critical appraisal of the full text. Exclusion criteria were papers with an absence of obstetric information, papers reporting fetal abnormalities and literature reviews.
Figure 3.

Flowchart of the search strategy and study selection process.
The full text versions of the remaining publications were obtained and underwent a second selection. To ensure all cases were CPM, diagnostic workup had to be complete to meet inclusion. Trisomy had to be found in placenta or chorionic villus sampling and normal results had to be reported in fetal tissue or amniocentesis. As the aim was to analyze growth in fetuses with CPM, only studies describing birth weight (or percentiles of the birth weight) and/or ultrasound measurements were selected.
All comments on previous publications, conference abstracts and posters were excluded. A quality assessment could not be performed, due to the variety of collection/extraction protocols. The reasons for termination of pregnancy (TOP) were screened. If FGR or a structural fetal anomaly was the reason to terminate, the cases were included, in order not to miss these adverse pregnancy outcomes. If there was no information about fetal growth or other adverse pregnancy outcome, the cases were excluded.
Disagreements regarding inclusion or exclusion were resolved by discussion between the three reviewers until full agreement was achieved. The data were extracted from the publications and collected in a database categorized per chromosome. All reviewers agreed on the relevance of the articles in the last selection phase. All data were extracted from the articles and collected in a database, if the required criteria (as described above) were met. Publications that did not mention the involved chromosome were reported and discussed separately (Roland et al., 1994; Wilkins-Haug et al., 2006; Grati et al., 2020). These publications all made a comparison between CPM cases and a control group. Considering that these publications provided information about growth, all three were included.
If birth weight percentiles were missing in the original article, INTERGROWTH-21st was used to provide this missing data (Villar et al., 2014). Every chromosome with more than five cases was analyzed; 14 chromosomes met these criteria. We considered five cases as a minimal sample size for statistical analysis. The birth weight percentiles were compared using chi-square test (χ2) in SPSS v.26. The association between level of mosaicism and UPD with pregnancy outcomes was analyzed using the Mann-Whitney test in SPSS v.26.
Results
After critical appraisal of all 213 full-text articles, 70 publications were selected and 328 cases (fetuses) could be extracted. All cases were collected in a database and categorized per chromosome. The results of all the CPM cases were explored, with cytogenetics and pregnancy outcomes in the first section. After extraction of the main findings, an assessment of birth weight was performed. Birth weight was mentioned for the vast majority of the cases (n = 300, 91.5%). In the second section of the results, four sub-groups were examined. First the structural fetal anomalies, followed by CPM trisomy 16 (n = 100, 30.5%) which is the most published trisomy. The last two topics in the result section are follow-up and all publications, in which separate CPM cases were reported, but clustered into CPM and a control groups.
Characteristics of all cases are shown in Supplementary Table SI. The numbers of cases per chromosome are shown in Table I. Only four cases including sex chromosomes were found. As a result of the small number, we could not use these cases in our analyses. Because of different available variables per publication, there can be different total cases per analysis. The total involved cases will be named separately per analysis.
Table I.
Numbers of confined placental mosaicism cases involving different chromosomes.
| Chromosome | n | Chromosome | n |
|---|---|---|---|
| 2 | 22 | 13 | 13 |
| 3 | 15 | 14 | 2 |
| 4 | 3 | 15 | 9 |
| 5 | 4 | 16 | 100 |
| 6 | 3 | 17 | 2 |
| 7 | 41 | 18 | 17 |
| 8 | 32 | 20 | 6 |
| 9 | 11 | 21 | 10 |
| 10 | 6 | 22 | 16 |
| 11 | 4 | triploidy | 3 |
| 12 | 8 | tetraploidy | 1 |
Cytogenetics
Most of the cases were identified prenatally, either through CVS or NIPT. Only in 17 cases (5.3%), the diagnosis of CPM was made postnatally, through placental analysis. The numbers of tests performed are shown in Table II; the numbers in this table are not per person, as some cases had multiple tests per pregnancy.
Table II.
Numbers of tests performed among 328 cases.
| Test | n |
|---|---|
| Chorion villus sampling | 270 |
| NIPT | 44 |
| Amniocentesis | 291 |
| Placental biopsy | 85 |
| Fetal tissue | 103 |
Some cases had multiple tests per pregnancy.
In 100 cases (30.5%), the percentage of mosaicism in CVS was analyzed, with a median of 76% (inter-quartile range (IQR) 29–100). Only in 45 placental biopsies (52.9%), the percentage of mosaicism in the biopsy was reported, with a median of 100% (IQR 32.5–100).
In 118 cases (35.9%) uniparental disomy (UPD) was analyzed and was found in 29.7% (n = 35) of the cases. Most of the UPD cases were cases of CPM involving trisomy 16 (n = 21, 60%). In three cases, the results were inconclusive. In almost all of the cases, distinction between maternal and paternal UPD was made; only in three cases this distinction was not mentioned. The majority of the 35 UPD cases were maternal (90.9%). When considering only cases involving UPD, FGR was reported in 60% (n = 21). Comparing UPD cases with cases without UPD, UPD does not significantly increase the risk of fetal growth restriction (n = 27, p = 0.151). However pregnancy duration was significantly different between UPD and cases without UPD (n = 97, p = 0.000). UPD cases include significantly more birthweights below the 3rd, 5th and 10th percentile compared to cases without UPD (p = 0.025, 0.005, and 0.000, respectively).
In the 100 (30.5%) cases, where the level of mosaicism in CVS was given, higher levels of mosaicism were associated with significantly more premature births and more FGR. Significantly more birthweights below the 3rd, 5th and 10th percentile were found with higher levels of mosaicism in CVS (p = 0.032, 0.001, and 0.000, respectively).
Pregnancy outcomes
An overview of pregnancy outcomes is shown in Table III. As a result of different reported variables per publication, the total number of analyzed cases is included in this table.
Table III.
Pregnancy outcomes in cases of confined placental mosaicism.
| Pregnancy outcomes | Analyzed cases (n) | |
|---|---|---|
| Gestational age (weeks) | 38 + 0 (18 + 0 - 42 + 0)* | 229 |
| Female gender | 168 (57.5%) | 292 |
| Preterm birth | 44 (19.2%) | 229 |
| Very preterm birth | 27 (11.7%) | 229 |
| IUFD | 12 (3.6%) | 328 |
| TOP | 15 (4.6%) | 328 |
| Postnatal death | 9 (2.7%) | 328 |
| Structural fetal anomalies | 38 (24.2%) | 157 |
| Pregnancy complications | 21 (33.8%) | 62 |
| PIH, Preeclampsia and HELLP | 9 | |
| Gestational diabetes | 1 | |
| Premature rupture of membranes | 3 | |
| Oligo- or poly-hydramnion | 8 | |
| Prenatal fetal growth (ultrasound) | 138 | |
| Normal growth | 39 (28.3%) | |
| Growth restriction | 99 (71.7%) |
In 229 cases (69.8%), the gestational age at delivery was reported. The median gestational age at delivery was 38 weeks, with a range from 18 to 42 weeks. In 44 cases (19.2%), fetuses were born prematurely, between 32 and 37 weeks of gestation. In another 27 cases (11.7%), fetuses were born extremely premature, before 32 weeks of gestation. Termination of pregnancies (TOPs) was not included when analyzing gestational age. Percentages of a term birth, premature birth and extreme premature birth per involved chromosome are shown in Fig. 4.
Figure 4.

Overview of premature births for all chromosomes separately, divided into a term (>37 weeks), premature birth (≥32 and <37 weeks) and extreme premature birth (<32 weeks).
In nine cases, the pregnancy was complicated with hypertension (either pregnancy induced hypertension (PIH) or pre-eclampsia (PE)). Only one case reported gestational diabetes. In six cases, the pregnancies were complicated with an oligohydramnios and another one was complicated with polyhydramnios. In the majority of publications, pregnancy complications were not reported, with missing data in 266 cases.
Only in four out of the 328 cases, was the method of conception mentioned. Two pregnancies were conceived spontaneously: one through intra-uterine insemination (IUI) and one was through intracytoplasmic sperm injection (ICSI).
In 138 cases (42.1%), growth was defined and in 190 cases, prenatal growth was not mentioned. Prenatal fetal growth was measured by ultrasound. The timing of the ultrasound examinations varies between the publications. Of these 138 cases, fetal growth restriction was reported in 99 pregnancies (71.7%). The other 39 pregnancies (28.3%) reported normal growth (Table III).
In total, there were 12 cases reported with intra-uterine fetal death (IUFD), as shown in Table IV. Most cases (n = 8) were CPM trisomy 16. In one case IUFD occurred at 15 weeks of gestational age; this case is worth mentioning because of multiple structural fetal anomalies and growth below the 3rd percentile (Van Opstal et al., 1998).
Table IV.
Intra-uterine fetal deaths (IUFD) with characteristics among cases of confined placental mosaicism. FGR: fetal growth restriction.
| Author | Chrom. | Prenatal growth | Gestational age (weeks) |
|---|---|---|---|
| Nagamatsu et al. (2014) | 2 | FGR | 37 |
| Kuchinka et al. (2001) | 4 | FGR | 30 |
| Webb et al. (1995) | 11 | FGR | 19 |
| Peñaherrera et al. (2008) | 16 | FGR | 24 |
| Kalousek (1993) | 16 | n.a. | 20 |
| Zimmermann (1995) | 16 | FGR | 26 |
| 16 | FGR | 18 | |
| Sánchez et al. (1997) | 16 | FGR | 26 |
| Groli et al. (1996) | 16 | FGR | 27 |
| Van Opstal et al. (1998) | 16 | Normal | 38 |
| 16 | FGR | 33 | |
| 22 | FGR | 15 |
Birth weight
The majority of the cases (n = 300, 91.5%) mentioned the birth weight (percentile). In three articles, the birth weight percentile is only mentioned as above or below 10th percentile (Morssink et al., 1996; Toutain et al., 2010; Toutain et al., 2018). These cases could not be used in the analysis about birth weight below the 5th and 3rd percentile. This explains the different number of cases in all analysis.
Without considering individual chromosomes, 126 cases (42.0%) had a birth weight below the 10th percentile, 90 cases (30.8%) were below the 5th percentile and 64 cases (22.7%) were below the 3rd percentile. Secondly, all percentiles were analyzed per chromosome, to distinguish whether there was a difference in birth weight between the involving chromosomes. In the analysis of birth weight below the 10th percentile (with the most cases involved) eight chromosome (2, 3, 7, 13, 15, 16, 21 and 22) were involved in significantly more cases with a birth weight below the 10th percentiles than expected based on the percentiles. Looking at the threshold of the 5th percentile, eight involved chromosomes show significantly more cases with a low birth weight below the 5th percentile. Compared to the threshold of the 10th percentile, CPM trisomy 21 was no longer significant.
Using the threshold of the 3rd percentile, seven chromosomes had significantly more cases with a birth weight below the 3rd percentile than expected based on the percentiles. The data are shown in Fig. 5. In this cohort, 124 (42.5%) were male fetuses and 168 (57.5%) female, and in 36 cases the gender was not given. No significant difference could be found in low birth weight in relation to gender, as shown in Table V.
Figure 5.
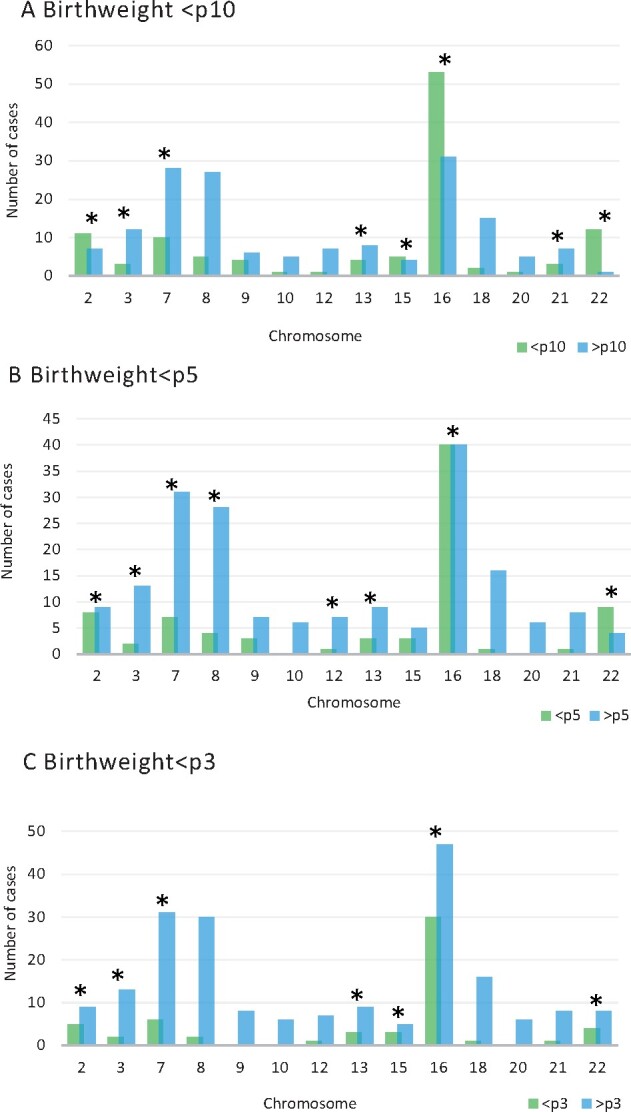
Analyses of low birth weights. (A) Analysis of birth weight below the 10th percentile (<p10). (* <p = 0.05). (B) Analysis of birth weight below the 5th percentile (<p5). (* <p = 0.05). (C) Analysis of birth weight below the 3rd percentile (<p3). (* <p = 0.05).
Table V.
Birth weight percentiles per gender in cases of among cases of confined placental mosaicism.
| Birth weight | Male n (%) | Female n (%) | p |
|---|---|---|---|
| ≤p10 | 53 (47.7%) | 58 (52.3%) | |
| >p10 | 67 (41.9%) | 88 (58.1%) | 0.373 |
|
|
|||
| ≤p5 | 36 (46.2%) | 42 (53.8%) | |
| >p5 | 79 (42.5%) | 107 (57.5%) | 0.582 |
|
|
|||
| ≤p3 | 26 (47.3%) | 29 (52.7%) | |
| >p3 | 86 (43.0%) | 114 (57.0%) | 0.572 |
Structural fetal anomalies
A total of 38 cases had structural fetal anomalies, and the majority were CPM trisomy 16 cases (21 cases). Taking into account that more than half of the cases (56.4%) did not report the presence or absence of structural fetal anomalies, the percentage of structural anomalies is 24.2% (38 of 157 cases) (Table III). Only three of these cases had a birth weight above the 10th percentile. FGR was described in 25 cases, with FGR starting in the first trimester in two cases. In 10 cases, there was no description of fetal growth. There is a wide variety of anomalies: an overview of structural fetal anomalies is shown in Table VI.
Table VI.
All reported structural fetal anomalies amongst CPM cases, with publications reference, involving chromosome, fetal growth and birth weight percentiles.
| Author | Structural anomaly | Chromosome | Fetal growth | Birth weight | |
|---|---|---|---|---|---|
| Toutain (2010) | Enlarged nuchal fold | 2 | n.a. | p50 | |
| Farra et al. (2020) | Microcephaly and bilateral microphtalmia | 2 | n.a. | <p5 | |
| Van Opstal et al. (1998) | Rocker bottom feet, abnormal spine and cardiomegaly | 2 | FGR | TOP at 23w | |
| Kapaya (2012) | Hypospadia and umbilical hernia | 3 | FGR from 17 weeks | p5-10 * | |
| Kunwar et al. (2018) | Hypotonia, torticollis and delayed motoric functioning | 5 | FL <p10 | <p3 | |
| Van Opstal et al. (1998) | Anusatresia, horseshoekidney and abnormal scrotum | 7 | normal | <p3 | |
| Appelman et al. (1991) | Hydronefrosis | 9 | FGR from 23 weeks | p10-50 | |
| Webb et al. (1995) | Hypospadia and intestinal malrotation | 11 | FGR from 19 weeks | n.a. | |
| Robinson et al. (2010) | SUA | 13 | FGR | <p3 | |
| Towner et al. (2001) | Clindactyly bilateral, simian crease and dysmorfic ear | 14 | FGR from 35 weeks | <p3 | |
| Redaelli (2005) | SUA, hypospadia, micropenis and bifid scrotum | 15 | FGR at 20 weeks | <p3 * | |
| Kim (1997) | Complex feet and hand anomaly (both right side) | 15 | FGR from 24 weeks | <p3 * | |
| Astner et al. (1998) | VSD (no surgery needed) | 16 | FGR from 21 weeks | <p3 | |
| Donato et al. (2018) | Unilateral pyelectasy | 16 | EFW <p10 | p5-10 | |
| Sánchez et al. (1997) | SUA, ventriculomegaly, corpus callosum hypoplasia and polyspleny | 16 | EFW <p5 | IUFD 26w (<p5) | |
| Van Opstal et al. (1998) | SUA, ambiguous genital, ASD (type 2), Caudal regression syndrome | 16 | n.a. | <p3 | |
| SUA | 16 | n.a. | <p3 | ||
| Dysmorfic ear | 16 | FGR | <p3 | ||
| Vaughan (1994) | SUA and anorectal malformation | 16 | FGR from 17 weeks | <p3 * | |
| Imperforate anus, large immature ears, simian crease left hand | 16 | FGR from 21 weeks | TOP at 24w | ||
| Post and Nijhuis (1992) | SUA | 16 | FGR from 31 weeks | p10-50 | |
| Woo et al. (1997) | Left renal agenesis and talipes equinovarus unilateral | 16 | normal | p10-50 | |
| Peñaherrera et al. (2008) | ASD | 16 | n.a. | <p3 * | |
| Kennerknecht and Terinde (1990) | Hypospadia | 16 | n.a. | p3-5 | |
| Grau Madsen et al. (2018) | Enlarged nuchal fold and cleft lip and palate | 16 | n.a. | TOP at 15w | |
| SUA and anhydramnion | 16 | n.a. | TOP at 18w | ||
| ASD, VSD and small brain cyst | 16 | FGR | <p3 | ||
| ASD, bilateral congenital coloboma | 16 | n.a. | p5-10 | ||
| ASD | 16 | FGR from 20 weeks | p3-5 | ||
| AVSD | 16 | FGR | TOP at 20w | ||
| Van Opstal et al. (1998) | Facial dysmorfity, ASD and VSD, hypoplastic truncus pulmonalis and atresia of the valve. Two Left pulmonary lobes and one on the right side | 16 | FGR | IUFD at 33w (<p3) | |
| Van Opstal et al. (1998) | Complete AVSD | 16 | n.a. | p5-10 | |
| Soong et al. (2009) | Enlarged nuchal fold | 16 | FGR | TOP at 21 w (<p5) | |
| Peñaherrera et al. (2008) | Rocker bottom feet, ASD and VSD, aortic stenosis and contractures in elbow and knees | 22 | FGR from 11 weeks | n.a. | |
| Van Opstal et al. (1998) | Facial dysmorfity, intestinal malrotation, asplenia and ASD | 22 | FGR | <p3 (IUFD at 15w) | |
| Balmer et al. (1999) | Hypospadia | 22 | FGR from 12 weeks | <p3 | |
| Piantelli et al. (2009) | Clinodactyly and facial dysformity α | 22 | normal | p5 | |
| Bryan et al. (2002) | Hypospadia | 22 | FGR from 18 weeks | <p3 |
Died within 1 month after birth. α Structural fetal anomalies were found postnatally.
TOP, termination of pregnancy; FGR, fetal growth restriction; FL, femur length; SUA, single umbilical artery; VSD, ventricular septal defect; EFW, estimated fetal weight; ASD, atrial septal defect; IUFD, intra uterine fetal death; AVSD, atrial ventricular septal defect; n.a., not available.
CPM involving trisomy 16
Of the reported cases, 100 cases were CPM involving chromosome 16. Due to this significant number of cases, we decided to analyze this subgroup separately. All characteristics of this subgroup are shown in Table VII.
Table VII.
Characteristics of CPM involving chromosome 16.
| Characteristic | Analyzed cases (n) | |
|---|---|---|
| GA at birth in weeks (median, ICR) | 36 (30-38) | 77 |
| Female fetuses | 56 (68.3%) | 82 |
| FGR (on ultrasound) | 53 (81.5%) | 65 |
| Extreme premature birth (<32 wks) | 20 (25.9%) | 77 |
| Premature birth (<37wks) | 23 (29.9%) | 77 |
| Birth weight ≤p10 | 53 (63.1%) | 84 |
| Birth weight ≤p5 | 40 (50.0%) | 80 |
| Birth weight ≤p3 | 30 (38.9%) | 77 |
| IUFD | 8 (8.0%) | 100 |
| TOP | 12 (12.0%) | 100 |
| Post-natal death | 4 (4.0%) | 100 |
| Structural fetal anomalies | 21 (21.0%) | 100 |
| Maternal hypertension | 7 (7.0%) | 100 |
GA, gestational age; FGR, fetal growth restriction; IUFD, intra uterine fetal death; TOP, termination of pregnancy.
Gestational age at birth was lower in the trisomy 16 group compared to the total group (all 319), respectively 36 weeks and to 38 weeks. The majority (68.3%) of the CPM 16 group was female and 21% (21 cases) had structural fetal anomalies. Four cases (4%) of postnatal death were reported, two cases eight days after birth, one case four weeks after birth and one case after a month.
Termination of pregnancy
In 15 cases, the parents opted for termination of pregnancy after diagnosis of CPM. The majority of the pregnancies (n = 12) were complicated not only with CPM but also with FGR. In 6 cases, structural fetal anomalies were reported. One pregnancy was complicated with premature rupture of membranes (PROM) and FGR (on the 5th percentile) at 21 weeks of gestation and only after birth post mortem examination revealed multiple structural fetal anomalies (Vaughan et al., 1994).
Four pregnancies were terminated because of structural fetal anomalies (Grau Madsen et al., 2018; Van Opstal et al., 2018). Only one pregnancy was terminated due to maternal hypertension and at postmortem examination, the fetus was found to have growth restriction but no structural fetal anomaly (Kalousek, 1993). The majority of the terminations were CPM trisomy 16: all TOPs are shown in Table VIII.
Table VIII.
All terminations of pregnancies.
| Author | Ref | Chromosome | Gender | Fetal growth | Structural fetal anomalies | Gestational age (weeks+days) |
|---|---|---|---|---|---|---|
| Kalousek (1993) | 16 | n.a. | normal | None | 25 | |
| Vaughan (1994) | 16 | female | FGR from 21 weeks | Imperforate anus, large immature ears and Simian crease left hand | 24 | |
| Ariel et al. (1997) | 2 | female | FGR from 20 weeks | None | 27 | |
| Gibbons et al. (1997) | 2 | male | FGR from 12 weeks | None | 19 | |
| Soong et al. (2009) | 16 | female | FGR | Enlarged nuchal fold | 21 | |
| Wang et al. (2017) | 16 | female | FGR from 21 weeks | None | 23 | |
| Grau Madsen et al. (2018) | 16 | female | FGR | AVSD | 20 + 5 | |
| 16 | female | FGR | None | 18 + 4 | ||
| 16 | female | n.a. | SUA and anhydramnion | 18 + 3 | ||
| 16 | female | n.a. | Enlarged nuchal fold and cleft lip and palate | 15 + 1 | ||
| Van Opstal et al. (1998) | 2 | n.a. | FGR | Rocker bottom feet, abnormal spine and cardiomegaly | 23 | |
| Wang et al. (2018) | 16 | n.a. | FGR from 19 weeks | n.a. | 19 | |
| (Li and He, 2019) | 16 | n.a. | FGR from 16 weeks | n.a. | 24 | |
| Wan et al. (2019) | 16 | female | FGR from 21 weeks | n.a. | 24 | |
| Donato (2018) | 16 | female | FGR from 16 weeks | None | 19 |
n.a., not available; AVSD, atrial ventricular septal defect; SUA, single umbilical artery.
CPM cases compared to normal controls
Three publications compared a group of CPM cases with a control group. The first article compared 26 CPM cases with 52 matched controls (Roland et al., 1994). In this retrospective cohort, there was no difference in birth weight, controls and gestational age at delivery between CPM affected and control pregnancies.
The second article was performed postnatally, when growth restricted new-borns were compared to a normal weight control group (Wilkins-Haug et al., 2006). CPM occurred significantly more often in the placentas of growth restricted newborns compared to the control group. Both groups consisted of 70 placentas: 11 CPMs were found in the growth restricted group compared to only one in the control group (p = 0.008). No difference could be found between symmetrical and asymmetrical growth restriction. Furthermore, the gestational age at delivery did not differ significantly between the groups.
The last and most recent article compared a CPM group versus a control group (Grati et al., 2020). If only considering trisomy 16 (11 cases) confined to the placenta, there was a strong association with increased incidence of birth weight below the 3rd percentile (OR 11.2), and preterm delivery (OR 10.2). All other trisomies did not show these associations.
One publication chose not to report all cases separately and made a summary (Sifakis et al., 2010). A total of 43 pregnancies showed trisomy 2 after CVS, with no signs of trisomy after follow-up by amniocentesis. In six neonates (13.9%), the birth weight was below the 5th percentile. In one case, fetal death reported at 15 weeks of gestation. This publication also found a significant association between the birth weight percentile and the percentage of trisomic cells in the CVS (p = 0.010).
Follow-up
In 26 cases, follow-up was available and the majority reported normal fetal (catch-up) growth. In eight of the 26 cases, post-neonatal death occurred and five of these are also mentioned in Table VI (marked with a *) because of structural fetal anomalies in the fetus (Vaughan et al., 1994; Kim et al., 1997; Peñaherrera et al., 2008; Redaelli et al., 2005; Kapaya et al., 2012; Grau Madsen et al., 2018). All cases had a birth weight below the 10th percentile, with seven cases even below the 3rd. Chromosome 16 was the involved chromosome in 4 cases, two cases had trisomy 15, one case had trisomy 2 and another cases had chromosome 3. Timing of death ranged from 1.5 hours after birth to 10 months.
Discussion
CPM is associated with negative developmental outcomes
First we like to address the complexity of establishing this review. We reviewed publications from 1983 until 2020, a period of over 30 years. The change in diagnostic genetic tests and the growing possibilities and intensity of measuring fetal growth and wellbeing has been enormous. Ultrasound machines have improved significantly and as have education and standardization in ultrasound examination practice during the last decade. Our purpose was to use all information available in our review in order to get the best possible impression of the association of CPM on pregnancy outcome. As a consequence of using these different sources and data, the result section is rather extensive. We have chosen not to simplify or generalize the data. We acknowledge that publication bias is inevitable in a literature review, as more severe or complicated cases are prone to be published. A prospective cohort analysis would give more insight, but we found these to be currently unavailable.
The aim of this review was to explore the available literature about the effect of CPM on prenatal fetal growth. Unfortunately, the majority of the publications did not report the prenatal fetal growth. This can be explained by the more (cyto)genetic orientation of most publications. Most of the publications focused on the diagnostic workup and only reported pregnancy outcome (livebirth versus termination). As a result of our focus on prenatal fetal growth and birth weight, we have to take into account a possible bias on secondary outcomes, such as structural fetal anomalies.
The general picture shows us that CPM is a high risk condition when chromosomes 2, 3, 7, 13, 15, 16 or 22 are involved. In addition, pregnancies affected by CPM involving any of the autosomal chromosomes showed prenatal FGR in 71.7% of our cohort. In 22.7% the birth weight was below the 3rd percentile and 42% had a birth weight below the 10th. Percentiles are based on appropriate population standards and provide a more reliable measure of fetal growth (Villar et al., 2014). CPM forms a major contributor to FGR. Other factors known to be associated with a higher incidence of FGR, such as smoking and systemic lupus erythematosus, cause a lower percentage of cases with low birth weight (11% and 12.7%, respectively) (Smyth et al., 2010; Blatt et al., 2015). Besides the high rate of FGR, we found a high rate of (sometimes extreme) premature birth as well. Almost 20% of pregnancies with CPM that we identified here ended with premature birth and almost another 12% ended in very premature birth. Although the prevalence of premature birth differs between continents, our percentage is remarkable higher than the estimated global preterm birth rate of 10.6% by the World Health Organization (WHO) (Chawanpaiboon et al., 2019). The survival rates of premature born babies have greatly increased, but these infants remain at risk of developing a variety of complications (Saigal and Doyle, 2008). In the postnatal period, prematurity leads to higher rates of temperature instability, respiratory distress, apnea, hypoglycemia and seizures. Even if the postnatal period is survived, risks remain for these premature infants. Preterm birth has been associated with poorer neurodevelopmental outcomes, higher rates of hospital admissions, as well as behavioral, social-emotional and learning difficulties in childhood (Vogel et al., 2018). Besides the physical consequences, there is also a psychological and financial burden for the families of premature new-borns.
Different strategies have been proposed in literature to identify high risk CPM pregnancies based on the presence of UPD, level of mosaicism or the type of CPM (type 1, 2 or 3). Only the first two, UPD and level of mosaicism, were analyzed in this review. Significant differences were found when comparing UPD cases with non-UPD. In cases with UPD, we found more premature deliveries and higher rates of birthweight below the 3rd, 5th and 10th percentiles. Therefore we suggest to analyze UPD in case of CPM, especially in case of CPM involving chromosome 16. In our artificial cohort, we found an association between the level of mosaicism in the CVS and adverse pregnancy outcomes. Higher levels of mosaicism were significantly associated with higher rates of premature births (p = 0.001), FGR (p = 0.003) and higher rates of birthweight below the 3rd, 5th and 10th percentile. The level of mosaicism can be a relative accessible strategy to identify the pregnancies with a higher risk of adverse pregnancy outcomes.
It is remarkable that this review shows a high rate of structural fetal anomalies (24.2%) in cases where placenta and fetal tissues were analyzed and the results indicated that the abnormal cell line was confined to the placenta. This is in contrast to other studies that found no significant difference between CPM and a control group (Amor et al., 2006). The higher incidence we found could also be explained by publication bias, because CPM affected pregnancies with structural fetal anomalies draw more attention. Secondly, there is always the chance that the percentage of mosaicism is very low in the fetus and that genetic testing does not reveal the fetal mosaicism. The higher incidence of structural fetal anomalies could also be explained by an unidentified fetal chromosomal mosaicism. Prospective research should be performed to understand this higher incidence of fetal anomalies in CPM affected pregnancies. Nevertheless, this cohort showed a higher rate compared to the general population. In the general population, structural fetal anomalies occur in approximately 2–4% of livebirths (Marden et al., 1964; Holmes, 1976; Leppig et al., 1987). Therefore, we can conclude that CPM pregnancies are at higher risk of structural fetal anomalies. It is advised to thoroughly examine CPM pregnancies for structural fetal anomalies with advanced ultrasound (Salomon et al., 2011).
In our cohort, six cases of hypospadias were reported and five of these pregnancies were also complicated with FGR. The relation between hypospadias and FGR is well known. A large North American study published data with more than 300 hypospadia cases (Toufaily et al., 2018). A higher rate of hypospadias is found in pregnancies complicated with intrauterine growth restriction, defined as a birth weight below the 10th percentile, than in fetuses with a normal birth weight. It is not clear whether hypospadias has an association with CPM or whether it forms a complex with FGR. Besides the known relation, hypospadias is a common congenital malformation, but a true prevalence is difficult to estimate (Springer et al., 2016).
Trisomy 16 is the most published and analyzed CPM and is often associated with adverse pregnancy outcomes. As a result of the high number (n = 100) of reported cases, we made a subgroup analysis of CPM 16. Pregnancies affected by CPM trisomy 16 showed FGR in 81.5% of cases, compared to 71.7% in the overall cohort. In the subgroup analysis, the percentages of birth weight below the 3rd percentile (5th and 10th) were also higher compared to the overall group, 38.9% versus 23.4%. Not only did we find a high rate of FGR and high percentages of low birth weight, we also found a higher number of structural fetal anomalies in case of CPM trisomy 16. Taking into account the total of 100 cases of CPM trisomy 16, more than 20% had structural fetal anomalies. Eight fetuses presented with cardiac anomalies, five of which were isolated, and three were in combination with other anomalies. Nine pregnancies were complicated with multiple structural fetal anomalies. These findings are in line with observations on CPM trisomy 16 in earlier literature (Neiswanger et al., 2006; Grau Madsen et al., 2018; Grati et al., 2020). On a critical note, although trisomy 16 is the most published, CPM trisomy 16 is not representative for all pregnancies affected with CPM. We found that the associations and relevance for each chromosome to be different.
The chromosomes found to be involved in CPM are not random. In our search, we did not find a CPM case of trisomy 1 or 19, while nearly a third were caused by trisomy 16. In preimplantation embryos at the 8-cell stage, it was observed in an extensive set of embryo biopsy samples that especially the larger chromosomes were more susceptible to post-zygotic errors (McCoy et al., 2015). In order to explain this difference, we looked at which chromosomes were found in spontaneous abortion materials. Multiple studies have investigated the chromosomal cause of spontaneous abortions (Boue and Boue, 1974; Boue et al., 1975; van den Berg et al., 2012; Pylyp et al., 2018). Trisomy is found in almost 60% of all miscarriages caused by chromosomal defects (Pylyp et al., 2018). Trisomy 16 is found to be a major contributor to miscarriage and more than 18% of all trisomies involve chromosome 16. However, it was recently described by extended culture of preimplantation embryos diagnosed by PGT-A with trisomy 16, that these embryos show hypoproliferation of the throphoblast compartment, but no overt changes in epiblast morphology (Shahbazi et al., 2020). It is possible that an extra chromosome 16 confers a growth advantage towards the placenta, initially facilitating implantation and further development. An explanation of the absence of trisomy 1 and 19 could be that these two type of trisomies are not compatible with cell viability. Only four published cases could be found of trisomy 1, and all ended in early miscarriage (Watt et al., 1987; Hanna et al., 1997; Dunn et al., 2001; Banzai et al., 2004) Only one article could be found on trisomy 19 (Babic et al., 2007). The fetus had multiple congenital malformations and the parents choose to terminate the pregnancy at 19 weeks of gestation.
The predominance of females (57.5% female versus 42.5% male) in this artificial cohort has been reported in other series (Benn, 1998; Yong et al., 2006; Sparks et al., 2016). In these publications, the difference is explained through two mechanisms. A higher rate of early miscarriage among male fetuses and secondly due to a higher rate of trisomic rescue among female fetuses. Nevertheless, in this review we could not demonstrate a significant difference in birth weight percentiles between the genders.
Only one publication tried to unravel the mechanism of how CPM is causing adverse pregnancy outcomes (Wilkins-Haug et al., 2006). Two groups of placentas were histologically compared: CPM and chromosomally normal placentas and all of FGR newborns. The proportion of placental infarcts and decidual vasculopathy nearly doubled in cases of CPM (p = 0.02). No reason was (yet) found for why these vascular alterations are more prevalent in CPM placentas. A possible explanation could be that such chromosome abnormalities could impair the local placental functions.
We did not select for literature on long-term outcomes, but there is literature about the neonatal outcomes and long-term follow-up, although with very limited numbers. An analysis of 12 cases CPM with trisomy 16 affected pregnancies reported multiple adverse pregnancy outcomes (Sparks et al., 2016). Preterm delivery was observed in nine pregnancies (75%), birth weight below 10th percentile in eight cases (66.7%) and congenital anomalies were present in four (33.3%) of the cases. Considering all mosaicisms in this article (CPM and generalized mosaicism), the majority (27 pregnancies of the total 33 pregnancies, 81.8%) of the children demonstrated normal neurodevelopmental outcomes at school. Another retrospective study also found no association between CPM and developmental problems after birth (Amor et al., 2006). This might suggest that closely monitoring these pregnancies may help in risk stratification and result in positive neonatal outcomes.
Clinical implications for obstetric care
With the results found by this review, we can make recommendations for clinicians, but this review also addresses the need for further research. Not only does NIPT draw fresh attention to CPM, due to the fact that CPM is the major origin of incidental findings (i.e. discordant results) of NIPT, it also appears to be a more sensitive test for CPM compared to CVS (Van Opstal et al., 2020). When CPM is suspected, the pregnancy should be identified as a high-risk pregnancy, certainly in cases where trisomy 2, 3, 7, 13, 15, 16 or 22 are involved. In case of CPM with chromosome 21 and 8, caution is also advised. We found that these pregnancies are at higher risk of FGR, so we advise to monitor the growth from the first trimester and throughout the rest of the pregnancy. Besides growth monitoring, we advise to examine the fetuses thoroughly for structural fetal anomalies. Counselling of future parents should include the message that there is a higher incidence of (extreme) premature birth, structural fetal anomalies, fetal growth restriction and low birth weight. The risk for these adverse outcomes is even more distinct in case of CPM trisomy 16.
On the other hand, in case of CPM involving trisomy for chromosomes 9, 10, 12, 18 and 20, there is no indication of adverse pregnancy outcomes. In our cohort, we found no information about chromosomes 1 and 19, meaning that they either are very rare or that these pregnancies develop normally.
Clinical implications for PGT-A
Clinical management of mosaicism detected in a PGT-A program is complicated. The finding of mosaicism could be the result of a technical artifact or the biopsied sample being poorly predictive of the remaining embryo, so that the embryo is in fact either euploid or aneuploid (Marin et al., 2020). Indications also suggest that mosaic embryos can self-correct, through the growth advantages of normal cells and/or elimination of abnormal cells, as recently demonstrated in a model for mosaicism in mouse embryos (Santos et al., 2010; Bolton et al., 2016; Zhou et al., 2019). The fate of these chemically induced aneuploid cells was shown to depend on the embryonic lineage: aneuploid cells in the fetal lineage (ICM) are actively eliminated by apoptosis, whereas those in the placental lineage (TE) show severe proliferative defects. In addition, it was shown in post-implantation mouse embryos that aneuploid cells are most effectively eliminated in the developing epiblast compartment, where chromosomally normal cells subsequently compensate for this loss by increased proliferation (Singla et al., 2020). So in the mouse, aneuploid cells appear to be enriched in the trophoblast lineage compared to the embryo proper. However, in these studies the mosaicism was induced experimentally in animal models and this does not necessarily display real-life mechanisms in human implantation.
Still, there is evidence that the proportion of aneuploid cells decreases after extended culture of mosaic human embryos through the peri-implantation stages (Santos et al., 2010) (Popovic et al., 2020). Also, single cell analysis of human embryos at different stages of developmental showed that, at the blastocyst stage, aneuploid cells are distributed evenly between TE and ICM. In contrast, after in-vitro culture to the post-implantation stage, aneuploidy is more frequently detected in the extra-embryonic trophoblast compartment (Starostik et al., 2020). The fact that the presence of all autosomal trisomies have been described in the placental tissues, support this notion that they may have a higher tolerance for cells with aneuploidy. Therefore, it is feasible that this self-correction is reduced in the placental tissue, potentially leading to CPM.
Still, so far there is no evidence that CPM is more prevalent or is causing more adverse perinatal outcomes in IVF pregnancies compared with natural conceptions (Jacod et al., 2008; Huang et al., 2009). Only one case report was published, at the time of writing this review, of a known mosaic embryo transfer involving monosomy 2 with a confirmed true fetal mosaicism in the karyotype of the resulting baby (Kahraman et al., 2020). At 37 weeks of gestation, a healthy baby was born with a normal birthweight (50th percentile). Recent studies have investigated the association between the level of mosaicism detected after PGT-A and miscarriage and live birth rates (LBR) after transfer (Capablo et al., 2020). A comparison was made between low grade (20–30%) and moderate grade mosaicism (30–50%). They stated that exclusion of transfer of mosaic embryos above the 20% variability results in a relative reduction in live birth rates, suggesting that these embryos with a low grade mosaicism are safe for transfer. Unfortunately no data were given on adverse pregnancy outcomes such as fetal growth or structural anomalies.
The specific chromosome involved in the abnormality is also likely to have a significant impact on the fate of the embryo, as each chromosome may impact differently on cell proliferation (Pfau et al., 2016). There is an ongoing debate about which mosaic embryos could be prioritized for transfer depending on the abnormality involved (Popovic et al., 2020). The Preimplantation Genetic Diagnosis International Society (PGDIS) and the Controversies in Preconception, Preimplantation and Prenatal Genetics (CoGen) have developed guidelines to aid the selection of mosaic embryos for transfer, based on the level of mosaicism and the specific chromosome involved (Gleicher et al., 2020). The first consideration is for deselecting mosaic embryos for transfer concerns aneuploidies that may lead to a viable affected birth (chromosomes 13, 18, 21). The second concern is for aneuploidies associated with intrauterine growth restriction (chromosomes 2, 7, 16). The last recommendation is avoiding those that may be associated with uniparental disomy syndromes (chromosomes 14, 15). Embryos with mosaicism involving trisomies for chromosome 1, 3, 4, 5, 6, 8, 9, 10, 11, 12, 17, 19 and 20 were considered save for transfer as they have not previously been associated with adverse outcomes. A recent paper has nuanced these findings and only considers mosaic trisomies 1, 3, 10, 12 and 19 as low risk (Grati et al., 2018). Based on our findings, we would also apply caution for embryos that are mosaic for trisomy 3. However, should an association with low birth weight be reason for entirely avoiding an embryo mosaic for this or other trisomies for transfer? What if there are no mosaic-free embryos available? Further research is needed to answer these questions. However, if no diploid embryos are available for transfer, patients should be informed on the potential risks based on the chromosome involved and NIPT would be recommended if a pregnancy is established.
Conclusion
CPM affected pregnancies, certainly in case of trisomy 2, 3, 7, 13, 15, 16 and 22, are associated with fetal growth restriction, preterm birth, low birth weight and fetal structural anomalies. Counselling future parents should include informing them of a higher risk for (possibly extreme) premature birth, structural fetal anomalies, FGR and low birth weight. All these adverse outcomes are even more pronounced in case of CPM trisomy 16.
Recommendations
When the decision to transfer a mosaic embryo (diagnosed after PGT-A) is made, we recommend to offer NIPT to the future parents. When a trisomy is found, further invasive prenatal genetic testing is recommended to distinguish between CPM, fetal mosaicism or generalized mosaicism.
When a pregnancy is affected with CPM, we advise to closely monitor the fetal growth (from the first trimester on) and examine for fetal structural anomalies. Clinicians should be aware (and should counsel future parents) of the risks of adverse pregnancy outcomes, such as premature birth and low birth weight.
Supplementary data
Supplementary data are available at Human Reproduction Update online.
Data availability
The data that support the findings of our conclusions are available from the corresponding author upon reasonable request.
Supplementary Material
Acknowledgements
We would like to thank Wichor M. Bramer and Sabrina Meertens-Gunput (both are Biomedical Information Specialist of Erasmus MC) for their assistance in performing the systematic search (and updates) and removing the duplicate papers during the review process.
Authors’ roles
G.E., A.G. and R.G. were involved in the execution and drafting of this review. G.E. and E.B were responsible for the writing. G.E. and M.K. were involved in the design and analysis of this review. All authors approved the final version of the article.
Funding
No specific funding was sought for the study, and departmental funds were used to support the authors throughout the study period and manuscript preparation: the Department of Obstetrics and Gynaecology and the Department of Clinical Genetics, both from the Erasmus MC University Medical Center, Rotterdam, The Netherlands.
Conflict of interest
The authors declare that there is no conflict of interest.
References
- Akera T, Lampson MA.. Chromosome segregation: poor supervision in the early stage of life. Curr Biol 2019;29:R156–R158. [DOI] [PubMed] [Google Scholar]
- Amor DJ, Neo WT, Waters E, Heussler H, Pertile M, Halliday J.. Health and developmental outcome of children following prenatal diagnosis of confined placental mosaicism. Prenat Diagn 2006;26:443–448. [DOI] [PubMed] [Google Scholar]
- AppelmanZ, , RosensaftJ, , ChemkeJ, , CaspiB, , AshkenaziM, , Mogilner MB.. Trisomy 9 confined to the placenta: prenatal diagnosis and neonatal follow-up. Am J Med Genet 1991;40:464–466. [DOI] [PubMed] [Google Scholar]
- Ariel I, Lerer I, Yagel S, Cohen R, Ben-Neriah Z, Abeliovich D.. Trisomy 2: confined placental mosaicism in a fetus with intrauterine growth retardation. Prenat Diagn 1997;17:180–183. [DOI] [PubMed] [Google Scholar]
- AstnerA, , SchwingerE, , CaliebeA, , JonatW, , Gembruch U.. Sonographically detected fetal and placental abnormalities associated with trisomy 16 confined to the placenta. A case report and review of the literature. Prenatal Diagnosis 1998;18:1308–1315. [PubMed] [Google Scholar]
- Baart EB, Martini E, van den Berg I, Macklon NS, Galjaard RJ, Fauser BC, Van Opstal D.. Preimplantation genetic screening reveals a high incidence of aneuploidy and mosaicism in embryos from young women undergoing IVF. Hum Reprod 2006;21:223–233. [DOI] [PubMed] [Google Scholar]
- Babic I, Brajenovic-Milic B, Petrovic O, Mustac E, Kapovic M.. Prenatal diagnosis of complete trisomy 19q. Prenat Diagn 2007;27:644–647. [DOI] [PubMed] [Google Scholar]
- Balmer D, Baumer A, Röthlisberger B, Schinzel A.. Severe intra-uterine growth retardation in a patient with maternal uniparental disomy 22 and a 22-trisomic placenta. Prenat Diagn 1999;19:1061–1064. [DOI] [PubMed] [Google Scholar]
- Banzai M, Sato S, Matsuda H, Kanasugi H.. Trisomy 1 in a case of a missed abortion. J Hum Genet 2004;49:396–397. [DOI] [PubMed] [Google Scholar]
- Benn P.Trisomy 16 and trisomy 16 mosaicism: A review. Am J Med Genet 1998;79:121–133. [PubMed] [Google Scholar]
- Bennett P, Vaughan J, Henderson D, Loughna S, Moore G.. Association between confined placental trisomy, fetal uniparental disomy, and early intrauterine growth retardation [1]. Lancet 1992;340:1284–1285. [DOI] [PubMed] [Google Scholar]
- Blatt K, Moore E, Chen A, Van Hook J, DeFranco EA.. Association of reported trimester-specific smoking cessation with fetal growth restriction. Obstet Gynecol 2015;125:1452–1459. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Bolton H, Graham SJL, Van der Aa N, Kumar P, Theunis K, Fernandez Gallardo E, Voet T, Zernicka-Goetz M.. Mouse model of chromosome mosaicism reveals lineage-specific depletion of aneuploid cells and normal developmental potential. Nat Commun 2016;7:11165. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Boue A, Boue J.. Chromosome abnormalities and abortion Review. Basic Life Sci 1974;4:317–339. [DOI] [PubMed] [Google Scholar]
- Boue J, Bou A, Lazar P.. Retrospective and prospective epidemiological studies of 1500 karyotyped spontaneous human abortions. Teratology 1975;12:11–26. [DOI] [PubMed] [Google Scholar]
- Brison N, Neofytou M, Dehaspe L, Bayindir B, Van Den Bogaert K, Dardour L, Peeters H, Van Esch H, Van Buggenhout G, Vogels A. et al. Predicting fetoplacental chromosomal mosaicism during non-invasive prenatal testing. Prenat Diagn 2018;38:258–266. [DOI] [PubMed] [Google Scholar]
- BryanJ, , PetersM, , PritchardG, , HealeyS, , Payton D.. A second case of intrauterine growth retardation and primary hypospadias associated with a trisomy 22 placenta but with biparental inheritance of chromosome 22 in the fetus. Prenat Diagn 2002;22:137–140. [DOI] [PubMed] [Google Scholar]
- Capalbo A, Rienzi L.. Mosaicism between trophectoderm and inner cell mass. Fertil Steril 2017;107:1098–1106. [DOI] [PubMed] [Google Scholar]
- Chawanpaiboon S, Vogel JP, Moller AB, Lumbiganon P, Petzold M, Hogan D, Landoulsi S, Jampathong N, Kongwattanakul K, Laopaiboon M. et al. Global, regional, and national estimates of levels of preterm birth in 2014: a systematic review and modelling analysis. Lancet Glob Health 2019;7:e37–e46. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Donato XC, Brechard MP, François-Renard P, Hairion D, Quarello E, Hoffet M, Katsogiannou M, Desbriere R.. Pregnancy course and outcomes in mosaic trisomy 16 confined to the placenta: A case series. Prenat Diagn 2018;38:924–927. [DOI] [PubMed] [Google Scholar]
- Dunn TM, Grunfeld L, Kardon NB.. Trisomy 1 in a clinically recognized IVF pregnancy. Am J Med Genet 2001;99:152–153. [DOI] [PubMed] [Google Scholar]
- Farra C, Giudicelli B, Pellissier MC, Philip N, Piquet C.. Fetoplacental chromosomal discrepancy. Prenat Diagn 2020;20:190–193. [PubMed] [Google Scholar]
- Fragouli E, Alfarawati S, Spath K, Babariya D, Tarozzi N, Borini A, Wells D.. Analysis of implantation and ongoing pregnancy rates following the transfer of mosaic diploid-aneuploid blastocysts. Hum Genet 2017;136:805–819. [DOI] [PubMed] [Google Scholar]
- Fragouli E, Munne S, Wells D.. The cytogenetic constitution of human blastocysts: insights from comprehensive chromosome screening strategies. Hum Reprod Update 2019;25:15–33. [DOI] [PubMed] [Google Scholar]
- Ghi TA, Sotiriadis P, Calda F, Da Silva Costa N, Raine-Fenning Z, Alfirevic G, McGillivray O, International Society of Ultrasound in and Gynecology ISUOG Practice Guidelines: invasive procedures for prenatal diagnosis. Ultrasound Obstet Gynecol 2016;48:256–268. [DOI] [PubMed] [Google Scholar]
- Gibas LM, Grujic S, Barr MA, Jackson LG.. A simple technique for obtaining high quality chromosome preparations from chorionic villus samples using FdU synchronization. Prenat Diagn 1987;7:323–327. [DOI] [PubMed] [Google Scholar]
- Gibbons B, Cheng HH, Yoong AK, Brown S.. Confined placental mosaicism for trisomy 2 with intrauterine growth retardation and severe oligohydramnios in the absence of uniparental disomy in the fetus. Prenat Diagn 1997;17:689–90. [PubMed] [Google Scholar]
- Gleicher N, Albertini DF, Barad DH, Homer H, Modi D, Murtinger M, Patrizio P, Orvieto R, Takahashi S, Weghofer A, for the International Do No Harm Group in IVF (IDNHG-IVF) et al. International Do No Harm Group in (2020). The 2019 PGDIS position statement on transfer of mosaic embryos within a context of new information on PGT-A. Reprod Biol Endocrinol 2020;18:57. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Goldberg JD, Wohlferd MM.. Incidence and Outcome of Chromosomal Mosaicism Found at the Time of Chorionic Villus Sampling. Elsevier, 1997. [DOI] [PubMed] [Google Scholar]
- Grati FR, Ferreira J, Benn P, Izzi C, Verdi F, Vercellotti E, Dalpiaz C, D’Ajello P, Filippi E, Volpe N. et al. Outcomes in pregnancies with a confined placental mosaicism and implications for prenatal screening using cell-free DNA. Genet Med 2020;22:309–316. [DOI] [PubMed] [Google Scholar]
- Grati FR, Gallazzi G, Branca L, Maggi F, Simoni G, Yaron Y.. An evidence-based scoring system for prioritizing mosaic aneuploid embryos following preimplantation genetic screening. Reprod Biomed Online 2018;36:442–449. [DOI] [PubMed] [Google Scholar]
- Grau Madsen SN, Uldbjerg L, Sunde N, Becher G, Danish Fetal Medicine Study and G. Danish Clinical Genetics Study (2018). Prognosis for pregnancies with trisomy 16 confined to the placenta: a Danish cohort study. [DOI] [PubMed]
- Groli C, Cerri V, Tarantini M, Bellotti D, Jacobello C, Gianello R, Zanini R, Lancetti S, Zaglio S.. Maternal serum screening and trisomy 16 confined to the placenta. Prenat Diagn 1996;16:685–689. [DOI] [PubMed] [Google Scholar]
- Gruhn JR, Zielinska AP, Shukla V, Blanshard R, Capalbo A, Cimadomo D, Nikiforov D, Chan AC, Newnham LJ, Vogel I. et al. Chromosome errors in human eggs shape natural fertility over reproductive life span. Science 2019;365:1466–1469. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Hanna JS, Shires P, Matile G.. Trisomy 1 in a clinically recognized pregnancy. Am J Med Genet 1997;68:98–98. [PubMed] [Google Scholar]
- Holmes LB.Current concepts in genetics. Congenital malformations. N Engl J Med 1976;295:204–207. [DOI] [PubMed] [Google Scholar]
- Hook EB.Prevalence of chromosome abnormalities during human gestation and implications for studies of environmental mutagens. Lancet 1981;318:169–172. [DOI] [PubMed] [Google Scholar]
- Huang A, Adusumalli J, Patel S, Liem J, Williams IJ.. Prevalence of chromosomal mosaicism in pregnancies from couples with infertility. Fertility and Sterility. Elsevier, 2009. [DOI] [PubMed] [Google Scholar]
- Jacod BC, Lichtenbelt KD, Schuring-Blom GH, Laven JSE, van Opstal D, Eijkemans MJC, Macklon NS, on behalf of the IVF-CPM Study Group. Does confined placental mosaicism account for adverse perinatal outcomes in IVF pregnancies? Hum Reprod 2008;23:1107–1112. [DOI] [PubMed] [Google Scholar]
- Jelin AC, Sagaser KG, Wilkins-Haug L.. Prenatal Genetic Testing Options. Pediatr Clin North Am 2019;66:281–293. [DOI] [PubMed] [Google Scholar]
- Kahraman S, Cetinkaya M, Yuksel B, Yesil M, Cetinkaya CP.. The birth of a baby with mosaicism resulting from a known mosaic embryo transfer: a case report. Hum Reprod 2020;35:727–733. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Kalousek DK. (1993). The effect of confined placental mosaicism on development of the human aneuploid conceptus. Birth defects original article series. [PubMed]
- Kalousek DK.Pathogenesis of chromosomal mosaicism and its effect on early human development. Am J Med Genet 2000;91:39–45. [DOI] [PubMed] [Google Scholar]
- Kalousek DK, Dill FJ.. Chromosomal mosaicism confined to the placenta in human conceptions. Science 1983;221:665–667. [DOI] [PubMed] [Google Scholar]
- Kapaya H, Ikhena SE, Brookman MJN.. Trisomy 3 confined placental mosaicism: A management dilemma. J Obstet Gynaecol 2012;32:696–698. [DOI] [PubMed] [Google Scholar]
- KennerknechtI, , Terinde R.. Intrauterine growth retardation associated with chromosomal aneuploidy confined to the placenta. Three observations: triple trisomy 6,21,22; trisomy 16; and trisomy 18. Prenat Diagn 1990;10:539–544. [DOI] [PubMed] [Google Scholar]
- Kim ES, Ryu HM, Yang JH, Kim MY, Park SY, Choi SK, Hong SR, Han HW.. Intrauterine growth restriction (IUGR) associated with confined placental mosaicism of ring chromosome 15. Am J Hum Genet 1997;61:A378–A378. [Google Scholar]
- KuchinkaBD, , BarrettIJ, , MoyaG, , SanchezJM, , LangloisS, , YongSL, , KalousekDK, , Robinson WP.. Two cases of confined placental mosaicism for chromosome 4, including one with maternal uniparental disomy. Prenatal Diagnosis 2001;21:36–39. [DOI] [PubMed] [Google Scholar]
- Kunwar F, Pabst R, Bakshi S.. Intrauterine growth restriction associated with paternal isodisomy of chromosome 5: a clinical report and literature survey. J Matern Fetal Neonatal Med 2018:1–3. [DOI] [PubMed] [Google Scholar]
- Leppig KA, Werler MM, Cann CI, Cook CA, Holmes LB.. Predictive value of minor anomalies. I. Association with major malformations. J Pediatr 1987;110:531–537. [DOI] [PubMed] [Google Scholar]
- LiD-Z, , He Y.. Confined placental trisomy detection through cell-free DNA in the maternal circulation: Benefit for pregnancy management. Am J Obstet Gynecol 2019;221:286. [DOI] [PubMed] [Google Scholar]
- Macklon NS, Geraedts JP, Fauser BC.. Conception to ongoing pregnancy: the ‘black box’ of early pregnancy loss. Hum Reprod Update 2002;8:333–343. [DOI] [PubMed] [Google Scholar]
- Marden PM, Smith DW, McDonald MJ.. Congenital Anomalies in the Newborn Infant, Including Minor Variations. A Study of 4,412 Babies by Surface Examination for Anomalies and Buccal Smear for Sex Chromatin. J Pediatr 1964;64:357–371. [DOI] [PubMed] [Google Scholar]
- Marin D, Xu J, Treff NR. (2020). Preimplantation genetic testing for aneuploidy: A review of published blastocyst reanalysis concordance data. Prenat Diagn. [DOI] [PMC free article] [PubMed]
- McCoy RC.Mosaicism in Preimplantation Human Embryos: When Chromosomal Abnormalities Are the Norm. Trends Genet 2017;33:448–463. [DOI] [PMC free article] [PubMed] [Google Scholar]
- McCoy RC, Demko ZP, Ryan A, Banjevic M, Hill M, Sigurjonsson S, Rabinowitz M, Petrov DA.. Evidence of Selection against Complex Mitotic-Origin Aneuploidy during Preimplantation Development. PLoS Genet 2015;11:e1005601. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Mertzanidou A, Wilton L, Cheng J, Spits C, Vanneste E, Moreau Y, Vermeesch JR, Sermon K.. Microarray analysis reveals abnormal chromosomal complements in over 70% of 14 normally developing human embryos. Hum Reprod 2013;28:256–264. [DOI] [PubMed] [Google Scholar]
- Morssink LP, Sikkema-Raddatz B, Beekhuis JR, De Wolf BTHM, Mantingh A.. Placental mosaicism is associated with unexplained second-trimester elevation of MShCG levels, but not with elevation of MSAFP levels. Prenat Diagn 1996;16:845–851. [DOI] [PubMed] [Google Scholar]
- Munne S, Spinella F, Grifo J, Zhang J, Beltran MP, Fragouli E, Fiorentino F.. Clinical outcomes after the transfer of blastocysts characterized as mosaic by high resolution Next Generation Sequencing- further insights. Eur J Med Genet 2020;63:103741. [DOI] [PubMed] [Google Scholar]
- Nagamatsu T, Kamei Y, Yamashita T, Fujii T, Kozuma S.. Placental abnormalities detected by ultrasonography in a case of confined placental mosaicism for trisomy 2 with severe fetal growth restriction. J Obstet Gynaecol Res 40;2014:279–283. [DOI] [PubMed] [Google Scholar]
- Nagaoka SI, Hassold TJ, Hunt PA.. Human aneuploidy: mechanisms and new insights into an age-old problem. Nat Rev Genet 2012;13:493–504. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Neiswanger K, Hohler PM, Hively-Thomas LB, McPherson EW, Hogge WA, Surti U.. Variable outcomes in mosaic trisomy 16: five case reports and literature analysis Review. Prenat Diagn 2006;26:454–461. [DOI] [PubMed] [Google Scholar]
- Peñaherrera M, Barrett IJ, Brown CJ, Langlois S, Yong SL, Lewis S, Bruyère H, Howard-Peebles PN, Kalousek DK, Robinson WP.. An association between skewed X-chromosome inactivation and abnormal outcome in mosaic trisomy 16 confined predominantly to the placenta. Clin Genet 2008;58:436–446. [DOI] [PubMed] [Google Scholar]
- Pfau SJ, Silberman RE, Knouse KA, Amon A.. Aneuploidy impairs hematopoietic stem cell fitness and is selected against in regenerating tissues in vivo. Genes Dev 2016;30:1395–1408. [DOI] [PMC free article] [PubMed] [Google Scholar]
- PiantelliG, , PatrelliT S, , AnfusoS, , NeriT M, , GramelliniD, , Nardelli G B.. Association between fetal Doppler velocimetry abnormalities and confined placental trisomy 22: A case report. J Matern Fetal Neonatal Med 2009;22:629–632. [DOI] [PubMed] [Google Scholar]
- Popovic M, Dhaenens L, Boel A, Menten B, Heindryckx B.. Chromosomal mosaicism in human blastocysts: the ultimate diagnostic dilemma. Hum Reprod Update 2020;26:313–334. [DOI] [PubMed] [Google Scholar]
- Popovic M, Dheedene A, Christodoulou C, Taelman J, Dhaenens L, Van Nieuwerburgh F, Deforce D, Van den Abbeel E, De Sutter P, Menten B. et al. Chromosomal mosaicism in human blastocysts: the ultimate challenge of preimplantation genetic testing? Hum Reprod 2018;33:1342–1354. [DOI] [PubMed] [Google Scholar]
- Popovic M, Dheedene A, Dhaenens L, Taelman J, De Sutter P, Chuva De Sousa Lopes SM, Menten B, Heindryckx B.. Human in vitro post-implantation culture models reveal the depletion of aneuploid cells in chromosomally mosaic embryos 12 days post fertilization. Hum Reprod 2018;33:i121–i122. [Google Scholar]
- Post JG, Nijhuis JG.. Trisomy 16 confined to the placenta. Prenat Diagn 1992;12:1001–1007. [DOI] [PubMed] [Google Scholar]
- Pylyp LY, Spynenko LO, Verhoglyad NV, Mishenko AO, Mykytenko DO, Zukin VD.. Chromosomal abnormalities in products of conception of first-trimester miscarriages detected by conventional cytogenetic analysis: a review of 1000 cases. J Assist Reprod Genet 2018;35:265–271. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Redaelli S, Sala E, Roncaglia N, Colombo C, Crosti F, Villa N, Tagliabue P, Cappellini A, Dalprà L.. Severe intrauterine growth restriction and trisomy 15 confined placental mosaicism: A case report and review of literature. Prenat Diagn 2005;25:140–147. [DOI] [PubMed] [Google Scholar]
- Robinson WP, Peñaherrera MS, Jiang R, Avila L, Sloan J, McFadden DE, Langlois S, von Dadelszen P.. Assessing the role of placental trisomy in preeclampsia and intrauterine growth restriction. Prenat Diagn 2010;30:1–8. [DOI] [PubMed] [Google Scholar]
- Roland B, Lynch L, Berkowitz G, Zinberg R.. Confined placental mosaicism in CVS and pregnancy outcome. Prenat Diagn 1994;14:589–593. [DOI] [PubMed] [Google Scholar]
- Saigal S, Doyle LW.. An overview of mortality and sequelae of preterm birth from infancy to adulthood. Lancet 2008;371:261–269. [DOI] [PubMed] [Google Scholar]
- Salomon LJ, Alfirevic Z, Berghella V, Bilardo C, Hernandez-Andrade E, Johnsen SL, Kalache K, Leung KY, Malinger G, Munoz H, on behalf of the ISUOG Clinical Standards Committee et al. Practice guidelines for performance of the routine mid-trimester fetal ultrasound scan. Ultrasound Obstet Gynecol 2011;37:116–126. [DOI] [PubMed] [Google Scholar]
- Sánchez JM, López De Díaz S, Panal MJ, Moya G, Kenny A, Iglesias D, Wolstenholme J.. Severe fetal malformations associated with trisomy 16 confined to the placenta. Prenat Diagn 1997;17:777–779. [DOI] [PubMed] [Google Scholar]
- Santos MA, Teklenburg G, Macklon NS, Van Opstal D, Schuring-Blom GH, Krijtenburg PJ, de Vreeden-Elbertse J, Fauser BC, Baart EB.. The fate of the mosaic embryo: chromosomal constitution and development of Day 4, 5 and 8 human embryos. Hum Reprod 2010;25:1916–1926. [DOI] [PubMed] [Google Scholar]
- Schuring-Blom GH, Keuzer M, Jakobs ME, van den Brande DM, Visser HM, Wiegant J, Hoovers JMN, Leschot NJ.. Molecular Cytogenetic Analysis of Term Placentae Suspected of Mosaicism Using Fluorescence in-Situ Hybridization. Prenat Diagn 1993;13:671–679. [DOI] [PubMed] [Google Scholar]
- Shahbazi MN, Wang T, Tao X, Weatherbee BAT, Sun L, Zhan Y, Keller L, Smith GD, Pellicer A, Scott RT Jr. et al. Developmental potential of aneuploid human embryos cultured beyond implantation. Nat Commun 2020;11:3987. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Shi Q, Qiu Y, Xu C, Yang H, Li C, Li N, Gao Y, Yu C.. Next-generation sequencing analysis of each blastomere in good-quality embryos: insights into the origins and mechanisms of embryonic aneuploidy in cleavage-stage embryos. J Assist Reprod Genet 2020;37:1711–1718. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Sifakis S, Staboulidou I, Maiz N, Velissariou V, Nicolaides KH.. Outcome of pregnancies with trisomy 2 cells in chorionic villi. Prenat Diagn 2010;30:329–332. [DOI] [PubMed] [Google Scholar]
- Singla S, Iwamoto-Stohl LK, Zhu M, Zernicka-Goetz M.. Autophagy-mediated apoptosis eliminates aneuploid cells in a mouse model of chromosome mosaicism. Nat Commun 2020;11:2958. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Smidt-Jensen S, Christensen B, Lind AM.. Chorionic villus culture for prenatal diagnosis of chromosome defects: reduction of the long-term cultivation time. Prenat Diagn 1989;9:309–319. [DOI] [PubMed] [Google Scholar]
- Smyth A, Oliveira GH, Lahr BD, Bailey KR, Norby SM, Garovic VD.. A systematic review and meta-analysis of pregnancy outcomes in patients with systemic lupus erythematosus and lupus nephritis. CJASN 2010;5:2060–2068. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Soong YK, Wang TH, Lee YS, Chen CP, Chang CL, Ho SY, Chao AS, Cheng PJ, Chang SD.. Genome-wide detection of uniparental disomy in a fetus with intrauterine growth restriction using genotyping microarrays. Taiwan J Obstet Gynecol 2009;48:152–158. [DOI] [PubMed] [Google Scholar]
- Sparks TN, Thao K, Castillo JP, Norton ME.. Mosaic trisomy 16: What are the obstetric and longterm childhood outcomes? Am J Obstet Gynecol 2016;214:S319–S320. [Google Scholar]
- Spinner NB, Conlin LK.. Mosaicism and clinical genetics. Am J Med Genet C Genet 2014;166:397–405. [DOI] [PubMed] [Google Scholar]
- Springer A, van den Heijkant M, Baumann S.. Worldwide prevalence of hypospadias. J Pediatr Urol 2016;12:152 e151–157. [DOI] [PubMed] [Google Scholar]
- Starostik MR, Sosina OA, McCoy RC.. Single-cell analysis of human embryos reveals diverse patterns of aneuploidy and mosaicism. Genome Res 2020;30:814–825. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Tiegs AW, Tao X, Zhan Y, Whitehead C, Kim J, Hanson B, Osman E, Kim TJ, Patounakis G, Gutmann J Jr.. et al. A multicenter, prospective, blinded, nonselection study evaluating the predictive value of an aneuploid diagnosis using a targeted next-generation sequencing-based preimplantation genetic testing for aneuploidy assay and impact of biopsy. Fertil Steril 2020. [DOI] [PubMed] [Google Scholar]
- Toufaily MH, Roberts DJ, Westgate MN, Hunt AT, Holmes LB.. Hypospadias, Intrauterine Growth Restriction, and Abnormalities of the Placenta. Birth Defects Res 2018;110:122–127. [DOI] [PubMed] [Google Scholar]
- Toutain J, Goutte-Gattat D, Horovitz J, Saura R.. Confined placental mosaicism revisited: Impact on pregnancy characteristics and outcome. PLoS One 2018;13:e0195905. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Toutain J, Labeau-Gaüzere C, Barnetche T, Horovitz J, Saura R.. Confined placental mosaicism and pregnancy outcome: A distinction needs to be made between types 2 and 3. Prenat Diagn 2010;30:1155–1164. [DOI] [PubMed] [Google Scholar]
- Towner DR, Shaffer LG, Yang SP, Walgenbach DD.. Confined placental mosaicism for trisomy 14 and maternal uniparental disomy in association with elevated second trimester maternal serum human chorionic gonadotrophin and third trimester fetal growth restriction. Prenat Diagn 2001;21:395–398. [DOI] [PubMed] [Google Scholar]
- Tsuiko O, Fernandez Gallardo E, Voet T, Vermeesch JR.. PREIMPLANTATION GENETIC TESTING: Single-cell technologies at the forefront of PGT and embryo research. Reproduction 2020;160:A19–A31. [DOI] [PubMed] [Google Scholar]
- van den Berg MM, van Maarle MC, van Wely M, Goddijn M.. Genetics of early miscarriage. Biochim Biophys Acta 2012;1822:1951–1959. [DOI] [PubMed] [Google Scholar]
- van Echten-Arends J, Mastenbroek S, Sikkema-Raddatz B, Korevaar JC, Heineman MJ, van der Veen F, Repping S.. Chromosomal mosaicism in human preimplantation embryos: a systematic review. Hum Reprod Update 2011;17:620–627. [DOI] [PubMed] [Google Scholar]
- Van Opstal D, Eggenhuizen GM, Joosten M, Diderich K, Govaerts L, Galjaard RJ, Go A, Knapen M, Boter M, Cheung WY. et al. Noninvasive prenatal testing as compared to chorionic villus sampling is more sensitive for the detection of confined placental mosaicism involving the cytotrophoblast. Prenat Diagn 2020;40:1338–1342. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Van Opstal D, Van den Berg C, Deelen WH, Brandenburg H, Cohen-Overbeek TE, Halley DJJ, Van den Ouweland AMW, Veld P. A I T, Los FJ.. Prospective prenatal investigations on potential uniparental disomy in cases of confined placental trisomy. Prenat Diagn 1998;18:35–44. [PubMed] [Google Scholar]
- Van Opstal D, Van Maarle MC, Lichtenbelt K, Weiss MM, Schuring-Blom H, Bhola SL, Hoffer MJV, Amsterdam KHV, Macville MV, Kooper AJA, for the Dutch NIPT Consortium et al. Origin and clinical relevance of chromosomal aberrations other than the common trisomies detected by genome-wide NIPS: Results of the TRIDENT study. Genet Med 2018;20:480–485. [DOI] [PMC free article] [PubMed] [Google Scholar]
- Vanneste E, Voet T, Caignec CL, Ampe M, Konings P, Melotte C, Debrock S, Amyere M, Vikkula M, Schuit F. et al. Chromosome instability is common in human cleavage-stage embryos. Nat Med 2009;15:577–583. [DOI] [PubMed] [Google Scholar]
- Vaughan J, Ali Z, Bower S, Bennett P, Chard T, Moore G.. Human maternal uniparental disomy for chromosome 16 and fetal development. Prenat Diagn 1994;14:751–756. [DOI] [PubMed] [Google Scholar]
- Vazquez-Diez C, Paim LMG, FitzHarris G.. Cell-Size-Independent Spindle Checkpoint Failure Underlies Chromosome Segregation Error in Mouse Embryos. Curr Biol 2019;29:865–873. e863. [DOI] [PubMed] [Google Scholar]
- Victor AR, Tyndall JC, Brake AJ, Lepkowsky LT, Murphy AE, Griffin DK, McCoy RC, Barnes FL, Zouves CG, Viotti M.. One hundred mosaic embryos transferred prospectively in a single clinic: exploring when and why they result in healthy pregnancies. Fertil Steril 2019;111:280–293. [DOI] [PubMed] [Google Scholar]
- Villar J, Cheikh Ismail L, Victora CG, Ohuma EO, Bertino E, Altman DG, Lambert A, Papageorghiou AT, Carvalho M, Jaffer YA, Newborn Growth Consortium for the 21st et al. International standards for newborn weight, length, and head circumference by gestational age and sex: the Newborn Cross-Sectional Study of the INTERGROWTH-21st Project. Lancet 2014;384:857–868. [DOI] [PubMed] [Google Scholar]
- Vogel JP, Chawanpaiboon S, Moller AB, Watananirun K, Bonet M, Lumbiganon P.. The global epidemiology of preterm birth. Best Pract Res Clin Obstet Gynaecol 2018;52:3–12. [DOI] [PubMed] [Google Scholar]
- Wan JH, Han J, Yang YD, Li DZ.. Detection of confined placental trisomy 16 using non-invasive prenatal testing in a pregnancy associated with intrauterine growth restriction and normal karyotype. Eur J Obstet Gynecol Reprod Biol 2019;233:81–83. [DOI] [PubMed] [Google Scholar]
- Wang T, Zhang Q, Li H, Wang W.. Confined placental mosaicism of trisomy 16 detected by non-invasive prenatal testing and multiple abnormalities. Clin Exp Obstet Gynecol 2017;44:806–809. [Google Scholar]
- Wang H, Luo C, Liu Y, Li S, Jiang N, Zhang G, Xie J, Zhong M.. UPD16 itself is not a cause of intrauterine growth restriction. Fetal Pediatr Pathol 2018;37:452–464. [DOI] [PubMed] [Google Scholar]
- Watt JL, Templeton AA, Messinis I, Bell L, Cunningham P, Duncan RO.. Trisomy 1 in an eight cell human pre-embryo. J Med Genet 1987;24:60–64. [DOI] [PMC free article] [PubMed] [Google Scholar]
- WebbA, , BeardJ, , WrightC, , RobsonS, , WolstenholmeJ, , Goodship J.. A case of paternal uniparental disomy for chromosome 11. Prenat Diagn 1995;15:773–777. [DOI] [PubMed] [Google Scholar]
- Wilkins-Haug L, Quade B, Morton CC.. Confined placental mosaicism as a risk factor among newborns with fetal growth restriction. Prenat Diagn 2006;26:428–432. [DOI] [PubMed] [Google Scholar]
- Woo V, Bridge PJ, Bamforth JS.. Maternal uniparental heterodisomy for chromosome 16: case report. Am J Med Genet 1997;70:387–390. [DOI] [PubMed] [Google Scholar]
- Wolstenholme J, Rooney DE, Davison EV.. Confined placental mosaicism, IUGR, and adverse pregnancy outcome: A controlled retrospective U.K. collaborative survey. Prenat Diagn 1994;14:345–361. [DOI] [PubMed] [Google Scholar]
- Yamazawa K, Ogata T, Ferguson-Smith AC.. Uniparental disomy and human disease: an overview. Am J Med Genet C Genet 2010;154C:329–334. [DOI] [PubMed] [Google Scholar]
- Yong PJ, Langlois S, Von Dadelszen P, Robinson W.. The association between preeclampsia and placental trisomy 16 mosaicism. Prenat Diagn 2006;26:956–961. [DOI] [PubMed] [Google Scholar]
- Zhou F, Wang R, Yuan P, Ren Y, Mao Y, Li R, Lian Y, Li J, Wen L, Yan L. et al. Reconstituting the transcriptome and DNA methylome landscapes of human implantation. Nature 2019;572:660–664. [DOI] [PubMed] [Google Scholar]
- Zimmermann R, Lauper U, Streicher A, Huch R, Huch A.. Elevated alpha-fetoprotein and human chorionic gonadotropin as a marker for placental trisomy 16 in the second trimester? Prenat Diagn 1995;15:1121–1124. [DOI] [PubMed] [Google Scholar]
Associated Data
This section collects any data citations, data availability statements, or supplementary materials included in this article.
Supplementary Materials
Data Availability Statement
The data that support the findings of our conclusions are available from the corresponding author upon reasonable request.