



Abstract
Objective(s):
Cigarette smoke may play a direct role in proliferation of human pulmonary artery smooth muscle cells (HPASMCs). However, the mechanism involved and the effect of interventions remain unclear. We aimed to evaluate the effect of cigarette smoke extract (CSE) on HPASMCs, explore the role of inflammation and oxidative stress, and the effects of Tempol and PDTC in this process.
Materials and Methods:
HPASMCs were subjected to normal control (NC), CSE, CSE+Tempol (CSE+T), and CSE+PDTC (CSE+P) groups. Proliferation of HPASMCs was measured by CCK-8 and Western blot. TNF-α, IL-6, MDA, and SOD levels were determined by ELISA and commercial kits. Nuclear translocation of NF-κB p65 was evaluated by western blot.
Results:
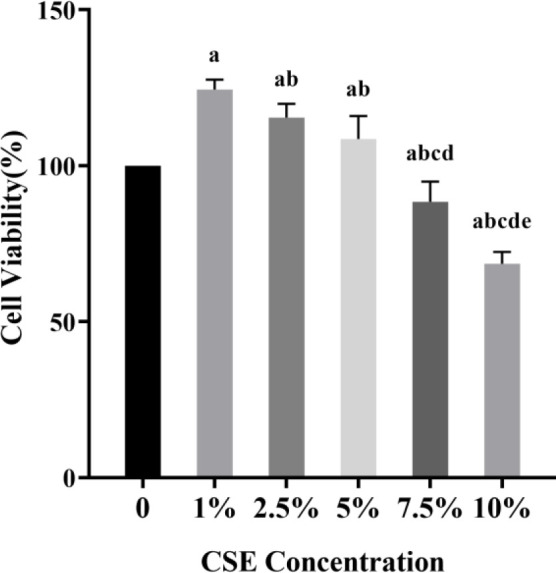
1%, 2.5%, and 5% CSE all promoted proliferation of HPASMCs, and effect of 1% CSE was the most significant, however, 7.5% and 10% CSE inhibited viability of cells (all P<0.05). Compared with the NC group, TNF-α, IL-6, and MDA levels increased, SOD activity decreased (all P<0.05), and NF-κB p65 expression in nuclei increased (P=0.04) in the CSE group. Tempol and PDTC inhibited the proliferation of HPASMCs induced by CSE (all P<0.05). And compared with the CSE group, TNF-α, IL-6, and MDA levels in CSE+T and CSE+P groups decreased, while SOD activity increased (all P<0.05). Tempol reduced the expression of NF-κB p65 in nuclei but did not achieve a significant difference (P=0.08). PDTC inhibited the nuclear translocation of NF-κB p65 (P=0.03).
Conclusion:
CSE stimulates HPASMCs proliferation in a certain concentration range. The CSE-induced proliferation of HPASMCs involved excessive inflammatory response and oxidative stress. Tempol and PDTC attenuate these effects of CSE on HPASMCs.
Key Words: Cigarette smoking, Inflammation, NF-κB, Oxidative stress, Pulmonary arterial - hypertension
Introduction
Chronic obstructive pulmonary disease (COPD) is a kind of chronic airway and lung disease with respiratory symptoms such as persistent cough and expectoration. It has been generally accepted and acknowledged that COPD with significant characteristic of irreversible airflow limitation has far-reaching effects on cardiac function and gas exchange, which could initiate various comorbid diseases (1). Pulmonary hypertension (PH) is one of the most common complications characterized by the rise in pulmonary vascular resistance and pulmonary arterial pressure, eventually resulting in right ventricular hypertrophy, functional decline, failure, and even death (2). The prevalence of COPD complicated with PH varies from 20%–91% (3, 4), and increases with the severity of COPD (5). It is universally considered that COPD complicated with PH results from hypoxia in the process of illness. Chronic hypoxia stimulates pulmonary vasoconstriction and causes remodeling of pulmonary small vessels. Interestingly, some studies have found that pulmonary tissues of COPD had obvious pathological reconstruction in the early days even before hypoxia appeared (6-8). Moreover, it has been declared that cigarette smoke may be directly involved in the proliferation of vascular smooth muscle cells in the bovine thoracic aorta, human greater saphenous vein, and aortic and iliac arteries (9). It was also reported that cigarette smoke could directly induce production of vasoactive mediators controlling dynamic vasoconstriction and vasodilation (8). All these findings showed cigarette smoke may directly cause remodeling of pulmonary vessels and PH. Nevertheless, the underlying mechanism and effect of interventions are still poorly understood.
Pulmonary vascular remodeling is a landmark pathophysiological basis for the development of PH, in which the increased proliferation of pulmonary artery smooth muscle cells (PASMCs) is a pivotal contributor. Abnormal proliferation of PASMCs is believed to be responsible for medial hypertrophy, artery remodeling, and vascular lumen narrowing, which is the typical pathological manifestation of PH (10). There is evidence in the literature that inflammation and oxidative stress were considered to play key intermediary roles in the development of hypoxia-induced PH (11, 12). However, to the best of our knowledge, whether cigarette smoke extraction (CSE) induces excessive inflammation and oxidative stress, and its roles in the proliferation of human pulmonary artery smooth muscle cells (HPASMCs) have not as yet been elucidated clearly.
Herein, we aimed to clarify the effect of CSE on HPASMCs, investigate whether excessive inflammation and oxidative stress are involved in this pathological process, and explore the effect of interventions, such as 4-hydroxy-2,2,6,6-tetramethylpiperidine (Tempol) and pyrrolidine dithiocarbamate (PDTC) in this process.
Materials and Methods
Preparation of CSE solution
Commercial filtered cigarettes (Zuanshi, Zhangjiakou Cigarette Factory, China), which contain 11 mg tar, 0.9 mg nicotine, and 12 mg carbon monoxide, were used. CSE solution was prepared as described by Oltmanns et al. with a few modifications (13). Briefly, smoke derived from one cigarette was slowly dissolved in 10 ml of preheated phosphate buffer solution (PBS, pH=7.4) under suction and driving of 50 ml syringes at room temperature. The resulting solution, which was considered pure stoste, was adjusted to pH 7.4 with NaOH and filtered through a 0.22 μm pore filter before diluting it into solutions of different concentrations with Dulbecco’s modified Eagle’s medium (DMEM, Gibco Life Technologies Inc, Rockville, MD, USA). Finally, the CSE solutions of different concentrations ranging from 0% to 10% (0%, 1%, 2.5%, 5%, 7.5%, and 10%) were used to evaluate the effect of CSE on HPASMCs.
Cell culture and treatment
HPASMCs (Otwo Biotech, Shenzhen, China) were cultured in DMEM supplemented with 10% fetal bovine serum (FBS), 100 U/ml penicillin, and 100 ug/ml streptomycin in a 5% CO2 and 37 °C incubator with saturated humidity. The medium was replaced every other day. HPASMCs were treated with varying concentrations of CSE solutions for 24 hr, with or without the anti-oxidant, Tempol (0.4 mmol/L, Sigma-Aldrich), or the NF-κB inflammatory channel blocker, PDTC(50 umol/L, Abcam).
Cell proliferation analysis
The effects of CSE on viability and proliferation of HPASMCs waere examined by Cell Counting Kit-8 (CCK-8) assay according to the kit instructions (Nanjing Jiancheng Bioengineering Research Institute, China). Cells (1*104/well) were seeded in 96-well plates in replicates of three. After 24 hr of different treatments, the absorbance at 490 nm was recorded.
Western blot analysis
After being cultured for 24 hr, HPASMCs were lysed with radioimmunoprecipitation (RIPA) buffer with 1 mM phenylmethylsulfonyl fluoride (PMSF) on ice for 30 min. The cell lysates were sonicated and then centrifuged at 12,000 rpm for 15 min at 4 °C, and the insoluble fraction was discarded. Cytoplasmic and nuclear protein was extracted according to the protocol of the Nuclear and Cytoplasmic Protein Extraction Kit (Sangon Biotech, Shanghai, China). The protein concentration was measured using the BCA Protein Assay Kit (Thermo, USA). The samples were separated on 10% sodium dodecyl sulfate-polyacrylamide gels and transferred to polyvinylidene difluoride membranes. Then the membranes were blocked with 5% non-fat milk for 1 hr at room temperature, followed by overnight incubation at 4 °C with primary antibodies against the following proteins: H3 antibody (1:1000), β-actin antibody (1:1000), α-SMA antibody (1:1000), NF-κB antibody (1:1000). After overnight incubation, the membranes were incubated with appropriate HRP-labeled secondary antibodies at a dilution of 1:3000. The ECL detection system (Thermo, USA) was used to detect the signals on the membranes.
Enzyme-linked immunosorbent assay
The levels of tumor necrosis factor-α (TNF-α) and interleukin-6 (IL-6) were determined in the extracted supernatant with the use of the double-antibody sandwich enzyme-linked immunosorbent assay (ELISA, R&D System, Los Angeles, USA) according to the protocol.
Assay of MDA and SOD
The contents of malondialdehyde (MDA) and superoxide dismutase (SOD) were measured using commercial kits (Nanjing Jiancheng BioengineeringResearch Institute, China) and analyzed with a spectrophotometer according to the manufacturer’s instructions.
Statistical analysis
SPSS 25.0 software package (SPSS Inc., Chicago, IL, USA) was used for statistical analysis and illustration. All results in the study were expressed as mean±standard deviation. One-way analysis of variance was performed for whole difference among groups, and the difference between two groups was compared using the Student t-test. Two-sided P<0.05 was considered statistically significant.
Results
Effect of different concentrations of CSE on HPASMCs proliferation
To investigate the effect of different concentrations of CSE on cell proliferation, HPASMCs were stimulated with 0%, 1%, 2.5%, 5%, 7.5%, and 10% CSE solutions for 24 hr, respectively. As shown in Figure 1, the 1%, 2.5%, and 5% CSE treatments all caused a significant increase in cell growth compared with the NC group, and the effect of 1% CSE was the most significant (all P<0.05). However, 7.5% and 10% CSE significantly inhibited cell viability (all P<0.05). Therefore, 1% CSE was used for further experiments.
Figure 1.
The HPASMCs were treated with increasing concentrations of CSE for 24 hr. Cell proliferation was analyzed by CCK-8 assay. The data were shown as mean±standard deviation from five duplicated experiments. aP<0.05 compared with NC group, bP<0.01 compared with 1% CSE group, cP<0.01 compared with 2.5% CSE group, dP<0.01 compared with 5% CSE group, eP<0.01 compared with 7.5% CSE group
HPASMCs: human pulmonary artery smooth muscle cells; NC: normal control; CSE: cigarette smoke extract; CCK-8: Cell Counting Kit-8
Effect of Tempol and PDTC on HPASMCs proliferation promoted by 1% CSE
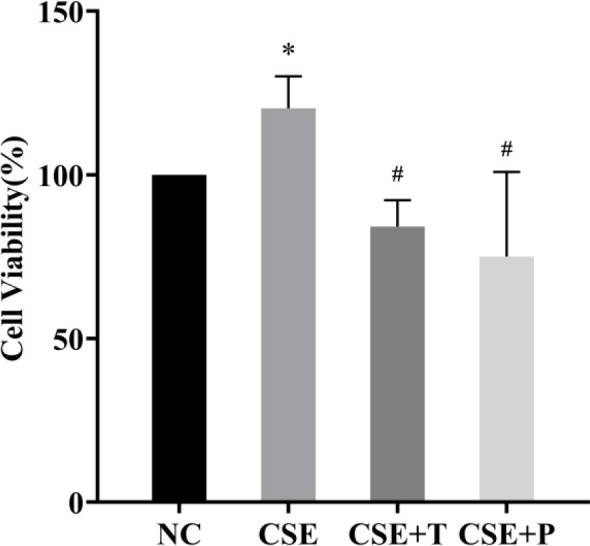
Within the 24-hr 1% CSE exposure, cell viability was significantly increased in the CSE group compared with that in the NC group (P=0.02). Tempol and PDTC treatment significantly inhibited the increase of cell growth induced by CSE (all P<0.05, Figure 2). Consistent with this, a significant up-regulation of α-SMA, a proliferation-related protein, in the CSE group was observed by Western blotting, compared with that in the NC group (P=0.01, Figure 3). However, Tempol and PDTC treatment inhibited the increased expression of α-SMA in HPASMCs induced by CSE (all P<0.05, Figure 3).
Figure 2.
HPASMCs were pretreated with Tempol or PDTC before exposure to 1% CSE. Cell viability was analyzed by CCK-8 assay. The data were shown as mean±standard deviation from three replicated experiments. *P<0.05 compared with NC group, #P<0.05 compared with 1% CSE group
PDTC: pyrrolidine dithiocarbamate; HPASMCs: human pulmonary artery smooth muscle cells; NC: normal control; CSE: cigarette smoke extract; CCK-8: Cell Counting Kit-8
Figure 3.
CSE induced up-expression of α-SMA and nuclear translocation of NF-κB p65 in HPASMCs. a: Western blot analysis showed the expression level of α-SMA, Nuclear NF-κB p65, Cytoplasm NF-κB p65, β-actin, and H3. b: Summarized data showed the average protein level of α-SMA and NF-κB p65 in the nuclear and cytoplasm fraction. *P<0.05 compared with NC group, #P<0.05 compared with 1% CSE group

The data were shown as mean±standard deviation from three repeated experiments
HPASMCs: human pulmonary artery smooth muscle cells; NC: normal control; CSE, cigarette smoke extract
Comparisons of inflammatory factors in the supernatant
Within the 24-hr 1%CSE exposure, TNF-α and IL-6 levels in the CSE group both significantly increased compared with that in the NC group (all P<0.01, Figure 4). The anti-oxidant, Tempol, and the NF-κB inflammatory channel blocker, PDTC, both significantly reduced the levels of TNF-α and IL-6 induced by CSE exposure (all P<0.01, Figure 4).
Figure 4.

Effect of CSE on TNF-α (a) and IL-6 (b) levels in the supernatants of HPASMCs with or without Tempol and PDTC. The data were expressed as the mean±standard deviation of three replicated experiments.*P<0.01 compared with NC group, #P<0.01 compared with 1% CSE groupC: normal control; PDTC: pyrrolidine dithiocarbamate; HPASMCs: human pulmonary artery smooth muscle cells; CSE: cigarette smoke extract
Comparisons of oxidative stress markers in the supernatant
To determine the oxidative stress response of HPASMCs to CSE exposure, the levels of SOD activity and MDA concentration were analyzed in the supernatant. The results showed that CSE decreased the levels of SOD activity, and increased the levels of MDA concentration (all P<0.05, Figure 5). Tempol and PDTC significantly reduced this CSE-induced damage (all P<0.05, Figure 5).
Figure 5.
Levels of MDA concentration (a) and SOD activity (b) in different exposure conditions. The data were expressed as the mean±standard deviation of three replicated experiments.*P<0.05 compared with NC group, #P<0.05 compared with 1% CSE group

MDA: malondialdehyde; SOD: superoxide dismutase; NC: normal control; CSE: cigarette smoke extract
Comparison of NF- ĸ B expression levels in HPASMCs
CSE induced nuclear translocation of NF-κB. As shown in Figure 3, exposure of HPASMCs to 1% CSE had little effect on the expression level of NF-κB p65 in the cytoplasm (P=0.97), but significantly increased the expression level of NF-κB p65 in nuclei (P=0.04). Tempol decreased the expression level of NF-κB p65 in nuclei compared with that in the CSE group but failed to achieve a statistically significant difference (P=0.08). PDTC markedly inhibited the nuclear translocation of NF-κBp65 (P=0.03).
Discussion
Cigarette smoking is a major public health problem, responsible for killing more than seven million people every year globally (14), associated with various kinds of diseases, including vascular diseases, such as atherosclerosis and PH (15). Cigarette smoke is a complex chemical mixture that contains over 4000 different compounds, in which 158 of the chemical constituents are identified to be toxic hazards, and 15 individual chemical constituents contribute to cardiovascular dysfunction (16). Studies in both animal models and human patients have shown that cigarette smoke exerted a direct effect on pulmonary vascular structure, resulting in pulmonary vascular remodeling and PH (17, 18). Proliferation of vascular smooth muscle cells is considered to play a key role in the occurrence and development of vascular diseases. Abnormal vascular smooth muscle cell proliferation leads to vascular remodeling, medial hypertrophy of the vessel wall, and vascular lumen narrowing, all of which contribute to the development of PH (19, 20). In this study, we have shown that lower concentrations of CSE (1%, 2.5%, and 5%) stimulated the proliferation of HPASMCs, whereas higher concentrations of CSE (7.5% and 10%) were inhibitory as a result of cytotoxicity. These results are consistent with previous findings, although the concentration of CSE with the best proliferative effect on cells is different (21, 22). This may be related to different CSE preparation methods, cell types, and cell culture conditions (21).
A substantial body of evidence has affirmed that PH was linked to inflammation (11, 23-26). The inflammatory factors included IL-1β, IL-2, IL-4, IL-5, IL-6, IL-8, IL-10, IL-12p70, IL-13, TNF-α, etc (11,27). The studies on human patients showed the serum levels of IL-6 in PH patients were significantly higher than that in normal controls(28); and the levels were also related to the survival of patients(25, 27,29). Moreover, the plasma levels of IL-6 were higher in COPD patients complicated with PH compared with pure COPD patients, and the levels correlated with mean pulmonary arterial pressure (30). Bhargava et al. declared that the expression of IL-6 mRNA and bioactivity of IL-6 were increased in the lung of monocrotaline-induced PH and right ventricular hypertrophy (RVH) rats. When the rats were treated with dexamethasone, the IL-6 levels decreased, and the pulmonary pressures and RVH attenuated compared with pre-treatment (31). Steiner et al. found that there was enhanced muscularization of distal arterioles and occlusive neointimal angioproliferative lesions in rats over-expressing IL-6, which were consistent with the early pathological manifestations of PH and RVH (32). Similarly, elevated serum levels of TNF-α were described in PH patients, and the levels were also associated with quality of life-related symptoms (25, 27). In addition, COPD patients with PH showed significantly higher TNF-α levels than COPD patients without PH (33). Several studies have shown that over-expression of TNF-α could result in chronic pulmonary inflammation and PH (34, 35). However, TNF-α antagonists showed an ameliorated effect on pulmonary hemodynamic, RVH, and pulmonary inflammation in rats with monocrotaline-induced PH and in pigs with endotoxemic-shock-induced PH (36-38). Smoking is associated with the release and inhibition of pro-inflammatory and anti-inflammatory mediators. Cigarette smoke has been shown to increase the production of a variety of pro-inflammatory cytokines, such as TNF- α and IL-6, and reduce the levels of anti-inflammatory cytokines, such as IL-10 (39). NF-κB is a pro-inflammatory transcription factor controlling many genes which are important for immunity, inflammation, cell proliferation, and apoptosis. Under physiological conditions, NF-κB dimer was sequestered in the cytoplasm in an inactive form bounding to its inhibitory protein, IκB. Under pathological conditions, IκB kinase was activated, then IκB was phosphorylated, and the released NF-κB dimer translocated to the nucleus, in which it induced transcription of NF-κB target genes (40). It has been reported that NF-κB played key roles in pathological processes of PH, including monocrotaline-induced PH, growth factors (PDGF, bFGF, EGF, and IGF-1)-induced PH, and chronic hypoxia-induced PH (41-44). In accordance with this, our data showed that CSE exposure caused nuclear translocation of NF-κB in the process of HPASMC proliferation. Meanwhile, our results showed that IL-6 and TNF-α levels were increased in the CSE exposure group versus the NC group, suggesting that inflammation may be involved in vascular smooth muscle cell proliferation under CSE stimulation through NF-κB pathway activation.
Another important factor involved with PH was oxidative stress. Increased oxidative stress was considered to play a pivotal role in the development of hypoxia-induced PH (45, 46). Reactive oxygen species (ROS) was the most important effector in excessive oxidative damage in the pathogenesis of PH, which regulates the release of several vasoactive factors, such as ET-1, TXA-2, and prostacyclin, which can influence vasomotor and lead to vascular remodeling (47-49). ROS has been proven to increase in both in vitro and in vivo models of chronic hypoxia-induced vascular smooth muscle cell proliferation and pulmonary vessel remodeling, and inhibition of ROS production has been shown to attenuate PH (50-52). Oxidative stress can be reflected by several markers. The lipid peroxidation product, MDA, can indirectly reflect cellular oxidative stress levels, while SOD can protect the cells against the potential damage from superoxide radicals via catalyzing the conversion of superoxide radicals to hydrogen peroxide. COPD patients had higher serum MDA concentrations compared with healthy subjects (53). Moreover, the serum MDA levels in COPD patients with PH were elevated compared with that in COPD patients without PH, while the SOD levels were reduced in COPD patients with PH compared with that in pure COPD patients. Additionally, the serum MDA levels were positively correlated with 3-year PH incidence, and negatively correlated with 3-year survival rate in COPD patients; however, serum SOD levels were negatively correlated with 3-year PH incidence, and positively correlated with 3-year survival rate in COPD patients(54). Previous studies have demonstrated that billions of free radicals and chemicals in cigarettes could generate ROS through the redox cycle, causing excessive oxidative stress in the lungs and imposing an undue oxidative burden (55). It has been reported that ROS can cause oxidative damage to the cell’s lipids, proteins, and DNA, and may be involved in the development of PH (56). Our results showed that the CSE group had higher levels of MDA concentrations and lower levels of SOD activity as compared with those in the NC group, indicating that excessive oxidative stress would be present in vascular smooth muscle cell proliferation upon CSE stimulation.
Our current results showed that the levels of inflammatory factors, oxidative stress markers, and proliferation-associated indicators were all improved in the CSE+T/P group as compared with that in the CSE group. Tempol is a superoxide scavenger, which can reduce the damage of exogenous ROS to cultured cells (57). It has been reported that Tempol reduced superoxide production and improved vascular endothelial function (58, 59). Tempol can also decrease pulmonary arterial hypertension in hypoxia-induced PH rats (12). Here, our data showed that Tempol was effective in alleviating the proliferation of HPASMCs under CSE stimulation by diminishing oxidative stress and inflammatory response. Meanwhile, we also declared that PDTC, which inhibits the activation and translocation of NF-κB by repressing the phosphorylation and degradation of IκB (60), resulted in markedly reduced expression/production of TNF-α, IL-6, and MDA, and improved production of SOD, which contributed to decreasing the proliferating effect of CSE on HPASMCs.
Conclusion
In summary, CSE in a certain concentration range could stimulate the proliferation of HPASMCs, which is one of the pathogenesis of PH, through aggravating inflammatory responses and oxidative stress. Application of Tempol and PDTC could markedly reduce the CSE-induced proliferation of HPASMCs by attenuating the above process.
Authors’ Contributions
The work presented in this article was carried out through collaboration between all authors. JW and LW Made the initial hypothesis. All authors participated in defining the research theme and providing the proposal. JW, LW, XC, MLL, and DHW Performed the experiments. JW, LW, and XC Interpreted the data and wrote and edited the article. JC and JZ Supervised the work. All authors edited and approved the article.
Conflicts of Interest
There are no conflicts of interest to declare.
Acknowledgment
This work is supported by grants from the National Natural Science Foundation of China (No. 81970084).
References
- 1.Karnati S, Seimetz M, Kleefeldt F, Sonawane A, Madhusudhan T, Bachhuka A, et al. Chronic obstructive pulmonary disease and the cardiovascular system: Vascular repair and regeneration as a therapeutic target. Front Cardiovasc Med. 2021;8:649512. doi: 10.3389/fcvm.2021.649512. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 2.Gao L, Liu J, Hao Y, Zhao Z, Tan H, Zhang J, et al. Chronic intermittent hypobaric hypoxia attenuates monocrotaline-induced pulmonary arterial hypertension via modulating inflammation and suppressing NF-κB/p38 pathway. Iran J Basic Med Sci. 2018;21:244–252. doi: 10.22038/ijbms.2018.25399.6280. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 3.Scharf SM, Iqbal M, Keller C, Criner G, Lee S, Fessler HE. Hemodynamic characterization of patients with severe emphysema. Am J Respir Crit Care Med. 2002;166:314–322. doi: 10.1164/rccm.2107027. [DOI] [PubMed] [Google Scholar]
- 4.Thabut G, Dauriat G, Stern JB, Logeart D, Lévy A, Marrash-Chahla R, et al. Pulmonary hemodynamics in advanced COPD candidates for lung volume reduction surgery or lung transplantation. Chest. 2005;127:1531–1536. doi: 10.1378/chest.127.5.1531. [DOI] [PubMed] [Google Scholar]
- 5.Nathan SD, Barbera JA, Gaine SP, Harari S, Martinez FJ, Olschewski H, et al. Pulmonary hypertension in chronic lung disease and hypoxia. Eur Respir J. 2019;53:1801914. doi: 10.1183/13993003.01914-2018. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 6.Santos S, Peinado VI, Ramírez J, Melgosa T, Roca J, Rodriguez-Roisin R, et al. Characterization of pulmonary vascular remodelling in smokers and patients with mild COPD. Eur Respir J. 2002;19:632–638. doi: 10.1183/09031936.02.00245902. [DOI] [PubMed] [Google Scholar]
- 7.Peinado VI, Pizarro S, Barberà JA. Pulmonary vascular involvement in COPD. Chest. 2008;134:808–814. doi: 10.1378/chest.08-0820. [DOI] [PubMed] [Google Scholar]
- 8.Wright JL, Levy RD, Churg A. Pulmonary hypertension in chronic obstructive pulmonary disease: Current theories of pathogenesis and their implications for treatment. Thorax. 2005;60:605–609. doi: 10.1136/thx.2005.042994. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 9.Li Y, Pu G, Chen C, Yang L. Inhibition of FHL1 inhibits cigarette smoke extract-induced proliferation in pulmonary arterial smooth muscle cells. Mol Med Rep. 2015;12:3801–3808. doi: 10.3892/mmr.2015.3787. [DOI] [PubMed] [Google Scholar]
- 10.Wang X, Wang W, Liu C, Wu XJ. Involvement of TRPC1 and cyclin D1 in human pulmonary artery smooth muscle cells proliferation induced by cigarette smoke extract. Curr Med Sci. 2020;40:1085–1091. doi: 10.1007/s11596-020-2290-1. [DOI] [PubMed] [Google Scholar]
- 11.Groth A, Vrugt B, Brock M, Speich R, Ulrich S, Huber LC. Inflammatory cytokines in pulmonary hypertension. Respir Res. 2014;15:47–55. doi: 10.1186/1465-9921-15-47. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 12.Shao J, Wang P, Liu A, Du X, Bai J, Chen M. Punicalagin prevents hypoxic pulmonary hypertension via anti-oxidant effects in rats. Am J Chin Med. 2016;44:785–801. doi: 10.1142/S0192415X16500439. [DOI] [PubMed] [Google Scholar]
- 13.Oltmanns U, Chung KF, Walters M, John M, Mitchell JA. Cigarette smoke induces IL-8, but inhibits eotaxin and RANTES release from airway smooth muscle. Respir Res. 2005;6:74. doi: 10.1186/1465-9921-6-74. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 14.Collaborators GT. Smoking prevalence and attributable disease burden in 195 countries and territories, 1990-2015: a systematic analysis from the Global Burden of Disease Study 2015. Lancet. 2017;389:1885–1906. doi: 10.1016/S0140-6736(17)30819-X. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 15.Wang W, Zhao T, Geng K, Yuan G, Chen Y, Xu Y. Smoking and the pathophysiology of peripheral artery disease. Front Cardiovasc Med. 2021;8:704106. doi: 10.3389/fcvm.2021.704106. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 16.Fowles J, Dybing E. Application of toxicological risk assessment principles to the chemical constituents of cigarette smoke. Tob Control. 2003;12:424–430. doi: 10.1136/tc.12.4.424. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 17.Blanco I, Piccari L, Barberà JA. Pulmonary vasculature in COPD: The silent component. Respirology. 2016;21:984–994. doi: 10.1111/resp.12772. [DOI] [PubMed] [Google Scholar]
- 18.Hadzic S, Wu CY, Gredic M, Kojonazarov B, Pak O, Kraut S, et al. The effect of long-term doxycycline treatment in a mouse model of cigarette smoke-induced emphysema and pulmonary hypertension. Am J Physiol Lung Cell Mol Physiol. 2021;320:L903–l915. doi: 10.1152/ajplung.00048.2021. [DOI] [PubMed] [Google Scholar]
- 19.Pietra GG, Capron F, Stewart S, Leone O, Humbert M, Robbins IM, et al. Pathologic assessment of vasculopathies in pulmonary hypertension. J Am Coll Cardiol. 2004;43:25s–32s. doi: 10.1016/j.jacc.2004.02.033. [DOI] [PubMed] [Google Scholar]
- 20.Rabinovitch M. The mouse through the looking glass: A new door into the pathophysiology of pulmonary hypertension. Circ Res. 2004;94:1001–1004. doi: 10.1161/01.RES.0000128079.89263.68. [DOI] [PubMed] [Google Scholar]
- 21.Hu J, Xu YJ, Zhang ZX, Tian F. Effect of cigarette smoke extract on proliferation of rat pulmonary artery smooth muscle cells and the relevant roles of protein kinase C. Chin Med J (Engl) 2007;120:1523–1528. [PubMed] [Google Scholar]
- 22.Xing AP, Du YC, Hu XY, Xu JY, Zhang HP, Li Y, et al. Cigarette smoke extract stimulates rat pulmonary artery smooth muscle cell proliferation via PKC-PDGFB signaling. J Biomed Biotechnol. 2012;2012:534384. doi: 10.1155/2012/534384. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 23.Dolenc J, Šebeštjen M, Vrtovec B, Koželj M, Haddad F. Pulmonary hypertension in patients with advanced heart failure is associated with increased levels of interleukin-6. Biomarkers. 2014;19:385–390. doi: 10.3109/1354750X.2014.918654. [DOI] [PubMed] [Google Scholar]
- 24.Hashimoto-Kataoka T, Hosen N, Sonobe T, Arita Y, Yasui T, Masaki T, et al. Interleukin-6/interleukin-21 signaling axis is critical in the pathogenesis of pulmonary arterial hypertension. Proc Natl Acad Sci U S A. 2015;112:E2677–2686. doi: 10.1073/pnas.1424774112. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 25.Matura LA, Ventetuolo CE, Palevsky HI, Lederer DJ, Horn EM, Mathai SC, et al. Interleukin-6 and tumor necrosis factor-α are associated with quality of life-related symptoms in pulmonary arterial hypertension. Ann Am Thorac Soc. 2015;12:370–375. doi: 10.1513/AnnalsATS.201410-463OC. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 26.Pugliese SC, Poth JM, Fini MA, Olschewski A, El Kasmi KC, Stenmark KR. The role of inflammation in hypoxic pulmonary hypertension: from cellular mechanisms to clinical phenotypes. Am J Physiol Lung Cell Mol Physiol. 2015;308:L229–252. doi: 10.1152/ajplung.00238.2014. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27.Soon E, Holmes AM, Treacy CM, Doughty NJ, Southgate L, Machado RD, et al. Elevated levels of inflammatory cytokines predict survival in idiopathic and familial pulmonary arterial hypertension. Circulation. 2010;122:920–927. doi: 10.1161/CIRCULATIONAHA.109.933762. [DOI] [PubMed] [Google Scholar]
- 28.Humbert M, Monti G, Brenot F, Sitbon O, Portier A, Grangeot-Keros L, et al. Increased interleukin-1 and interleukin-6 serum concentrations in severe primary pulmonary hypertension. Am J Respir Crit Care Med. 1995;151:1628–1631. doi: 10.1164/ajrccm.151.5.7735624. [DOI] [PubMed] [Google Scholar]
- 29.Selimovic N, Bergh CH, Andersson B, Sakiniene E, Carlsten H, Rundqvist B. Growth factors and interleukin-6 across the lung circulation in pulmonary hypertension. Eur Respir J. 2009;34:662–668. doi: 10.1183/09031936.00174908. [DOI] [PubMed] [Google Scholar]
- 30.Chaouat A, Savale L, Chouaid C, Tu L, Sztrymf B, Canuet M, et al. Role for interleukin-6 in COPD-related pulmonary hypertension. Chest. 2009;136:678–687. doi: 10.1378/chest.08-2420. [DOI] [PubMed] [Google Scholar]
- 31.Bhargava A, Kumar A, Yuan N, Gewitz MH, Mathew R. Monocrotaline induces interleukin-6 mRNA expression in rat lungs. Heart Dis. 1999;1:126–132. [PubMed] [Google Scholar]
- 32.Steiner MK, Syrkina OL, Kolliputi N, Mark EJ, Hales CA, Waxman AB. Interleukin-6 overexpression induces pulmonary hypertension. Circ Res. 2009;104:236–244, 228p following 244. doi: 10.1161/CIRCRESAHA.108.182014. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 33.Joppa P, Petrasova D, Stancak B, Tkacova R. Systemic inflammation in patients with COPD and pulmonary hypertension. Chest. 2006;130:326–333. doi: 10.1378/chest.130.2.326. [DOI] [PubMed] [Google Scholar]
- 34.Stevens T, Janssen PL, Tucker A. Acute and long-term TNF-alpha administration increases pulmonary vascular reactivity in isolated rat lungs. J Appl Physiol. 1992;73:708–712. doi: 10.1152/jappl.1992.73.2.708. [DOI] [PubMed] [Google Scholar]
- 35.Fujita M, Shannon JM, Irvin CG, Fagan KA, Cool C, Augustin A, et al. Overexpression of tumor necrosis factor-alpha produces an increase in lung volumes and pulmonary hypertension. Am J Physiol Lung Cell Mol Physiol. 2001;280:L39–49. doi: 10.1152/ajplung.2001.280.1.L39. [DOI] [PubMed] [Google Scholar]
- 36.Sutendra G, Dromparis P, Bonnet S, Haromy A, McMurtry MS, Bleackley RC, et al. Pyruvate dehydrogenase inhibition by the inflammatory cytokine TNFα contributes to the pathogenesis of pulmonary arterial hypertension. J Mol Med (Berl) 2011;89:771–783. doi: 10.1007/s00109-011-0762-2. [DOI] [PubMed] [Google Scholar]
- 37.Wang Q, Zuo XR, Wang YY, Xie WP, Wang H, Zhang M. Monocrotaline-induced pulmonary arterial hypertension is attenuated by TNF-α antagonists via the suppression of TNF-α expression and NF-κB pathway in rats. Vascul Pharmacol. 2013;58:71–77. doi: 10.1016/j.vph.2012.07.006. [DOI] [PubMed] [Google Scholar]
- 38.Mutschler D, Wikström G, Lind L, Larsson A, Lagrange A, Eriksson M. Etanercept reduces late endotoxin-induced pulmonary hypertension in the pig. J Interferon Cytokine Res. 2006;26:661–667. doi: 10.1089/jir.2006.26.661. [DOI] [PubMed] [Google Scholar]
- 39.Arnson Y, Shoenfeld Y, Amital H. Effects of tobacco smoke on immunity, inflammation and autoimmunity. J Autoimmun. 2010;34:J258–265. doi: 10.1016/j.jaut.2009.12.003. [DOI] [PubMed] [Google Scholar]
- 40.Oeckinghaus A, Hayden MS, Ghosh S. Crosstalk in NF-κB signaling pathways. Nat Immunol. 2011;12:695–708. doi: 10.1038/ni.2065. [DOI] [PubMed] [Google Scholar]
- 41.Li L, Wei C, Kim IK, Janssen-Heininger Y, Gupta S. Inhibition of nuclear factor-κB in the lungs prevents monocrotaline-induced pulmonary hypertension in mice. Hypertension. 2014;63:1260–1269. doi: 10.1161/HYPERTENSIONAHA.114.03220. [DOI] [PubMed] [Google Scholar]
- 42.Ogawa A, Firth AL, Yao W, Rubin LJ, Yuan JX. Prednisolone inhibits PDGF-induced nuclear translocation of NF-kappaB in human pulmonary artery smooth muscle cells. Am J Physiol Lung Cell Mol Physiol. 2008;295:L648–657. doi: 10.1152/ajplung.90245.2008. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 43.Fan J, Fan X, Li Y, Ding L, Zheng Q, Guo J, et al. Chronic Normobaric Hypoxia Induces Pulmonary Hypertension in Rats: Role of NF-κB. High Alt Med Biol. 2016;17:43–49. doi: 10.1089/ham.2015.0086. [DOI] [PubMed] [Google Scholar]
- 44.Obata H, Biro S, Arima N, Kaieda H, Kihara T, Eto H, et al. NF-kappa B is induced in the nuclei of cultured rat aortic smooth muscle cells by stimulation of various growth factors. Biochem Biophys Res Commun. 1996;224:27–32. doi: 10.1006/bbrc.1996.0979. [DOI] [PubMed] [Google Scholar]
- 45.Makarenko VV, Usatyuk PV, Yuan G, Lee MM, Nanduri J, Natarajan V, et al. Intermittent hypoxia-induced endothelial barrier dysfunction requires ROS-dependent MAP kinase activation. Am J Physiol Cell Physiol. 2014;306:C745–752. doi: 10.1152/ajpcell.00313.2013. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 46.Tuleta I, França CN, Wenzel D, Fleischmann B, Nickenig G, Werner N, et al. Hypoxia-induced endothelial dysfunction in apolipoprotein E-deficient mice; effects of infliximab and L-glutathione. Atherosclerosis. 2014;236:400–410. doi: 10.1016/j.atherosclerosis.2014.08.021. [DOI] [PubMed] [Google Scholar]
- 47.Aggarwal S, Gross CM, Sharma S, Fineman JR, Black SM. Reactive oxygen species in pulmonary vascular remodeling. Compr Physiol. 2013;3:1011–1034. doi: 10.1002/cphy.c120024. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 48.Fulton DJR, Li X, Bordan Z, Haigh S, Bentley A, Chen F, et al. Reactive oxygen and nitrogen species in the development of pulmonary hypertension. Anti-oxidants (Basel) 2017;6:1–22. doi: 10.3390/antiox6030054. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 49.Zuo L, Rose BA, Roberts WJ, He F, Banes-Berceli AK. Molecular characterization of reactive oxygen species in systemic and pulmonary hypertension. Am J Hypertens. 2014;27:643–650. doi: 10.1093/ajh/hpt292. [DOI] [PubMed] [Google Scholar]
- 50.Zhu J, Kovacs L, Han W, Liu G, Huo Y, Lucas R, et al. Reactive oxygen species-dependent calpain activation contributes to airway and pulmonary vascular remodeling in chronic obstructive pulmonary disease. Anti-oxid Redox Signal. 2019;31:804–818. doi: 10.1089/ars.2018.7648. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 51.Liu JQ, Zelko IN, Erbynn EM, Sham JS, Folz RJ. Hypoxic pulmonary hypertension: role of superoxide and NADPH oxidase (gp91phox) Am J Physiol Lung Cell Mol Physiol. 2006;290:L2–10. doi: 10.1152/ajplung.00135.2005. [DOI] [PubMed] [Google Scholar]
- 52.Jin H, Liu M, Zhang X, Pan J, Han J, Wang Y, et al. Grape seed procyanidin extract attenuates hypoxic pulmonary hypertension by inhibiting oxidative stress and pulmonary arterial smooth muscle cells proliferation. J Nutr Biochem. 2016;36:81–88. doi: 10.1016/j.jnutbio.2016.07.006. [DOI] [PubMed] [Google Scholar]
- 53.Joppa P, Petrásová D, Stancák B, Dorková Z, Tkácová R. Oxidative stress in patients with COPD and pulmonary hypertension. Wien Klin Wochenschr. 2007;119:428–434. doi: 10.1007/s00508-007-0819-y. [DOI] [PubMed] [Google Scholar]
- 54.Li C, Yan L, Xu J. Correlations between lipid ratio/oxidative stress status in COPD patients and pulmonary hypertension as well as prognosis. Zhong Nan Da Xue Xue Bao Yi Xue Ban. 2016;41:1168–1174. doi: 10.11817/j.issn.1672-7347.2016.11.009. [DOI] [PubMed] [Google Scholar]
- 55.Kluchová Z, Tkáčová R. The role of oxidative stress in lung injury induced by cigarette smoke. Biologia. 2006;61:643–650. [Google Scholar]
- 56.Yamaguchi Y, Nasu F, Harada A, Kunitomo M. Oxidants in the gas phase of cigarette smoke pass through the lung alveolar wall and raise systemic oxidative stress. J Pharmacol Sci. 2007;103:275–282. doi: 10.1254/jphs.fp0061055. [DOI] [PubMed] [Google Scholar]
- 57.Xiao F, Li X, Wang J, Cao J. Mechanisms of vascular endothelial cell injury in response to intermittent and/or continuous hypoxia exposure and protective effects of anti-inflammatory and anti-oxidant agents. Sleep Breath. 2019;23:515–522. doi: 10.1007/s11325-019-01803-9. [DOI] [PubMed] [Google Scholar]
- 58.Simonsen U, Christensen FH, Buus NH. The effect of tempol on endothelium-dependent vasodilatation and blood pressure. Pharmacol Ther. 2009;122:109–124. doi: 10.1016/j.pharmthera.2009.02.002. [DOI] [PubMed] [Google Scholar]
- 59.Bourgoin F, Bachelard H, Badeau M, Larivière R, Nadeau A, Pitre M. Effects of tempol on endothelial and vascular dysfunctions and insulin resistance induced by a high-fat high-sucrose diet in the rat. Can J Physiol Pharmacol. 2013;91:547–561. doi: 10.1139/cjpp-2012-0273. [DOI] [PubMed] [Google Scholar]
- 60.Hayakawa M, Miyashita H, Sakamoto I, Kitagawa M, Tanaka H, Yasuda H, et al. Evidence that reactive oxygen species do not mediate NF-kappaB activation. Embo j. 2003;22:3356–3366. doi: 10.1093/emboj/cdg332. [DOI] [PMC free article] [PubMed] [Google Scholar]