


Abstract
Background
Approximately 75% of hyperthyroid cats lose muscle mass as accessed with a muscle condition scoring (MCS) system. After treatment, MCS improves as the cats regain muscle mass.
Objectives
To quantify the degree of muscle loss in hyperthyroid cats using ultrasonography and evaluate changes in muscle mass after treatment.
Animals
Forty‐eight clinically normal cats and 120 cats with untreated hyperthyroidism, 75 of which were reevaluated after radioiodine‐131 therapy.
Methods
Prospective cross‐sectional and before‐after studies. All cats underwent ultrasonography and measurement of epaxial muscle height (EMH), with subsequent calculation of vertebral and forelimb epaxial muscle scores (VEMS and FLEMS). A subset of hyperthyroid cats underwent repeat muscle imaging 6 months after treatment.
Results
Untreated hyperthyroid cats had a lower EMH than did clinically normal cats (median [25th‐75th percentile], 0.98 [0.88‐1.16] cm vs 1.34 [1.23‐1.58] cm, P < .001). Seventy‐seven (64.2%) untreated cats had subnormal EMH. Similarly, compared to normal cats, hyperthyroid cats had lower VEMS (0.93 [0.84‐1.07] vs 1.27 [1.18‐1.39], P < .001) and FLEMS (1.24 [1.10‐1.35] vs 1.49 [1.39‐1.63], P < .001). After treatment, EMH increased (1.03 [0.89‐1.03] cm to 1.33 [1.17‐1.41] cm, P < .001), with abnormally low EMH normalizing in 36/41 (88%). Both VEMS (0.94 [0.87‐1.10] to 1.21 [1.10‐1.31], P < .001) and FLEMS (1.31 [1.17‐1.40] to 1.47 [1.38‐1.66], P < .001) also increased after treatment.
Conclusions and Clinical Importance
Almost two‐thirds of hyperthyroid cats have abnormally low muscle mass when measured quantitatively by ultrasound. Successful treatment restores muscle mass in >85% of cats. EMH provided the best means of quantitating muscle mass in these cats.
Keywords: 131I, cachexia, feline, muscle condition, radioactive iodine, sarcopenia, thyroid gland, ultrasound
Abbreviations
- 131I
radioiodine
- EMH
epaxial muscle height
- FLEMS
forelimb epaxial muscle score
- IQR
interquartile range
- MCS
muscle condition score
- T3
triiodothyronine
- T4
thyroxine
- TSH
thyroid‐stimulating hormone
- VEMS
vertebral epaxial muscle score
1. INTRODUCTION
Hyperthyroidism is a catabolic state that leads to loss of body weight because of decreases in both fat stores and lean body mass (primarily muscle). In untreated human patients, initial weight loss is predominantly caused by a loss of muscle mass, rather than loss of fat. 1 , 2 , 3 After successful treatment for hyperthyroidism, weight gain is expected but the pattern of recovery is reversed, with muscle mass being restored before fat deposits. 1 , 3 , 4 , 5 , 6 , 7
In cats, weight loss is the earliest and most common clinical feature of hyperthyroidism. 8 As in human hyperthyroid patients, this weight loss appears to be largely because of loss of muscle mass, affecting >75% of hyperthyroid cats in 1 study 9 when accessed clinically by use of a 4‐point muscle condition scoring (MSC) system. 10 , 11 Similar to human patients, the hyperthyroid cats' muscle condition scores improved after treatment, as the cats became euthyroid and regained their lost body weight. 9
The MSC system is a clinical, semiquantitative method based on physical assessment of a cat's muscle mass (ie, visualization and palpation of musculature over the spine, scapulae, skull, and pelvis). This can lead to problems of interobserver reproducibility. In 1 study designed to validate its accuracy in cats, this system had a good intra‐rater agreement (repeatability), but only fair inter‐rater agreement (reproducibility), especially for cats with mild to moderate muscle loss. 12 Similar findings are reported for the repeatability and reproducibility of MCS in dogs. 13 Therefore, although clinically useful in cats and dogs when performed by single observers, results are subjective and can vary when a cat is evaluated by multiple clinicians. In addition, MCS might not be precise enough for research studies, especially when the changes in muscle mass are small or if one is quantifying changes in muscle mass over time.
Several other more objective, quantitative techniques have been used to estimate body composition (specifically muscle mass) in cats, including deuterium oxide dilution, 14 , 15 bioelectrical impedance analysis, 16 , 17 , 18 magnetic resonance imaging, 15 computed tomography, 19 and dual‐energy X‐ray absorptiometry (DXA). 15 , 18 , 19 , 20 , 21 However, all of these methods have a cost disadvantage, typically require general anesthesia or heavy sedation, and have other limitations that make them less accurate for the measurement of muscle. 15 , 20 To more easily identify and quantitatively monitor the treatment of muscle wasting syndromes (eg, cachexia or sarcopenia), clinical investigators have sought an accurate, noninvasive method to assess muscle loss.
Recently, investigators have evaluated ultrasound imaging of muscle as a quantitative measure of muscle loss in humans, 22 , 23 , 24 dogs, 13 , 25 , 26 and cats. 27 , 28 In dogs and cats, investigators measured epaxial muscle height (EMH) from transverse ultrasonographic images obtained at the level of the 13th thoracic vertebrae (T13) and validated this approach in healthy cats and cats with various degrees of muscle loss. 13 , 25 , 26 , 27 , 28 The method displayed good repeatability and reproducibility.
In this study, we sought to quantify the prevalence and degree of muscle loss in untreated hyperthyroid cats using ultrasound imaging. We then prospectively followed a subset of these cats to examine the effects of successful radioiodine treatment on their muscle mass using ultrasound imaging.
2. MATERIALS AND METHODS
2.1. Study cohorts and study design
This study was conducted in 2 phases. The first phase was a prospective cross‐sectional study conducted from January 2018 to January 2021 that included both hyperthyroid cats referred to our clinic for evaluation before radioiodine treatment, and a cohort of clinically normal cats. The second phase was a before‐after study 29 , 30 involving a subset of the cats from the initial study that were reevaluated approximately 6 months after treatment with radioiodine.
2.1.1. Initial cross‐sectional study
Hyperthyroid cats
To be eligible for inclusion, hyperthyroid cats underwent a thorough evaluation that included review of the past medical record, detailed medical and dietary history, complete physical examination, routine laboratory testing (CBC and serum biochemical profile), and determination of a serum thyroid panel (thyroxine [T4], triiodothyronine [T3], free T4 [fT4], and thyroid stimulating hormone [TSH]). 31 , 32 All study cats also underwent quantitative thyroid scintigraphy, which was used as the reference standard to confirm hyperthyroidism. 33 , 34 , 35 We excluded cats if they had received methimazole within 15 days of evaluation or if they had concurrent nonthyroidal disease, such as azotemia (Figure 1).
FIGURE 1.
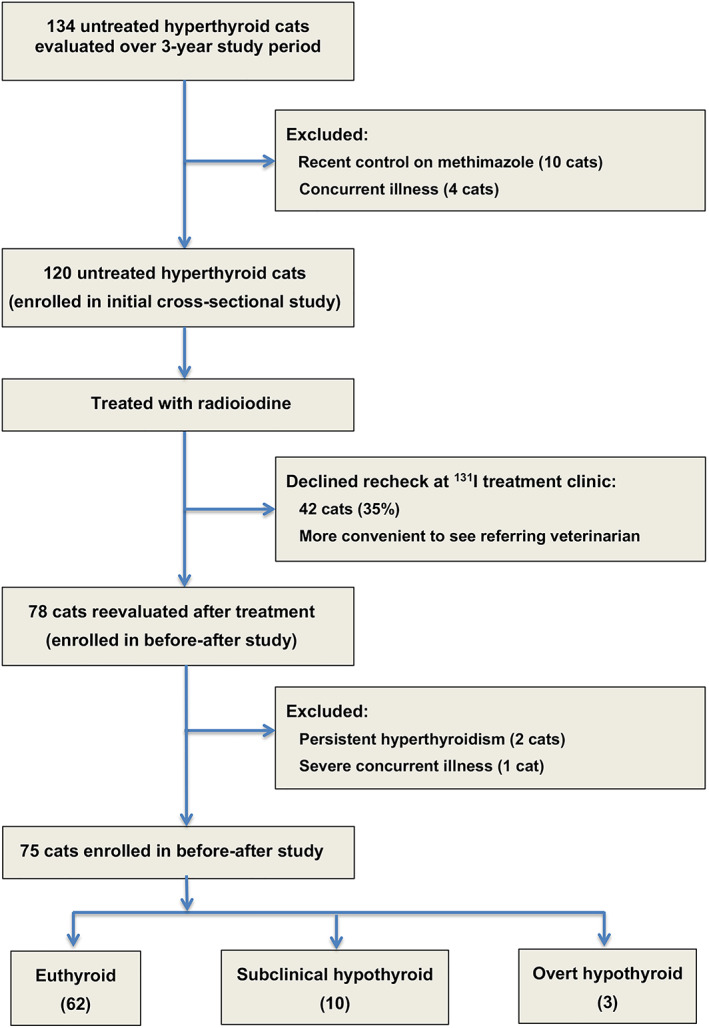
Flowchart for enrollment of hyperthyroid cats, into study 1 (cross‐sectional study of untreated cats) and study 2 (before‐after treatment)
On the day of treatment with radioiodine (131I), a single investigator (PX) weighed each cat and assigned a body condition score (BCS; 9‐point scale) and muscle condition score (MCS; 4‐point scale). 10 , 11 A right lateral radiograph (centered over the 4th thoracic vertebrae) was then obtained using a computed radiography system (Neovet V210, Sedecal, Madrid, Spain). One investigator (SIS) measured the length of the 4th thoracic vertebrae using the line tool on a DICOM workstation (CR 30‐XB, Agfa Healthcare, Mortsel, Belgium); the vertebrae length was measured 3 times, and the results averaged, as previously described. 27 , 28 The same investigator (SIS) also measured the forelimb circumference at the approximate midpoint between the carpus and elbow joints of the left hand of each cat. 27 , 28
Ultrasonographic measurements were next obtained at the level of 13th thoracic vertebrae with a 7.5 to 12 MHz, multifrequency, 50 mm linear transducer (LOGIQ P5, GE Healthcare, Jiangsu, China). For this procedure, cats were gently restrained in a crouching position during the measurements. The ultrasound transducer was placed at the level of the 13th thoracic vertebrae, with the beam angle perpendicular to the longitudinal axis of the vertebral column, at the level of the articulation of the transverse process of the vertebra with the rib (ie, costotransverse joint), as previously described. 27 , 28 A single investigator (PX) measured epaxial muscle height (EMH) 3 times (a separate placement of the probe for each measurement), and the results were averaged.
To address differences in size of our cats, EMH was also normalized on the basis of 4th thoracic vertebral length and forelimb circumference 25 , 26 , 27 , 28 by calculating ratios for the vertebral epaxial muscle score (VEMS) and forelimb epaxial muscle score (FLEMS), as follows:
and
Clinically normal, euthyroid cats
Clinically normal cats were recruited as controls at the time of visit for routine evaluation. To be enrolled in the study, these cats had to be ≥7 years of age and considered healthy by their owners. None of these cats had any history or clinical signs suggestive of disease, and all were normal on physical examination. These cats also were evaluated by routine laboratory testing (CBC, serum biochemical profile, and complete urinalysis) and had serum T4 and TSH concentrations measured to exclude hyperthyroidism and other non‐thyroidal disease.
All clinically normal cats underwent thoracic radiography, forelimb circumference measurement, and muscle ultrasound measurements as described above. We used the measurements from these clinically normal cats to compare to those in the untreated hyperthyroid cats, as well as to calculate clinic‐specific reference intervals for EMH, VEMS, and FLEMS (see Section 2.2, below).
2.1.2. Before‐after study of hyperthyroid cats treated with radioiodine
A subset of hyperthyroid cats evaluated in the initial cross‐sectional study were reevaluated approximately 6 months after treatment with radioiodine (Figure 1). These cats again underwent a thorough evaluation which included a review of the medical history since the time of 131I treatment, complete physical examination, routine laboratory testing (CBC and serum biochemical profile), and determination of serum T4 and TSH concentrations. Based on these results, we classified the cats' thyroid status into 1 of 4 categories: euthyroid (T4, 1.0‐3.8 μg/dL; TSH ≤0.30 ng/mL), subclinically hypothyroid (T4, 1.0‐3.8 μg/dL; TSH > 0.30 ng/mL), overtly hypothyroid (T4 < 1.0 μg/dL; TSH > 0.30 ng/mL), and persistently hyperthyroid (T4, ≥ 3.9 μg/dL; TSH < 0.30 ng/mL), as previously described. 36 , 37 , 38 Cats that remained hyperthyroid were excluded from this part of the study (Figure 1).
The primary investigator reweighed all eligible study cats and assigned a BCS and MCS. All cats then underwent repeat muscle ultrasound and forelimb circumference measurement, as described above, without knowledge of the cats' pretreatment values. We did not repeat the chest radiography or remeasure the length of the 4th thoracic vertebrae but used the original length to calculate the VEMS.
2.2. Data and statistical analyses
Data were assessed for normality by the D'Agostino‐Pearson test and by visual inspection of graphical plots. 39 Data were not normally distributed; therefore, all analyses used nonparametric tests. Results for continuous data (eg, EMH, VEMS, FLEMS) are expressed as median (interquartile range, [IQR], 25th‐75th percentile) and are represented graphically as box‐and‐whisker plots (Turkey method). 40
Reference intervals (RI) for EMH, forelimb circumference, VEMS, and FLEMS were established by the robust method using Box‐Cox transformed data from the results of our 48 clinically normal cats (Table 1). 41 , 42 The 90% confidence intervals (CI) for the upper and lower limits of the RI were also calculated.
TABLE 1.
Reference interval (RI) values for the epaxial muscle height (EMH), length of the 4th thoracic vertebrae, vertebral epaxial muscle score (VEMS), and forelimb epaxial muscle score (FLEMS) determined in 48 clinically normal, euthyroid cats
| Variable | Median (IQR) | Lower limit of RI (90% CI) | Upper limit of RI (90% CI) |
|---|---|---|---|
| Epaxial muscle height (cm) | 1.34 (1.23‐1.58) | 1.05 (1.00‐1.10) | 1.81 (1.70‐1.89) |
| Length of 4th thoracic vertebrae (cm) | 1.07 (1.03‐1.13) | 0.92 (0.89‐0.95) | 1.20 (1.18‐1.22) |
| Forelimb circumference (cm) | 9.05 (8.50‐9.95) | 7.07 (6.65‐7.56) | 10.97 (10.64‐11.27) |
| Vertebral epaxial muscle score | 1.27 (1.18‐1.39) | 0.98 (0.93‐1.03) | 1.65 (1.57‐1.72) |
| Forelimb epaxial muscle score | 1.49 (1.39‐1.63) | 1.17 (1.11‐1.23) | 1.96 (1.83‐2.07) |
Abbreviations: CI, confidence interval; IQR, interquartile range (25th‐75th percentile); RI, reference interval.
In our initial cross‐sectional study, we compared continuous variables between hyperthyroid and clinically normal cat groups by the Mann‐Whitney U‐test. In the subgroup of hyperthyroid cats that were reevaluated after successful treatment with radioiodine, we compared the before‐and‐after variable groups by the Wilcoxon signed ranks test.
BCSs were determined on a 9‐point scale, with a score of 5/9 designating an ideal body weight, scores of ≤4/9 being underweight and ≥6/9 being overweight. 10 For analysis, MCS ordinal categories were converted to numerical values, as follows: 3 = normal muscle mass, 2 = mild muscle loss, 1 = moderate muscle loss, and 0 = severe muscle loss. Relationships between body weight and MCS and muscle parameters (eg, EMH, VEMS, FLEMS) were tested with Spearman correlation analyses.
For all analyses, statistical significance was defined as P ≤ .05. All statistical analyses were performed using proprietary software (GraphPad Prism, version 9.3.1; GraphPad Software, La Jolla, CA; MedCalc, version 19.2, MedCalc Statistical Software, Ltd, Ostend, Belgium).
3. RESULTS
3.1. Initial cross‐sectional study (untreated hyperthyroid cats and clinically normal cats)
3.1.1. Characteristics of cat study groups
Hyperthyroid cats
During the 3‐year study period, we evaluated 134 hyperthyroid cats, of which 120 met the eligibility requirements (Figure 1). The 120 cats ranged in age from 7 to 20 years (median, 13 years; IQR, 11‐15 years). Breeds included domestic longhair and shorthair (n = 107; 87.5%), Siamese (6), Persian (4), Maine Coon (1), Ragdoll (1), and Norwegian Forest cat (1). Of these, 60 (50%) were male and 60 were female; all had been neutered.
The time from diagnosis of hyperthyroidism to 131I treatment ranged from 2 days to 4.8 years (median, 74 days; IQR, 40‐205 days). Thirty‐five of the 120 cats (29%) had been treated with methimazole within 3 months of our evaluation, but only 15 cats became euthyroid and 20 remained hyperthyroid on the drug. In all 35 methimazole‐treated cats, the drug was discontinued ≥2 weeks before evaluation and treatment with 131I.
Body weight ranged from 2.0 to 7.5 kg (median, 3.7 kg; IQR, 3.1‐4.9 kg); 51 (42.5%) cats were considered underweight, 48 (40%) had an ideal BCS, and 21 (17.5%) were considered overweight. Of the 120 cats with untreated hyperthyroidism, 25 (20.8%) cats had a normal MCS, whereas mild, moderate, and severe muscle loss was recorded in 35 (29.2%), 41 (34.2%), and 19 (15.8%), respectively.
Hyperthyroid cats had high serum concentrations of T4 (median, 10.6 μg/dL, IQR, 7.0‐13.5 mg/dL) and T3 (median, 155, IQR, 93‐250 ng/dL), whereas the serum TSH concentration was below the limit of detection (<0.03 ng/mL) in 117 (98.5%) cats. On thyroid scintigraphy, 60 (50%) hyperthyroid cats had unilateral thyroid disease, 58 cats had bilateral disease, and 2 had multifocal disease (ie, ≥3 separate tumor nodules or areas of distinctly increased radionuclide uptake). 33 , 34 All hyperthyroid cats had a high thyroid uptake of the injected pertechnetate, as evidenced by high thyroid‐to‐salivary gland ratio (median, 6.7; IQR, 4.6‐11.1; reference interval <1.5).
Clinically normal, euthyroid cats
The 48 cats ranged in age from 7 to 17 years (median, 10 years; IQR, 9‐13 years). Breeds included domestic longhair and shorthair (43 cats; 89.6%), Persian (2 cats), Siamese (2 cat), and Sphinx (1 cat). Of these cats, 25 (52%) were male and 23 were female; all had been neutered.
Body weight ranged from 3.4 to 9.9 kg (median, 5.3 kg; IQR, 4.5‐6.2 kg); none of the cats were considered underweight, 34 (71%) had an ideal BCS (5/9), and 14 (29%) were considered overweight (BCS ≥ 6). All clinically normal cats had a normal MCS (3/3 score). All normal cats had serum T4 concentrations within reference interval (median 1.9; IQR, 1.2‐3.2 μg/dL).
Compared with the hyperthyroid cats, the clinically normal cats were younger (P < .001), weighed more (P < .001), had higher BCSs (P < .001), and had high MCSs (P < .001), with no difference in breed (P > .99) or sex distribution (P = .9). The clinically normal cats had lower serum T4 concentrations (P < .001).
3.1.2. Epaxial muscle height, vertebral epaxial muscle score, and forelimb epaxial muscle score
Epaxial muscle height
The untreated hyperthyroid cats had a lower epaxial muscle height (EMH) than did clinically normal euthyroid cats (median, 0.98 vs 1.34 cm, P < .001; Figure 2). Seventy‐seven (64.2%) of the 120 untreated cats had a subnormal EMH. Of the 43 cats with a normal EMH, 30 (69.8%) had low‐normal values (ie, below the lowest quartile of the reference interval; <1.24 cm; Table 1 and Figure 2).
FIGURE 2.
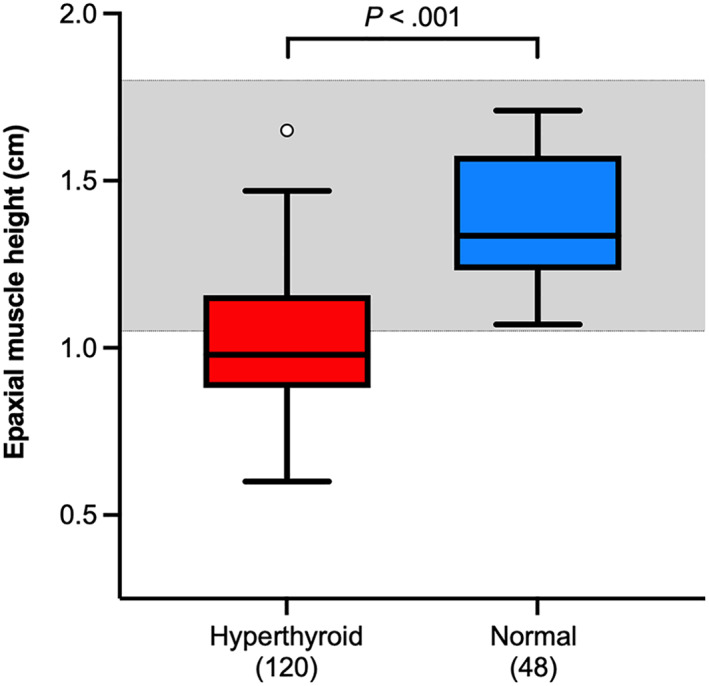
Boxplots of the epaxial muscle height (EMH) in 120 untreated hyperthyroid cats and 48 clinically normal euthyroid cats. Boxes represent the interquartile range from the 25th to 75th percentile. The horizontal bar in each box represents the median value. The whiskers indicate the range of data values unless outliers are present, in which case the whiskers extend to a maximum of 1.5 times the interquartile range. 40 Such outlying data points are represented by open circles. The shaded area indicates the reference interval
Length of 4th thoracic vertebrae and forelimb circumference
Hyperthyroid cats had a length of 4th thoracic vertebrae not different from that of euthyroid cats (median, 1.06 vs 1.07 cm; P = .5; Figure 3), but a forelimb circumference less than that of euthyroid cats (8.2 vs 9.1 cm; P < .001; Figure 4). Eighteen (15%) of the 120 untreated hyperthyroid cats had a forelimb circumference below the reference limit for normal cats.
FIGURE 3.
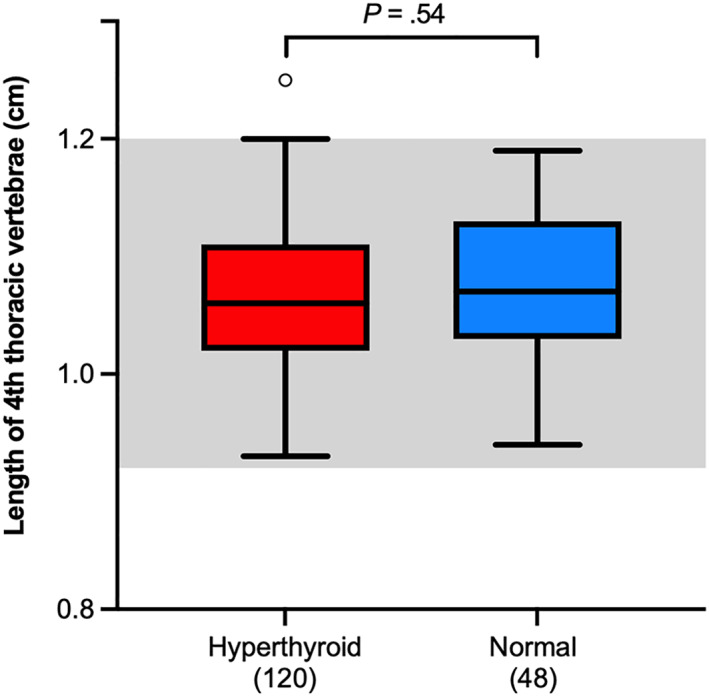
Boxplots of the length of the 4th thoracic vertebrae in 120 untreated hyperthyroid cats and 48 clinically normal euthyroid cats. See Figure 2 for key
FIGURE 4.
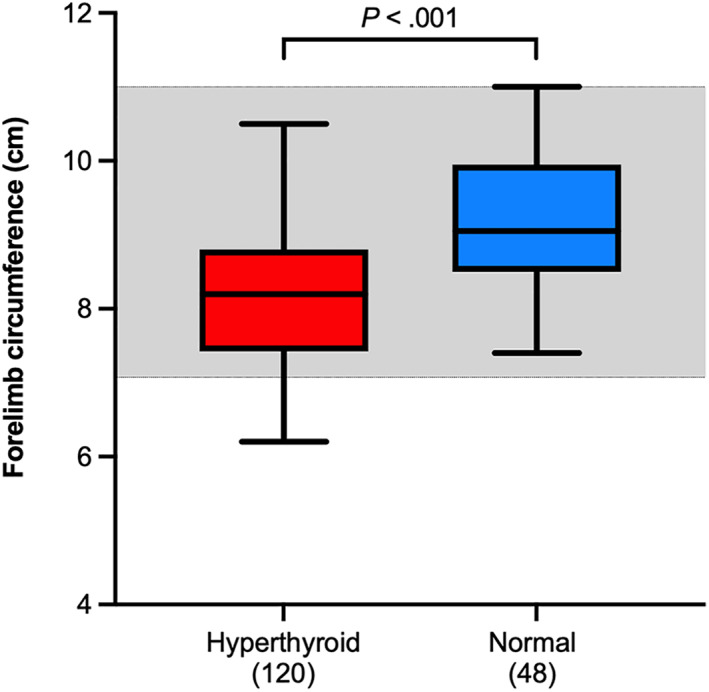
Boxplots of the forelimb circumference in 120 untreated hyperthyroid cats and 48 clinically normal euthyroid cats. See Figure 2 for key
Vertebral epaxial muscle score
Hyperthyroid cats had a lower vertebral epaxial muscle score (VEMS) than did clinically normal euthyroid cats (median, 0.93 vs 1.27 cm, P < .001; Figure 5). Seventy‐seven (64.2%) hyperthyroid cats had a low VEMS; 72 of these 77 cats also had a low EMH. Of the 43 cats with a normal VEMS, 31(72.1%) cats had a low‐normal VEMS (ie, below the lowest quartile of the reference interval; <1.15 cm; Table 1 and Figure 5); 29 of these 31 cats also had a low to low‐normal EMH.
FIGURE 5.
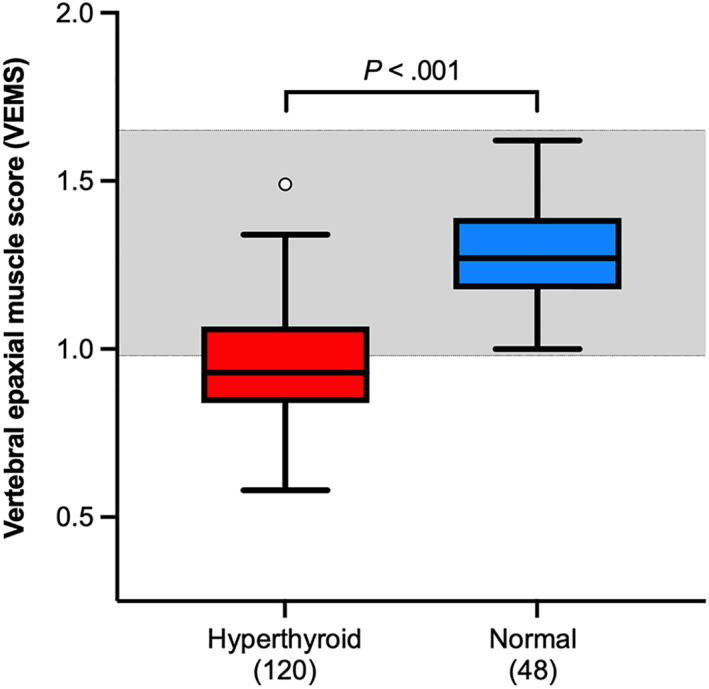
Boxplots of the vertebral epaxial muscle score (VEMS) in 120 untreated hyperthyroid cats and 48 clinically normal euthyroid cats. See Figure 2 for key
Forelimb epaxial muscle score
Hyperthyroid cats had a lower forelimb epaxial muscle score (FLEMS) than did clinically normal euthyroid cats (median, 1.24 vs 1.49 cm, P < .001; Figure 6). Forty‐two (35%) hyperthyroid cats had a low FLEMS; of these, all 42 also had a low EMH and 39/42 had a low VEMS. Of the 78 cats with normal FLEMS, 52 (66.7%) cats had a low‐normal FLEMS (ie, below the lowest quartile of the reference interval; <1.36 cm; Table 1 and Figure 6); 50 of these 52 cats also had low or low‐normal values for EMH and VEMS.
FIGURE 6.
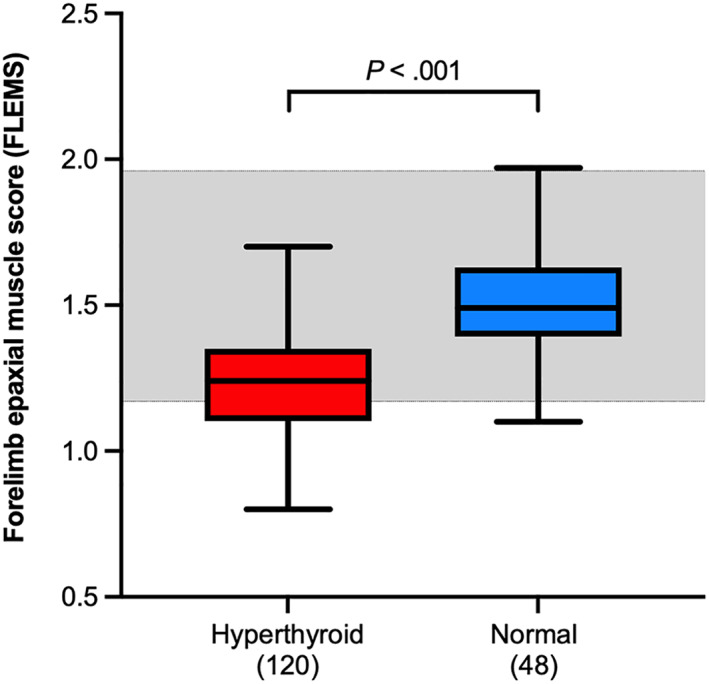
Boxplots of the forelimb epaxial muscle score (FLEMS) in 120 untreated hyperthyroid cats and 48 clinically normal euthyroid cats. See Figure 2 for key
3.2. Before‐and‐after study of hyperthyroid cats treated with radioiodine
3.2.1. Characteristics of the hyperthyroid cat subgroup studied before‐after treatment
Seventy‐five of the 120 cats underwent re‐evaluation 197 days (IQR, 182‐213 days) after treatment with 131I. These cats ranged in age from 7 to 20 years (median, 13 years; IQR, 11‐14 years). Breeds included domestic longhair and shorthair (n = 67; 89.3%), Siamese (4), Persian (2), Ragdoll (1), and Norwegian Forest cat (1). Of these, 40 (53%) were male and 35 were female; all had been neutered.
Body weight, BCS, and MCS all increased in the 75 131I‐treated cats (Table 2). Of the 32 cats that were underweight before treatment, only 6/75 (8%) remained underweight, whereas 24/75 (32%) were considered overweight. Before treatment, 57 (76%) of these cats had low MC, whereas only 16 (28%) cats were still considered to have mild to moderate muscle loss (low MCSs) on physical examination after 131I treatment.
TABLE 2.
Median (IQR) values for body weight, body condition score (BCS), muscle condition scores (MCS), and serum concentrations of T4, TSH, and creatinine in 75 hyperthyroid cats studied before and after treatment with radioiodine (131I)
| Variable | Before treatment | 131I‐treated | P value |
|---|---|---|---|
| Body weight (kg) | 4.0 (3.1‐5.0) | 4.75 (3.8‐5.9) | P < .001 |
| Body condition score a | 4 (3‐5) | 5 (5‐7) | P < .001 |
| Muscle condition score b | 2 (1‐3) | 3 (2.5‐3) | P < .001 |
| Serum T4 (μg/dL) | 10.5 (7.0‐13.4) | 1.7 (1.3‐2.3) | P < .001 |
| Serum TSH (ng/mL) c | 0.02 (0.02‐0.02) | 0.06 (0.02‐0.22) | P < .001 |
| Serum creatinine (mg/dL) | 0.9 (0.7‐1.1) | 1.5 (1.2‐1.9) | P < .001 |
Abbreviation: IQR, interquartile range (25th‐75th percentile).
BCS on 9‐point scale (5 = ideal weight, ≤4 underweight, and ≥6 overweight).
MCS on 4‐point scale (3 = normal muscle condition, 2 = mild loss, 1 = moderate loss, and 0 = severe muscle loss).
All serum TSH concentrations below the level of detection (<0.03 ng/mL) were assigned a value of 0.02 ng/mL.
Serum T4 concentrations were lower after 131I treatment, whereas serum TSH concentrations were within the reference interval (Table 2). Sixty‐two (82.7%) the 75 cats became euthyroid, 10 (13.3%) developed subclinical hypothyroidism (ie, normal serum T4 with high TSH concentrations) and 3 (4%) developed overt hypothyroidism (ie, low serum T4 with high TSH concentrations). Serum creatinine concentrations also increased after 131I treatment (Table 2), with 13 (17.3%) of the 75 cats becoming azotemic (serum creatinine >2.0 mg/dL).
3.2.2. EMH, VEMS, and FLEMS (before‐after cat study)
Epaxial muscle height
The EMH increased after 131I treatment (median, 1.03 vs 1.33 cm, P < .001; Figure 7). Thirty‐six (87.8%) the 41 hyperthyroid cats with low pretreatment EMH dimensions normalized their EMH after 131I treatment. The 41 cats that had low EMH values before treatment showed a greater increase in muscle thickness after 131I treatment than did the 34 cats that had EMH within the reference interval before treatment (0.28 vs 0.15 cm; P = .001).
FIGURE 7.
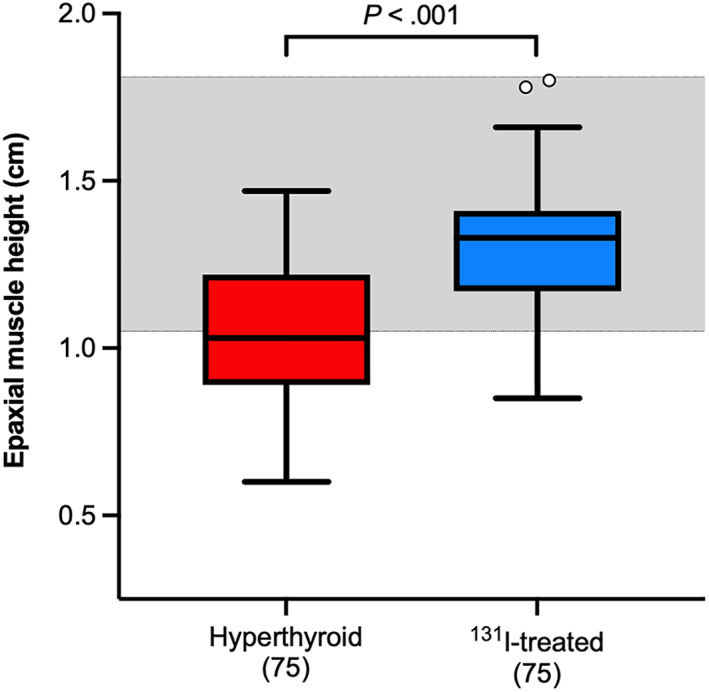
Boxplots of the epaxial muscle height (EMH) in 75 hyperthyroid cats evaluated before and after treatment with radioiodine. See Figure 2 for key
Vertebral epaxial muscle score
VEMS increased after treatment (median, 0.94 vs 1.21 cm, P < .001; Figure 8). Thirty‐seven (88.1%) the 42 hyperthyroid cats with low VEMS before treatment normalized their VEMS after 131I treatment. The 42 cats with low pretreatment VEMS before treatment showed a greater increase in score values after 131I treatment than did the 33 cats with that had VEMS within the reference interval before treatment (0.27 vs 0.10; P < .001).
FIGURE 8.
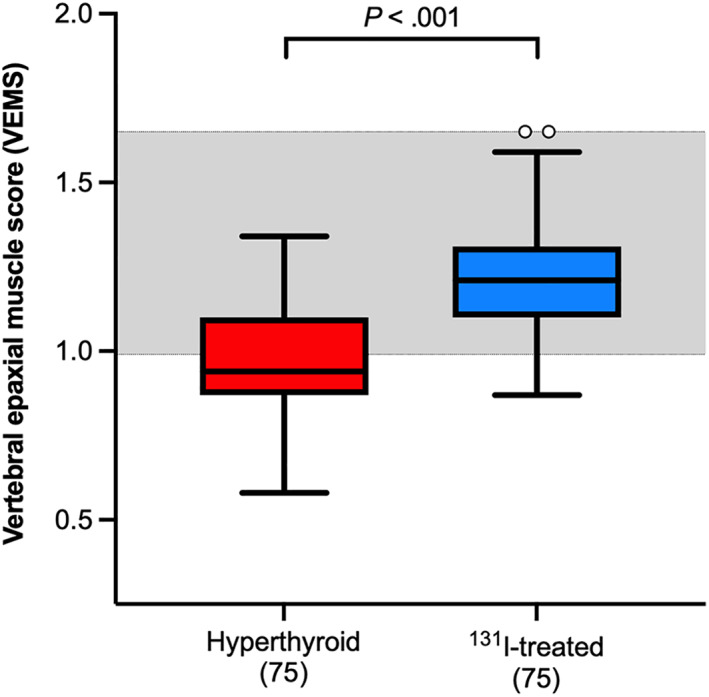
Boxplots of the vertebral epaxial muscle score (VEMS) in 75 hyperthyroid cats evaluated before and after treatment with radioiodine. See Figure 2 for key
Forelimb circumference
In the 48 hyperthyroid cats evaluated both before and after treatment, forelimb circumference increased from a median value of 8.5 vs 9.2 cm (P < .001; Figure 9). Before treatment, 6 (13%) of the 48 hyperthyroid cats had a small forelimb circumference; all normalized after 131I treatment.
FIGURE 9.
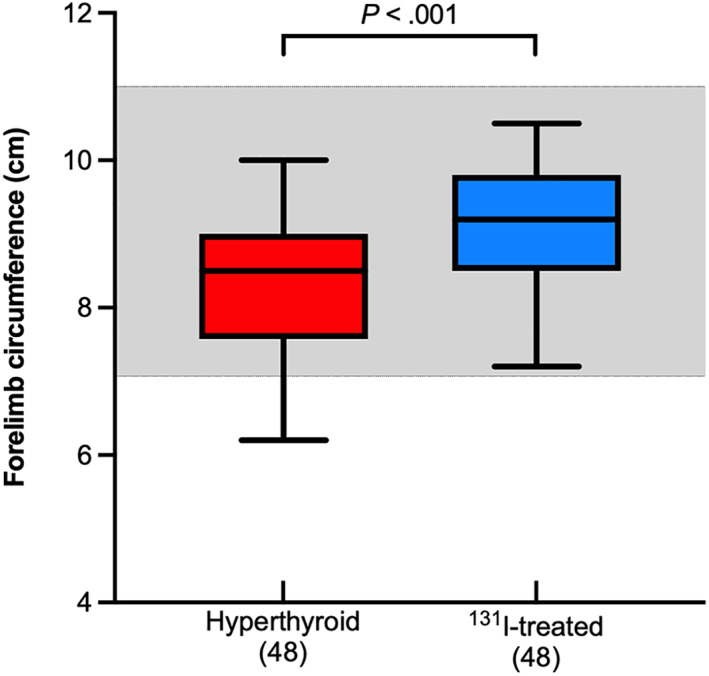
Boxplots of the forelimb circumference in 45 hyperthyroid cats evaluated before and after treatment with radioiodine. See Figure 2 for key
Forelimb epaxial muscle score
FLEMS increased after treatment (median, 1.31 vs 1.47 cm, P < .001; Figure 10). Of the 48 hyperthyroid cats evaluated, all 8 cats with a low FLEMS before treatment normalized this score after 131I treatment.
FIGURE 10.
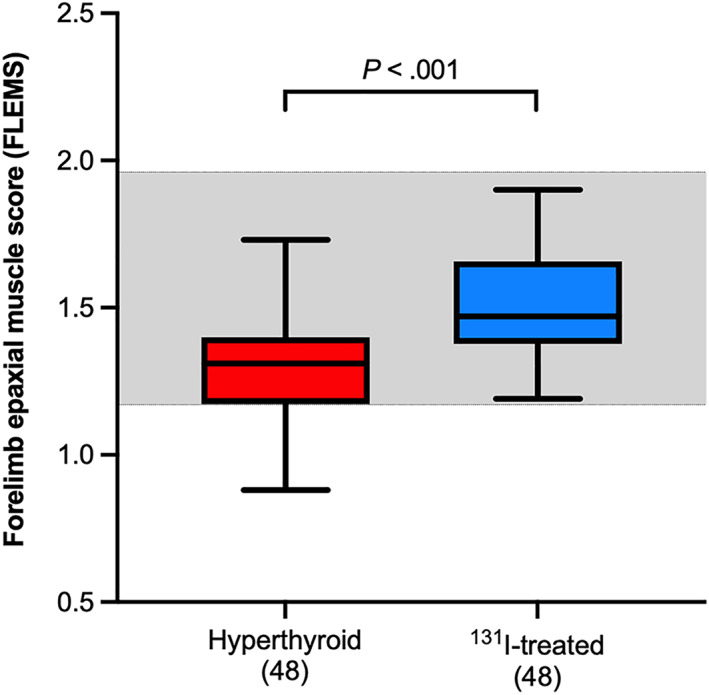
Boxplots of the forelimb epaxial muscle score (FLEMS) in 48 hyperthyroid cats evaluated before and after treatment with radioiodine. See Figure 2 for key
3.2.3. EMH, VEMS, and FLEMS in euthyroid and hypothyroid cats after 131I treatment
When the 75 131I‐treated cats were divided into euthyroid and hypothyroid groups, the 62 euthyroid cats had a EMH that was similar to the EMH in the 13 hypothyroid cats (median [25th‐75th percentile], 1.34 [1.15‐1.41] cm vs 1.28 [1.18‐1.50] cm; P = .6). The euthyroid cats also had similar VEMSs to that of the 13 hypothyroid cats (median, 1.21 [1.08‐1.30] vs 1.15 [1.08‐1.38] cm; P = .3), as well as similar FLEMSs (median, 1.47 [1.39‐1.66] vs 1.44 [1.21‐1.68]; P = .6).
3.2.4. EMH, VEMS, and FLEMS in azotemic and non‐azotemic cats after 131I treatment
When the 75 131I‐treated cats were divided into azotemic and non‐azotemic groups, the 13 azotemic cats (defined as serum creatinine >2.0 mg/dL) had a higher creatinine concentration than did the 62 non‐azotemic cats (median [25th‐75th percentile], 2.7 [2.1‐3.2] mg/dL vs 1.4 [1.2‐1.6] mg/dL; P < .001). The 13 azotemic cats had a posttreatment EMH that did not differ from the EMH in the 62 non‐azotemic cats (median, 1.18 [1.03‐1.44] cm vs 1.35 [1.18‐1.41] cm; P = .1). The azotemic cats also had similar VEMSs to that of the non‐azotemic cats (median, 1.14 [1.04‐1.34] vs 1.22 [1.13‐1.31]; P = .3), as well as similar FLEMSs (median, 1.44 [1.19‐1.81] vs 1.47 [1.41‐1.65]; P = .7).
3.3. Relationship between body weight and MCS to EMH, VEMS, and FLEMS
3.3.1. Clinically normal cats
In the 48 clinically normal cats, body weight was positively correlated with EMH (r = .48; 95% CI, 0.22‐0.68; P < .001). However, body weight did not correlate with either VEMS (r = .26; 95% CI, −0.03‐0.51; P = 0.07), or FLEMS (r = .08; 95% CI, −0.02‐0.37; P = 0.6).
3.3.2. Hyperthyroid cats
In the 120 hyperthyroid cats studied before treatment, body weight was positively correlated with EMH (r = .67; 95% CI, 0.55‐0.76; P < .001), as well as with VEMS (r = .52; 95% CI, 0.37‐0.64; P < .001) and FLEMS (r = .38; 95% CI, 0.21‐0.53; P < .001). Similarly, when the pre‐ and posttreatment variables from the 75 131I‐treated cats were analyzed, body weight remained correlated with EMH (r = .71; 95% CI, 0.62‐0.78; P < .001), VEMS (r = .58; 95% CI, 0.46‐0.68; P < .001), and FLEMS (r = .43; 95% CI, 0.27‐0.57; P < .001).
The MCSs of the 120 untreated cats correlated with EMH (r = .75; 95% CI, 0.66‐0.82; P < .001), VEMS (r = .74; 95% CI, 0.65‐0.82; P < .001), and FLEMS (r = .59; 95% CI, 0.46‐0.70; P < .001). Similarly, MCSs of the 131I‐treated cats also correlated with EMH (r = .59; 95% CI, 0.42‐0.73; P < .001), VEMS (r = .66; 95% CI, 0.50‐0.77; P < .001), and FLEMS (r = .44; 95% CI, 0.17‐0.65; P < .001).
When the prevalence of muscle loss using MCS and EMH measurements were compared, we identified more hyperthyroid cats with muscle loss using MCS than EMH. Of the 120 untreated cats, 95 (79.2%) had low MCSs, whereas 75 (62.5%) had low EMH (P = .007) All 20 of these discordant cats (ie, low MCS with normal EMH) had EMH values that were within the lower quartile of the reference interval (ie, low‐normal values for EMH). However, of the 25 hyperthyroid cats judged to have normal muscle mass with MCS, 3 (12%) had low EMH when measured by ultrasound. Therefore, although the MCSs correlated well with the EMH values, 23 (19.2%) of the 120 untreated cats had discordant values.
4. DISCUSSION
We found that about two‐thirds of hyperthyroid cats have mild to severe muscle loss when quantified by ultrasound muscle imaging. This finding is similar to the 75% prevalence of muscle loss reported in hyperthyroid cats evaluated clinically with a subjective muscle condition scoring system. 9 After successful 131I treatment, over 90% of cats with muscle wasting regained lost muscle mass, as demonstrated by normalization of their epaxial muscle height. Therefore, this study also confirms that successful treatment of hyperthyroidism will improve or resolve muscle loss in most cats. 9
The MCS system involves a subjective, physical assessment of a cat's muscle mass, which includes visualization and palpation of the musculature over the spine, scapulae, skull, and pelvis, with results reported as normal muscle or mild, moderate, or severe muscle loss. 10 , 11 In contrast, ultrasound imaging, as performed in this study, is a quantitative measure of muscle mass but obviously takes more time to perform than muscle condition scoring. However, ultrasound is a non‐invasive method that can be readily performed in clinical practice without the need for anesthesia or purchase of additional, expensive equipment.
In our study, MCSs of our hyperthyroid cats correlated well with epaxial muscle measurements obtained with ultrasound imaging, similar to results of a recent study of 40 cats with nonthyroidal illness (eg, because of CKD, neoplastic, cardiac, or hepatic disease). 28 Quantitative ultrasound imaging, however, appears to be a more accurate measurement of muscle mass than the qualitative clinical MCS system for assessment of muscle loss. This is especially true in cats with early or mild muscle loss, when the clinical MCS system is less accurate. 28 Overall, muscle ultrasound provides a clinically feasible method for easily detecting and quantifying early muscle loss, as well as for monitoring changes in a cat's muscle mass over time. As an outcome measure, quantitative ultrasound is certainly recommended over MCSs for use in research studies, particularly when the small changes in muscle mass need to be detected.
We used a described protocol for ultrasound muscle imaging of cats 27 , 28 and dogs. 13 , 25 , 26 In those studies, investigators normalized epaxial muscle height (EMH) to vertebral length or forelimb circumference to address differences in the size and weight of individual dogs and cats. 25 , 26 , 27 Although this appeared to be useful in dogs and clinically normal cats, 13 , 26 , 27 neither vertebral size nor forelimb circumference (and subsequent calculation of VEMS and FLEMS, respectively) were able to effectively normalize EMH in a recent study of cats with nonthyroidal illness. 28 Similarly, we also found that neither vertebral size nor forelimb circumference helped normalize EMH in our hyperthyroid cats, evidenced by the fact that VEMS and FLEMS correlated with body weight in both our untreated and treated hyperthyroid cats. This indicates that body weight alone accounts for at least some of the increases in these muscle scores. It is likely that, because the size and body weights of most cats are similar, such adjustments (ratios) are not needed and that use of EMH alone is adequate. In support of that, the vertebral length in our normal and hyperthyroid cats ranged from only 0.93 to 1.25 cm, with a median length of 1.07 cm. Therefore, to calculate the VEMS, EMH was essentially divided by a denominator of 1, which did not normalize the EMH as effectively as in previous studies. 13 , 26 , 27 Obviously, further studies need to be done in clinically normal cats, hyperthyroid cats, and cats with nonthyroidal illness to address which indices (EMH or VEMS) is most accurate.
We found the use of forelimb circumference as a potential means of normalizing EMH in hyperthyroid cats to be even more problematic than VEMS. The forelimb circumference of our untreated hyperthyroid cats was ~1 cm smaller than that of clinically normal cats (Figure 4), indicating that weight loss likely contributed to the smaller forelimb circumference in hyperthyroid cats. After 131I treatment, forelimb circumference increased and normalized in all of these cats as they gained weight (Figure 9). Given that the basis of normalizing requires a fixed (unchanging) constant against which to index, these marked changes in before‐after forelimb circumference (denominator) makes use of this ratio questionable. In untreated hyperthyroid cats, the smaller forelimb circumference would tend to falsely increase the apparent FLEMS value, whereas the increase in forelimb circumference that developed after successful treatment would tend to mask the associated increase in muscle thickness (because the numerator and denominator are both increasing).
Overall, EMH alone appeared to be the best quantitative indices for quantitating muscle mass with ultrasound imaging, at least in cats with hyperthyroidism. This deduction agrees with the conclusions of a study of cats with nonthyroidal illness, 28 in which EMH provided the best means of assessing and monitoring muscle mass in cats.
In this study, we identified more cats with muscle loss using MCS than EMH (≈80% vs 65%). However, most of these discordant cats (ie, mild to moderate muscle loss with MCS, but normal EMH), had EMH measurements that were within the lower quartile of the reference interval (ie, low‐normal values for EMH), similar to findings in muscle wasted cats with nonthyroidal illness. 28 Our overestimation of muscle loss with subjective MCSs compared to ultrasound measurement occurred both in the untreated hyperthyroid cats and the cats treated successfully with 131I. We also had a few discordant cats that had normal MCSs but clearly low EMH values, highlighting the subjective nature of the clinical MCS system. The primary aims of this study were not to compare MCS to ultrasound measurements of muscle mass. It is important to realize that all MCSs were assigned by a single investigator in this study, and that other clinicians would have likely assigned different MCSs to many of our cats, which might have correlated better or worse to their EMH measurements.
We did not study the biological variation in EMH in this study, but our findings suggest that some cats might simply be more muscular than others. In other words, some hyperthyroid cats will lose small to moderate amounts of muscle mass but still maintain EMH within the established reference interval. After the hyperthyroid state resolves, these cats regain lost muscle mass, with their low‐normal EMH values increasing into the mid‐normal or even high‐normal reference interval.
The present study had several important limitations. First, no reference standard for determining muscle mass was used in this study, so the true accuracy of our ultrasonographic measurements cannot be determined from our results. However, the EMH (as well as VEMS and FLEMS) correlated well with the MCSs from our cats, as also reported in other studies in cats, 28 suggesting that the ultrasound measurements are clinically meaningful. Another limitation was the unblinded nature of our study, that is, the investigators knew which cats were hyperthyroid vs clinically normal and had access to the pretreatment data when reevaluating the cats after 131I treatment. A final limitation of this study was that the EMH was measured at only a single vertebral location (ie, T13); additional studies are needed to determine whether the degree of muscle loss in cats with hyperthyroidism is comparable along the entire length of the thoracic vertebrae. Regardless of these limitations, our results confirm that ultrasonographic measurements EMH at the location of T13 can be used for quantitative assessment of muscle mass, and that these measurements agree with those obtained with the clinical MCS system.
In conclusion, most hyperthyroid cats evaluated in this study had loss of muscle mass when evaluated by a clinical MCS system or with ultrasound imaging. After successful treatment, the normal muscle mass was restored in most hyperthyroid cats, as weight was regained. Overall, MCS is ideal for clinical use in cats because it can be quickly and easily performed. However, it might not be precise enough as an outcome measure for research studies when the changes in muscle mass are small or quantification of muscle mass over time is needed. Ultrasound imaging offers a clinically feasible alternative method for monitoring and quantifying muscle loss that can easily be performed in clinical feline practice.
CONFLICT OF INTEREST DECLARATION
Authors declare no conflict of interest.
OFF‐LABEL ANTIMICROBIAL DECLARATION
Authors declare no off‐label use of antimicrobials.
INSTITUTIONAL ANIMAL CARE AND USE COMMITTEE (IACUC) OR OTHER APPROVAL DECLARATION
Authors declare that ethics approval (IACUC) was obtained before the study commenced.
HUMAN ETHICS APPROVAL DECLARATION
Authors declare human ethics approval was not needed for this study.
ACKNOWLEDGMENT
No funding was received for this study. The preliminary results of this study were presented an oral Research Report at the XXXVII VetMadrid Veterinary Congress (2020). We thank Dr. Mark Rishniw for editorial and statistical assistance.
Xifra P, Serrano SI, Peterson ME. Effect of radioiodine treatment on muscle mass in hyperthyroid cats. J Vet Intern Med. 2022;36(6):1931‐1941. doi: 10.1111/jvim.16560
REFERENCES
- 1. Acotto CG, Niepomniszcze H, Mautalen CA. Estimating body fat and lean tissue distribution in hyperthyroidism by dual‐energy X‐ray absorptiometry. J Clin Densitom. 2002;5:305‐311. [DOI] [PubMed] [Google Scholar]
- 2. Lonn L, Stenlof K, Ottosson M, et al. Body weight and body composition changes after treatment of hyperthyroidism. J Clin Endocrinol Metab. 1998;83:4269‐4273. [DOI] [PubMed] [Google Scholar]
- 3. Dutta P, Bhansali A, Walia R, et al. Weight homeostasis & its modulators in hyperthyroidism before & after treatment with carbimazole. Indian J Med Res. 2012;136:242‐248. [PMC free article] [PubMed] [Google Scholar]
- 4. de la Rosa RE, Hennessey JV, Tucci JR. A longitudinal study of changes in body mass index and total body composition after radioiodine treatment for thyrotoxicosis. Thyroid. 1997;7:401‐405. [DOI] [PubMed] [Google Scholar]
- 5. Da Nobrega AC, Vaisman M, De Araujo CG. Skeletal muscle function and body composition of patients with hyperthyroidism. Med Sci Sports Exerc. 1997;29:175‐180. [DOI] [PubMed] [Google Scholar]
- 6. Greenlund LJ, Nair KS, Brennan MD. Changes in body composition in women following treatment of overt and subclinical hyperthyroidism. Endocr Pract. 2008;14:973‐978. [DOI] [PubMed] [Google Scholar]
- 7. Xie LJ, Zhou HJ, Li JF, et al. Redistribution of body composition in patients with Graves' disease after iodine‐131 treatment. Eur J Clin Nutr. 2015;69:856‐861. [DOI] [PubMed] [Google Scholar]
- 8. Miller ML, Randolph JF, Peterson ME. Hyperthyroidism: clinical signs and physical examination findings. In: Feldman EC, Fracassi F, Peterson ME, eds. Feline Endocrinology. Milan: EDRA; 2019:130‐140. [Google Scholar]
- 9. Peterson ME, Castellano CA, Rishniw M. Evaluation of body weight, body condition, and muscle condition in cats with hyperthyroidism. J Vet Intern Med. 2016;30:1780‐1789. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 10. Freeman L, Becvarova I, Cave N, et al. WSAVA nutritional assessment guidelines. J Small Anim Pract. 2011;52:385‐396. [DOI] [PubMed] [Google Scholar]
- 11. WSAVA.org . Muscle Condition Score Chart for Cats. https://wsava.org/wp-content/uploads/2020/01/Muscle-Condition-Score-Chart-for-Cats.pdf. Accessed August 7, 2022.
- 12. Michel KE, Anderson W, Cupp C, Laflamme DP. Correlation of a feline muscle mass score with body composition determined by dual‐energy X‐ray absorptiometry. Br J Nutr. 2011;106(Suppl 1):S57‐S59. [DOI] [PubMed] [Google Scholar]
- 13. Freeman LM, Michel KE, Zanghi BM, Vester Boler BM, Fages J. Evaluation of the use of muscle condition score and ultrasonographic measurements for assessment of muscle mass in dogs. Am J Vet Res. 2019;80:595‐600. [DOI] [PubMed] [Google Scholar]
- 14. Nguyen P, Leray V, Dumon H, et al. High protein intake affects lean body mass but not energy expenditure in nonobese neutered cats. J Nutr. 2004;134:2084S‐2086S. [DOI] [PubMed] [Google Scholar]
- 15. Zanghi BM, Cupp CJ, Pan Y, et al. Noninvasive measurements of body composition and body water via quantitative magnetic resonance, deuterium water, and dual‐energy x‐ray absorptiometry in cats. Am J Vet Res. 2013;74:721‐732. [DOI] [PubMed] [Google Scholar]
- 16. Stanton CA, Hamar DW, Johnson DE, et al. Bioelectrical impedance and zoometry for body composition analysis in domestic cats. Am J Vet Res. 1992;53:251‐257. [PubMed] [Google Scholar]
- 17. Center SA, Warner KL, Randolph JF, Wakshlag JJ, Sunvold GD. Resting energy expenditure per lean body mass determined by indirect calorimetry and bioelectrical impedance analysis in cats. J Vet Intern Med. 2011;25:1341‐1350. [DOI] [PubMed] [Google Scholar]
- 18. Borges NC, Vasconcellos RS, Carciofi AC, et al. DXA, bioelectrical impedance, ultrasonography and biometry for the estimation of fat and lean mass in cats during weight loss. BMC Vet Res. 2012;8:111. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 19. Buelund LE, Nielsen DH, McEvoy FJ, et al. Measurement of body composition in cats using computed tomography and dual energy X‐ray absorptiometry. Vet Radiol Ultrasound. 2011;52:179‐184. [DOI] [PubMed] [Google Scholar]
- 20. Freeman LM, Kehayias JJ, Roubenoff R. Use of dual‐energy x‐ray absorptiometry (DEXA) to measure lean body mass, body fat, and bone mineral content (BMC) in dogs and cats. J Vet Intern Med. 1996;10:99‐100. [DOI] [PubMed] [Google Scholar]
- 21. Speakman JR, Booles D, Butterwick R. Validation of dual energy X‐ray absorptiometry (DXA) by comparison with chemical analysis of dogs and cats. Int J Obes Relat Metab Disord. 2001;25:439‐447. [DOI] [PubMed] [Google Scholar]
- 22. Nijholt W, Scafoglieri A, Jager‐Wittenaar H, Hobbelen JSM, van der Schans CP. The reliability and validity of ultrasound to quantify muscles in older adults: a systematic review. J Cachexia Sarcopenia Muscle. 2017;8:702‐712. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 23. Naruse M, Trappe SW, Trappe TA. Human skeletal muscle size with ultrasound imaging: a comprehensive review. J Appl Physiol (1985). 2022;132:1267‐1279. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 24. Tang X, Huang L, Yue J, Qiu L. Quantitative estimation of muscle mass in older adults at risk of sarcopenia using ultrasound: a cross‐sectional study. Quant Imaging Med Surg. 2022;12:2498‐2508. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 25. Hutchinson D, Sutherland‐Smith J, Watson AL, Freeman LM. Assessment of methods of evaluating sarcopenia in old dogs. Am J Vet Res. 2012;73:1794‐1800. [DOI] [PubMed] [Google Scholar]
- 26. Freeman LM, Sutherland‐Smith J, Prantil LR, Sato AF, Rush JE, Barton BA. Quantitative assessment of muscle in dogs using a vertebral epaxial muscle score. Can J Vet Res. 2017;81:255‐260. [PMC free article] [PubMed] [Google Scholar]
- 27. Freeman LM, Sutherland‐Smith J, Cummings C, Rush JE. Evaluation of a quantitatively derived value for assessment of muscle mass in clinically normal cats. Am J Vet Res. 2018;79:1188‐1192. [DOI] [PubMed] [Google Scholar]
- 28. Freeman LM, Michel KE, Zanghi BM, Vester Boler BM, Fages J. Usefulness of muscle condition score and ultrasonographic measurements for assessment of muscle mass in cats with cachexia and sarcopenia. Am J Vet Res. 2020;81:254‐259. [DOI] [PubMed] [Google Scholar]
- 29. American College of Physicians . A primer on before‐after studies: evaluating a report of a “successful” intervention. Eff Clin Pract. 2002;5:100‐101. [PubMed] [Google Scholar]
- 30. Eccles M, Grimshaw J, Campbell M, Ramsay C. Research designs for studies evaluating the effectiveness of change and improvement strategies. Qual Saf Health Care. 2003;12:47‐52. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 31. Peterson ME. More than just T4: diagnostic testing for hyperthyroidism in cats. J Feline Med Surg. 2013;15:765‐777. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 32. Peterson ME, Guterl JN, Nichols R, Rishniw M. Evaluation of serum thyroid‐stimulating hormone concentration as a diagnostic test for hyperthyroidism in cats. J Vet Intern Med. 2015;29:1327‐1334. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 33. Peterson ME, Broome MR. Thyroid scintigraphy findings in 2096 cats with hyperthyroidism. Vet Radiol Ultrasound. 2015;56:84‐95. [DOI] [PubMed] [Google Scholar]
- 34. Peterson ME, Guterl JN, Rishniw M, Broome MR. Evaluation of quantitative thyroid scintigraphy for diagnosis and staging of disease severity in cats with hyperthyroidism: comparison of the percent thyroidal uptake of pertechnetate to the thyroid‐to‐salivary ratio and thyroid‐to‐background ratios. Vet Radiol Ultrasound. 2016;57:427‐440. [DOI] [PubMed] [Google Scholar]
- 35. Broome MR, Peterson ME. Thyroid imaging. In: Feldman EC, Fracassi F, Peterson ME, eds. Feline Endocrinology. Milan: EDRA; 2019:169‐197. [Google Scholar]
- 36. Lucy JM, Peterson ME, Randolph JF, et al. Efficacy of low‐dose (2 millicurie) versus standard‐dose (4 millicurie) radioiodine treatment for cats with mild‐to‐moderate hyperthyroidism. J Vet Intern Med. 2017;31:326‐334. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 37. Peterson ME, Nichols R, Rishniw M. Serum thyroxine and thyroid‐stimulating hormone concentration in hyperthyroid cats that develop azotaemia after radioiodine therapy. J Small Anim Pract. 2017;58:519‐530. [DOI] [PubMed] [Google Scholar]
- 38. Peterson ME, Rishniw M. A dosing algorithm for individualized radioiodine treatment of cats with hyperthyroidism. J Vet Intern Med. 2021;35:2140‐2151. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 39. D'Agostino RB. Tests for normal distribution. In: D'Agostino RB, Stephens MA, eds. Goodness‐of‐Fit Techniques. New York: Macel Dekker; 1986:367‐420. [Google Scholar]
- 40. Simpson RJ Jr, Johnson TA, Amara IA. The box‐plot: an exploratory analysis graph for biomedical publications. Am Heart J. 1988;116:1663‐1665. [DOI] [PubMed] [Google Scholar]
- 41. National Committee for Clinical Laboratory Standards . Defining, establishing and verifying reference intervals in the clinical laboratory. Approved guideline. In: Horowitz GL, Altaie CS, Boyd JC, et al., eds. Clinical and Laboratory Standards Institute (CLSI). 3rd ed. Wayne, PA: CLSI; 2008. [Google Scholar]
- 42. Friedrichs KR, Harr KE, Freeman KP, et al. ASVCP reference interval guidelines: determination of de novo reference intervals in veterinary species and other related topics. Vet Clin Pathol. 2012;41:441‐453. [DOI] [PubMed] [Google Scholar]