



Abstract
The use of tyrosine kinase inhibitors (TKIs) in the treatment of solid tumors is the expected standard of care for many types of tumors. Since the description of signal transduction pathways, followed by the development of small molecules designed to inhibit those pathways, there has been significant improvement not only in progression-free survival and overall survival but also in aiming toward chemotherapy-free treatment of solid tumors to maximize quality of life. This article reviews available TKIs and discusses toxicity, dosing, and resistance.
Keywords: tyrosine kinase inhibitors, solid tumors, TKIs, EGFR mutation, TKI toxicities, targeted therapy, signaling pathways
Introduction
Signal transduction pathways identified to induce cell proliferation in solid tumors include the growth factor receptor (ErbB/HER), the vascular endothelial growth factor receptor (VEGFR), anaplastic lymphoma kinase (ALK), MET, and KIT surface tyrosine kinases, as well as RAS/RAF/MEK/ERK and PI3K/AKT pathways for intracellular signal transduction.1 These signaling pathways are often abnormally upregulated and dependent on oncogenic mutations, such as exon 19 deletion and others for EGFR,2 V600 for BRAF,3 gene rearrangement with EML4 fusion gene for ALK,4 and KIT for gastrointestinal stromal tumors (GISTs).5 Since their description, there have been fruitful efforts in developing targeted drugs for effective blockade of the upregulated signaling pathways.6,7 The involvement of small inhibitory molecules (tyrosine kinase inhibitors or TKIs) binding the adenosine triphosphate site of tyrosine kinases successfully led to down-regulation through autophosphorylation.
For the clinician the implications of TKIs have been revolutionary over the last decade. Following imatinib for the treatment of chronic myelogenous leukemia in 2001, there have been significant efforts taken to identify oncogenic mutations, and important advances in applying TKIs in the treatment of solid tumors. Through trials of TKIs in the treatment of tumors considered more oncogenic driven, such as renal cell cancer or melanoma, a new standard of treatment has been set. Nevertheless, expanding the use of TKIs to include treatment of other solid tumors has remained a challenge.8,9 Further research on signaling pathways has helped identify mutations that lead to enhanced signal transduction and tumor proliferation, or to pathway alterations that cause resistance to TKI treatment through feedback mechanisms.
In clinical practice, EGFR and RAS mutation analysis, applied to non-small cell lung cancer (NSCLC) and colon cancer, as well as EML4–ALK fusion gene testing in NSCLC are standards of care. In case of positivity, a chemotherapy-free first-line therapy option arises.
The issue of acquired resistance to TKIs and how this could be overcome remains a major topic of research and further trials. Moreover, the identification and handling of TKI-induced organ toxicity, especially where it leads to quality- of-life restriction, is of great importance.
This article reviews the current commercially available TKIs approved for use in the treatment of solid tumors.
Breast Cancer
In patients with HER2 overexpression and hormone receptor-positive metastatic breast cancer who had not received prior therapy for metastatic disease, lapatinib has been approved after a randomized trial with lapatinib plus letrozole vs. placebo plus letrozole.10 Patients in the lapatinib plus letrozole group showed an improved progression-free survival (PFS) of 35.4 weeks, compared to 13.0 weeks for the placebo plus letrozole arm (hazard ratio = 0.71; P = 0.019).
In HER2 overexpressing metastatic breast cancer, lapatinib in combination with capecitabine compared with capecitabine alone in pretreated patients has shown improvement in the primary endpoint of time to progression (27.1 vs. 18.6 weeks; hazard ratio = 0.57; P < 0.001).11
Colon Cancer
The small-molecule multikinase inhibitor, regorafenib, inhibits multiple membrane-bound and intracellular kinases, such as VEGFR, KIT, TIE2, PDGFR, FGFR, and BRAF. In a phase III trial on pretreated patients with metastatic colon cancer, there was an overall survival (OS) benefit for patients treated with regorafenib (6.4 vs. 5.0 months; P = 0.0052).12
Gastrointestinal Stromal Tumors
In the presence of oncogenic mutations in one of two receptor tyrosine kinases, KIT or PDGFRA (platelet-derived growth factor receptor alpha), imatinib is the standard first-line treatment in unresectable or metastatic GISTs (Fig. 1). The majority of patients showed a response (53.7% had partial response and 27.9% had stable disease), improved survival (durable responses more than 42 weeks), and delayed disease progression.5,13 A dose escalation to 800 mg daily was tested in phase III trials, showing no significant benefit compared to 400 mg daily.14 The authors concluded that a dose escalation can be considered in case of progression.15 In cases of nonresectable GIST after imatinib resistance, the multitargeted TKI sunitinib showed a median time to tumor progression of 27.3 vs. 6.4 weeks for patients on placebo in a randomized trial (hazard ratio = 0.33; P < 0.0001).16 Regorafenib has recently been approved for the treatment of GIST after the failure of imatinib and sunitinib, according to the GRID study, in which a PFS of 4.8 months was shown for regorafenib compared to 0.9 months for placebo (P < 0.001). After progression, 85% of the patients crossed over to regorafenib.17
Figure 1.

Patient with relapse of GIST tumor with peritoneal, adrenal, and hepatic metastasis (left images) 2 years after individual discontinuation of imatinib shows partial response after reexposure to imatinib 400 mg daily. Measurable response was shown in the liver (34.82 mm before and 29 mm after) and the left adrenal gland (40.13 mm before and 30.64 mm after). Peritoneal metastasis with thickening of the peritoneum is visible on the lower left image, showing regress on the lower right image.
Hepatocellular Carcinoma
Sorafenib in the treatment of advanced and unresectable hepatocellular carcinoma has shown a benefit in OS (10.7 vs. 7.9 months; P < 0.001), although the median time to symptomatic progression was not significantly different in the two groups (4.1 months for sorafenib vs. 4.9 months for placebo; P = 0.77). The endpoint of radiological progression was significantly different (5.5 months for the sorafenib group vs. 2.8 months for the placebo group; P < 0.001).18
Melanoma
The identification of the BRAF mutation with the development of BRAF inhibitors has been a boon to the treatment of melanoma patients, increasing OS (84% OS after 6 months for vemurafenib vs. 64% for dacarbazine in a phase III randomized trial). The response rate of vemurafenib was up to 48% compared to 5% for dacarbazine.19 Nevertheless, the effect of BRAF inhibition was short lasting. Further studies revealed a feedback mechanism through MEK-mediated reactivation of the ERK signaling pathway.20 Either a dual inhibition of RAF and MEK or reexposure to BRAF inhibitor after drug holiday has been shown effective to overcome resistance.21,22 Dabrafenib, another BRAF inhibitor, has also shown effectiveness in the treatment of patients with advanced BRAF V600 mutated melanoma.23 In a phase III trial vs. dacarbazine, there was a significant benefit in PFS (5.1 months for dabrafenib vs. 2.7 months for dacarbazine; P < 0.001),24 but because of short duration of antitumor activity, current studies are being carried out in combination with the MEK inhibitor trametinib.25
Non-Small Cell Lung Cancer
The use of a TKI in case of EGFR mutation positivity or EML4-ALK fusion gene evidence has become standard of care in NSCLC.
Several randomized phase III clinical trials showed benefit in PFS for patients with the upregulation of EGFR.26 Erlotinib was tested in EGFR mutation-positive tumors in first-line treatment vs. chemotherapy in a European trial. It demonstrated a statistically significant improvement in PFS, 9.7 months compared to 5.2 months for the chemotherapy arm (P < 0.001).2 Two Japanese trials tested gefitinib vs. chemotherapy in the first-line setting, showing PFS of 9.2 and 10.8 months for gefitinib compared to 6.3 and 5.4 months for the chemotherapy arms.27,28 The latest study was stopped after showing the above results at the interim analysis; most patients crossed over to gefitinib.
The second-generation TKI afatinib, which irreversibly blocks EGFR as well as HER2 and HER4, was tested in a phase IIb/III trial vs. best supportive care for patients with EGFR-mutated tumors, pretreated with platinum doublet and at least 3 months of EGFR–TKI gefitinib or erlotinib. There was an increase in PFS, but the primary endpoint, which was OS, was not significantly improved. In the first-line setting, afatinib showed a statistically significant difference in PFS of 11 months vs. 5.6 months in the LUX-Lung 6 trial (P < 0.001), but still no difference in OS.29 Further sub-population analysis has been able to detect a benefit in OS in patients with a del-19 mutation (31.4 months vs. 18.4 months with chemotherapy; P = 0.02).30
In nononcogenic-driven metastatic lung cancer, erlotinib remains an option as maintenance therapy after first-line treatment without tumor progression,31 or after the failure of first-line or second-line chemotherapy.32 In the metastatic setting, erlotinib showed similar PFS and OS compared to chemotherapy with docetaxel.33
In the setting of chromosomal rearrangements of the ALK gene, the TKI crizotinib (dual TKI of MET and ALK) showed a significant benefit in median PFS (7.7 months in the crizotinib group vs. 3.0 months in the chemotherapy group; P < 0.001) in pretreated patients with advanced disease.34 A phase III clinical trial of crizotinib as first-line treatment has also shown advantage in PFS (median 10.9 months with crizotinib vs. 7.0 months with chemotherapy; P < 0.001). The end point of significant improvement in OS was not reached, while the probability of one-year survival was 84% with crizotinib and 79% with chemotherapy. The relief of symptoms and the quality of life were greater in the crizotinib arm.35
The potent ALK inhibitor ceritinib was approved for the second-line treatment of advanced NSCLC harboring ALK rearrangement. The majority of patients were pretreated with crizotinib. The overall response rate was 58% with a median PFS of 7 months. In the group of crizotinib pretreated patients, the response rate was 56% with a PFS of 6.9 months. The crizotinib naive patients showed 62% response rate, and the median PFS in this group had not been reached at the time of analysis.36
Ovarian Cancer
The important role of angiogenesis in ovarian cancer has been well described, making VEGFR targeting appealing for clinical trials.37 In a randomized trial for maintenance treatment, the VEGFR inhibitor, pazopanib, showed a median improvement in PFS of 5.6 months (hazard ratio = 0.77) vs. placebo, in 940 patients with advanced ovarian cancer who had not progressed after first-line chemotherapy; no benefit was shown in OS.38
Pancreatic Cancer
The EGFR–TKI erlotinib has resulted in prolonged survival when added to gemcitabine for the treatment of advanced pancreatic cancer (median PFS of 6.24 months vs. 5.91 months) and increased the one-year survival to 23% for the combination therapy vs. 17% for gemcitabine monotherapy (P = 0.023).39
Pancreatic Neuroendocrine Tumors
The antiangiogenic TKI sunitinib has shown efficacy in a phase III trial on patients with advanced, well-differentiated pancreatic neuroendocrine tumors. PFS was significantly prolonged (11.4 months for sunitinib and 5.5 months for placebo; P < 0.001).40
Renal Cell Carcinoma
The refractory nature of renal cell carcinoma against radiation and chemotherapy led to early immunologic therapeutic approaches, such as cytokines, and observations about the efficacy of TKIs.
In a trial against interferon alfa, patients treated with sunitinib showed prolonged PFS (11 months vs. 5 months) and overall higher objective response rate (31% vs. 6%; P < 0.001).41 The trial, conducted in 2007, put sunitinib in the first-line choice of TKI treatment for renal cancer.
Sorafenib was tested on advanced renal cell carcinoma patients in a phase III trial after the failure of prior treatment. It showed a significant improvement in PFS (5.5 months vs. 2.8 months; P < 0.001) and reduction in risk of progression of 51%. OS was 19.3 months for sorafenib and 15.9 months for the placebo group, which is not a statistically significant difference.42
Several years later, the TKI pazopanib showed a significantly prolonged PFS compared to placebo (9.2 vs. 4.2 months) and response rate (30% vs. 3%; P < 0.001).43 Compared to sunitinib, pazopanib showed similar efficacy but was better tolerated,44 thus setting a second option for first-line treatment.
The antiangiogenic TKI axitinib was compared with sorafenib in a phase III trial of second-line treatment. Although OS was not significantly different (20.1 months for axitinib vs. 19.2 months for sorafenib; P = 0.3744), there was a statistically significant benefit in PFS (8.3 months for axi-tinib vs. 5.7 months for sorafenib; P < 0.001) that established axitinib as a second-line treatment for advanced renal cell carcinoma patients.45
Soft Tissue Sarcomas
Two European Organisation for Research and Treatment of Cancer trials with the VEGFR–TKI pazopanib have shown significant improvement in PFS (4.6 months for pazopanib vs. 1.6 months for placebo; P < 0.001) and OS (12.5 months for pazopanib vs. 10.7 months for placebo; P = 0.25), cementing the place of pazopanib in the treatment of nonadipocytic soft tissue sarcomas after chemotherapy.46,47
Thyroid Cancer
Medullary
The TKIs vandetanib and cabozantinib are licensed for the treatment of advanced medullary thyroid cancer. Vandetanib showed a significant longer PFS vs. placebo (30.5 months vs. 19.3 months; P < 0.001) in both patients with sporadic and hereditary medullary thyroid cancer. Median PFS of vandetanib was not reached at the time of analysis, so the reported PFS concerns the predicted one. Subgroup analysis showed a higher response rate for patients with M918T mutations.48 In the phase III trial comparing cabozantinib versus placebo, 48.2% of tumors harbored M918T RET mutations, 12% were negative, whereas for rest RET mutations status was unknown. The majority of patients suffered from sporadic medullary thyroid cancer. Cabozantinib showed a significantly longer PFS (11.2 months) vs. placebo (4 months; P < 0.001). The estimation of one year survival and progression free was estimated 47.3% for cabozantinib vs. 7.2% for placebo.49
Differentiated
Patients with locally advanced or metastatic differentiated thyroid cancer refractory to radioactive iodine were randomized in a phase III trial to receive sorafenib vs. placebo. PFS was significantly longer for those in the sorafenib arm (10.8 vs. 5.8 months; P < 0.001), although no difference was noticed in OS. The risk of progression or death was reduced by 41% in the sorafenib arm during the double- blind phase.50 The latest TKI that has been licensed for differentiated thyroid cancer is lenvatinib, which in a phase III trial vs. placebo showed a significantly prolonged PFS (18.3 months vs. 3.6 months, P < 0.001).51
In Table 1, are listed the indications for use of the above described TKIs in solid tumors.
Table 1.
TKI lists according to the indication of use.
| TKI | PATHWAY OF ACTION | INDICATION | DOSING# |
|---|---|---|---|
| Breast cancer | |||
| Lapatinib | EGFR and HER2 (dual reversible) | Advanced/metastatic breast cancer that overexpress HER2 in combination with capecitabine who have received prior therapy including an anthracycline, a taxane, and trastuzumab11 In combination with letrozole for treatment of postmenopausal women with hormone receptor-positive and HER2-positive breast cancer for whom hormonal therapy is indicated10 |
1250 mg daily on Days 1–21 continuously in combination with capecitabine (2000 mg/m2/day bid) on Days 1–14 in 21-day cycle 1500 mg daily continuously in combination with letrozole 2.5 mg daily |
| Colon cancer | |||
| Regorafenib | VEGFR, TIE2, KIT, RET, RAF-1, BRAF, BRAFV600E, PDGFR, FGFR | Metastatic disease pretreated with fluoropyrimidine-, oxaliplatin-, andirinotecan-based chemotherapy, anti- VEGF therapy and anti-EGFR therapy (KRAS wild type)12 | 160 mg daily for the first 21 days of each 28-day cycle |
| GIST | |||
| Imatinib | Bcr-abl, KIT, PDGFR, SRC (reversible) | Unresectable or metastatic disease5 Adjuvant treatment following complete gross resection62 | 400 mg daily 400 mg daily for 3 years |
| Regorafenib | VEGFR, TIE2, KIT, RET, RAF-1, BRAF, BRAFV600E, PDGFR, FGFR | After progression to imatinib and sunitinib17 | 160 mg daily for the first 21 days of each 28-day cycle |
| Sunitinib | VEGFR, KIT, RET, PDGFR | After progression to imatinib16 | 50 mg daily (4 weeks on/2 weeks off) |
| HCC | |||
| Sorafenib | w-BRAF, m-BRAF, CRAF, Flt-3, RET, KIT, VEGFR, PDGFR-ß | Unresectable disease18 | 400 mg bid fasting |
| Melanoma | |||
| Dabrafenib | BRAF | Advanced disease24 | 150 mg bid |
| Vemurafenib | V600E BRAF | Advanced disease19 | 960 mg bid |
| NSCLC | |||
| Afatinib | Dual irreversible EGFR and HER2 | First-line treatment for metastatic tumors with EGFR mutations*,30 | 50 mg daily fasting |
| Ceritinib | ALK | Advanced or metastatic tumors with ALK rearrangement after crizotinib treatment36 | 750 mg daily fasting |
| Crizotinib | MET and ALK | First-line treatment for advanced or metastatic tumors with ALK rearrangement34 | 250 mg bid |
| Erlotinib | EGFR (reversible) | First-line treatment for tumors with EGFR mutations*,2 Maintenance treatment of locally advanced or metastatic NSCLC in patients whose disease has not progressed after 4 cycles of platinum-based first-line chemotherapy63 Advanced or metastatic NSCLC after failure of at least 1 prior chemotherapy32 |
150 mg daily as single agent |
| Gefitinib | EGFR (reversible) | Patients that previously benefited from gefitinib27 | 250 mg daily as single agent |
| Ovarian cancer | |||
| Pazopanib | VEGFR | Maintenance treatment in advanced disease, no progression after first-line (orphan designation)38 | 800 mg daily fasting |
| Pancreatic cancer | |||
| Erlotinib | EGFR (reversible) | In combination with gemcitabine for locally advanced, unresectable or metastatic disease39 | 100 mg daily |
| pNET | |||
| Sunitinib | VEGFR, KIT, RET, PDGFR | Advanced disease40 | 37,5 mg daily |
| Renal cell carcinoma | |||
| Axitinib | VEGFR | Advanced disease45 | 5 mg bid |
| Pazopanib | VEGFR, PDGFR, KIT | Advanced disease44 | 800 mg daily fasting |
| Sorafenib | w-BRAF, m-BRAF, CRAF, Flt-3, RET, KIT, VEGFR, PDGFR-β | Advanced disease42 | 400 mg bid fasting |
| Sunitinib | VEGFR, KIT, RET, PDGFR | Advanced disease41 | 50 mg daily (4 weeks on/2 weeks off) |
| Sarcomas | |||
| Pazopanib | VEGFR, PDGFR, KIT | Advanced disease after chemotherapy47 | 800 mg daily fasting |
| Thyroid cancer | |||
| Cabozantinib | VEGF, RET, MET | Progressive metastatic medullary TC49 | 140 mg daily fasting |
| Lenvatinib | VEGFR, FGFR, PGFR, RET, KIT | locally recurrent or metastatic, progressive, differentiated TC refractory to radioactive iodine51 | 24 mg daily |
| Sorafenib | w-BRAF, m-BRAF, CRAF, Flt-3, RET, KIT, VEGFR, PDGFR-β | locally recurrent or metastatic, progressive, differentiated TC refractory to radioactive iodine50 | 400 mg bid fasting |
| Vandetanib | EGFR, VEGFR, RET | Progressive metastatic medullary TC48 | 300 mg daily |
Notes:
Exon 19 deletions or exon 21 (L858R) substitution as detected by FDA-approved test,
Dosing adaptation for renal or hepatic impairment omitted.
Abbreviations: NSCL, non-small cell lung cancer; bid, twice daily; GIST, gastrointestinal stromal tumors; pNET, pancreatic neuroendocrine tumors; TC, thyroid cancer; HCC, hepatocellular carcinoma.
Discussion
Side effects
A major obstacle in treatment with TKIs is the variety and intensity of side effects that they induce (Table 2). Notable literature covers the spectrum and the adequate management of these side effects.52 The majority of TKIs can cause gastrointestinal symptoms such as diarrhea, nausea, and emesis, as well as general symptoms including fatigue, weight loss, and anorexia. A particular feature of VEGFR–TKIs, but also indirectly a marker for successful VEGF inhibition, is the development of hypertension. The pathomechanism relies on the decrease of nitric oxide (NO) production after VEGF serum levels are reduced. Moreover, downregulation of VEGF causes endothelin dysfunction and renal podocyte cell dysregulation. These can also be responsible for hypertension and cause proteinuria.53 The most appropriate antihypertensive treatment is angiotensin-converting enzyme inhibitors or angiotensin II receptor blockers, mainly because of nephroprotective ability.54 Additionally, the use of long-acting nitrates in order to overcome the vasoconstriction caused by NO suppression is very effective in the management of VEGFR inhibition induced hypertension.55 Further side effects of VEGFR–TKIs can include hemorrhage and impaired wound healing (Fig. 2).
Table 2.
| TKI | METABOLISM* | COMMON SIDE EFFECTS |
|---|---|---|
| Afatinib | Hepatic | Rash, fatigue, nausea, diarrhea, anorexia, stomatitis |
| Axitinib | Hepatic | Diarrhea, hypertension, fatigue, nausea, hand-foot syndrome, hypothyroidism, thromboembolic event |
| Cabozantinib | Hepatic (CYP3A) | Diarrhea, mucositis, hand-foot syndrome, weight loss, anorexia, fatigue, hair discoloration, dysgeusia, abdominal pain |
| Ceritinib | Hepatic (CYP3A) | Diarrhea, nausea, fatigue, vomiting, interstitial lung disease |
| Crizotinib | Hepatic (CYP3A4) | Nausea, vomiting, diarrhea, visual disorders, peripheral edema, fatigue |
| Dabrafenib | Hepatic (CYP3A4) | Hyperkeratosis, headache, pyrexia, arthralgia, papilloma, alopecia, hand-foot syndrome |
| Erlotinib | Hepatic (CYP3A4) | Skin toxicity, diarrhea, fatigue, anorexia, nausea, vomiting, stomatitis/mucositis, conjunctivitis |
| Gefitinib | Hepatic (CYP3A4) | Diarrhea, skin toxicity, anorexia, interstitial lung disease (2%) |
| Imatinib | Hepatic (CYP3A4) | Edema, muscle cramps, muscle pain, nausea, vomiting, rash |
| Lapatinib | Hepatic (CYP3A4, CYP3A5) | Diarrhea, nausea, vomiting, skin toxicity, fatigue, mucositis, cardiotoxicity |
| Lenvatinib | Hepatic (CYP3A) | Diarrhea, hypertension, fatigue, anorexia, weight loss, nausea |
| Pazopanib | Up to 95% unchanged in plasma | Diarrhea, nausea, vomiting, fatigue, weight loss, anorexia, hypertension, vomiting, hair or skin discoloration, headache, dysgeusia |
| Regorafenib | Hepatic (CYP3A4) | Diarrhea, fatigue, hypertension, hand foot syndrome, rash, anorexia, mucositis, weight loss, dysphonia |
| Sorafenib | Hepatic (CYP3A4) | Fatigue, anorexia, weight loss, rash, skin discoloration, hand foot syndrome, alopecia, diarrhea, nausea, abdominal pain |
| Sunitinib | Hepatic (CYP3A4) | Diarrhea, nausea, anorexia, vomiting, fatigue, stomatitis, hypertension, hand foot syndrome, skin discoloration, rash, mucositis, left ventricular dysfunction |
| Vandetanib | Hepatic (CYP3A4) | Diarrhea, rash, nausea, hypertension, headache, fatigue, anorexia, abdominal pain |
| Vemurafenib | Hepatic (CYP3A4) | Arthralgia, rash, photosensitivity, fatigue, alopecia, pruritus, nausea, cutaneous squamous cell carcinoma |
Note:
Only the main metabolizing cytochromes are mentioned.
Figure 2.
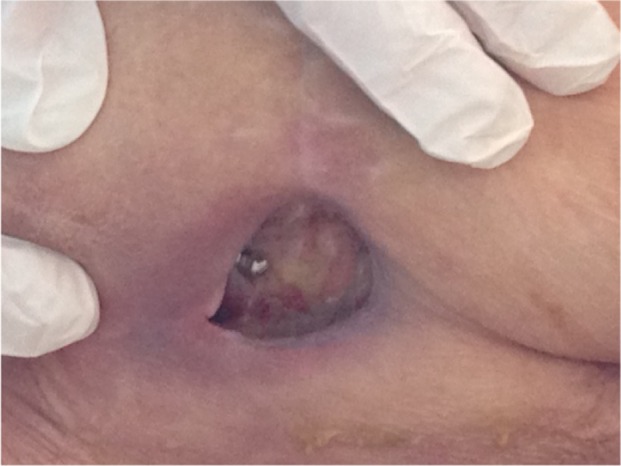
Impaired wound healing after gluteal abscess under pazopanib and later axitinib treatment for metastatic renal cell cancer. Osteosynthesis material of the hip after surgery for fracture because metastasis is visible.
Resistance Mechanisms
The restricted efficacy of TKIs compared to the length of survival achieved after immunotherapy remains a major drawback and raises further discussion regarding mechanisms of resistance. It mainly concerns upregulation through bypass pathways (upregulation of MET, overexpression of HER3, activation of IGF-1R, loss or downregulation of PTEN, abnormal dimerization of STAT3) or acquired receptor mutations (EGFR-T790M, HER2, PIK3CA/AKT mutations).56 Moreover, the inability of TKIs to eliminate cancer stem cells presumably attributes to relapse under TKI treatment.57 Approaches to overcome resistance to TKIs include the development of multitargeted agents, such as new-generation EGFR–TKIs and inhibitors of MET, IGF-1R, HER3, PIK3 A/AKT, ERK, or STAT3.58 The use, safety, and efficacy of these agents in clinical practice, as monotherapy or in combination with already licensed TKIs, is the subject of further clinical trials.
The development of resistance to ALK TKIs has been attributed to acquired secondary mutations of the kinase domain, amplification of the ALK gene or activation of alternative signaling pathways (EGFR, c-KIT). The second generation ALK TKI ceritinib was effective through more potent inhibition.59 In BRAF mutant melanoma, resistance mechanisms that have been studied revealed an increase in the amount of RAF dimers in tumor cells or bypass of RAF dependence for cell proliferation.60 The dual blockade of RAF and MEK, in order to effectively inhibit the ERK signaling pathway, has been tested in trials after development of RAF resistance but showed rather modest efficacy and increased toxicity. Dual inhibition in first-line treatment appeared to be more effective in prolongation of PFS.22,25
Pharmacokinetics
The majority of TKIs are metabolized hepatically and commonly show interactions mainly through CYP3A4 induction. An individualized dosing approach applied through therapeutic drug monitoring may be indicated in order to avoid undertreatment or toxicity.61
Conclusion
The past decade has been one of major importance for cancer therapy with TKIs, as many milestones have been reached in the development of targeted cancer therapies along with monoclonal antibodies. Although TKIs are well established in the treatment of solid tumors, such as renal cell carcinoma, melanoma, or GIST, their efficacy for other solid tumors still remains dubious. The future of TKIs remains challenging in terms of combination regimes, optimizing dosing, or broadening of the therapeutic spectrum. Studies to overcome resistance, enhance knowledge on pharmacokinetics, and manage side effects could provide effective future approaches to improve the efficacy of cancer treatment while preserving the quality of life.
Footnotes
ACADEMIC EDITOR: Karen Pulford, Editor in Chief.
PEER REVIEW: Four peer reviewers contributed to the peer review report. Reviewers’ reports totaled 437 words, excluding any confidential comments to the academic editor.
FUNDING: Author discloses no funding sources.
COMPETING INTERESTS: Author discloses no potential conflicts of interest.
Paper subject to independent expert blind peer review. All editorial decisions made by independent academic editor. Upon submission manuscript was subject to anti-plagiarism scanning. Prior to publication all authors have given signed confirmation of agreement to article publication and compliance with all applicable ethical and legal requirements, including the accuracy of author and contributor information, disclosure of competing interests and funding sources, compliance with ethical requirements relating to human and animal study participants, and compliance with any copyright requirements of third parties. This journal is a member of the Committee on Publication Ethics (COPE).
Author Contributions
Conceived the concepts: MV. Wrote the first draft of the manuscript: MV. Developed the structure and arguments for the paper: MV. Made critical revisions: MV. The author reviewed and approved of the final manuscript.
REFERENCES
- 1.Scaltriti M, Baselga J. The epidermal growth factor receptor pathway: a model for targeted therapy. Clin Cancer Res. 2006;12(18):5268–72. doi: 10.1158/1078-0432.CCR-05-1554. [DOI] [PubMed] [Google Scholar]
- 2.Rosell R, Carcereny E, Gervais R, Spanish Lung Cancer Group in collaboration with Groupe Français de Pneumo-Cancérologie and Associazione Italiana Oncologia Toracica Erlotinib versus standard chemotherapy as first-line treatment for European patients with advanced EGFR mutation-positive non-small-cell lung cancer (EURTAC): a multicentre, open-label, randomised phase 3 trial. Lancet Oncol. 2012;13(3):239–46. doi: 10.1016/S1470-2045(11)70393-X. [DOI] [PubMed] [Google Scholar]
- 3.Flaherty KT, Puzanov I, Kim KB, et al. Inhibition of mutated, activated BRAF in metastatic melanoma. N Engl J Med. 2010;363(9):809–19. doi: 10.1056/NEJMoa1002011. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 4.Soda M, Choi YL, Enomoto M, et al. Identification of the transforming EML4-ALK fusion gene in non-small-cell lung cancer. Nature. 2007;448(7153):561–6. doi: 10.1038/nature05945. [DOI] [PubMed] [Google Scholar]
- 5.Demetri GD, von Mehren M, Blanke CD, et al. Efficacy and safety of imatinib mesylate in advanced gastrointestinal stromal tumors. N Engl J Med. 2002;347(7):472–80. doi: 10.1056/NEJMoa020461. [DOI] [PubMed] [Google Scholar]
- 6.Baselga J, Swain SM. Novel anticancer targets: revisiting ERBB2 and discovering ERBB3. Nat Rev Cancer. 2009;9(7):463–75. doi: 10.1038/nrc2656. [DOI] [PubMed] [Google Scholar]
- 7.Cai SX. Small molecule vascular disrupting agents: potential new drugs for cancer treatment. Recent Pat Anticancer Drug Discov. 2007;2(1):79–101. doi: 10.2174/157489207779561462. [DOI] [PubMed] [Google Scholar]
- 8.Krause DS, Van Etten RA. Tyrosine kinases as targets for cancer therapy. N Engl J Med. 2005;353(2):172–87. doi: 10.1056/NEJMra044389. [DOI] [PubMed] [Google Scholar]
- 9.Traxler P. Tyrosine kinases as targets in cancer therapy - successes and failures. Expert Opin Ther Targets. 2003;7(2):215–34. doi: 10.1517/14728222.7.2.215. [DOI] [PubMed] [Google Scholar]
- 10.Johnston S, Pippen J, Jr, Pivot X, et al. Lapatinib combined with letrozole versus letrozole and placebo as first-line therapy for postmenopausal hormone receptor-positive metastatic breast cancer. J Clin Oncol. 2009;27(33):5538–46. doi: 10.1200/JCO.2009.23.3734. [DOI] [PubMed] [Google Scholar]
- 11.Cameron D, Casey M, Press M, et al. A phase III randomized comparison of lapatinib plus capecitabine versus capecitabine alone in women with advanced breast cancer that has progressed on trastuzumab: updated efficacy and biomarker analyses. Breast Cancer Res Treat. 2008;112(3):533–43. doi: 10.1007/s10549-007-9885-0. [DOI] [PubMed] [Google Scholar]
- 12.Grothey A, Van Cutsem E, Sobrero A, et al. CORRECT Study Group Regorafenib monotherapy for previously treated metastatic colorectal cancer (CORRECT): an international, multicentre, randomised, placebo-controlled, phase 3 trial. Lancet. 2013;381(9863):303–12. doi: 10.1016/S0140-6736(12)61900-X. [DOI] [PubMed] [Google Scholar]
- 13.Judson I, Demetri G. Advances in the treatment of gastrointestinal stromal tumours. Ann Oncol. 2007;18(suppl 10):x20–4. doi: 10.1093/annonc/mdm410. [DOI] [PubMed] [Google Scholar]
- 14.Verweij J, Casali PG, Zalcberg J, et al. Progression-free survival in gastrointestinal stromal tumours with high-dose imatinib: randomised trial. Lancet. 2004;364(9440):1127–34. doi: 10.1016/S0140-6736(04)17098-0. [DOI] [PubMed] [Google Scholar]
- 15.Blanke CD, Rankin C, Demetri GD, et al. Phase III randomized, intergroup trial assessing imatinib mesylate at two dose levels in patients with unresectable or metastatic gastrointestinal stromal tumors expressing the kit receptor tyrosine kinase: S0033. J Clin Oncol. 2008;26(4):626–32. doi: 10.1200/JCO.2007.13.4452. [DOI] [PubMed] [Google Scholar]
- 16.Demetri GD, van Oosterom AT, Garrett CR, et al. Efficacy and safety of sunitinib in patients with advanced gastrointestinal stromal tumour after failure of imatinib: a randomised controlled trial. Lancet. 2006;368(9544):1329–38. doi: 10.1016/S0140-6736(06)69446-4. [DOI] [PubMed] [Google Scholar]
- 17.Demetri GD, Reichardt P, Kang YK, et al. GRID Study Investigators Efficacy and safety of regorafenib for advanced gastrointestinal stromal tumours after failure of imatinib and sunitinib (GRID): an international, multicentre, randomised, placebo-controlled, phase 3 trial. Lancet. 2013;381(9863):295–302. doi: 10.1016/S0140-6736(12)61857-1. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 18.Llovet JM, Ricci S, Mazzaferro V, et al. SHARP Investigators Study Group Sorafenib in advanced hepatocellular carcinoma. N Engl J Med. 2008;359(4):378–90. doi: 10.1056/NEJMoa0708857. [DOI] [PubMed] [Google Scholar]
- 19.Chapman PB, Hauschild A, Robert C, et al. BRIM-3 Study Group Improved survival with vemurafenib in melanoma with BRAF V600E mutation. N Engl J Med. 2011;364(26):2507–16. doi: 10.1056/NEJMoa1103782. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 20.Sun C, Wang L, Huang S, et al. Reversible and adaptive resistance to BRAF(V600E) inhibition in melanoma. Nature. 2014;508(7494):118–22. doi: 10.1038/nature13121. [DOI] [PubMed] [Google Scholar]
- 21.Ribas A, Gonzalez R, Pavlick A, et al. Combination of vemurafenib and cobimetinib in patients with advanced BRAF(V600)-mutated melanoma: a phase 1b study. Lancet Oncol. 2014;15(9):954–65. doi: 10.1016/S1470-2045(14)70301-8. [DOI] [PubMed] [Google Scholar]
- 22.Larkin J, Ascierto PA, Dréno B, et al. Combined vemurafenib and cobimetinib in BRAF-mutated melanoma. N Engl J Med. 2014;371(20):1867–76. doi: 10.1056/NEJMoa1408868. [DOI] [PubMed] [Google Scholar]
- 23.Amaria RN, Kim KB. Dabrafenib for the treatment of melanoma. Expert Opin Pharmacother. 2014;15(7):1043–50. doi: 10.1517/14656566.2014.909410. [DOI] [PubMed] [Google Scholar]
- 24.Hauschild A, Grob JJ, Demidov LV, et al. Dabrafenib in BRAF-mutated metastatic melanoma: a multicentre, open-label, phase 3 randomised controlled trial. Lancet. 2012;380(9839):358–65. doi: 10.1016/S0140-6736(12)60868-X. [DOI] [PubMed] [Google Scholar]
- 25.Robert C, Karaszewska B, Schachter J, et al. Improved overall survival in melanoma with combined dabrafenib and trametinib. N Engl J Med. 2015;372(1):30–9. doi: 10.1056/NEJMoa1412690. [DOI] [PubMed] [Google Scholar]
- 26.Hotta K, Kato Y, Leighl N, et al. Magnitude of the benefit of progression-free survival as a potential surrogate marker in phase 3 trials assessing targeted agents in molecularly selected patients with advanced non-small cell lung cancer: systematic review. PLoS One. 2015;10(3):e0121211. doi: 10.1371/journal.pone.0121211. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 27.Maemondo M, Inoue A, Kobayashi K, et al. North-East Japan Study Group Gefitinib or chemotherapy for non-small-cell lung cancer with mutated EGFR. N Engl J Med. 2010;362(25):2380–8. doi: 10.1056/NEJMoa0909530. [DOI] [PubMed] [Google Scholar]
- 28.Mitsudomi T, Morita S, Yatabe Y, et al. West Japan Oncology Group Gefitinib versus cisplatin plus docetaxel in patients with non-small-cell lung cancer harbouring mutations of the epidermal growth factor receptor (WJTOG3405): an open label, randomised phase 3 trial. Lancet Oncol. 2010;11(2):121–8. doi: 10.1016/S1470-2045(09)70364-X. [DOI] [PubMed] [Google Scholar]
- 29.Wu YL, Zhou C, Hu CP, et al. Afatinib versus cisplatin plus gemcitabine for first-line treatment of Asian patients with advanced non-small-cell lung cancer harbouring EGFR mutations (LUX-Lung 6): an open-label, randomised phase 3 trial. Lancet Oncol. 2014;15(2):213–22. doi: 10.1016/S1470-2045(13)70604-1. [DOI] [PubMed] [Google Scholar]
- 30.Yang JC, Wu YL, Schuler M, et al. Afatinib versus cisplatin-based chemotherapy for EGFR mutation-positive lung adenocarcinoma (LUX-Lung 3 and LUX-Lung 6): analysis of overall survival data from two randomised, phase 3 trials. Lancet Oncol. 2015;16(2):141–51. doi: 10.1016/S1470-2045(14)71173-8. [DOI] [PubMed] [Google Scholar]
- 31.Pérol M, Chouaid C, Pérol D, et al. Randomized, phase III study of gemcitabine or erlotinib maintenance therapy versus observation, with predefined second-line treatment, after cisplatin-gemcitabine induction chemotherapy in advanced non-small-cell lung cancer. J Clin Oncol. 2012;30(28):3516–24. doi: 10.1200/JCO.2011.39.9782. [DOI] [PubMed] [Google Scholar]
- 32.Shepherd FA, Rodrigues Pereira J, Ciuleanu T, et al. National Cancer Institute of Canada Clinical Trials Group Erlotinib in previously treated non-small-cell lung cancer. N Engl J Med. 2005;353(2):123–32. doi: 10.1056/NEJMoa050753. [DOI] [PubMed] [Google Scholar]
- 33.Kawaguchi T, Ando M, Asami K, et al. Randomized phase III trial of erlotinib versus docetaxel as second- or third-line therapy in patients with advanced non-small-cell lung cancer: Docetaxel and Erlotinib Lung Cancer Trial (DELTA) J Clin Oncol. 2014;32(18):1902–8. doi: 10.1200/JCO.2013.52.4694. [DOI] [PubMed] [Google Scholar]
- 34.Shaw AT, Kim DW, Nakagawa K, et al. Crizotinib versus chemotherapy in advanced ALK-positive lung cancer. N Engl J Med. 2013;368(25):2385–94. doi: 10.1056/NEJMoa1214886. [DOI] [PubMed] [Google Scholar]
- 35.Solomon BJ, Mok T, Kim DW, et al. PROFILE 1014 Investigators First-line crizotinib versus chemotherapy in ALK-positive lung cancer. N Engl J Med. 2014;371(23):2167–77. doi: 10.1056/NEJMoa1408440. [DOI] [PubMed] [Google Scholar]
- 36.Shaw AT, Kim DW, Mehra R, et al. Ceritinib in ALK-rearranged non-small-cell lung cancer. N Engl J Med. 2014;370(13):1189–97. doi: 10.1056/NEJMoa1311107. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 37.Eskander RN, Tewari KS. Incorporation of anti-angiogenesis therapy in the management of advanced ovarian carcinoma–mechanistics, review of phase III randomized clinical trials, and regulatory implications. Gynecol Oncol. 2014;132(2):496–505. doi: 10.1016/j.ygyno.2013.11.029. [DOI] [PubMed] [Google Scholar]
- 38.du Bois A, Floquet A, Kim JW, et al. Incorporation of pazopanib in maintenance therapy of ovarian cancer. J Clin Oncol. 2014;32(30):3374–82. doi: 10.1200/JCO.2014.55.7348. [DOI] [PubMed] [Google Scholar]
- 39.Moore MJ, Goldstein D, Hamm J, et al. National Cancer Institute of Canada Clinical Trials Group Erlotinib plus gemcitabine compared with gemcitabine alone in patients with advanced pancreatic cancer: a phase III trial of the National Cancer Institute of Canada Clinical Trials Group. J Clin Oncol. 2007;25(15):1960–6. doi: 10.1200/JCO.2006.07.9525. [DOI] [PubMed] [Google Scholar]
- 40.Raymond E, Dahan L, Raoul JL, et al. Sunitinib malate for the treatment of pancreatic neuroendocrine tumors. N Engl J Med. 2011;364(6):501–13. doi: 10.1056/NEJMoa1003825. [DOI] [PubMed] [Google Scholar]
- 41.Motzer RJ, Hutson TE, Tomczak P, et al. Sunitinib versus interferon alfa in metastatic renal-cell carcinoma. N Engl J Med. 2007;356(2):115–24. doi: 10.1056/NEJMoa065044. [DOI] [PubMed] [Google Scholar]
- 42.Escudier B, Eisen T, Stadler WM, et al. TARGET Study Group Sorafenib in advanced clear-cell renal-cell carcinoma. N Engl J Med. 2007;356(2):125–34. doi: 10.1056/NEJMoa060655. [DOI] [PubMed] [Google Scholar]
- 43.Sternberg CN, Davis ID, Mardiak J, et al. Pazopanib in locally advanced or metastatic renal cell carcinoma: results of a randomized phase III trial. J Clin Oncol. 2010;28(6):1061–8. doi: 10.1200/JCO.2009.23.9764. [DOI] [PubMed] [Google Scholar]
- 44.Motzer RJ, Hutson TE, Cella D, et al. Pazopanib versus sunitinib in metastatic renal-cell carcinoma. N Engl J Med. 2013;369(8):722–31. doi: 10.1056/NEJMoa1303989. [DOI] [PubMed] [Google Scholar]
- 45.Motzer RJ, Escudier B, Tomczak P, et al. Axitinib versus sorafenib as second-line treatment for advanced renal cell carcinoma: overall survival analysis and updated results from a randomised phase 3 trial. Lancet Oncol. 2013;14(6):552–62. doi: 10.1016/S1470-2045(13)70093-7. [DOI] [PubMed] [Google Scholar]
- 46.Kasper B, Sleijfer S, Litière S, et al. Long-term responders and survivors on pazopanib for advanced soft tissue sarcomas: subanalysis of two European Organisation for Research and Treatment of Cancer (EORTC) clinical trials 62043 and 62072. Ann Oncol. 2014;25(3):719–24. doi: 10.1093/annonc/mdt586. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 47.van der Graaf WT, Blay JY, Chawla SP, et al. EORTC Soft Tissue and Bone Sarcoma Group, PALETTE Study Group Pazopanib for metastatic soft-tissue sarcoma (PALETTE): a randomised, double-blind, placebo-controlled phase 3 trial. Lancet. 2012;379(9829):1879–86. doi: 10.1016/S0140-6736(12)60651-5. [DOI] [PubMed] [Google Scholar]
- 48.Wells SA, Jr, Robinson BG, Gagel RF, et al. Vandetanib in patients with locally advanced or metastatic medullary thyroid cancer: a randomized, double-blind phase III trial. J Clin Oncol. 2012;30(2):134–41. doi: 10.1200/JCO.2011.35.5040. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 49.Elisei R, Schlumberger MJ, Müller SP, et al. Cabozantinib in progressive medullary thyroid cancer. J Clin Oncol. 2013;31(29):3639–46. doi: 10.1200/JCO.2012.48.4659. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 50.Brose MS, Nutting CM, Jarzab B, et al. DECISION Investigators Sorafenib in radioactive iodine-refractory, locally advanced or metastatic differentiated thyroid cancer: a randomised, double-blind, phase 3 trial. Lancet. 2014;384(9940):319–28. doi: 10.1016/S0140-6736(14)60421-9. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 51.Schlumberger M, Tahara M, Wirth LJ, et al. Lenvatinib versus placebo in radioiodine-refractory thyroid cancer. N Engl J Med. 2015;372(7):621–30. doi: 10.1056/NEJMoa1406470. [DOI] [PubMed] [Google Scholar]
- 52.Lacouture ME. Mechanisms of cutaneous toxicities to EGFR inhibitors. Nat Rev Cancer. 2006;6(10):803–12. doi: 10.1038/nrc1970. [DOI] [PubMed] [Google Scholar]
- 53.Hayman SR, Leung N, Grande JP, Garovic VD. VEGF inhibition, hypertension, and renal toxicity. Curr Oncol Rep. 2012;14(4):285–94. doi: 10.1007/s11912-012-0242-z. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 54.Izzedine H, Ederhy S, Goldwasser F, et al. Management of hypertension in angiogenesis inhibitor-treated patients. Ann Oncol. 2009;20(5):807–15. doi: 10.1093/annonc/mdn713. [DOI] [PubMed] [Google Scholar]
- 55.Dirix LY, Maes H, Sweldens C. Treatment of arterial hypertension (AHT) associated with angiogenesis inhibitors. Ann Oncol. 2007;18(6):1121–2. doi: 10.1093/annonc/mdm205. [DOI] [PubMed] [Google Scholar]
- 56.Lin Y, Wang X, Jin H. EGFR-TKI resistance in NSCLC patients: mechanisms and strategies. Am J Cancer Res. 2014;4(5):411–35. [PMC free article] [PubMed] [Google Scholar]
- 57.Naka K, Hoshii T, Muraguchi T, et al. TGF-beta-FOXO signalling maintains leukaemia-initiating cells in chronic myeloid leukaemia. Nature. 2010;463(7281):676–80. doi: 10.1038/nature08734. [DOI] [PubMed] [Google Scholar]
- 58.Lin L, Bivona TG. Mechanisms of resistance to epidermal growth factor receptor inhibitors and novel therapeutic strategies to overcome resistance in NSCLC patients. Chemother Res Pract. 2012;2012:817297. doi: 10.1155/2012/817297. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 59.Gainor J. O10.1 Next generation ALK inhibitors and mechanisms of resistance to therapy. Ann Oncol. 2015;26(suppl 2):ii14. [Google Scholar]
- 60.Lito P, Rosen N, Solit DB. Tumor adaptation and resistance to RAF inhibitors. Nat Med. 2013;19(11):1401–9. doi: 10.1038/nm.3392. [DOI] [PubMed] [Google Scholar]
- 61.Gao B, Yeap S, Clements A, Balakrishnar B, Wong M, Gurney H. Evidence for therapeutic drug monitoring of targeted anticancer therapies. J Clin Oncol. 2012;30(32):4017–25. doi: 10.1200/JCO.2012.43.5362. [DOI] [PubMed] [Google Scholar]
- 62.Dematteo RP, Ballman KV, Antonescu CR, et al. American College of Surgeons Oncology Group (ACOSOG) Intergroup Adjuvant GIST Study Team Adjuvant imatinib mesylate after resection of localised, primary gastrointestinal stromal tumour: a randomised, double-blind, placebo-controlled trial. Lancet. 2009;373(9669):1097–104. doi: 10.1016/S0140-6736(09)60500-6. [DOI] [PMC free article] [PubMed] [Google Scholar]
- 63.Cappuzzo F, Ciuleanu T, Stelmakh L, et al. Erlotinib as maintenance treatment in advanced non-small-cell lung cancer: a multicentre, randomised, placebo-controlled phase 3 study. Lancet Oncol. 2010;11(6):521–9. doi: 10.1016/S1470-2045(10)70112-1. [DOI] [PubMed] [Google Scholar]
- 64.de Wit D, Guchelaar HJ, den Hartigh J, Gelderblom H, van Erp NP. Individualized dosing of tyrosine kinase inhibitors: are we there yet? Drug Discov Today. 2015;20(1):18–36. doi: 10.1016/j.drudis.2014.09.007. [DOI] [PubMed] [Google Scholar]